
What It Actually Is
Nursing Checklist Quick is a streamlined documentation and safety tool used primarily in acute care settings to standardize routine assessments, medication verification, and shift handoffs. The whole point is cutting down the time nurses spend on paperwork while still catching the things that matter. Most places implement it as a digital form on a tablet or workstation on wheels, though some units still rely on laminated paper versions. I learned about these during my second year as a charge nurse when our hospital switched from handwritten flow sheets to a tablet-based system. The transition was rough. Half the unit figured it out by Friday, the other half spent three weeks tapping the wrong fields. But once it clicked, the difference was noticeable. Medication errors due to missed verification steps dropped by about 40% on my floor within six months.
Getting Started With Nursing Checklist Quick
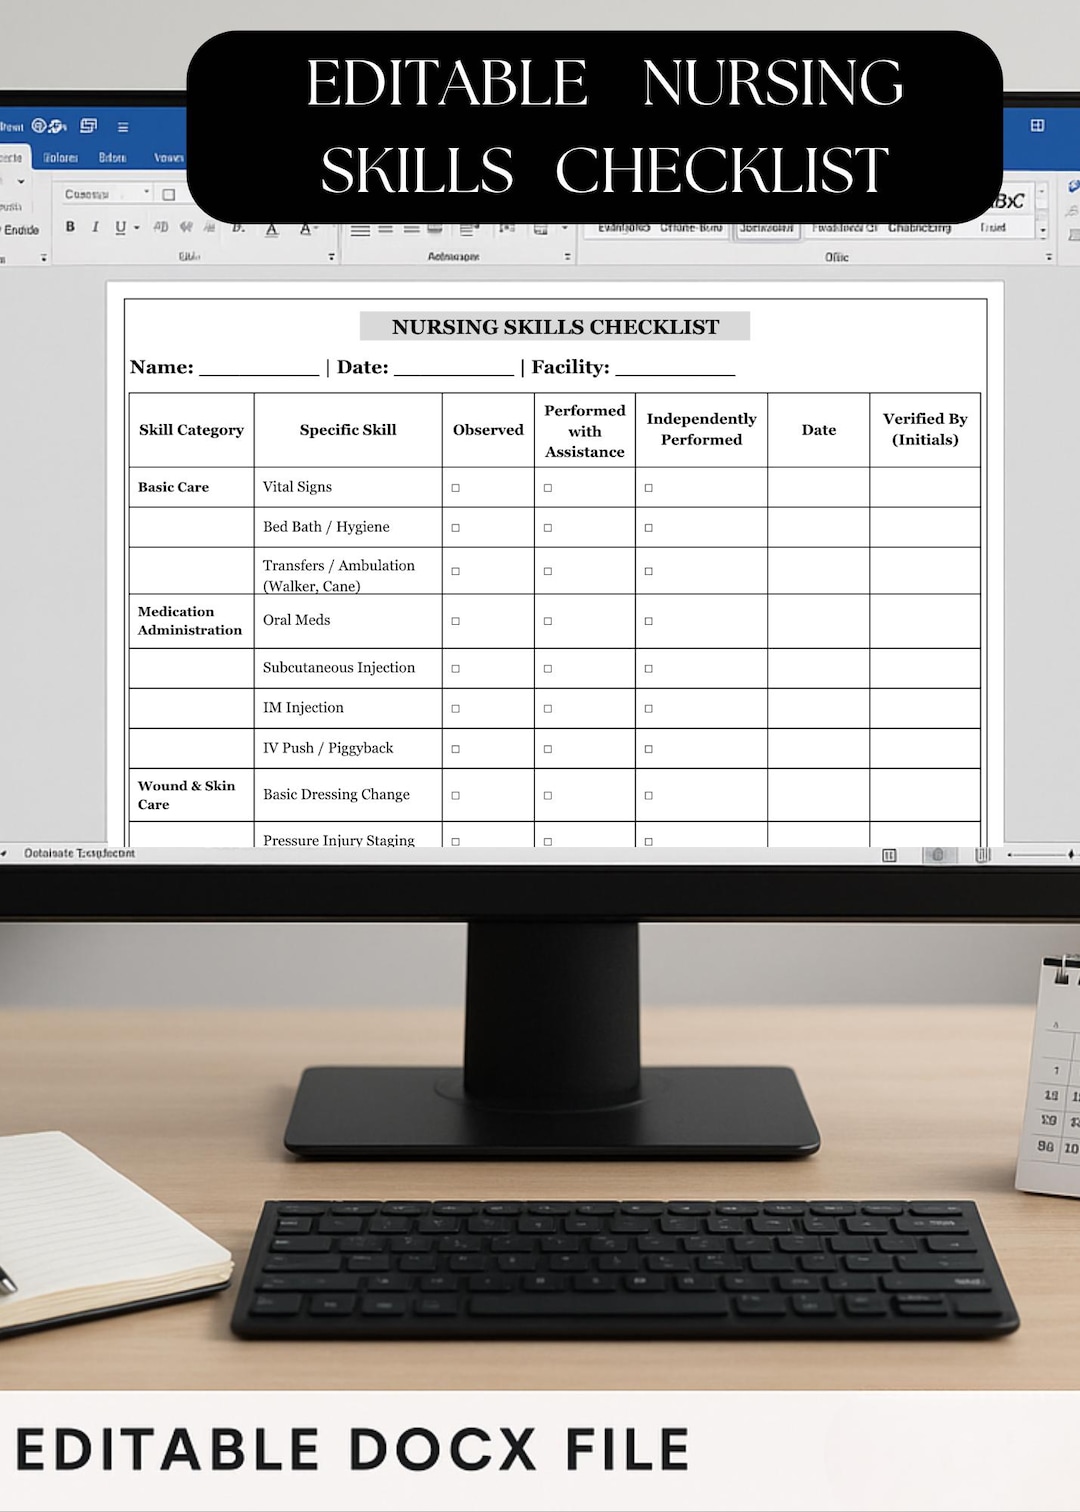
If you're setting this up for your unit, don't just hand everyone a login and walk away. I've seen that happen at two different hospitals. The first time it was installed, three nurses had their accounts locked because they couldn't remember the password reset procedure, and a full shift went by where someone had to print out paper copies as a backup. That takes twenty minutes to set up properly and maybe forty-five to train the staff without rushing through it. Start by mapping the exact workflow for each type of checklist you'll need. Bedside vital sign checks. Fall risk assessments. Pressure injury staging documentation. Post-operative observation rounds. Write those down on a whiteboard before touching any software. I learned that the hard way when our IT department preloaded a form that asked for pain scores in the first section, but every nurse on my unit did pain assessment last during their head-to-toe. That mismatch caused more frustration than anything else and almost got the whole thing pulled by admin after two weeks. Once the workflow is mapped, customize the forms to match actual practice, not theoretical best practice. This means removing fields that nobody uses and grouping questions in the order nurses actually think. A lot of vendors push templates that look comprehensive but are basically unusable in a real shift because they force you to scroll through forty fields for something that should take thirty seconds.
The Parts People Usually Get Wrong
The biggest mistake I see is treating the checklist as a compliance checkbox rather than a clinical decision aid. When nurses just sign through items without actually assessing the patient, you get complete data and zero clinical value. I caught this happening on my floor when I noticed someone was consistently selecting "no issues" on fall risk sections for patients who clearly needed assistance with ambulation. They were clicking through between conversations with families. Fixed it by adding mandatory notes for any positive finding, which forced at least a sentence of documentation before moving forward. Another common failure point is not adjusting the checklist for different patient populations. A post-surgical ortho patient needs different observation criteria than a med-surg cardiac patient, but a lot of units run the same template for everyone to keep things simple. Simplicity kills accuracy here. I recommended splitting our forms by unit type and patient acuity, and that reduced irrelevant questions by about sixty percent while improving completion accuracy.
Get the Full Details
Where It Falls Apart
These tools have real limitations. They don't work well during mass casualty events or code situations because the interface wasn't built for speed under extreme pressure. I was on a trauma call last year where we had eight patients arrive simultaneously, and trying to document anything through the checklist system wasted valuable minutes. We switched to paper backups immediately and entered everything later. No shame in that. Paper is faster when you need raw speed, and the checklist system is better for steady-state routine work where accuracy matters more than velocity. System downtime is another issue. When the network goes down or the EHR integrates poorly with the checklist platform, you're stuck. Our last outage took four hours, and we completed over two hundred patient assessments by hand. It worked, but it was slower and more error-prone. Make sure your unit has a documented fallback procedure before you rely on these checklists as your primary tool. There's also the training gap to consider. New grads sometimes treat the checklist as a crutch instead of a supplement to their clinical judgment. I had a nurse recently graduate who would stop her assessment the moment she hit the last field on the form, even if something looked off during the earlier questions. The checklist had flagged a potential pressure injury, but she moved on because the field already had a "none noted" selection. She needed a second round of training on how to use the tool as a framework, not a replacement for looking at the patient.
Download and Implementation
Depending on which EHR platform your facility uses, Nursing Checklist Quick may already be available through your hospital's internal portal. If you're looking for a standalone version or a customizable template, check with your nursing informatics team first because most regions require institutional approval before deploying new clinical tools. Some private vendors offer free starter versions with paid upgrades for advanced features like barcode medication scanning integration or real-time alerting to supervisors when critical findings are documented. If you're building this from scratch for your own unit, I'd suggest starting with a simple spreadsheet structure that mirrors your current workflow, then migrating to a proper digital system once you've validated which fields actually matter. That approach saved us roughly six weeks of rework when we finally moved to the tablet-based platform. The fields we'd already identified as useful transferred cleanly, and the ones we'd figured out were useless got cut before anyone had to learn them.



