What Actually Matters When You're Managing a Patient on Tamsulosin
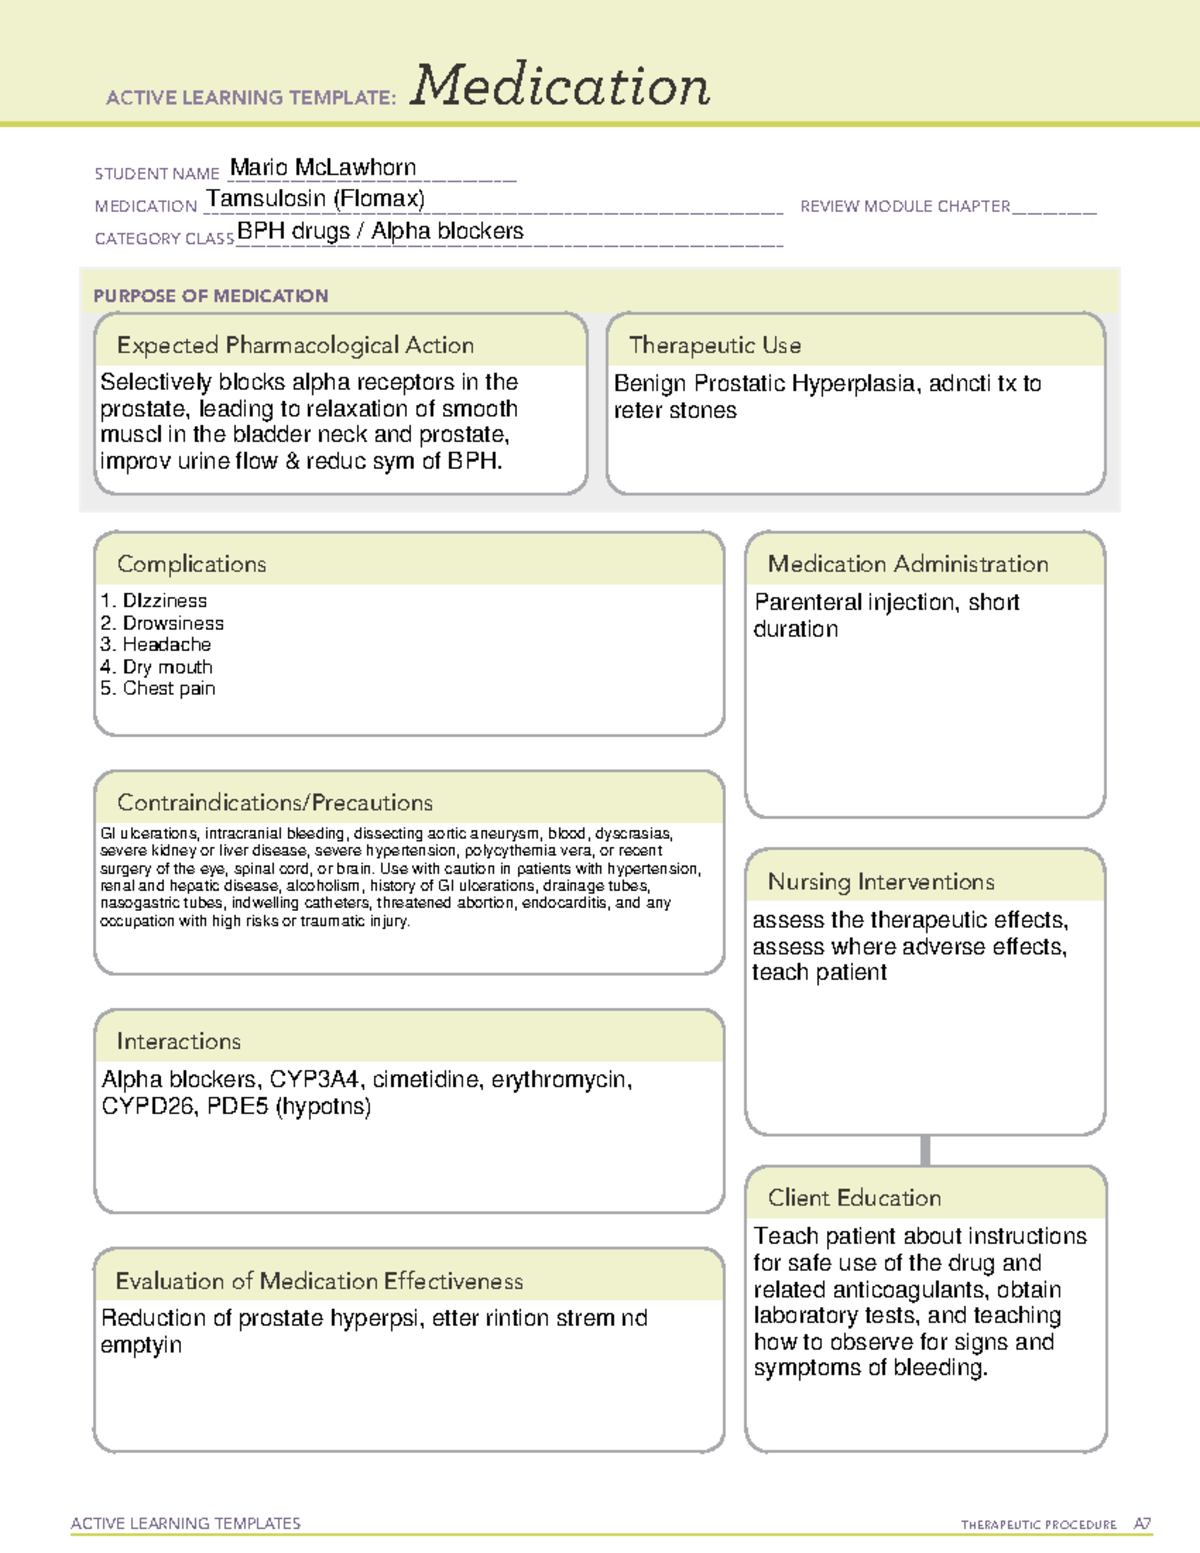
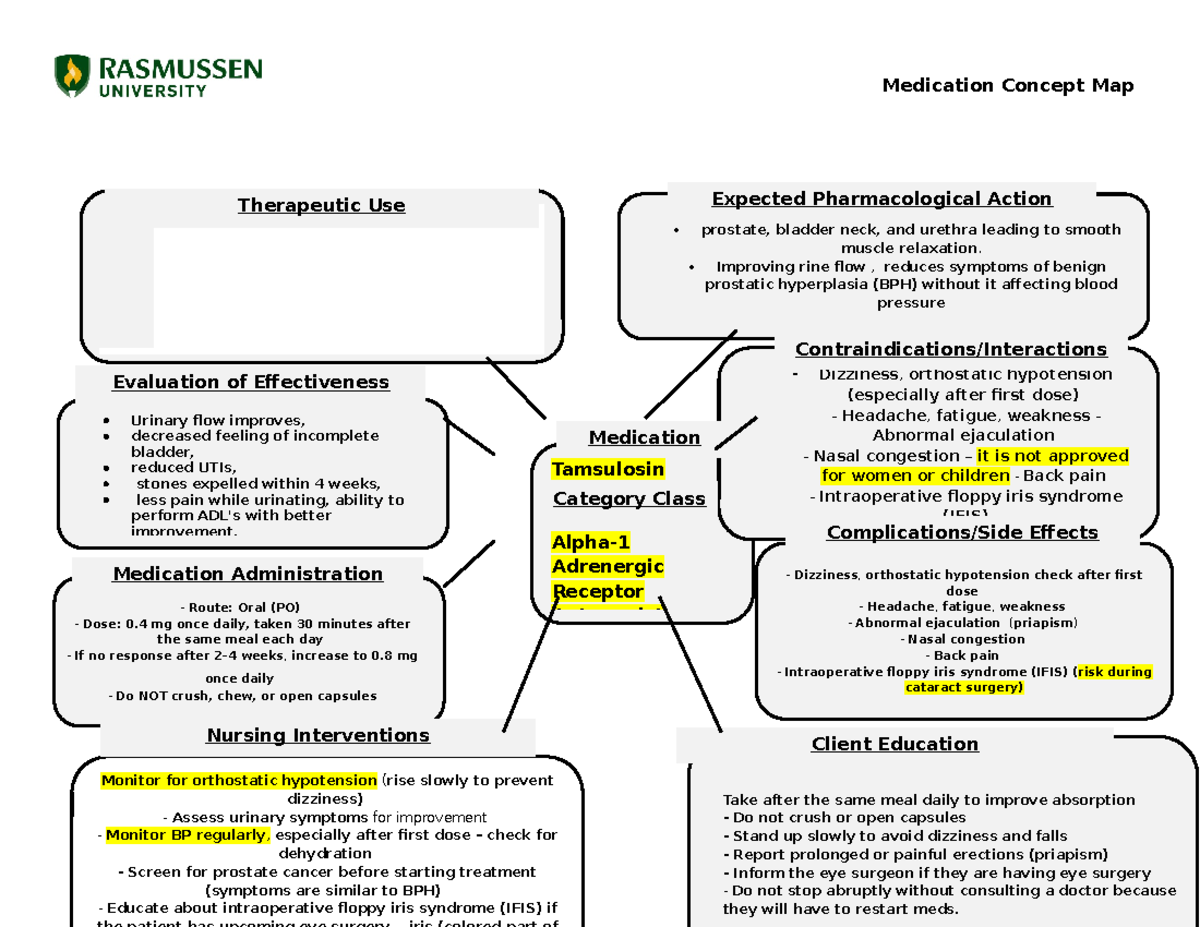
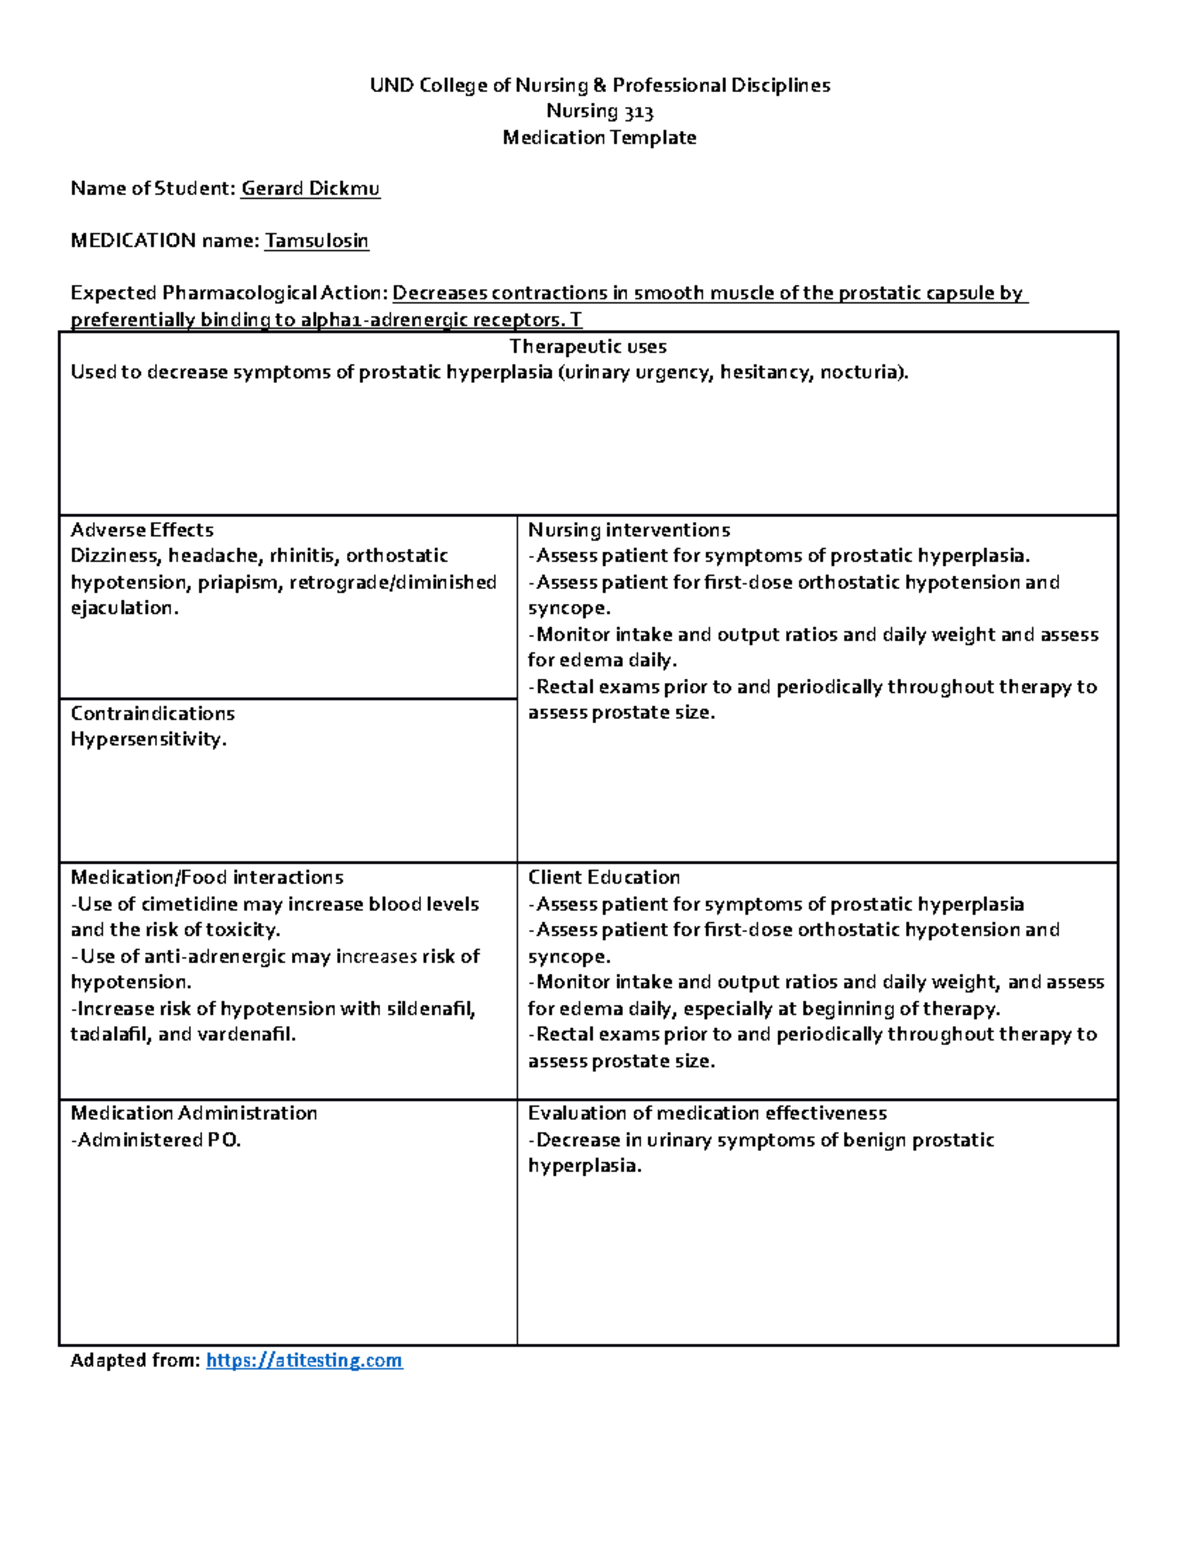
Tamsulosin is a selective alpha-1a adrenergic antagonist, meaning it targets the prostate and bladder neck specifically rather than hitting every alpha receptor in the body. That selectivity is the whole point. In practice, it's prescribed most often for benign prostatic hyperplasia, and sometimes off-label for kidney stones to help with passage. The nursing work around it is straightforward if you know where the traps are. The package insert lists orthostatic hypotension as the primary concern. It doesn't lead with the fact that first-dose syncope happens more often than most nurses realize, especially in elderly men who are already volume-depleted or on other antihypertensives. I had a patient in his late seventies who dropped his systolic to 80 after his very first dose at 2100 hours. He was sitting on the edge of the bed when it happened. He'd been on doxazosin before and we'd switched him to tamsulosin thinking the selectivity would make a difference. It did, somewhat, but not enough. The workaround was simple but easy to miss: hold the dose, keep him supine with legs elevated, give a 250 mL bolus of normal saline if the protocol allows, and restart the next morning with a strict recalculation of his other antihypertensives. We also moved the dose to right before bedtime going forward, which reduces the chance of falls during waking hours. Here's something most people don't think about: tamsulosin is highly protein-bound, around 94 percent. That matters when you're dealing with malnourished patients or those with low albumin. Less protein means more free drug in the system, which means more vasodilation and more hypotension risk at standard doses. I've seen two instances where patients with albumin below 2.5 had profound dizziness on what should have been a routine 0.4 mg daily dose. In both cases, we held the medication and got urology involved. The dose wasn't adjusted downward formally, but the clinical response made it obvious that the standard dosing wasn't appropriate for those physiologies. Document the albumin. Mention it in the handoff. It's not in the nursing drug guide usually, but it changes the risk profile significantly.
Monitoring and Documentation That Actually Prevents Problems
Blood pressure checks before administration are table stakes. The trick is knowing what baseline to expect. If the patient's sitting systolic is in the low 110s and their diastolic is in the high 60s, you're not looking at a hypertensive patient who needs to come down. You're looking at someone who might actually faint when the smooth muscle relaxes. I check orthostatics on any patient over 65 who's starting tamsulosin, and I do it during my med pass, not just at admission. The numbers at 0900 are different from the numbers at 1500, and by 1500 most nurses are already running behind and skipping the second check. Don't skip it. Urinary retention is the paradox you need to watch for. Tamsulosin relaxes the bladder neck and prostate capsule, which should improve flow. But in some patients, particularly those with significant detrusor weakness or chronic retention, the relaxation can actually reduce the closing pressure enough that the bladder doesn't empty efficiently. I saw this in a patient who was switched from finasteride plus tamsulosin to tamsulosin monotherapy after his PSA normalized. His post-void residuals went from 80 mL to 350 mL over three days. The discharge planner was already scheduling his follow-up with urology for two weeks out. I flagged it to the attending, they ordered a straight cath once, confirmed the retention, and moved the urology follow-up up to five days. The nurse on the next shift would have missed it entirely because the patient was voiding regularly, just incompletely.
Drug Interactions That Come Up More Than You'd Expect
CYP3A4 inhibitors are the main interaction to know about. Ketoconazole, itraconazole, clarithromycin — these can increase tamsulosin levels significantly. I don't mean a little bit. I mean clinically significant increase. There was a patient who was on chronic tamsulosin for BPH and was started on fluconazole for a fungal infection. His blood pressure dropped over four days and he became intermittently confused from poor cerebral perfusion. We caught it because I was already tracking his orthostatics daily after the first fall scare with another patient. The fluconazole was discontinued and switched to a non-interacting alternative per pharmacy recommendation. Other antihypertensives compound the effect. This is obvious but worth stating plainly: a patient on a beta-blocker and an ACE inhibitor who gets added to tamsulosin is asking for a symptomatic hypotensive event. The synergy isn't additive, it's multiplicative. I calculate a rough MAP target for these patients — keep it above 65. If the math doesn't work out, you flag it before the first dose goes in. Warfarin interaction is another one that comes up. Tamsulosin can displace warfarin from protein binding sites and slightly increase the INR. It's not a dramatic effect, but in a patient whose INR was already therapeutic at 2.5, it can push them to 3.2 without any other change. Check the INR within three to five days of initiating tamsulosin in anyone on warfarin. Not everyone does this. It's a quiet way to get a preventable bleed event.
Get the Full Details
Patient Education That Actually Sticks
The standard advice is "take it after a meal" and "stand up slowly." Patients forget both things within a week. The evidence is that food affects absorption timing more than extent, but the clinical symptom is real. I tell patients to take it right after their evening meal, not at bedtime on an empty stomach. The food blunts the peak concentration slightly and spreads it out. More importantly, they're already horizontal within two hours, which means if they do get dizzy, they're not walking to the bathroom at 0200. I also make sure they understand that this medication doesn't fix the prostate. It relaxes the smooth muscle around it. The prostate is still enlarged. The improvement in flow is real, but it's mechanical, not curative. Patients who think they're cured often stop taking it when they feel better, then come back three weeks later with acute retention. I document that conversation. I also ask them to repeat it back to me in their own words, not because I don't trust them, but because I've seen too many patients nod along and then stop the medication because they felt fine. There's also the matter of intraoperative floppy iris syndrome. Any patient on tamsulosin who needs cataract surgery needs to be flagged to the ophthalmologist before the procedure. The drug causes the iris sphincter to relax in a way that makes the surgeon's job much harder. This isn't something that shows up on a standard medication reconciliation unless you're specifically looking for it. I keep a running list of patients on alpha-blockers who have scheduled eye appointments, and I flag them during every handoff. The ophthalmology team will adjust their surgical technique if they know, but they can't if they find out during the procedure.
When It Doesn't Work and What to Do About It
About 15 to 20 percent of patients don't respond adequately to tamsulosin alone. They get some improvement in flow, but not enough to avoid symptoms. In these cases, the combination with a 5-alpha reductase inhibitor like finasteride is the evidence-based next step. The combination takes longer to work — up to six months for the finasteride component — but it addresses the underlying gland enlargement rather than just the smooth muscle tone. I've seen residents miss this because they see a patient complain about ongoing symptoms after four weeks and think the drug failed. It hasn't failed yet. The finasteride hasn't had time to work. The patient needs to stay on it for at least three months before any judgment is made. Side effects that lead to discontinuation are usually ejaculatory dysfunction and nasal congestion. Both are common and both are dose-related. If a patient stops the medication because of these issues, that's a real problem. The genitourinary symptoms return and the cycle starts again. I've had conversations with patients where we accepted the side effect as the cost of not needing a catheter. That's not always the right call, but it's a conversation that needs to happen before the patient silently stops taking the drug and comes back to the ER with retention. Tamsulosin isn't a perfect drug. It doesn't work for everyone, it interacts with common medications, and it has a side effect profile that patients often don't report unless you specifically ask. But when you know how to monitor it properly and when to escalate, it's a genuinely useful tool in the outpatient management of lower urinary tract symptoms from BPH. The nursing work is mostly vigilance — blood pressure, hydration status, protein levels, drug interactions, and making sure the patient actually understands what they're taking and why. Do those things consistently and the complications stay rare.