Actual nursing diagnosis approach for anemia patients
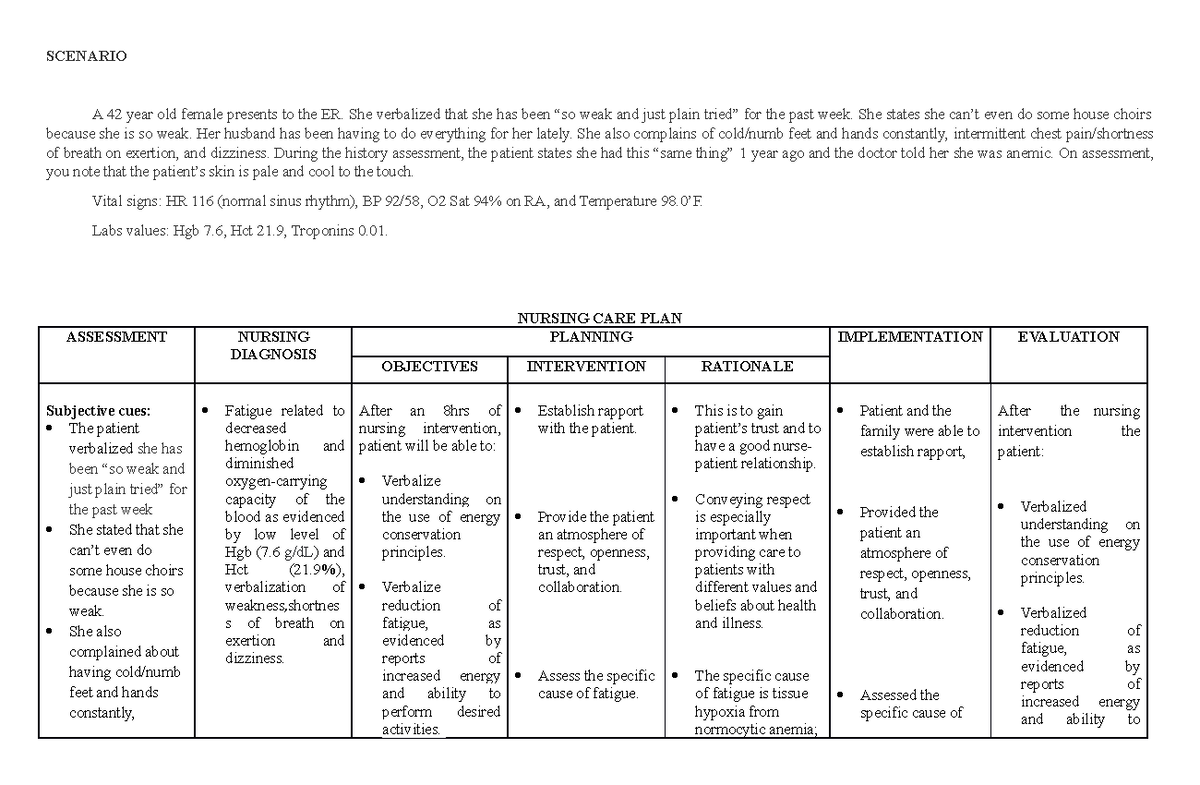
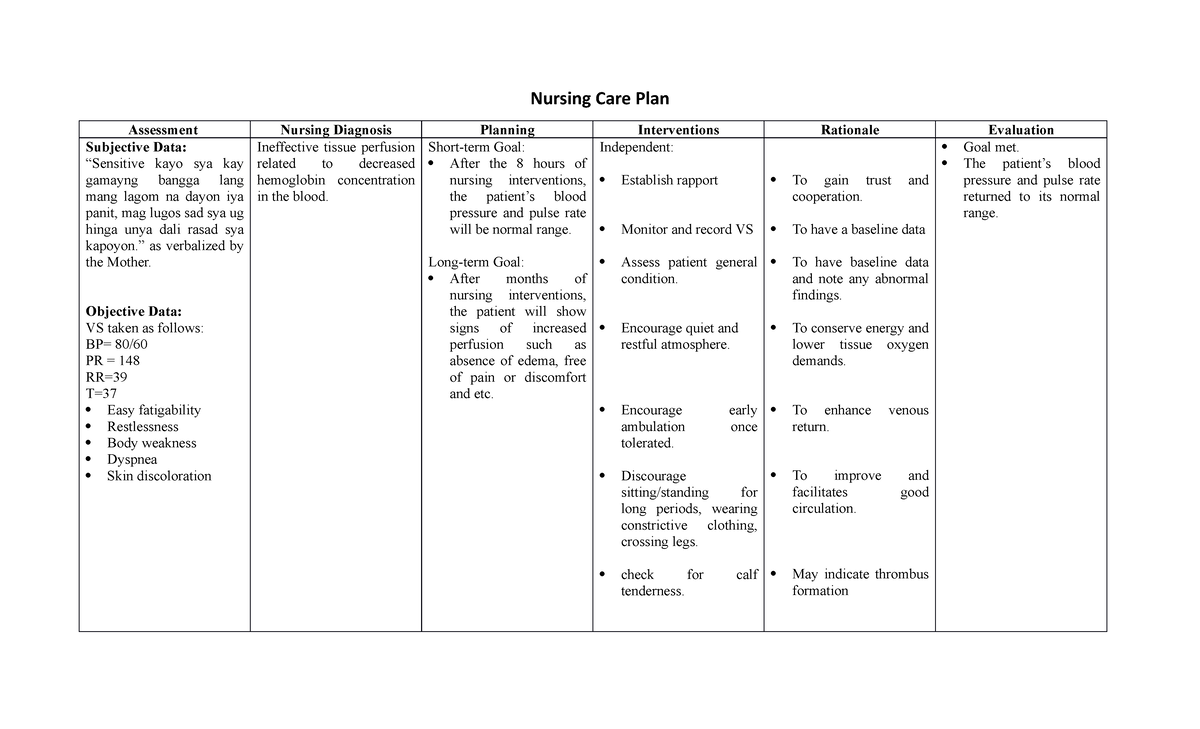
I spent about six years working med-surg and oncology units before moving into case management. Anemia patients show up constantly across both settings, and they are often understaffed to because nurses write "deficient knowledge" or "fatigue" as the primary diagnosis without actually assessing what's going on. The difference between a passable assessment and a useful one comes down to how you frame the nursing diagnosis and whether you're tracking the right data points. The PES format (Problem, Etiology, Signs/Symptoms) is what most nursing programs teach, but it's applied carelessly here. A correct statement looks like: Imbalanced Nutrition: Less Than Body Requirements related to inadequate iron intake and chronic blood loss as evidenced by hemoglobin of 8.2 g/dL, ferritin of 12 ng/mL, and patient report of dietary restrictions due to cost. That last piece — the etiology — is where most students and new grads trip up. They link the problem to the lab value itself rather than to the underlying cause. The lab value is the evidence (S in PES), not the cause. Common nursing diagnoses for anemia patients include:
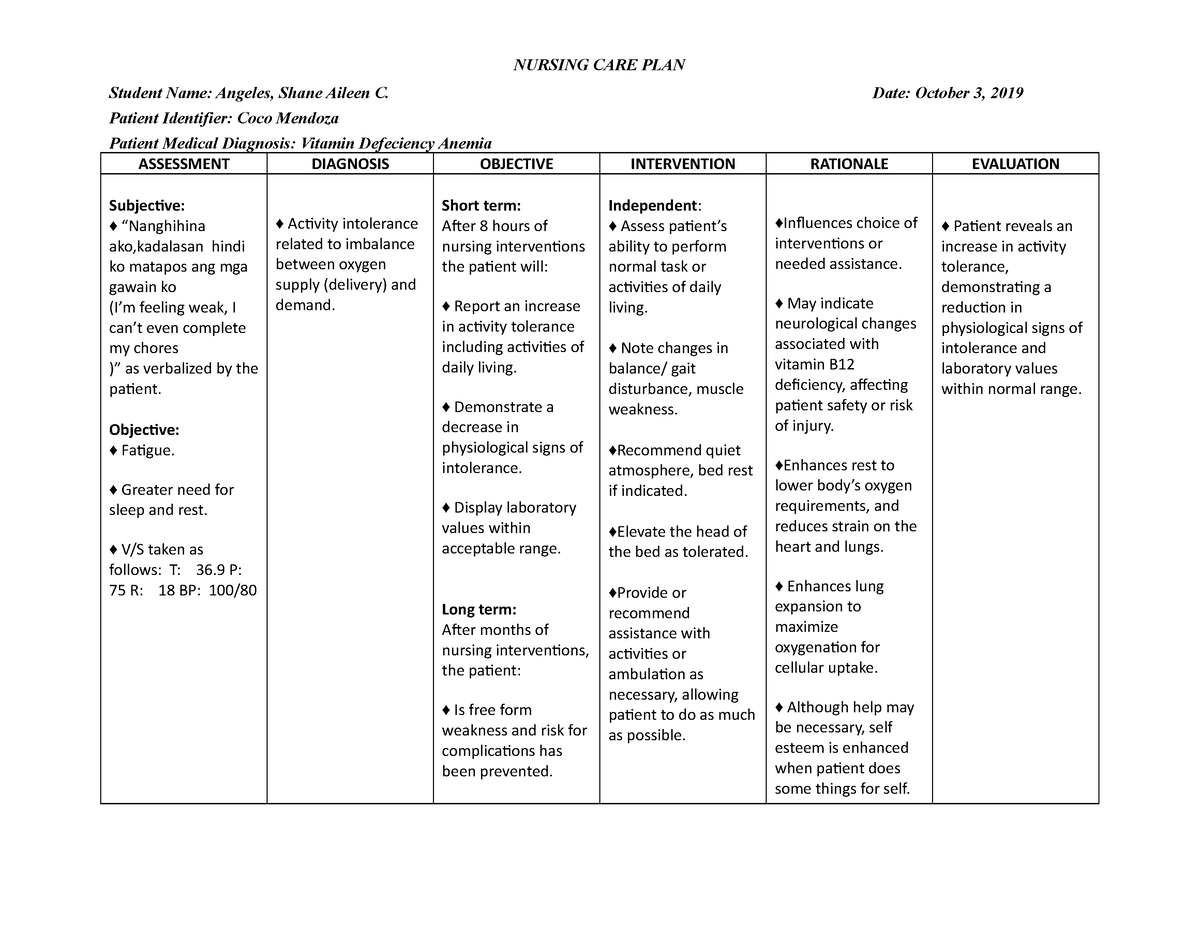
Fatigue related to inadequate oxygen delivery to tissues as evidenced by reports of exhaustion, resting heart rate of 98 bpm, and diminished activity tolerance. This is the most frequent one. It sounds obvious but most care plans attached to it are useless because they don't specify measurable goals. Instead of "patient will report increased energy," write "patient will ambulate 50 feet with one rest stop by day 3." Specificity matters for outcomes and for getting your plan of care approved during chart audits. Activity Intolerance related to imbalance between oxygen supply and demand. Different from fatigue in that it has a physiological basis you can tie directly to hemoglobin levels. A patient at 7.8 g/dL isn't being lazy when they can't climb stairs. Recognizing this distinction changes your interventions from "encourage rest" to something that actually maps to the physiology. Deficient Fluid Volume — rare in anemia specifically, but relevant if the anemia is acute hemorrhagic. I've seen this misapplied to chronic iron deficiency cases where fluid volume is completely normal. Don't conflate low hemoglobin with dehydration. They are separate problems that happen to coexist sometimes.
When I worked oncology, we had a patient — mid-sixties, female, breast cancer on AC-T regimen — who kept sliding into symptomatic anemia with hemoglobins in the 7-to-8 range. The standard transfusion trigger wasn't being met, and the fatigue diagnosis wasn't moving the needle. What actually worked was reframing it as Imbalanced Nutrition: Less Than Body Requirements with the etiology tied specifically to chemotherapy-induced anorexia combined with increased metabolic demand from the malignancy. We pulled in dietitian consults earlier, started oral nutritional supplements with iron fortification, and monitored weight trends weekly instead of monthly. Her hemoglobin stabilized around 8.5 and her functional status improved enough that she completed her full cycle. The lab numbers alone never told the whole story. The nutrition angle did.
Get the Full Details

Assessment priorities most people skip
Checking hemoglobin and hematocrit is baseline. If that's all you're doing, you're under-assessing. Look at the RDW, MCHC, platelet count, and reticulocyte count. These tell you whether the anemia is microcytic, macrocytic, normocytic, or hemolytic, and each category gets a completely different care plan. Iron deficiency typically shows low MCV and high RDW. B12 or folate deficiency shows high MCV. Hemolytic anemias may show elevated reticulocytes and low haptoglobin. Getting this wrong leads to supplementing iron in a patient who actually needs B12, which delays the real treatment and wastes time and money. Also assess for tachycardia, systolic flow murmurs, conjunctival pallor, and nail bed capillary refill. These are quick bedside indicators that correlate reasonably well with symptomatic severity. A patient with a hemoglobin of 9 who is tachycardic at rest and has a flow murmur is more symptomatic than a patient at 8.2 who feels fine. The number on the page isn't the whole picture. Functional status and compensatory mechanisms matter more for determining urgency than a single lab value. Don't forget to ask about bleeding sources. Menstrual history, GI bleeding symptoms, anticoagulant use, and recent surgeries. Post-menopausal bleeding or hematochezia in an elderly patient should immediately raise flags for GI malignancy. I once had a case where the primary team was focused entirely on treating the anemia with IV iron and transfusions, missing a colon mass that was the actual cause. The nursing assessment caught it because the patient mentioned dark stools three days into admission. The medical team hadn't asked. That's not a criticism of doctors — it's a reminder that nurses spend more continuous time with patients and hear things that don't make it into the formal history and physical.
Interventions that actually help
Iron supplementation routes matter. Oral iron causes constipation and nausea in roughly 30 to 50 percent of patients, and compliance drops off sharply after two weeks. If you're writing "administer oral iron" as the sole intervention, expect it to fail in a significant number of cases. The workaround is co-prescribing a stool softener, suggesting take-orbit supplements every other day instead of daily (recent studies show better absorption with alternate-day dosing due to hepcidin regulation), and scheduling a follow-up hemoglobin check at two weeks to assess response before escalating to IV iron. IV iron is appropriate when oral fails or when rapid repletion is needed — postpartum hemorrhage, active GI bleeding, or patients on hemodialysis. The typical response is a hemoglobin rise of 1 to 2 g/dL within two to four weeks. Monitor for hypophosphatemia with ferric carboxymaltose specifically, which can be asymptomatic but clinically relevant over time. Educational interventions need to be concrete. "Eat iron-rich foods" is not an intervention. "Include one serving of red meat or fortified cereal daily and pair with vitamin C sources to enhance absorption" is. Take-away materials with specific meal examples work better than verbal instructions alone, especially for patients with limited health literacy.
Energy conservation techniques for the Fatigue diagnosis should include activity pacing strategies, not just "rest between activities." Teach patients to schedule demanding tasks for late morning when energy is typically highest, break ADLs into smaller segments, and prioritize rather than attempt everything in one day. Patients respond better when they understand the why behind pacing, so briefly explain the oxygen supply-demand relationship in plain language.
Pitfalls and what doesn't work
Writing multiple diagnoses without linking them to the primary problem creates a scattered care plan. If the etiology of the fatigue is anemia, then the fatigue and activity intolerance diagnoses are essentially the same problem viewed from different angles. Pick the one that drives the most actionable interventions and drop the others. Redundant diagnoses waste charting time and dilute focus during interdisciplinary rounds. Another common error is setting outcome criteria that the nurse cannot influence. "Patient will achieve hemoglobin of 12 g/dL" is a medical outcome, not a nursing outcome. The nurse administers iron and educates, but the bone marrow response depends on multiple factors outside nursing control. Set nursing outcomes like "patient will demonstrate correct iron supplementation technique by teaching back," "patient will identify three dietary sources of iron," or "patient will report using energy conservation strategies during ADLs by discharge." The biggest bottleneck I've seen is the lack of follow-up. Anemia care plans are often written at admission and never revisited. Check hemoglobin trends at minimum every 48 to 72 hours during the acute phase. If the expected response to intervention isn't happening, escalate — that's when you contact the provider about adjusting treatment or investigating alternative etiologies. Stagnant or declining labs despite appropriate therapy mean the diagnosis or the plan is incomplete.
Also be aware that lab values from different facilities may use different reference ranges. A hemoglobin of 10.5 might be considered mild anemia at one hospital and moderate at another depending on their protocols. Know your facility's transfusion and treatment thresholds and document them explicitly in the plan rather than assuming everyone reading the chart is on the same page.