Why We Miss the Real Problem on the Flats
Most nursing students treat a nursing diagnosis as a paperwork exercise. You tick the boxes, label the patient, and move on. In practice, that is where things go sideways fast. A wrong label means the wrong intervention, and wrong intervention with constipation means you are pushing harder on a broken system. I learned this the hard way during a night shift on a medical-surgical unit about six years ago. We had a post-op patient who was three days out from a colectomy. The chart read constipation. The doctor ordered more senna. I watched the nurse give it, the patient strain, and nothing come out. Then I realized we were looking at the wrong diagnosis entirely. The patient did not have simple constipation. He had an early fecal impaction sitting right there, just proximal to the surgical site. Giving stimulant laxatives to an impaction is like pressing your foot harder on a gas pedal when the car is already stuck in mud. It makes things worse. I flagged it, called the provider, and we switched to a disimpaction protocol with an enema and manual removal. The difference was immediate. That was the day I stopped skimming assessment data and started reading it properly. This is the gap most guides do not address. The label looks the same on paper but the clinical picture is completely different. Getting the diagnosis right changes everything about what you do next.
Nursing Diagnosis For Constipation: What It Actually Means in Practice
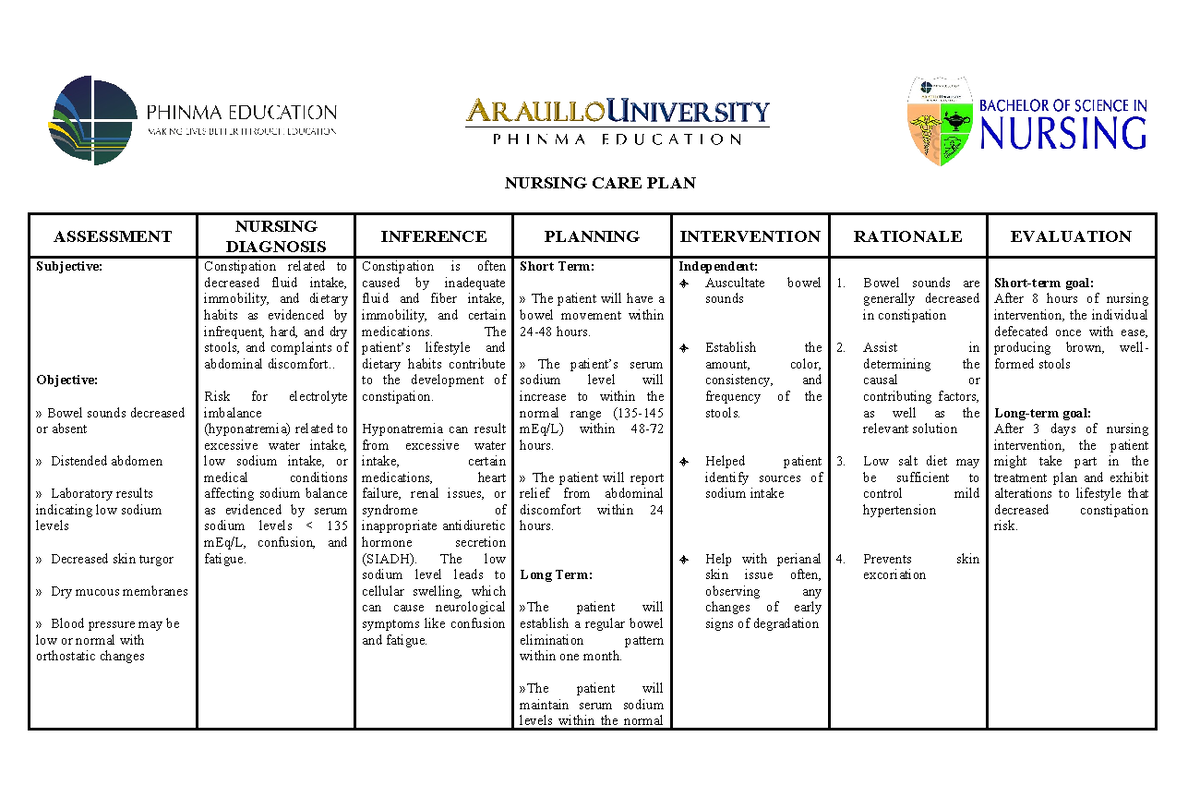
The NANDA-I definition for constipation involves a decrease in the normal frequency of defecation accompanied by the difficult or incomplete passage of stool. The diagnostic label is Constipation and it falls under the elimination and excretion domain. The defining characteristics are hard or compacted stool, reports of excessive straining, subjective sensation of incomplete evacuation, and a decreased frequency of bowel movements. The related factors are what actually drive the intervention choices. Here is the part nobody tells you clearly. Constipation and impaired bowel elimination are not interchangeable. Impaired bowel elimination is the broader category and covers irregularity, incontinence, and any bowel pattern that deviates from normal. Constipation is a specific subset. Using the broader label when the patient clearly meets constipation criteria dilutes your care plan and makes outcome tracking useless. You should be specific because specific leads to targeted interventions. Vague labels lead to vague treatment and that is where patients sit in their own stool for days because someone checked a box instead of doing the assessment.
The Assessment That Actually Matters
You cannot diagnose constipation from a single bowel movement count. The literature says fewer than three stools per week meets the frequency threshold, but that number alone is not enough. You need to build a picture across multiple data points. The first thing I check is stool consistency using the Bristol Stool Scale. Types one and two indicate constipation. Type one is separate hard lumps. Type two is lumpy and sausage shaped but still hard. If the patient is passing type three or four stools but complaining of incomplete evacuation, you are dealing with a different problem than if they are passing type one stools every four days. I also ask about straining. Not just whether they strain, but how long they strain and whether they use digito-rectal maneuvers. Patients will not volunteer that information unless you ask directly. A woman in her seventies once told me she had to press on her perineum to pass stool. That is a pelvic floor coordination issue, not simple constipation. The nursing diagnosis needs to reflect that nuance or you end up prescribing fiber and wonder why it does not work. Bowel sounds are part of the assessment but they are overrated. Hyperactive sounds do not rule out obstruction. Hypoactive sounds are common in constipation but also common in patients who are dehydrated and on opioids. I listen for twenty full minutes across all four quadrants before I write anything down. Thirty seconds is not an assessment. It is a guess. And guesses get people hurt on this unit.
Get the Full Details

Related Factors That Change Everything
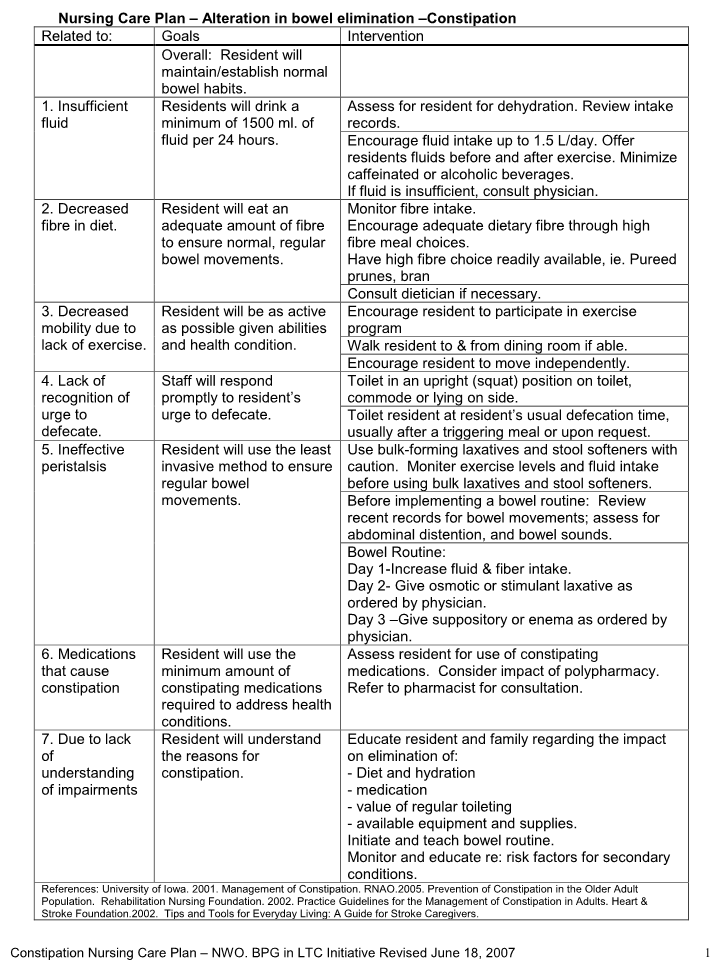
The related factors determine the outcome criteria and the interventions. Medications are the biggest driver in hospitalized patients. Opioids, anticholinergics, iron supplements, calcium channel blockers, and diuretics all slow colonic transit through different mechanisms. Opioids bind to mu-receptors in the gut wall. Iron precipitates in the colon. Anticholinergics reduce smooth muscle activity. When you know which drug is doing what, you can pick the right intervention instead of throwing polyethylene glycol at everything and hoping it sticks. Fluid intake is another factor that gets handled badly. Everyone says drink more water. That is correct but incomplete. A patient on bedrest who drinks more water but has no mobility and is on opioids will still be constipated. Water helps soften stool but it does not stimulate motility. You need both. I had a patient who drank two liters of water daily and still had type one stools because his mobility was zero and his morphine dose was high. We added a scheduled stimulant laxative, began assisted ambulation, and adjusted the fluid timing around medication administration. The stool pattern normalized in four days. Another factor people miss is the psychological component. Anxiety and depression slow gut motility through the gut-brain axis. A patient who is terrified of pain after abdominal surgery will voluntarily suppress the defecation reflex. The stool sits there, water gets absorbed, and it becomes harder. The diagnosis needs to include behavioral factors in those cases. Without that, you treat the symptom and ignore the cause.
What the Care Plan Actually Looks Like
The interventions should flow directly from the related factors. If the cause is medication-induced, the plan includes medication review and prophylactic bowel regimen. If the cause is low fluid intake, the plan includes hydration targets and monitoring. If the cause is immobility, the plan includes positioning, ambulation, and abdominal massage. For medication-induced constipation, the evidence supports a combination of a stimulant laxative and a stool softener. Docusate alone is weak. Senna or bisacodyl provides the motor stimulation. Polyethylene glycol draws water into the lumen osmotically. Using all three together is common in oncology and palliative care settings but it is overkill for most medical patients. Start with one stimulant and one osmotic agent. Escalate only if the response is inadequate after forty-eight hours. Dietary fiber is a double-edged sword. Soluble fiber from oats, apples, and psyllium absorbs water and forms a gel. Insoluble fiber from wheat bran and vegetables adds bulk. Both help but only if the patient is hydrated. I saw a patient given a high-fiber diet while drinking less than one liter of fluid per day. The fiber soaked up whatever water was available in the colon and made the stool harder. She went from a type three to a type one over two days. Fiber without fluid is constipation fuel. That is not a controversial statement. It is basic physiology. People forget it because the brochure always says eat more fiber.
Abdominal massage follows the anatomical path of the colon. Right lower quadrant up to the right upper quadrant, across the epigastrium, and down the left side. Ten to fifteen minutes clockwise. It is inexpensive, requires no equipment, and has moderate evidence behind it for improving stool frequency. It is also something patients can learn to do themselves. I had a male patient in his fifties who was discharged with nothing but a printed diagram and a fifteen-minute instruction. He called the clinic three days later saying it changed his life. That is not marketing language. That was an actual phone call.

When the Diagnosis Is Wrong
The biggest risk is misdiagnosing a partial bowel obstruction as simple constipation. The signs overlap significantly. Both present with decreased stool frequency and abdominal discomfort. The difference is vomiting, distension, and the character of the pain. Obstruction pain is often colicky and comes in waves. Constipation discomfort is a constant pressure. Vomiting is a red flag. Distension that does not resolve after a bowel movement is a red flag. If you see those, you stop treating constipation and you escalate. I once managed a patient who was treated for constipation for five days because the team only saw the stool frequency data. On day six, he started vomiting bilious material and his abdomen was visibly distended. A plain film showed a partial small bowel obstruction. He needed surgery. The five days of senna and enemas had delayed the correct diagnosis. The lesson is simple. Constipation is a working diagnosis, not a final one. If the patient does not respond to appropriate intervention within seventy-two hours, you reassess. You do not just add more laxatives.
Common Pitfalls in Documentation
The documentation needs to include the related factors, the defining characteristics, and the outcome criteria. Most charts I read have the diagnosis and maybe one or two related factors. That is insufficient. Future providers need to understand why the patient is constipated to make changes when the first line fails. Write the full three-part statement. It takes twenty seconds and it saves hours of confusion later. Another documentation error is recording stool frequency without recording consistency. Frequency without consistency is nearly meaningless. A patient passing a soft stool every other day is not constipated. A patient passing hard pellets daily is. The narrative note should describe the stool, not just the schedule.
Monitoring and Reassessment
Outcome monitoring for constipation should track stool frequency, consistency using the Bristol Scale, patient-reported ease of passage, and abdominal comfort. The time frame depends on the intervention. Osmotic laxatives like polyethylene glycol typically work within twenty-four to forty-eight hours. Stimulant laxatives act in six to twelve hours. Fiber supplements take two to three days. If you do not see improvement within the expected window, you reassess the diagnosis and the intervention, not just wait longer. I keep a simple bowel log for patients at risk. It tracks fluid intake, medication administration, stool characteristics, and any interventions attempted. The log is one page and it takes three minutes to update. It takes ten minutes to realize the pattern on a bad day. That data is worth more than any algorithm. The bottom line is that nursing diagnosis for constipation is not a label you apply and forget. It is a living assessment that guides every decision until the problem resolves or reveals itself as something else entirely. Get the diagnosis right, document the related factors, intervene based on the cause, and reassess if the response is not what you expected. Everything else is just paperwork.