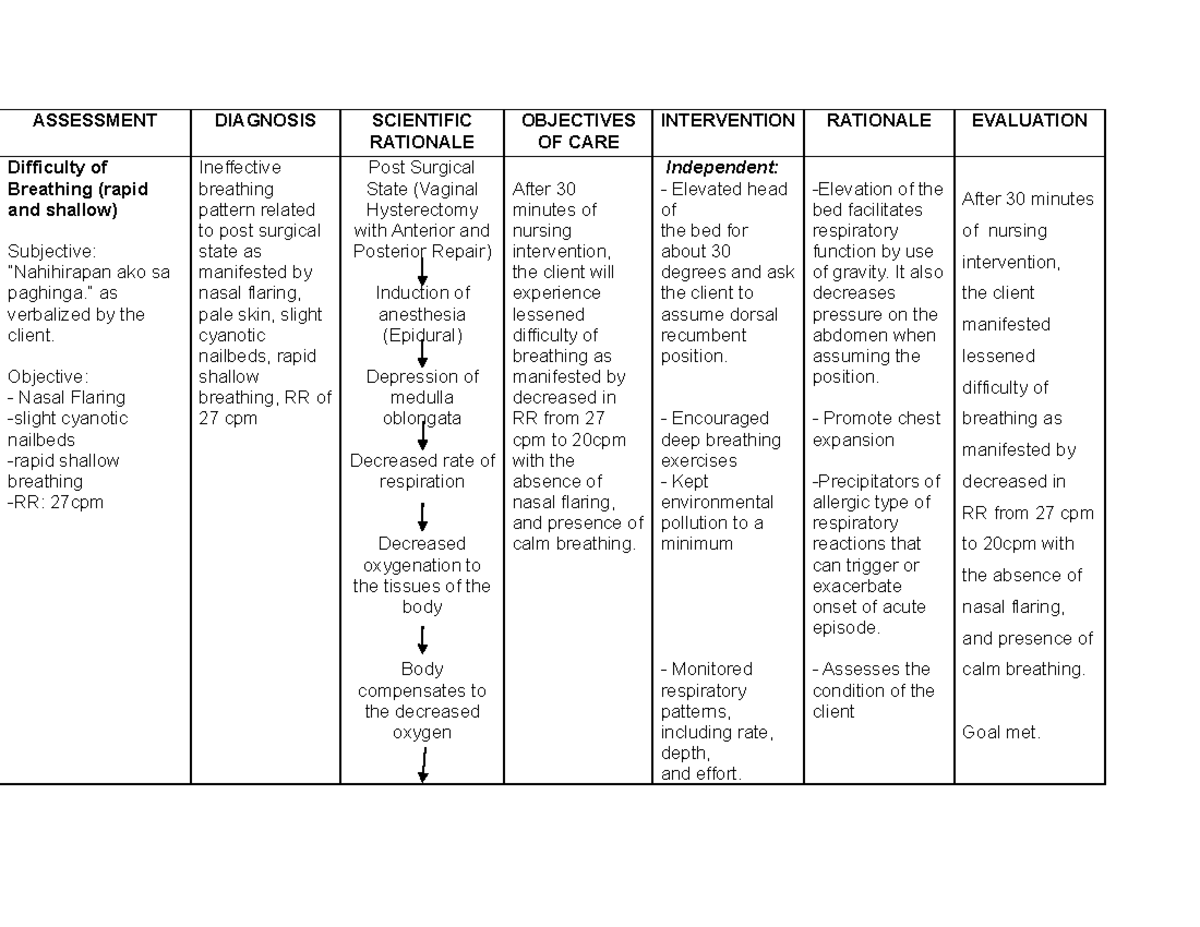
How to Actually Write a Nursing Diagnosis for Shortness of Breath Without Getting Flagged
Most nursing students and even some new nurses get this wrong. They write "Nursing Diagnosis Related To Shortness Of Breath" as if the symptom itself is the diagnosis. It's not. Shortness of breath is what the patient is experiencing. The diagnosis is what's happening underneath it. Here's how the NANDA-I framework actually maps to dyspnea.
Nursing Diagnosis Related To Shortness Of Breath: The Core Diagnoses
The primary NANDA-I diagnoses you'll use for a patient presenting with dyspnea are Ineffective Breathing Pattern, Impaired Gas Exchange, and Activity Intolerance. Each one addresses a different mechanism, and picking the wrong one shows up clearly on care plan reviews. Impaired Gas Exchange is defined as excess or deficit in oxygenation and/or carbon dioxide elimination at the alveolar-capillary membrane. The related factors here might be altered diffusion membranes, ventilation-perfusion ratios, or capillary blood volume. You'd see supporting evidence like abnormal ABGs, low SpO2 that doesn't respond proportionally to supplemental O2, changes in skin color, or tachycardia. This is your go-to for pneumonia, pulmonary embolism, ARDS, or significant COPD exacerbations where the actual gas swap at the alveoli is compromised. Ineffective Breathing Pattern relates to a state of inspiration and/or expiration that does not provide adequate ventilation. The related factors here are more about the mechanics and rhythm. Common causes include anxiety, pain, fatigue, neuromuscular impairment, or airway obstruction. The defining characteristics you look for are abnormal respiratory rate, depth, or rhythm; use of accessory muscles; nasal flaring; and patient-reported dyspnea. I've seen this misapplied to a post-op abdominal surgery patient who was genuinely splinting from incision pain. The breathing pattern was ineffective because of pain, not because of a primary respiratory problem. Labeling it purely as Impaired Gas Exchange when pain was the root driver led to interventions that missed the mark for days until someone connected the dots.
Activity Intolerance comes into play when there's an imbalance between oxygen supply and demand. The patient gets short of breath with minimal exertion. Related factors could be deconditioning, cardiovascular compromise, or generalized weakness. Defining characteristics include exaggerated heart rate or blood pressure response to activity, dyspnea with activity, and fatigue. This is the one that catches a lot of people off guard in elderly patients who aren't in acute respiratory distress at rest but can't walk to the bathroom without saturating down to 88 percent. There's also Anxiety related to dyspnea, which is a legitimate secondary diagnosis. The terror of not being able to breathe is real and it creates a feedback loop that makes the breathing pattern worse. Treating the gas exchange without addressing the anxiety component is like mopping the floor while the tap is still running.
Get the Full Details

How to Format It Properly
The standard PES format is Problem, Etiology, and Signs/Symptoms. You write it as: "Impaired Gas Exchange related to altered diffusion membranes as evidenced by SpO2 88 percent on room air, accessory muscle use, and ABG showing PaO2 of 58." Every component needs to be traceable to actual assessment data. I've reviewed care plans where the "evidenced by" section just said "shortness of breath." That's circular. The diagnosis can't be supported by the same symptom you're trying to diagnose. Pick measurable indicators. Vital signs, lab values, observable behaviors, patient statements. If you don't have objective data, the diagnosis doesn't hold up under scrutiny.
The Common Mistake That Wastes Hours
Here's a specific scenario I ran into last year. A patient with COPD came in with what looked like straightforward dyspnea. Everyone immediately wrote Impaired Gas Exchange. The ABGs were chronically elevated CO2, which was baseline for this patient. The real problem was Ineffective Breathing Pattern driven by anxiety and fatigue from a recent viral illness. We treated the gas exchange angle with O2 adjustments and nebulizers for two days with minimal improvement. What actually moved the needle was pacing interventions, breathing retraining with pursed-lip techniques, and addressing the anxiety. The oxygen saturation barely budged but the patient's work of breathing decreased significantly once the breathing pattern improved. The lesson is that dyspnea is multifactorial and the primary diagnosis depends on what's driving it in that specific moment. You can have more than one nursing diagnosis active simultaneously. In fact, you usually should. But the priority order matters clinically and it matters on paper during documentation reviews.
What Doesn't Work
Don't write "risk for" diagnoses based on shortness of breath alone unless there's a clear vulnerable population. Risk for Ineffective Breathing Pattern is valid for a post-thoracotomy patient. It's not valid for a general medical admission who happens to report being out of breath after climbing stairs. That's an actual problem, not a risk. Also avoid linking the etiology to a medical diagnosis without a nursing lens. "Ineffective Breathing Pattern related to heart failure" is a medical diagnosis masquerading as a nursing diagnosis. The nursing piece is the breathing pattern itself, the etiology should describe what's affecting the pattern, and the physician manages the heart failure. You manage the breathing pattern consequences. If you want a quick reference tool, most hospital systems have nursing diagnosis templates in their EHR. Flashcards for the PES format, NANDA-I approved labels, and common related factors for respiratory presentations are available through nursing education platforms. The NANDA-I taxonomy itself is subscription-based but many nursing schools provide access.
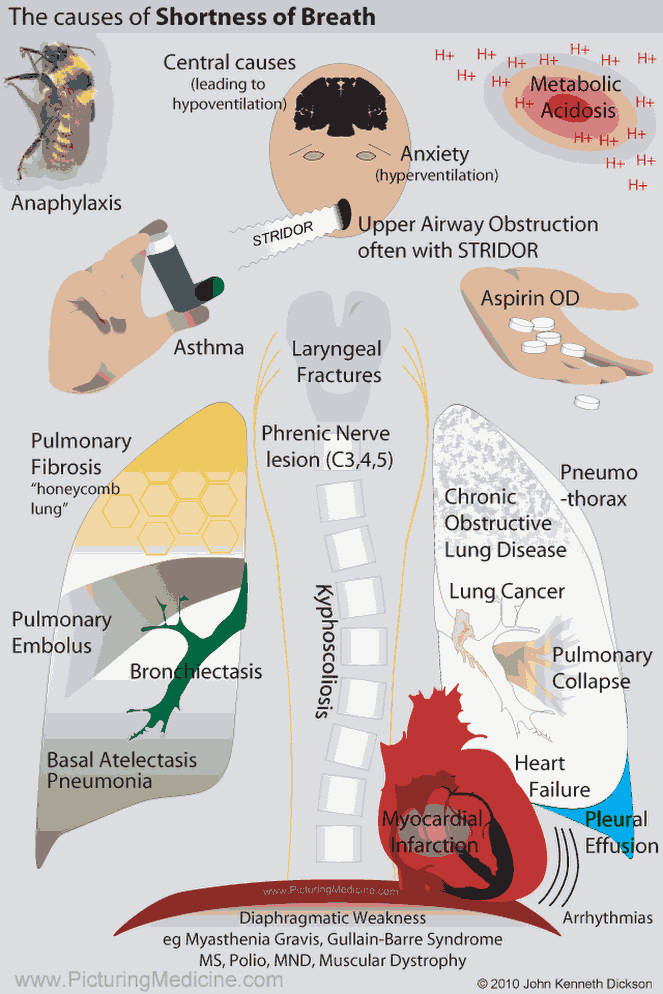
The bottom line is that shortness of breath is a symptom, not a diagnosis. Pinpoint the mechanism, support it with measurable evidence, and write it so another clinician can understand exactly what's wrong and why without guessing.



