Writing Nursing Diagnoses for Anemia Patients
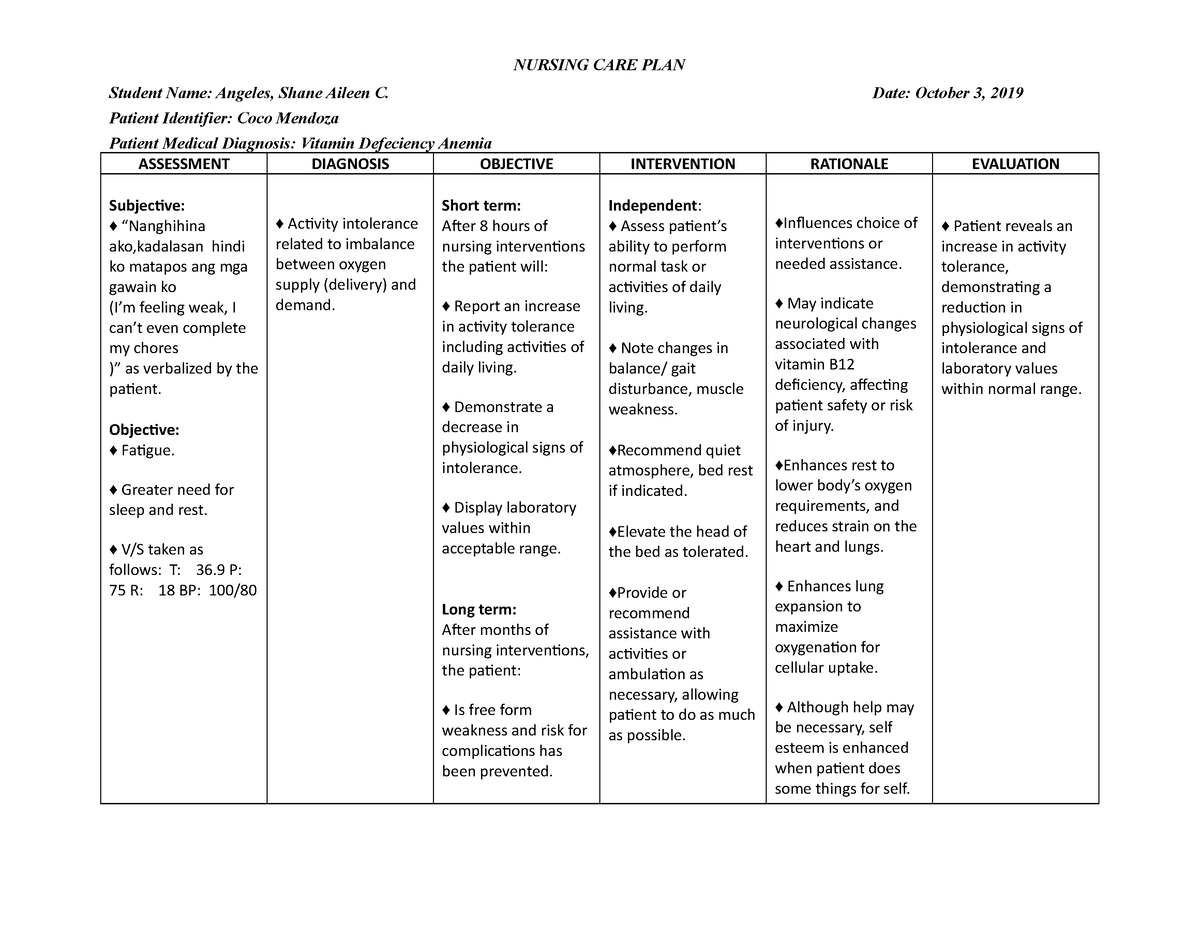
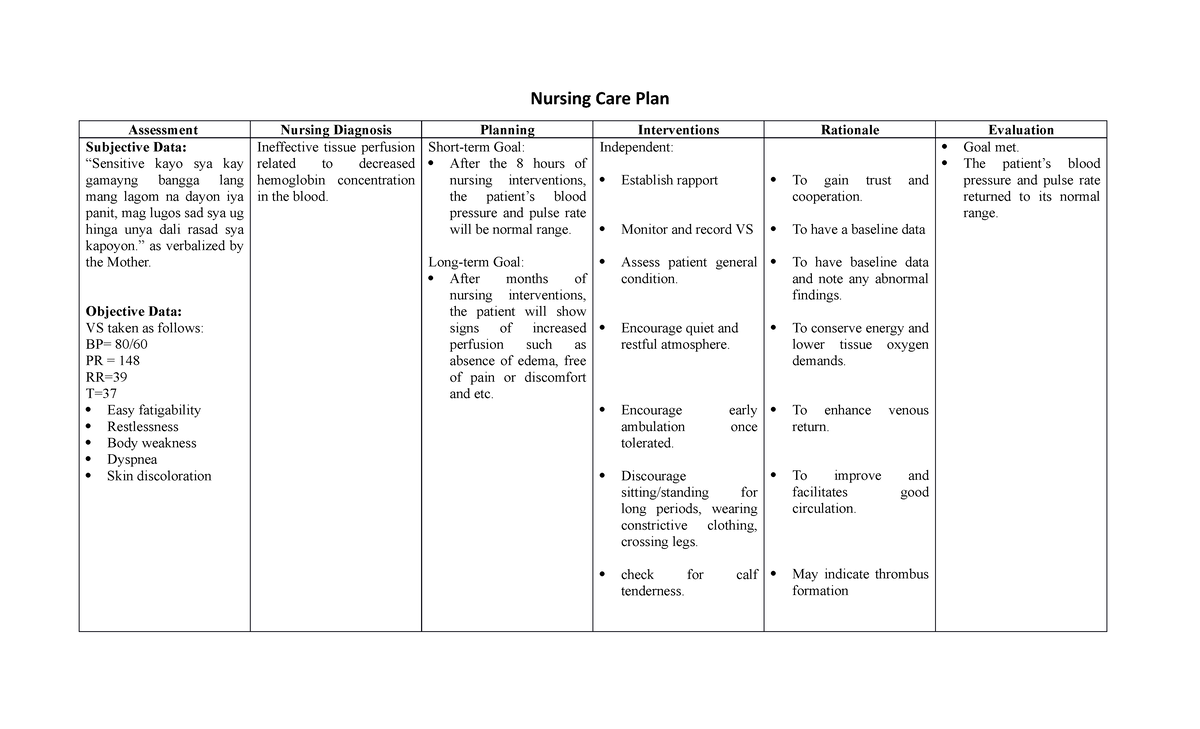
Anemia isn't one diagnosis. It's a lab value with a bunch of different downstream effects depending on what caused it, how fast it hit, and what the patient's baseline was. The nursing diagnosis you choose needs to match the actual problem the patient is presenting with, not just the number on the CBC. I see this go wrong all the time because people grab the first label that fits and move on. It matters which one you pick because it changes your outcome criteria and your interventions.Defining the problem first When I write Ineffective Tissue Perfusion for an anemic patient, I don't just note the hemoglobin. I tie it to concrete signs: resting heart rate of 108, O2 saturation dropping to 91% on ambulation from 97% at rest, complaints of dizziness with position changes, and a patient who can only walk 20 feet before needing to sit. The related factor is usually "decreased hemoglobin affecting oxygen-carrying capacity." The defining characteristics are what you actually observed. Without those specifics, the diagnosis is just a restatement of the medical diagnosis, which gives the care team nothing to act on. The Fatigue diagnosis works differently. It's not "tired because anemic." It's "self-care deficit in bathing and dressing related to generalized weakness secondary to decreased oxygen delivery as evidenced by patient requiring maximal assistance for ADLs and reporting inability to complete morning hygiene within expected timeframe." The intervention plan for that is completely different from tissue perfusion. One focuses on activity pacing and energy conservation. The other focuses on positioning, monitoring, and possibly blood product preparation.
One thing beginners consistently miss: Risk for Falls should be the primary diagnosis for elderly patients with hemoglobin below 8, regardless of whether you also write tissue perfusion. I learned this after a patient fell getting to the bathroom on day two of a transfusion protocol. We had documented ineffective tissue perfusion perfectly but hadn't flagged fall risk as a priority. The fall changed the entire trajectory of the stay. Now I always lead with it when the numbers support it. I also run into the same problem repeatedly with documentation timelines. You need to reassess the defining characteristics of any nursing diagnosis every shift for acute anemic patients. A hemoglobin of 7.2 in the morning might be 6.8 by evening if there's active bleeding. Your nursing diagnoses should reflect the current state, not the admission state. I use a quick bedside reassessment sheet — heart rate, blood pressure, O2 sat at rest and after walking the length of the room, level of consciousness, and skin color — that takes about four minutes and replaces the two-page narrative notes some people try to write. My unit went from spending roughly 45 minutes per shift on anemia-related documentation down to about eight minutes after we started using the sheet. There's a limitation to this approach that nobody talks about. When the patient is intubated or sedated, you can't use subjective defining characteristics like dizziness or fatigue. You're working with objective data only: tachycardia, hypotension, mottled skin, lactate levels, urine output. The nursing diagnosis still needs to exist, but your evidence base shrinks considerably. In those cases I default to Ineffective Tissue Perfusion with the related factor clearly stated as "mechanical ventilation and sedation limiting assessment of subjective symptoms." It's not ideal documentation, but it's accurate, and it tells the next nurse what to watch for once sedation lightens.
Another nuance that people overlook: iron supplementation changes the timeline for outcome evaluation. If the patient is on IV iron, you might see reticulocyte count rise in five to seven days and hemoglobin improve in two to four weeks. Oral iron takes longer and has much higher non-compliance rates due to GI side effects. Your nursing diagnosis outcomes need to match the treatment route. Writing "demonstrates improved hemoglobin within 48 hours" for someone starting oral ferrous sulfate sets them up for a failed outcome review no matter what you do. The workup for anemia-related nursing diagnoses should include understanding the patient's medication list. ACE inhibitors, NSAIDs, anticoagulants, metformin, PPIs — they all interact with anemia in ways that change the nursing focus. A patient on chronic NSAIDs with iron deficiency anemia has a different priority than someone whose anemia is purely nutritional. The diagnosis label might look similar, but the interventions diverge fast once you know what's driving it.
Get the Full Details