Writing Out a Foley Catheter Note Without Losing Your License
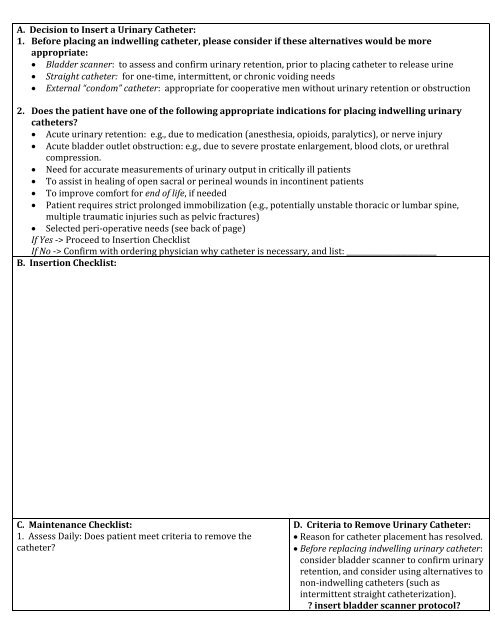
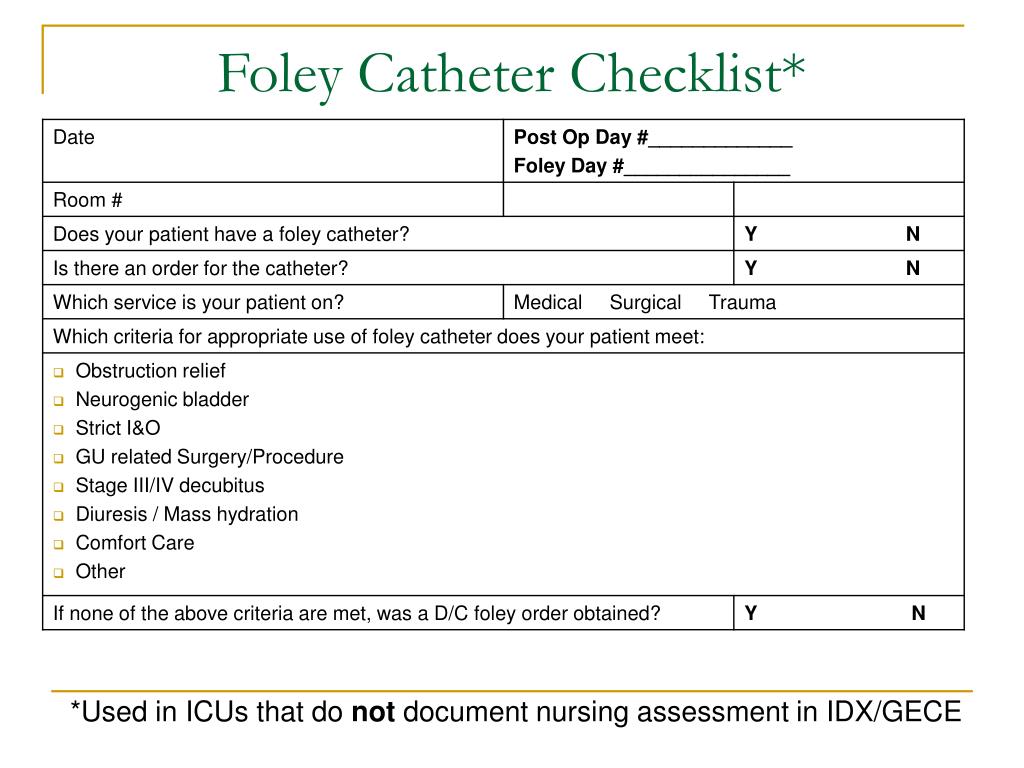
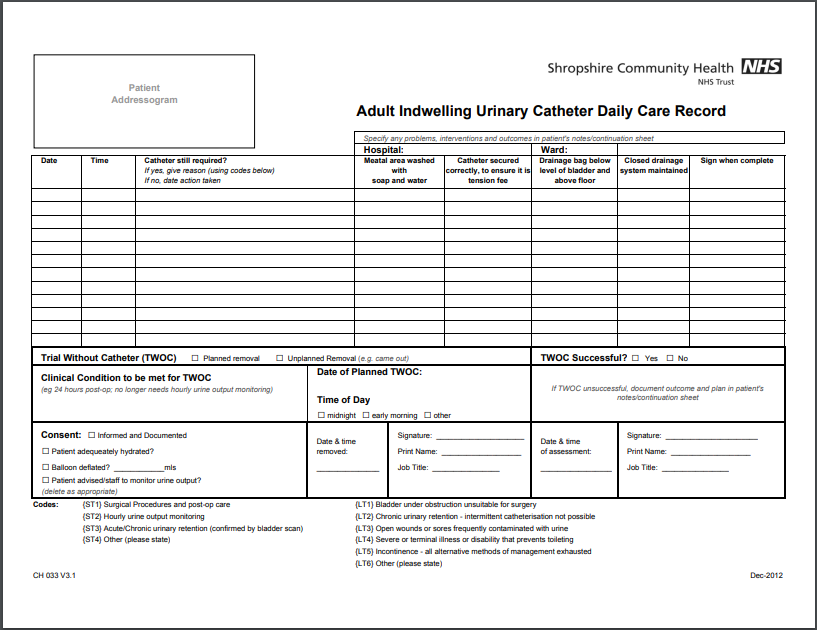
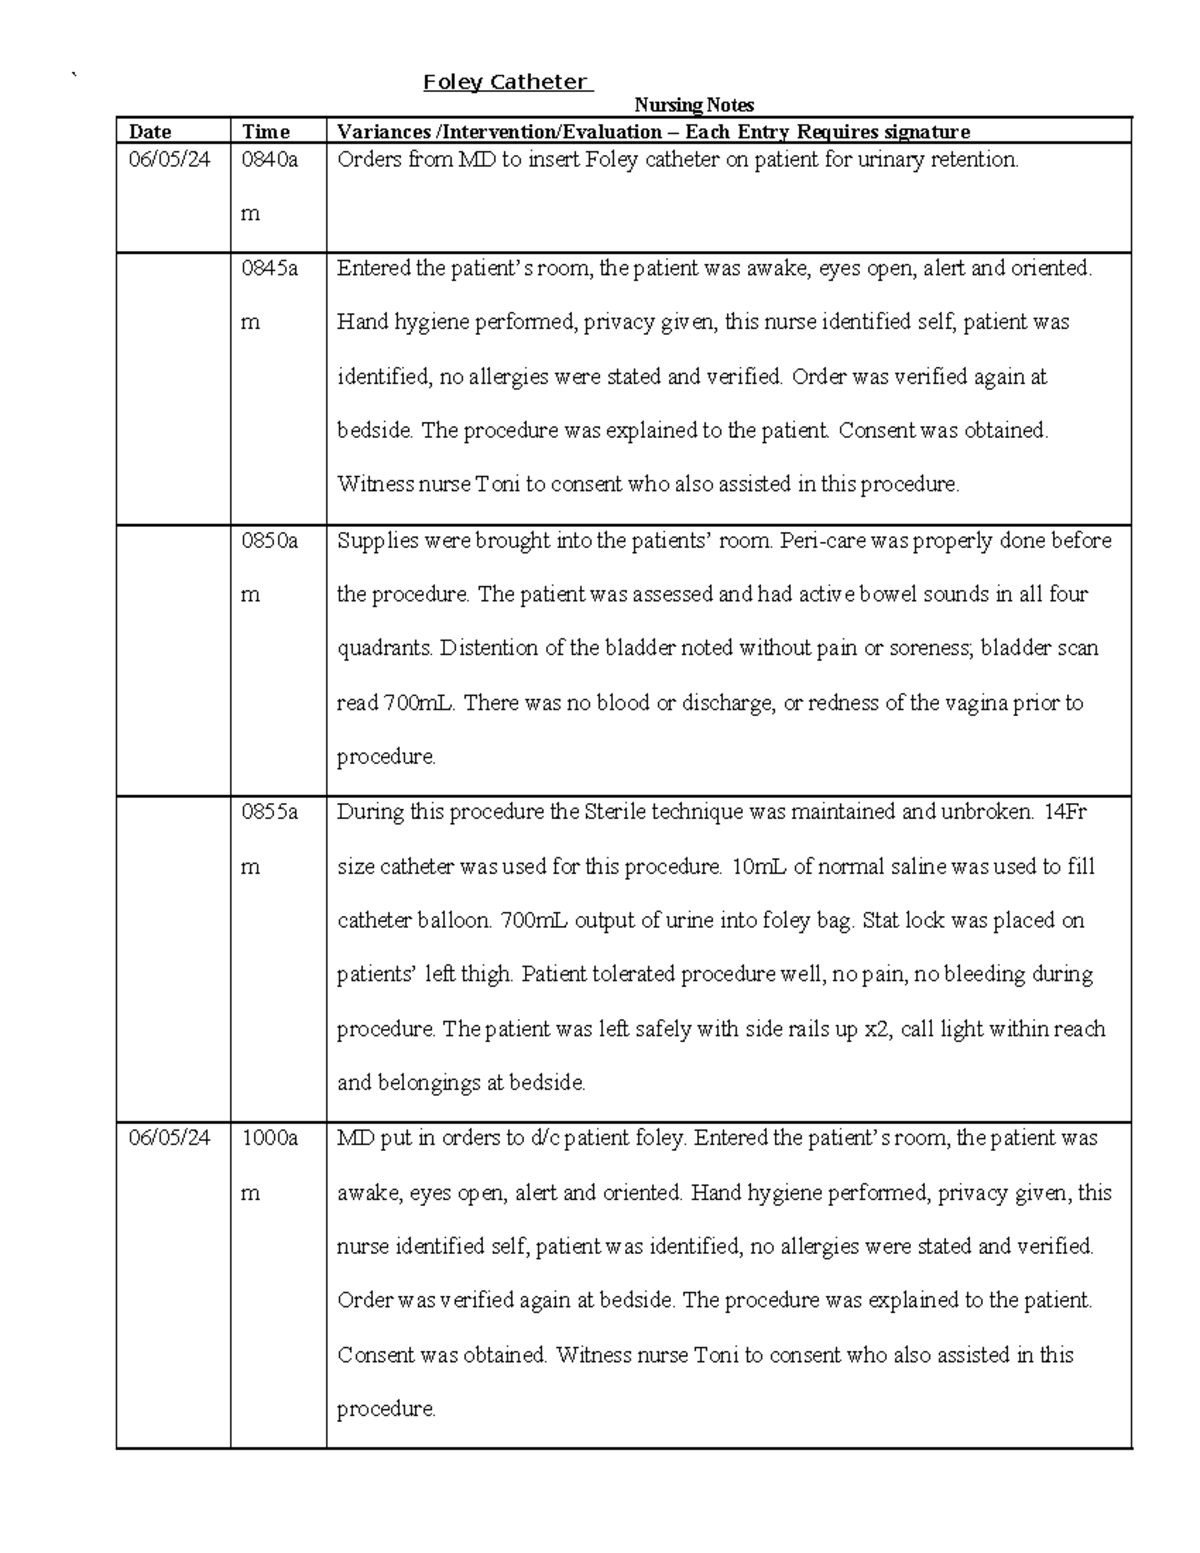
A foley catheter documentation error is one of the fastest ways to make your chart look negligent on review. It doesn't take much. A missed balloon volume, a conflicting insertion date, or output that doesn't match the fluid balance totals will set off flags fast. The actual process isn't complicated, but the places where people slip are specific and repetitive. Start by logging the catheter insertion date and time along with the indication for placement. Record the initial urine output and note the color and clarity. Confirm the balloon volume and document securement of the device. Assess the urethral meatus and perineal skin condition. Track ongoing hourly output with cumulative totals, and document any circuit disruptions or changes to the drainage system immediately. This is the core loop.
Nursing Foley Catheter Documentation Example
Here's how a complete note looks in practice. Insertion Date/Time: 2024-03-15 at 14:30. Catheter: 16 Fr silicone Foley. Indication: Acute urinary retention secondary to BPH with post-void residual of 850 mL confirmed by bladder scan. Technique: Sterile insertion performed at bedside. Balloon: 10 mL sterile water confirmed via backflow. Securement: StatLock applied to anterior thigh, no tension on catheter. Meatus/Skin: No erythema, no discharge, intact perineal skin. Initial Output: 720 mL clear yellow urine immediately upon insertion. Ongoing: Hourly outputs recorded. Shift total 1850 mL. Fluid balance calculated and reconciled with IV inputs. Complication: None documented during shift. Next scheduled catheter care: Q12H per protocol. That's one full cycle. It covers every required element. The details matter because auditors don't skim. They look for gaps.
One issue I've run into repeatedly involves catheters that were inserted on a different unit and transferred with the patient. The receiving nurse documents the transfer, but nobody documents the actual insertion date on the new unit's flow sheet. You end up with two dates in the chart and no way to know which is correct. When this happened to me on a med-surg floor, I pulled the original admitting nursing note from the previous shift, found the documented insertion time, and wrote a late entry on the new flowsheet stating the true insertion date with a timestamped addendum referencing the prior documentation. I also flagged it in the handoff report so the next nurse wouldn't miss it. That took five minutes and prevented a whole chain of confusion during a routine audit later. Another thing that catches people is the balloon volume. Most standard adult foleys use 10 mL, but some protocols call for 30 mL in specific cases like post-prostatectomy patients or when there's concern about spontaneous drainage. Using a 30 mL balloon without documenting the indication is a documentation gap. I've seen charts where the balloon volume was listed as 30 mL but there was zero note explaining why the larger volume was chosen. That's a liability issue. Document the rationale even if it's one sentence. The output tracking part has a nuance most beginners miss. When you're documenting hourly outputs, the cumulative total should match your fluid balance calculation at the end of the shift. If they don't match, you have an error somewhere. I've found that rounding at each hourly mark instead of carrying the exact number forward is the most common cause. Write down 150 mL, carry 150. Don't round to 200 and then wonder why your totals are off by 300 mL at shift change. Use the exact numbers throughout and round only on the final shift summary line.
Get the Full Details
There are situations where this documentation approach breaks down completely. Patients on continuous bladder irrigation don't fit neatly into standard hourly output forms. The irrigation fluid mixes with urine, and what comes out of the catheter isn't purely urinary output. In those cases, you need to document the CBI rate separately, calculate net urinary output by subtracting the irrigation volume from the total drainage, and note the calculation method in the chart. If your facility doesn't have a CBI-specific flowsheet built into the EMR, you'll need to create a manual calculation line and initial it every hour. It's tedious but necessary for accuracy. For catheters in place longer than 30 days, the documentation requirements expand. You need to document the ongoing indication, reassess the need for continued catheterization at regular intervals per facility policy, and record any changes to the catheter type or size. Some institutions require a physician order renewal every 30 or 60 days. Check your policy and document accordingly. Skipping the reassessment note is a common finding in infection control audits. If your EMR doesn't have a dedicated urinary output flowsheet, you can fall back to a structured narrative format. It's less efficient but covers the same ground. Group the data by shift, include all the same elements, and make sure the hourly outputs are listed in chronological order with running totals. Any deviation from the standard form should be noted with a brief explanation so the next reader understands why the format changed.
The hardest part isn't writing the note. It's remembering to update it in real time instead of trying to reconstruct a whole shift's data from memory at the end of the day. Memory fails under workload. Writing as you go takes seconds and prevents the kind of retrospective guesswork that creates documentation errors. I keep a small clinical reference card at the nurses' station with the essential documentation elements for foley catheters. It's not a substitute for knowing the material, but it's a quick check when I'm processing multiple patients and need to make sure I haven't missed an element. Most people don't need something this rigid if they do it regularly, but for new graduates or nurses transitioning to a unit that uses foleys infrequently, having a checklist reduces the chance of leaving out a required field.