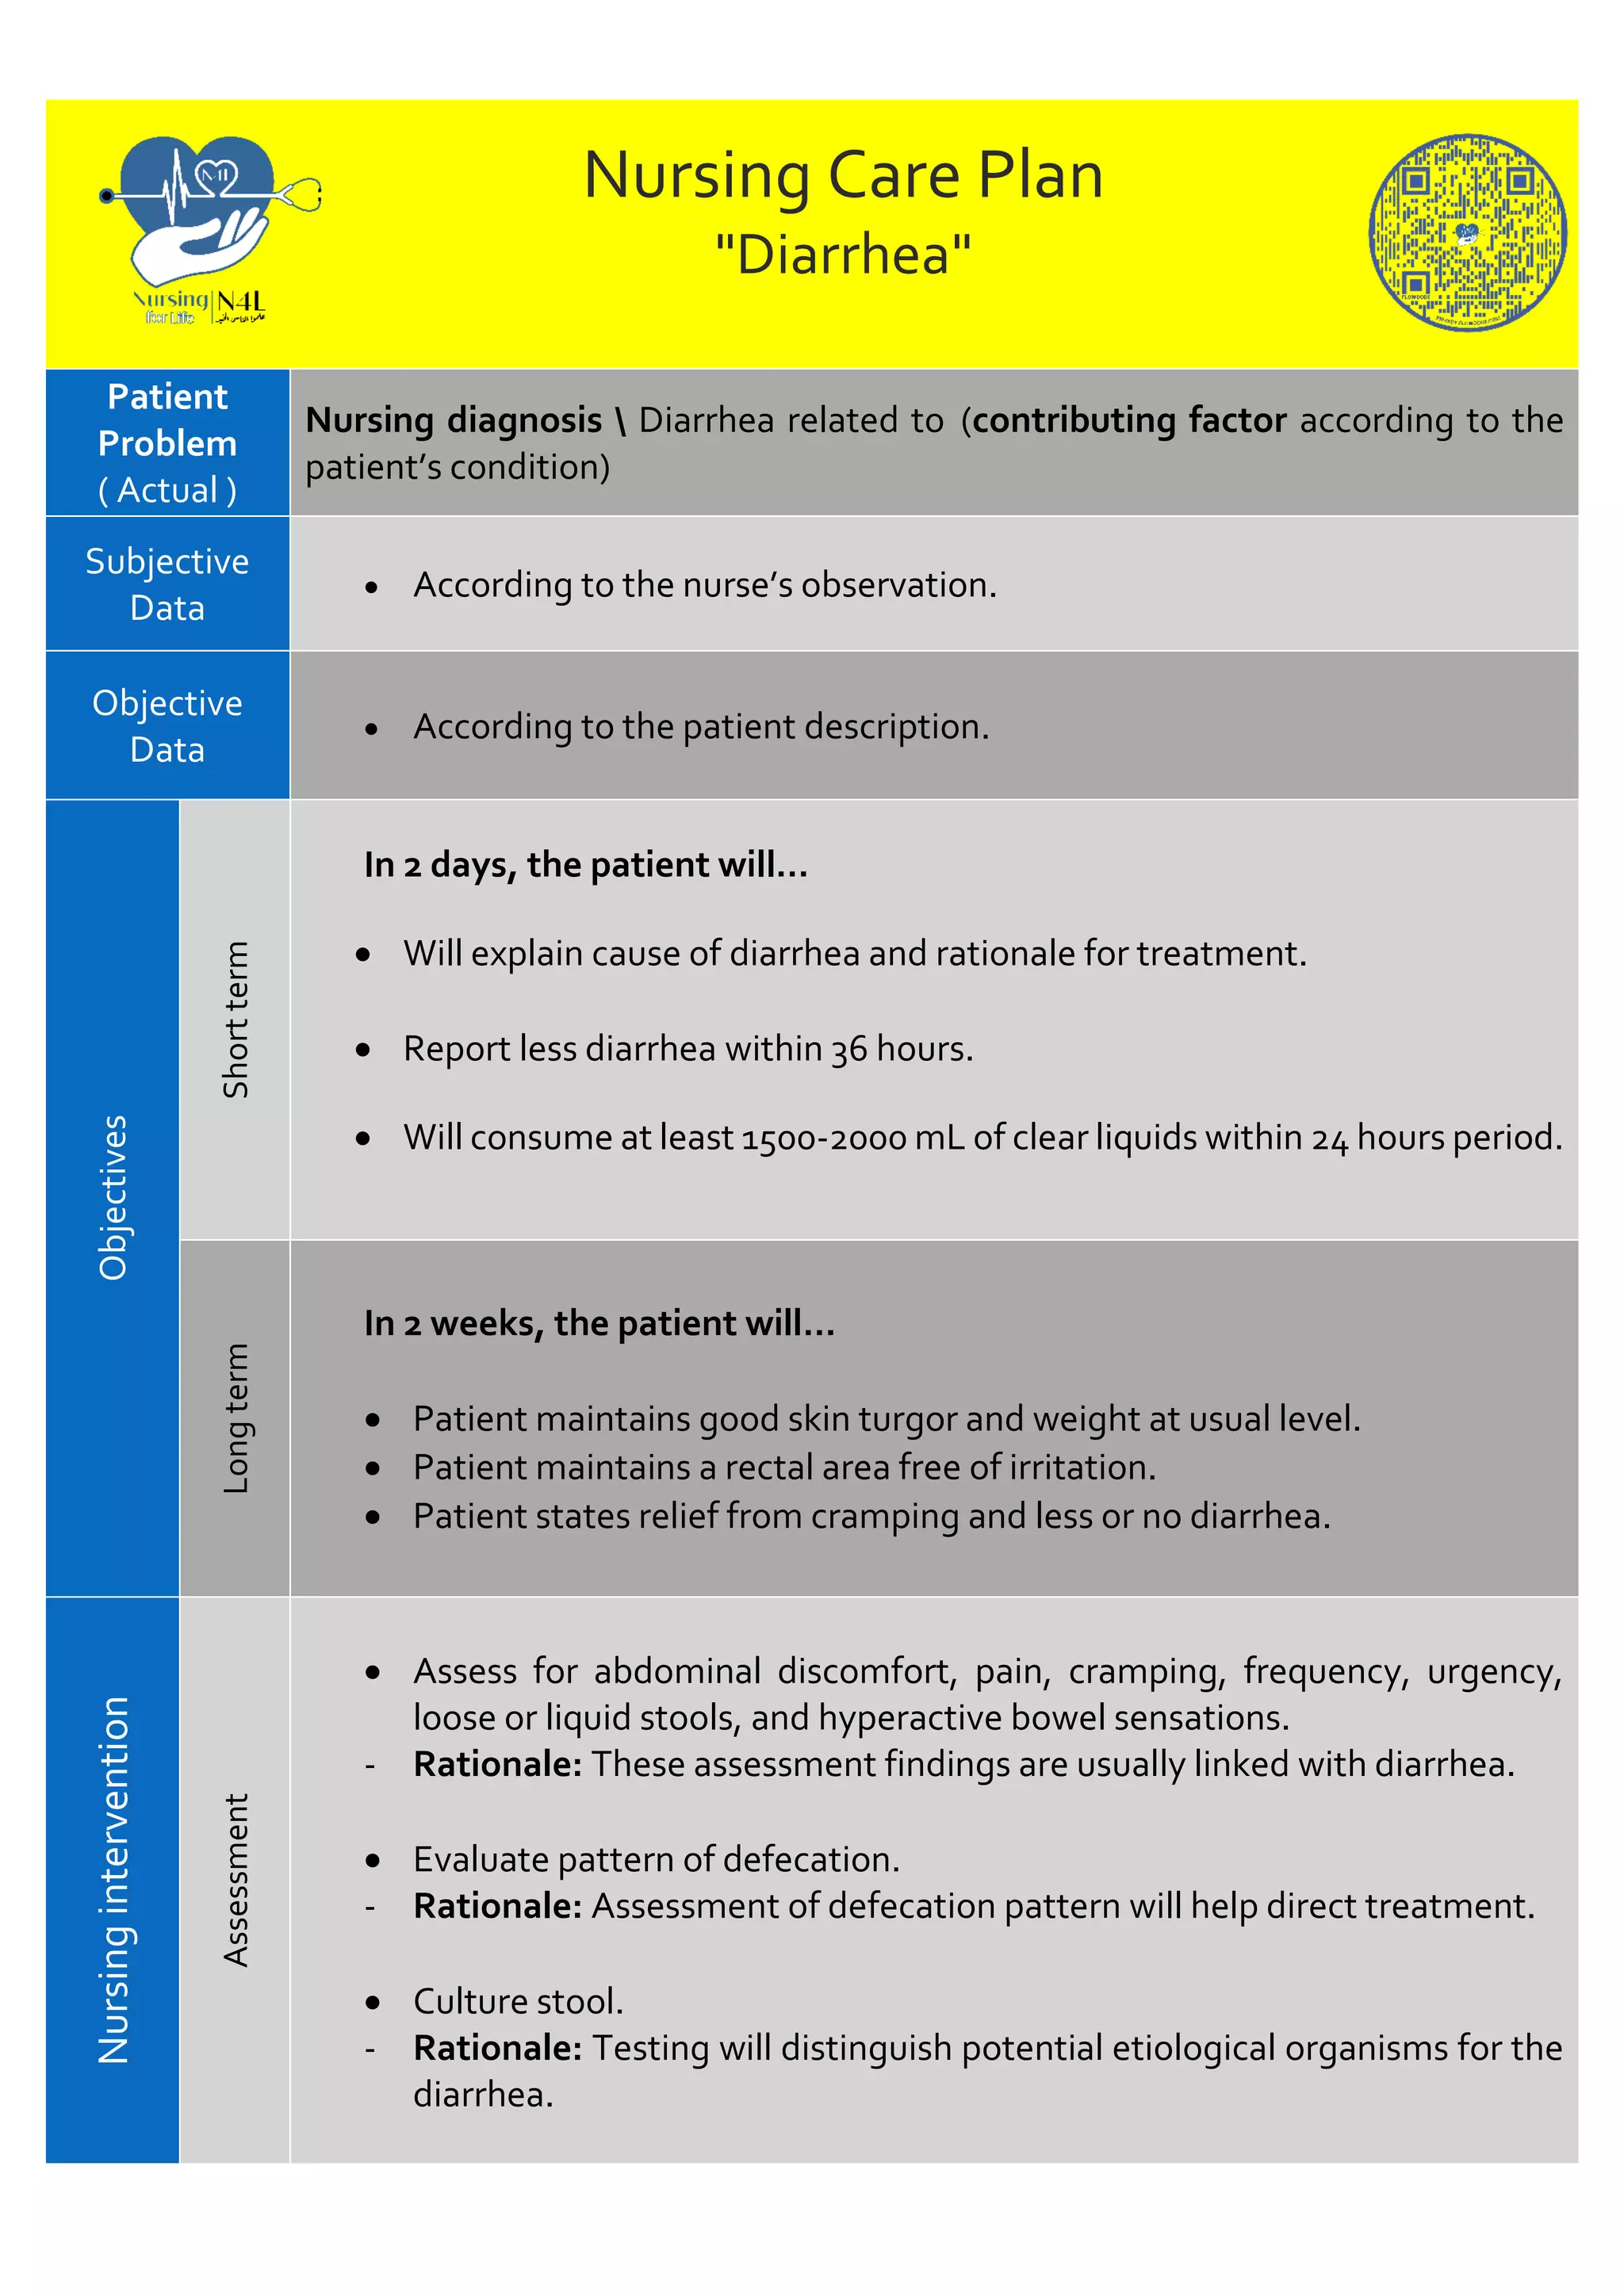
Setting Realistic Goals When Patients Have Diarrhea
Most nursing students and new nurses get this wrong because they copy textbook goals without thinking about whether the patient can actually achieve them. A nursing goal for diarrhea isn't just about stopping the bowel movements. It's about identifying what's causing it, preventing complications, and setting measurable outcomes that actually matter in a clinical setting. I've seen nurses write goals like "patient will have normal bowel movements within 24 hours" and then wonder why their care plans got questioned during clinical evaluations. That goal assumes you can control the underlying cause, which you often can't in a single shift. Let me walk through how this actually works.
Defining the Nursing Goal For Diarrhea Properly
Before you write any goal, you need a proper nursing diagnosis. Diarrhea in the NANDA-I sense is defined as the passage of loose, watery stools more frequently than usual. The related factors determine everything about your intervention plan and your goals. If it's antibiotic-associated, the goal is completely different from if it's osmotic, secretory, or motility-related. Here's the thing most people miss: the primary nursing problem with diarrhea isn't the diarrhea itself. It's the risk for deficient fluid volume and electrolyte imbalance. You can document "diarrhea" as the diagnosis, but your care should center on hydration status. I learned this the hard way during my third year of clinicals when a post-op patient had massive diarrhea from Clostridioides difficile. We focused entirely on bowel management and missed the fact that his potassium was dropping silently. He went into arrhythmia before we caught it. After that, I never wrote a diarrhea care plan without flagging electrolyte monitoring as a parallel priority.
The Care Plan Components That Actually Matter
A functional care plan for diarrhea needs assessment data, nursing diagnoses, goals, interventions, and evaluations. But the order you tackle them in is not always the order they appear on paper. In practice, I assess and intervene simultaneously while building the documentation around what's already happening. Assessment starts with stool characterization. Bristol Stool Scale types 6 and 7 confirm diarrhea, but frequency and volume matter more. I track bowel movement count per shift, estimate volume when possible, and note any presence of blood, mucus, or undigested food. You also need baseline vital signs, weight if available, mucous membrane assessment, skin integrity around the perineal area, and recent medication review. Antibiotics, metformin, PPIs, magnesium-containing supplements, and chemotherapy agents are the usual suspects. For nursing diagnoses, the top three you'll encounter are Deficient Fluid Volume, Risk for Electrolyte Imbalance, and Impaired Skin Integrity. Sometimes Acute Diarrhea itself is the primary diagnosis when the cause is identifiable and self-limiting. Remember that a risk diagnosis doesn't need actual signs yet, but it absolutely needs documented risk factors in your assessment to justify it.
Get the Full Details
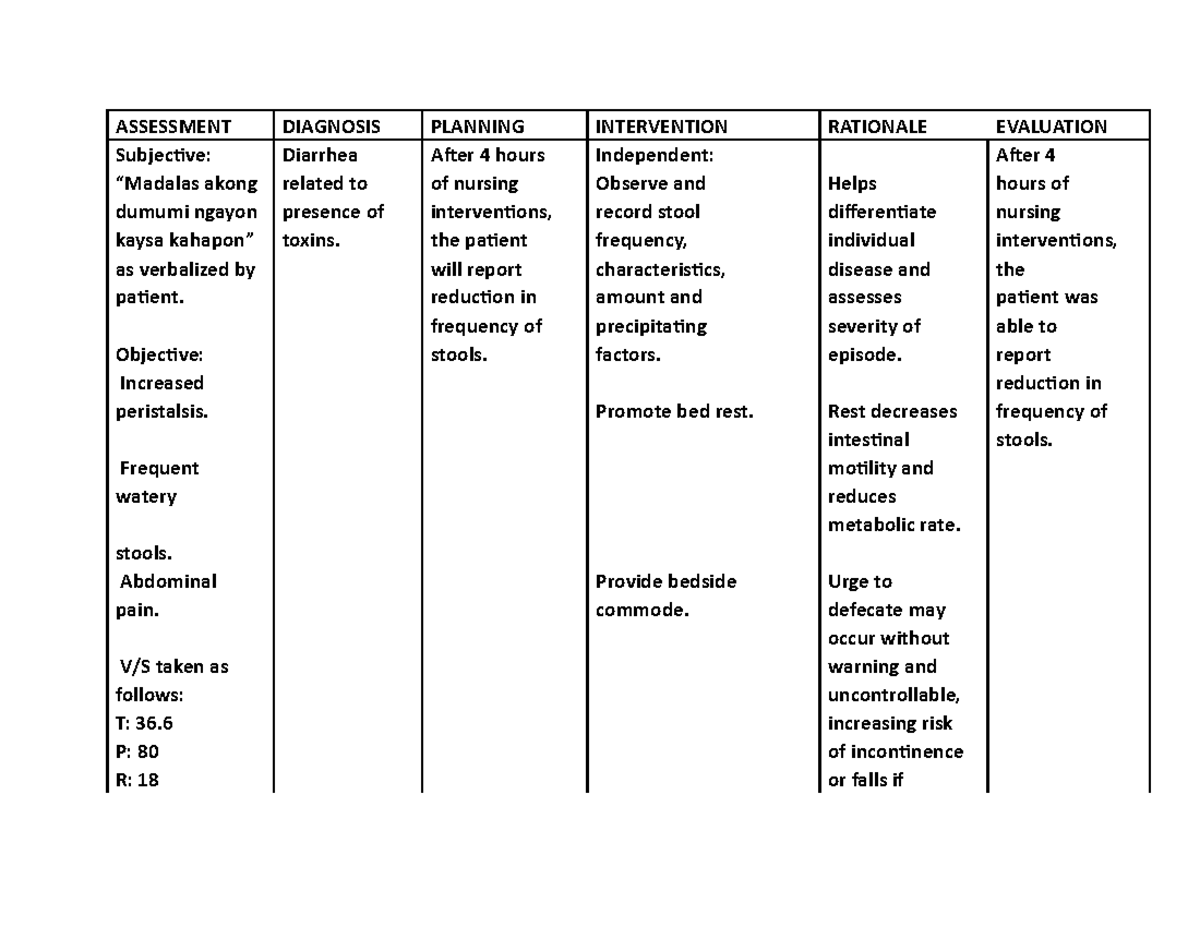
Goals should be SMART but realistic. Instead of "patient will resolve diarrhea in 24 hours," write something like "patient will maintain hemodynamic stability as evidenced by BP within 20% of baseline, heart rate below 100, and mucous membranes moist within 48 hours." That's measurable, time-bound, and focuses on what you're actually trying to prevent. A secondary goal might be "patient will maintain skin integrity around perianal area as evidenced by absence of breakdown at shift end." These goals acknowledge that you may not stop the diarrhea immediately but you can control the consequences. Interventions break into several categories. Fluid replacement is priority one. Oral rehydration solutions with proper glucose-sodium ratios work better than plain water for most cases. For patients who can't tolerate oral intake, IV fluids follow whichever protocol your facility uses, typically isotonic crystalloids with potassium replacement once levels are known. I prefer to check a basic metabolic panel before starting aggressive fluid resuscitation in chronic cases because rapid correction of potassium can be dangerous if the total body deficit is unknown. Dietary modifications come next. The old BRAT diet recommendation has been largely debunked as insufficient nutritionally, but avoiding high-osmolar foods, excessive caffeine, and lactose in lactose-intolerant patients makes a real difference. I usually recommend small frequent meals with soluble fiber sources like oats and bananas rather than restrictive diets that lead to malnutrition in prolonged cases.
Skin protection is where I see the most preventable harm. Perianal skin breakdown from repeated liquid stool exposure happens fast. I use barrier creams with zinc oxide or dimethicone at every perineal care episode, not just when skin looks compromised. Gentle cleansing with pH-balanced washes instead of soap and water reduces irritation significantly. Some facilities have wound ostomy nurses who can supply specialized barrier products that make a dramatic difference in difficult cases.
A Specific Problem I Encountered and How I Handled It
Once I had a patient on extended broad-spectrum antibiotics who developed persistent diarrhea. We treated it symptomatically for two days without improvement. The fecal toxin assay finally came back positive for C. diff, but by then the patient had significant dehydration and early acute kidney injury. The workaround I used that I wish I'd started earlier was aggressive contact precautions combined with early infectious disease consultation and switching to oral vancomycin per the latest guidelines instead of waiting for the stool culture to confirm. Metronidazole alone is no longer first-line for initial episodes according to current IDSA guidelines, but I've seen too many protocols lag behind the evidence. If you suspect C. diff clinically, don't wait for lab confirmation to start isolation and discuss treatment with the attending. The delay costs patients. Another edge case involves tube-fed patients. Diarrhea in patients on continuous enteral feeding is incredibly common and frequently misattributed. I've found that the formula temperature, osmolality, and rate of advancement matter enormously. Warming the formula to body temperature and slowing the infusion rate by 10 to 20 milliliters per hour often reduces stool frequency noticeably. Adding soluble fiber to the formula can help bulk the stool in some patients. This is counterintuitive for people who assume diarrhea always means reducing feeds, but in many cases the feeds themselves are the variable you can adjust.

Pitfalls and Limitations to Watch For
The biggest mistake I see is treating the symptom without investigating the cause. Antimotility agents like loperamide might seem like an easy solution, but they're contraindicated in infectious diarrhea, particularly C. diff and invasive bacterial pathogens. Using them in those cases can precipitate toxic megacolon. I've watched this happen. Don't reach for anti-diarrheals without knowing the etiology first. Another limitation of standard nursing goals for diarrhea is that they don't account well for terminal or palliative care patients. In those populations, aggressive intervention for diarrhea often causes more suffering than the symptom itself. The goal shifts from resolution to comfort. This is a nuanced distinction that requires honest conversation with the care team and family. No textbook covers this adequately. Documentation is also a recurring problem. Nurses often write "diarrhea managed" without specifying frequency, consistency, or patient response. This makes evaluation impossible and creates liability issues. Be specific. Document the number of episodes, estimated volume, appearance, and any interventions attempted with their timing and effect.
If the diarrhea persists beyond 48 to 72 hours despite basic interventions, the nursing goal changes from management to escalation. At that point, the goal should be timely identification of the underlying cause through appropriate diagnostics and specialist consultation rather than continued symptomatic treatment. There's a threshold where more nursing interventions stop helping and delayed diagnosis starts causing harm.