Senna: The Real Nursing Workflow
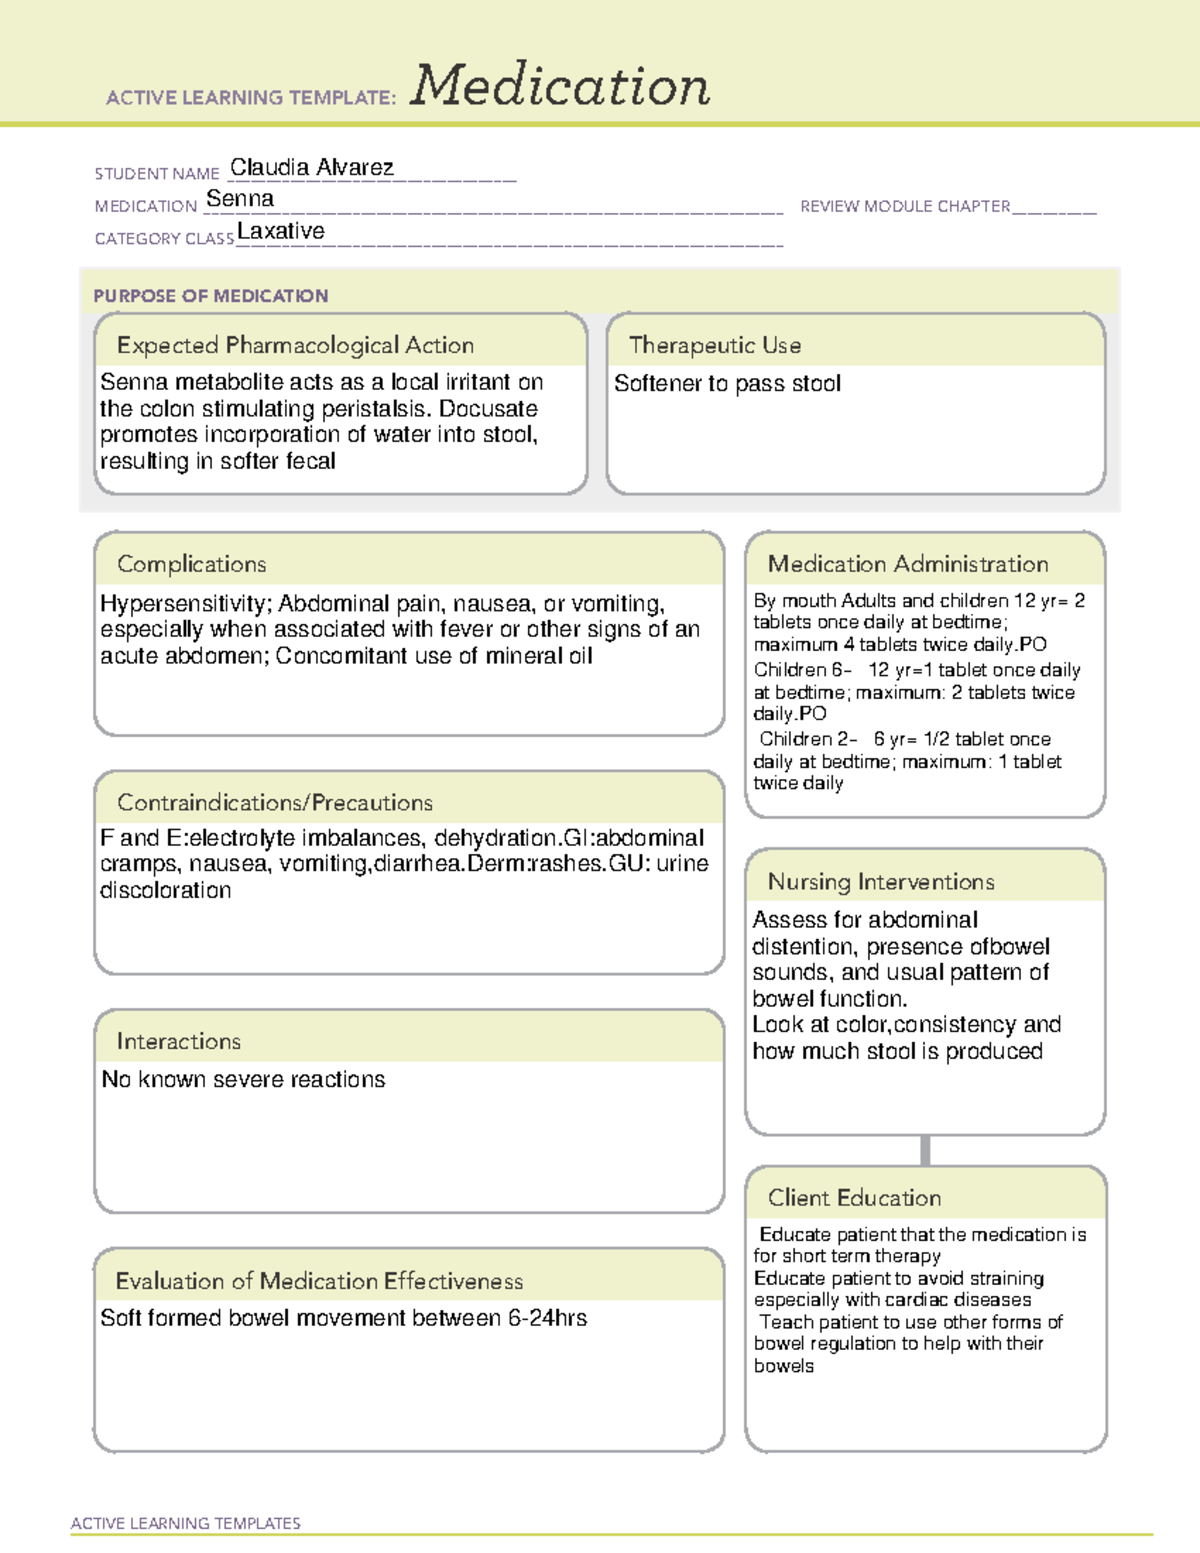
Senna gets prescribed almost automatically when a patient isn't moving their bowels. It works, but it also creates a predictable set of problems that most new nurses learn about the hard way. The medication is a stimulant laxative derived from plants, and it forces the colon to contract. That basic mechanism is why it causes cramping and why it messes with electrolytes. You need to know both before you hand out the dose. The core nursing implications for senna revolve around timing, fluid balance, and electrolyte monitoring. The drug typically takes 6 to 12 hours to work, which means a morning dose often results in a bowel movement the same evening. I always schedule the dose at bedtime for patients I want to move the next morning, rather than giving it at 0800. That simple shift reduces nighttime interruptions and lets me assess the result during my morning rounds instead of chasing a crisis at midnight. The big risk is hypokalemia. Senna causes fluid and electrolyte loss through the gut, and potassium drops quietly over days. In one case, a patient on furosemide for heart failure started taking senna daily for opioid-induced constipation. His potassium fell to 2.9, and he developed muscle weakness and irregular heartbeats. We missed the correlation at first because the focus stayed on his diuretic dose. The workaround was adding a scheduled potassium check twice a week whenever we combined senna with any diuretic or steroid. That pattern caught three more patients before anyone got symptomatic.
Another thing people miss is the interaction with digoxin. Low potassium makes digoxin toxicity much more likely. If a patient is on digoxin and needs a stimulant laxative, checking a level and potassium before each dose isn't excessive. It is standard practice. I keep a mental flag for any patient on digoxin, furosemide, or hydrochlorothiazide when senna comes up in med administration.
What the Label Doesn't Tell You
The patient education leaflets say senna is safe for short-term use. They don't mention that tolerance builds fast. After a week or two, the same dose produces a weaker response. Some clinicians respond by increasing the dose, which only increases potassium loss. The better move is switching to a bulk-forming agent or adding a stool softener, then using senna only as a rescue medication. That approach keeps the colon from becoming lazy and preserves the drug's usefulness for acute situations. Senna also has a distinct disadvantage in patients with renal impairment. Reduced kidney function slows the clearance of metabolites, and while the drug itself isn't heavily renally cleared, the resulting diarrhea can worsen volume depletion and push creatinine up quickly. I learned this when a patient with stage 3 CKD developed acute kidney injury after a routine discharge prescription of senna. The workaround was coordinating with the prescribing provider to use a lower starting dose and checking basic metabolic panels within 72 hours of initiation.
Get the Full Details

Practical Administration Steps
When you administer senna, verify the indication. It is meant for intermittent constipation, not for chronic daily management. Check the dose form. Tablets, capsules, and liquid exist, and the liquid version acts slightly faster because it does not need to dissolve first. Record the baseline bowel pattern before the first dose. Without that reference point, you cannot tell if the drug is working or if the patient simply never had a problem to begin with. Fluid intake matters more than most people realize. Senna pulls water into the colon to stimulate movement. If the patient is dehydrated, the medication becomes less effective and the risk of electrolyte imbalance rises. Encourage oral fluids unless there is a restriction. I remind myself to ask about fluid status every time I hand out the dose, even if the order includes a fluid restriction. A quick assessment of mucous membranes and skin turgor takes ten seconds and prevents several complications down the line.
When to Hold and When to Escalate
Hold the dose if the patient has undiagnosed abdominal pain, nausea, vomiting, or signs of bowel obstruction. Senna can mask worsening symptoms and lead to perforation in rare cases. Report any severe cramping or rectal bleeding immediately. These are not side effects to monitor through; they are signals to stop the drug and reassess. If the expected bowel movement does not occur within 24 hours, do not simply increase the dose. Reassess the patient. Check for fecal impaction, review other medications that cause constipation, and consider a different class of laxative. Escalate to the provider with a clear summary of what has been tried and what the patient's current symptoms are. That is the process that keeps patients safe and avoids the cycle of escalating stimulant use.
Quick Reference Summary
I keep a one-page reference for common stimulant laxatives in the nurses' station. It includes onset times, major drug interactions, and monitoring parameters. For senna specifically, the key points are: onset 6 to 12 hours, risk of hypokalemia, interaction with digoxin and diuretics, tolerance after prolonged use, and contraindication in bowel obstruction. I print these sheets myself because the hospital resource center rarely updates them fast enough. If you need a downloadable version of a similar quick reference, you can find freely available nursing pharmacology guides at the FDA drug information portal or through major nursing organizations. These resources provide updated dosing tables and safety warnings without the marketing fluff that sometimes appears in commercial drug databases.

Bottom Line
Senna is a useful medication when used correctly. It is also easy to misuse in ways that cause electrolyte disturbances, tolerance, and unnecessary patient discomfort. The nursing implications are straightforward once you internalize the monitoring requirements and the timing adjustments. Start with a baseline bowel pattern, check potassium in at-risk patients, respect the dose limit, and have a plan for when it stops working. That routine turns a simple laxative into a manageable part of patient care instead of a recurring problem. Most of the complications I have seen come from treating senna as a routine discharge medication without follow-up. Adding a single follow-up assessment within a week catches the issues early and prevents escalation. It is a small change in workflow that makes a noticeable difference in patient outcomes.



