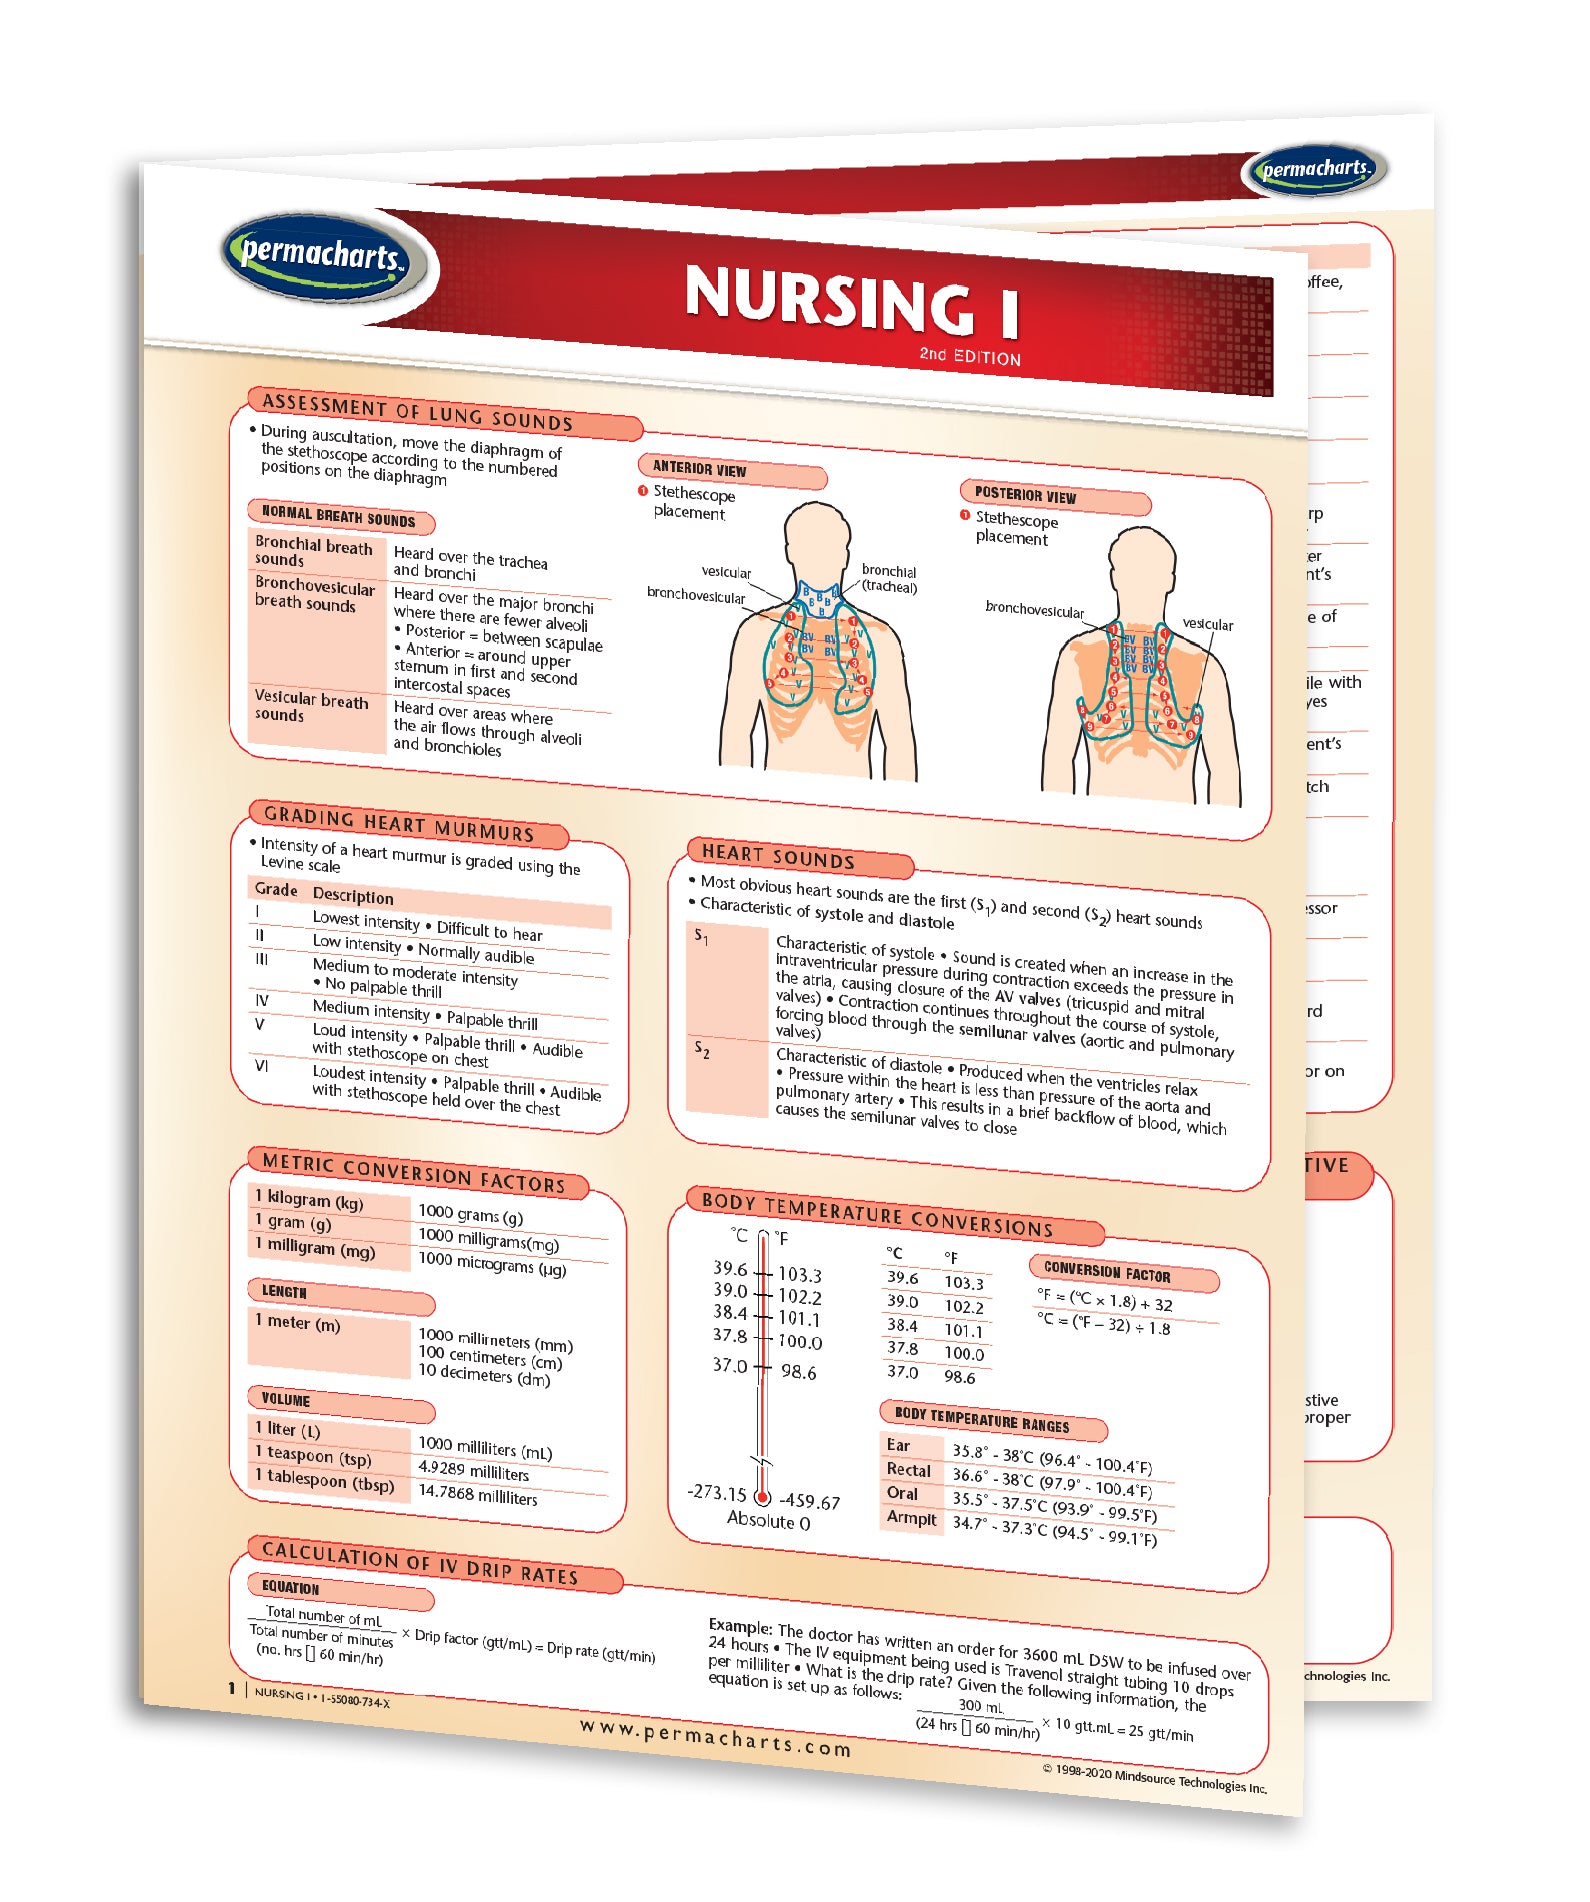
What Nurses Actually Need When They Search for Quick Reference Materials
I spent eight years on a med-surg floor before moving into clinical education. The thing I learned the hardest was that nurses don't want philosophy. They want something they can open on a break, scan in thirty seconds, and apply before their next med pass. Most resources miss this completely. There is a specific category of quick-reference tools that fills this gap. People call them different things, but the one that matters right now is Nursing Manual Quick. It is not a textbook. It is not a video course. It is a condensed reference system designed for busy shift workers who need answers without reading sixty pages to find one protocol.
How Nursing Manual Quick Actually Works in Practice
I started using this approach around 2019 when our hospital switched to an new electronic charting system. The old paper drug guides took up most of my cart space and still missed half the interactions I ran into. Nursing Manual Quick changed how I organized my personal reference materials. It is essentially a rapid-access compendium that groups interventions by acuity level, organ system, and medication class all in one search layer. The core structure is deceptively simple. Each entry has three parts: a one-paragraph mechanism summary, a bulleted intervention checklist, and a red-flag warnings section. Nothing else. No lengthy literature reviews. No theoretical debates. When I needed to verify the nursing implications of starting a new anticoagulant drip at 2 AM, I could pull the exact page in about twelve seconds. That saved me from making a documentation error that could have cost the unit a serious audit finding. Here is the practical workflow I developed. First, you identify the clinical scenario category—cardiac, respiratory, metabolic, neurological, or infectious. Second, you select the acuity tier. Emergency tier means protocols for unstable patients. Stable tier covers routine monitoring and discharge planning. Third, you cross-reference the medication or procedure if applicable. This three-layer filtering usually cuts research time from twenty minutes down to under two minutes during an actual shift.
The format is intentionally modular. Each section can be printed as a standalone card, saved as a phone wallpaper, or loaded into a searchable digital app. I carry a laminated set of the top forty protocols on my badge reel. They cover the scenarios I encounter most: cardiac arrhythmias, sepsis bundles, insulin titration, pain management, and fluid balance monitoring. The rest lives on my phone as a quick-search document.
Get the Full Details

Setting Up Your Own Nursing Manual Quick System
Building this from scratch takes about three hours your first time. After that, maintenance is maybe fifteen minutes per month. I will walk you through the process without fluff because you are probably reading this between patients. Step one: Gather your source material. You need at least four reliable references. The standard combination is the Davis Drug Guide, the nursing procedures handbook from your hospital's policy library, a recent evidence-based practice journal on your specialty area, and the hospital's own standing orders or protocol documents. If you work in a small clinic with limited resources, start with whatever policy manual your employer provided and supplement with the OpenTextbook Library nursing resources. Both are free. Step two: Create the category structure. Open a spreadsheet or note-taking app and build five main categories. Cardiac, Respiratory, Metabolic, Neurological, and General/Med-Surg. Under each category, add subcategories for common conditions or interventions. For cardiac, include arrhythmias, heart failure, post-catheterization, and anticoagulation. For respiratory, include COPD exacerbation, pneumonia, asthma, and ventilator management. Do not overcomplicate this. Eight to twelve subcategories per main category is plenty.
Step three: Write the three-part entry format. For each condition or intervention, create one page with three sections. Mechanism summary: two to four sentences explaining what is happening physiologically and why the treatment works. Intervention checklist: five to ten bullet points covering assessment, administration, monitoring, and patient education. Red flags: three to five warning signs that require immediate provider notification. Keep each bullet point under fifteen words. If it is longer, you are writing a paragraph instead of a quick reference. Step four: Add cross-references. At the bottom of each entry, link to related conditions and medications. If you are writing about heart failure management, link to diuretic protocols, fluid restriction guidelines, and daily weight monitoring procedures. This creates a network effect where finding one protocol leads directly to everything else you need for that clinical situation. Step five: Format for speed. This is where most people fail. Your final document should use large fonts, high contrast colors, and clear visual hierarchy. I use a yellow highlight for critical actions, red text for contraindications, and blue headers for medication names. When you are working under fluorescent lights with tired eyes at the end of a twelve-hour shift, color coding makes the difference between catching a warning and missing it entirely.
Step six: Test under realistic conditions. Print a test page and try to find information while multitasking. Time yourself searching for a specific drug interaction or assessment finding. If it takes longer than thirty seconds, simplify the entry. Rearrange the structure. Remove anything that does not directly support rapid decision-making. I spent three weeks refining my initial draft before I was satisfied with the speed and accuracy.

Common Pitfalls That Slow You Down
I have watched dozens of nurses build these systems and most run into the same problems. The biggest one is information overload. People want to include everything they know, so the document becomes massive and useless. A Nursing Manual Quick that takes five minutes to navigate defeats its own purpose. You are building a shortcut, not an archive. Another frequent mistake is copying directly from textbooks or policy manuals without condensing. The original language is often wordy and academic. Nurses need directive language. Instead of writing "The nurse should assess the patient's respiratory status continuously and monitor for signs of distress," write "Monitor respirations every 15 minutes. Report rate below 10 or above 28." The meaning is identical. The scanning speed is dramatically better. A third issue is outdated information. Hospital protocols change frequently. A drug dose that was correct last year might be wrong this year. I recommend setting a calendar reminder to review your entire system every ninety days. Update anything that conflicts with current policy. Most of my entries get a quick scan during these reviews, and maybe three or four entries actually need revision per cycle.
The fourth pitfall is ignoring your specialty context. A med-surg nurse needs different quick references than an ICU nurse or a pediatric nurse. Do not build a generic system and hope it works everywhere. Customize the acuity levels and common scenarios to your actual patient population. I initially copied a friend's ICU-focused system and struggled for weeks because half the entries never applied to my medical-surgical patients. Once I rebuilt it around my own caseload, everything clicked into place.
Advanced Techniques for Experienced Users
Once you have a working basic system, there are ways to make it significantly more powerful. The first technique is building medication-specific quick reference cards. These are single-page documents that cover the most commonly prescribed drugs in your practice area. Include mechanism, standard dosing, nursing implications, side effects, and patient education points. I keep a separate binder section for about sixty of these cards, and I reference them daily. The second technique is creating laboratory value interpretation guides. Normal ranges vary by facility, so customize yours to your hospital's standards. Include the clinical significance of abnormal values, likely causes, and appropriate nursing actions. This is especially valuable for nurses managing patients on multiple medications that affect renal function, electrolyte balance, or coagulation parameters. The third advanced technique is building a symptom-to-protocol decision tree. This is a flowchart-style reference that starts with a presenting symptom and branches into possible causes and corresponding interventions. Cardiac chest pain goes to EKG interpretation, monotherapy options, and escalation criteria. Shortness of breath goes to oxygenation targets, positioning strategies, and diagnostic workup recommendations. These trees are harder to create but save enormous time during complex assessments.
The fourth technique involves creating shift-specific quick checks. Many nurses find value in having a morning assessment checklist, a medication pass verification list, and an end-of-shift handoff template built into their system. These are not clinical references per se, but they reduce cognitive load and prevent oversights during transition periods.
When This Approach Falls Short
I want to be honest about limitations. Nursing Manual Quick is not a substitute for comprehensive clinical judgment or formal education. It is a reference tool, not a decision-making framework. If you rely on it blindly without understanding the underlying principles, you will make mistakes. The format is optimized for speed, not depth. Another limitation is that this system requires upfront investment. Three hours to build the foundation is significant time for a working nurse. Some people start with commercial products like Skyscape or UpToDate quick references and customize those instead. Those solutions cost money but save the build time. Evaluate your situation honestly and choose the path that fits your resources. The system also becomes outdated quickly if you do not maintain it. I have seen nurses build excellent references and then never touch them again for eighteen months. By then, half the information no longer matches current standards of care. Set a recurring review schedule and treat maintenance as part of your professional development, not an optional extra.
Finally, there is a security consideration. Never store patient-specific information in your personal quick reference documents. This is a HIPAA violation and could cost you your license. Keep the system focused on general protocols, drug references, and assessment guidelines only. If you need patient-specific documentation, use the official electronic health record system.

Where to Get Started Today
If you want to build your own Nursing Manual Quick system, start with whatever resources you already have access to through your employer. Hospital policy manuals, orientation binders, and in-service training materials are all valid source material. Organize them into the five-category structure I described. Write the first ten entries for your most common clinical scenarios. Test the speed and refine from there. Several online templates exist that can accelerate the process. Search for nursing quick reference templates in Word or Google Docs format. Many clinical educators share free versions that you can customize. Do not spend money on expensive software until you have validated that this approach actually helps your workflow. Simple tools are sufficient. The goal is not to create the most comprehensive reference ever assembled. The goal is to build something fast enough to use when it matters. If your system helps you find a critical intervention checklist in under thirty seconds during a real clinical situation, you have succeeded. Everything else is bonus points.
I have been using variations of this system for over six years now. It has reduced my pre-shift preparation time by approximately forty percent and cut my on-the-floor research moments to a fraction of what they used to be. More importantly, it has prevented several potential errors that I would have missed without quick access to consolidated protocol information. That is the real value proposition. Not convenience. Patient safety. The next time you find yourself digging through five different binders looking for one piece of information while a patient is waiting, invest the three hours to build this system. Your future self on a brutal night shift will thank you for it.

