Writing Nursing Notes That Won't Get You in Trouble
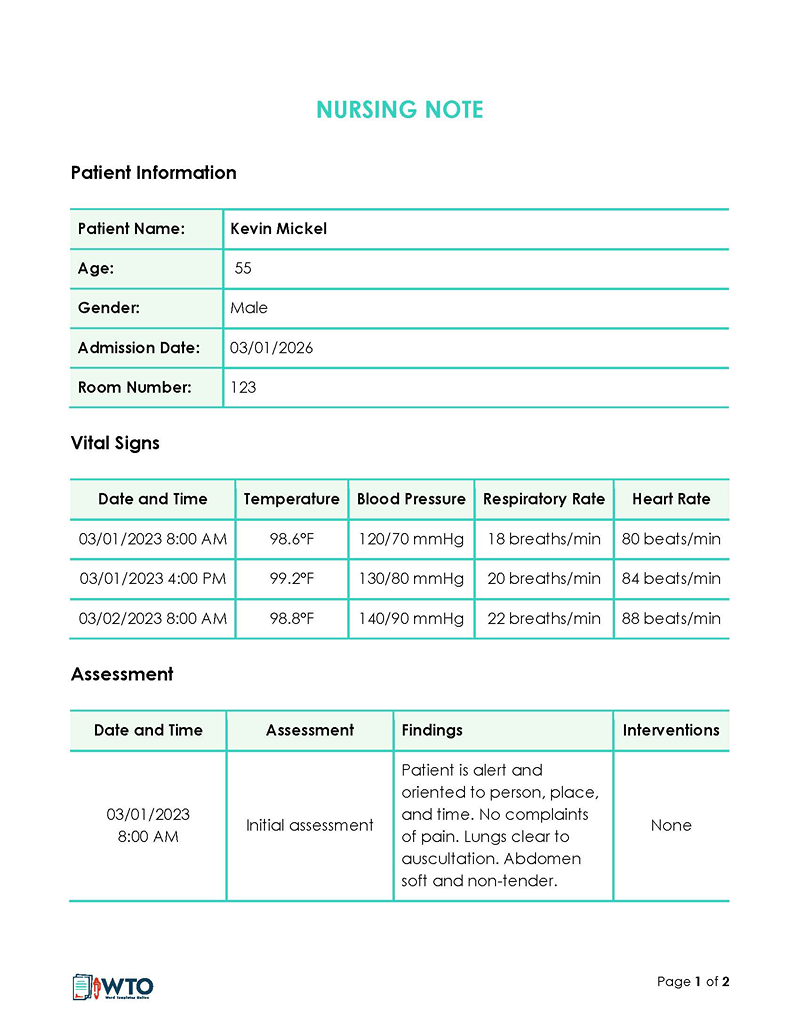
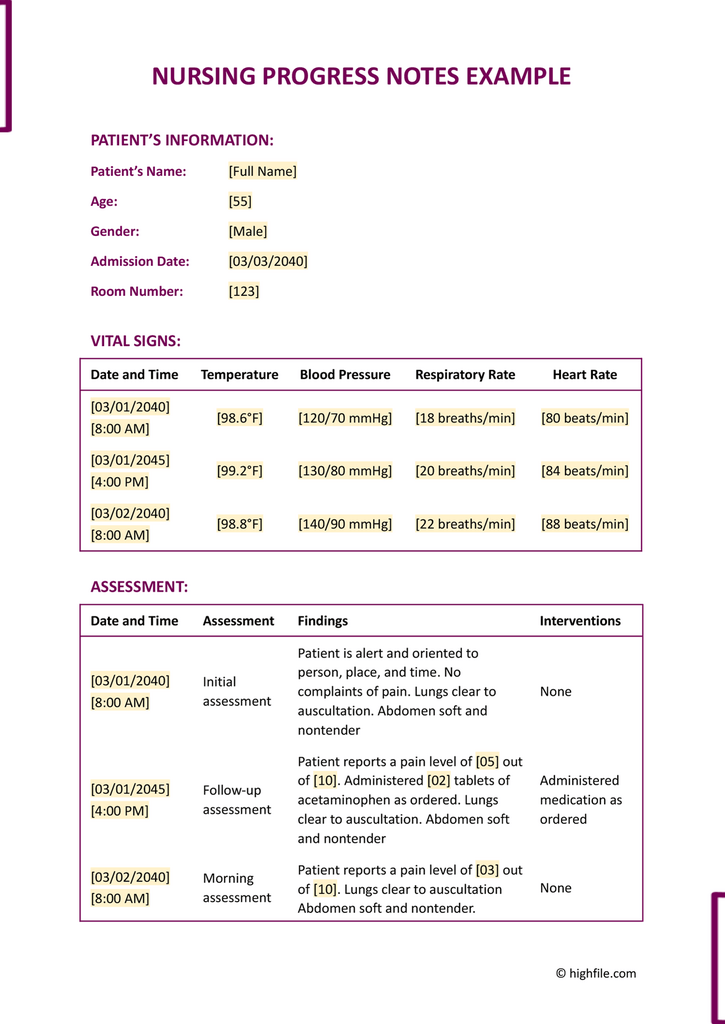
I spent most of my career on med-surg and long-term care, and if there is one thing I learned the hard way, it is that documentation is the difference between a clean shift and a legal nightmare. A good Nursing Note Example isn't fancy writing. It is a factual, chronological record that anyone—lawyer, doctor, or insurance auditor—can read and understand what happened without guessing. Here is a straightforward example that follows the standard SOAP format and shows the level of detail required: Subjective: Patient reports "I've been having more shortness of breath since this morning." Reports compliance with inhaler regimen. States last use of albuterol was at 0600 today.
Objective: Vitals at 0700: BP 142/88, HR 96, RR 22, SpO2 91% on room air. Lung auscultation reveals bilateral wheezing, worse at bases. Patient working harder to breathe; visible use of accessory muscles. Assessment: Acute exacerbation of COPD likely triggered by recent respiratory infection. Current oxygen saturation below target range. Plan: Oxygen initiated at 2L via nasal cannula per physician order. Repositioned patient to high-Fowler's. Notify attending physician. Administer prescribed bronchodilator treatment at 0800. Monitor SpO2 every 30 minutes for next 2 hours. Educated patient on pursed-lip breathing technique.
That is the structure most facilities expect. The format itself isn't the problem. The problem is how people fill it in. I have seen nurses write notes like "Patient resting comfortably" when they clearly were not, or "Vitals within normal limits" when the blood pressure was 190 over 110. These shortcuts sound fine at the time but collapse under any scrutiny later. A physician reviewing the chart weeks after the fact needs to know exactly what you saw, not what you think you saw.
Get the Full Details

What Actually Goes Into a Nursing Note
Nursing notes are legal medical records. They document the chain of care from admission through discharge. Every medication administered, every assessment performed, every patient response to treatment, and every change in condition needs to be recorded. This isn't optional. If it isn't documented, it didn't happen in the eyes of the law and insurance companies. The most common formats you will encounter are SOAP, DAR, and narrative notes. SOAP is the standard. DAR stands for Data, Action, Response, and it is essentially the same thing with different labels. Narrative notes are freestyle paragraphs and they tend to be messier. I recommend sticking to SOAP unless your facility requires something else. There is one detail most people skip. Time stamping. Every entry should include the exact time the observation or intervention occurred. I once worked a case where a nurse documented a fall at 2200 but the actual incident happened at 2345 because the note was written late from memory. That 1 hour and 45 minute gap became a major issue during a root cause analysis. The fix was simple: document immediately, or at minimum document the exact time of the event separately from the time of writing.
The Mistakes That Cause Real Problems
Copy-paste is the single biggest issue in modern nursing documentation. Electronic health records make it easy to duplicate previous assessments, and many nurses do it without updating the relevant data. I found a note once that said "Patient ambulating independently" when the patient had been bedbound for three days. The previous day's note had described them walking fine, and someone hit copy without checking. That note sat in the chart for an entire shift before anyone noticed. It is a lawsuit waiting to happen. Another issue is vague language. Words like "stable," "improved," and "normal" mean nothing without context. "Vitals stable" tells someone nothing. "BP 128/82, down from 145/90 at 0800" tells them everything. Always include numbers. Always include direction of change. Abbriviations are another minefield. Some facilities have banned certain ones entirely. I used to write "per bd" for per os, per buccae, and per vagina until my charge nurse caught me and said no one could tell which one I meant. Just write it out. It takes three extra seconds and it prevents a hundred misunderstandings.
When Documentation Fails You
A Nursing Note Example like the one above works well when everything goes according to plan. But in practice, things get messy. Here is a scenario I dealt with directly. A patient with a history of falls was discharged with a note saying "patient educated on fall precautions." The next day, the patient fell in the hallway of the rehabilitation facility and broke their hip. The lawsuit focused on whether that education actually happened or was just checked off a form. My workaround was to make notes more specific. Instead of "patient educated on fall precautions," I started writing exactly what was covered: "Patient and family educated on call bell use, non-slip socks, and keeping walk path clear. Patient verbalized understanding and demonstrated correct use of call light. Family confirmed they will accompany patient to bathroom." That level of detail shifted the entire liability picture. The downside of this approach is time. Detailed notes take longer. On a busy floor with eight patients, that can add 30 to 45 minutes to your shift. But I would rather spend those extra minutes now than in a deposition later.

Quick Reference for Routine Charting
For shift assessments, stick to these key elements every time: vital signs with actual numbers, pain level using a consistent scale, neurological status, skin integrity at pressure points, intake and output totals, medication administration times, patient responses to interventions, and any changes in condition. That covers the essentials without padding the note with irrelevant information. If a patient has multiple chronic conditions, don't list every single one every shift. Reference the previous assessment and note only what changed. "Per yesterday's neuro assessment, only changes noted are..." is efficient and clear. But never let that become a blanket excuse to skip the assessment entirely. Most importantly, read back what you wrote before you sign out. Three minutes of review will catch errors that would otherwise come back to haunt you. I've caught my own typos, wrong dates, and misplaced numbers this way more times than I care to admit. It sounds obvious but I have worked with nurses who never re-read their notes.