
How I Actually Approach Step-By-Step Nursing Procedures
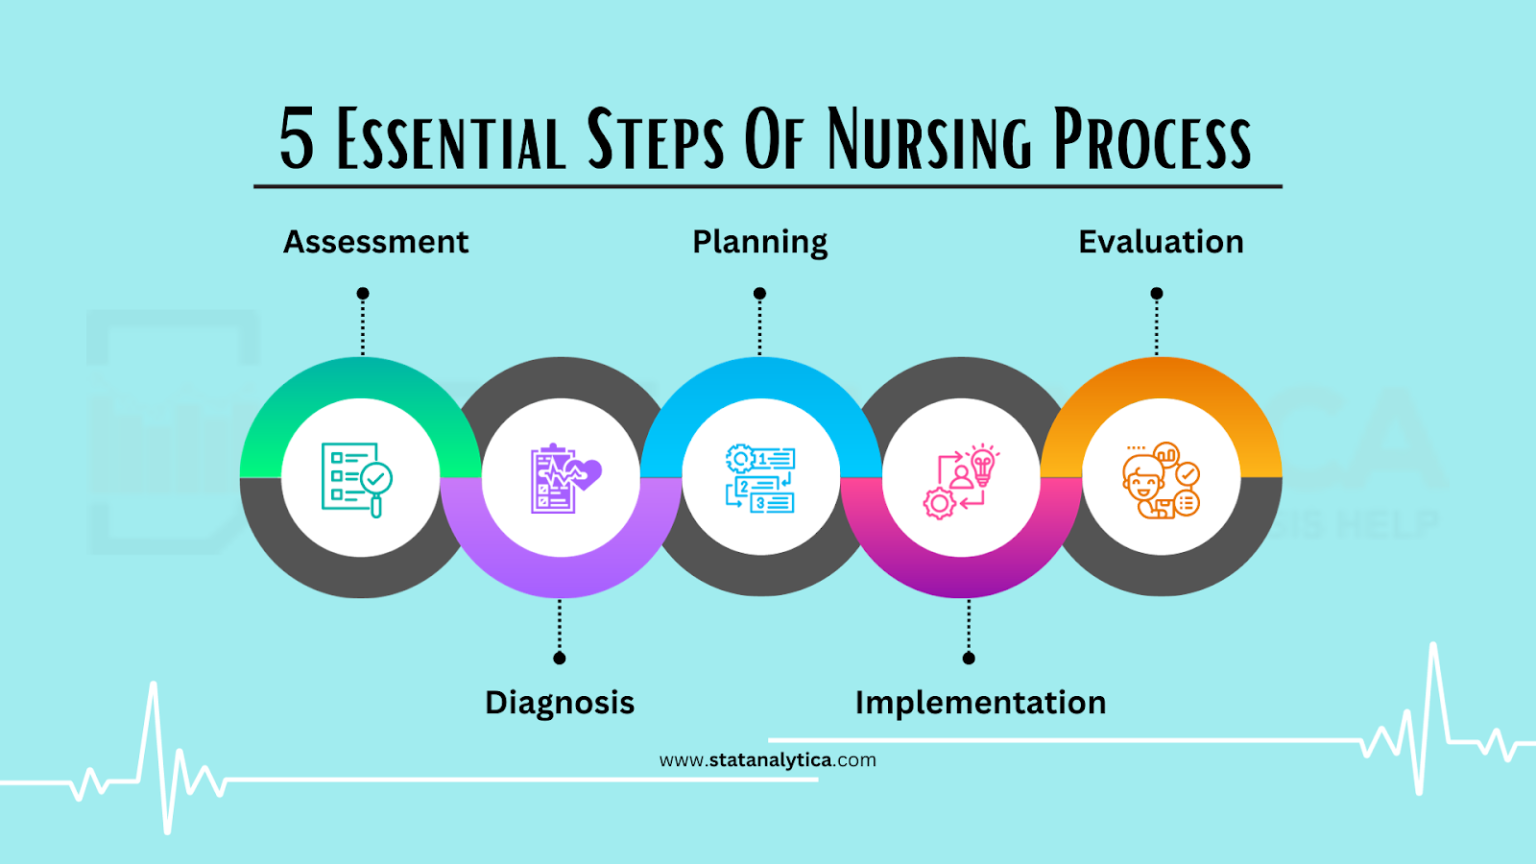
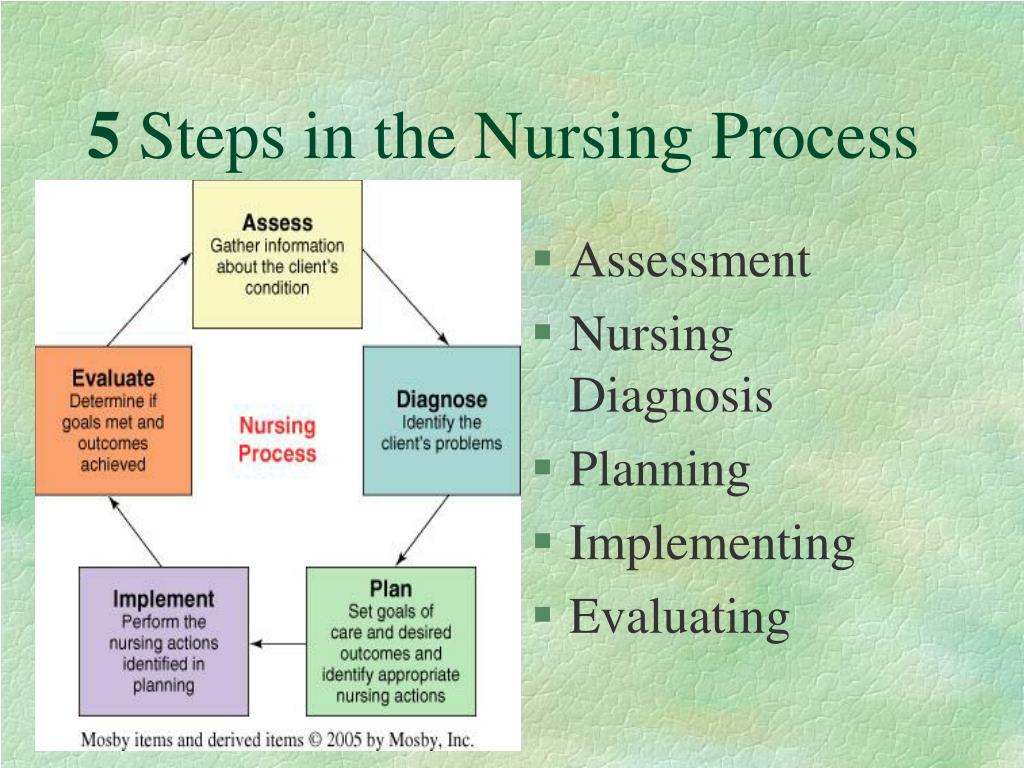
Most nursing students and new nurses treat every clinical skill like it needs to be memorized from a textbook flowchart. It doesn't work that way in practice. I spent years watching people panic over medication calculations or forget the order of steps during a procedure because they were reciting instead of understanding. The reality of Nursing Step By Step is less rigid than the manuals make it sound, and more about building a mental checklist you can fall back on when things get messy. Every single nursing procedure follows the same basic skeleton, regardless of what you're doing. You assess, you plan, you execute, you evaluate. That framework is what most people mean when they talk about a Nursing Step By Step approach. The problem is that textbooks present it as neat and linear. Real clinical work rarely is. I remember one shift where I was preparing to administer a continuous IV infusion through a port that had been accessed two days prior without proper flushing. The standard steps said to check patency first. I followed them. The arm was swollen, warm, and the patient reported mild burning. We stopped immediately, discontinued the line, and restarted on the other arm. Had I just pushed through with the medication like the schedule demanded, I would have missed the infiltrated site entirely because I was focused on the drug, not the access point.
That's the kind of thing no flowchart covers. You learn to keep your attention on the whole picture while still moving through the individual steps deliberately. Most hospital policy documents will list roughly eight to twelve steps for common procedures. Medication administration, wound dressing, vital sign collection, catheter insertion. These are the bread and butter items every nurse needs cold.
Medication Administration: Where Most People Mess Up
The five rights of medication administration are right and left, dose, route, time, and documentation. Every nursing program drills this into you. What they don't always emphasize is the documentation part. I've seen newer nurses skip verifying the patient's allergy status because the system flag was already green, then almost administered penicillin to someone with a documented anaphylaxis history. The flag had flickered off due to a system update. When I train people on my Nursing Step By Step method for medications, I start with the documentation because that's where the chain of accountability begins and ends. Print the MAR, verify against the order, check the patient's wristband against the medication label, scan the barcode, administer, document immediately. Do it in that exact order every time. I've found that rearranging the sequence even slightly creates gaps where errors hide. The barcode scanning step is non-negotiable. It catches roughly 60 percent of medication errors before they reach the patient, according to several studies I've reviewed over the years. Skip it because the machine is down or the barcode is worn off, and you're operating blind. I always carry a small penlight for reading faded barcodes and keep spare labels for when the printer runs out.
Get the Full Details
Wound Care: The Steps That Don't Matter As Much As You Think
There's a specific sequence for wound care that goes something like this: inspect, clean, debride if necessary, apply dressing, document. The inspection phase is where most nurses rush. I spent three months working in a surgical ward where the turnover rate for wound dressings was high. The faster we moved through inspections, the more pressure we felt from administrators. But I caught a stage two pressure ulcer on a patient's sacrum during one of those rushed checks because I noticed the skin had a different texture than the surrounding area. The team had missed it on two previous shifts because they were ticking boxes instead of actually looking. Proper wound inspection takes about ninety seconds per wound. I know that sounds slow when you have ten patients to check. But skipping it costs more time later when complications arise. Deep tissue injury that goes undetected can progress to stage four in as little as a week. The extra minute of attention during assessment pays for itself ten times over.
Vital Signs: What the Numbers Actually Mean
Collecting vitals is straightforward. Measuring them correctly is where the variation happens. I once had a patient whose blood pressure readings swung from 180 over 110 to 95 over 60 within the same hour. The chart showed consistent hypertension management failures. When I rechecked manually using a cuff that I calibrated myself, the readings dropped to 130 over 80. The automated machine was positioned on the wrong arm with the cuff two sizes too small, which artificially inflated the systolic reading by roughly thirty points. This is the part nobody teaches you in basics classes. Equipment calibration and proper sizing matter more than the technical act of taking the measurement. I keep a manual sphygmomanometer in my pocket at all times and verify automated readings against it whenever something looks off. It takes about thirty seconds and has prevented at least four medication dose errors on my shifts alone.
Documentation: The Part Everyone Hates But Shouldn't Skip
Documentation during and after procedures is where most nurses cut corners. I get it. You're exhausted. You have twelve patients, three call lights going off, and you just want to finish your chart. But incomplete or delayed documentation is the number one legal liability in nursing. I've seen cases where a nurse's entire defense of proper care fell apart because the chart didn't reflect what actually happened, regardless of how competent the care was. My approach is to document as I go. After each procedure, I step away for twenty seconds and write the essentials: time, intervention, patient response, any changes made. Twenty seconds per patient. That's forty minutes over a twelve-hour shift. Most nurses spend closer to two hours documenting at the end because they try to do it all at once, and by then memory has faded enough that details get fuzzy or omitted entirely. I also make it a habit to review my entries before signing off on any shift. Glancing over everything takes five minutes and catches things like wrong time stamps, missing signatures, and incomplete assessments. I caught one entry where I'd accidentally documented a post-procedure assessment under the pre-procedure section. The timing made the whole record unreliable. Finding that before I left saved me from a serious compliance issue.
Putting It All Together: A Practical Routine
Here's what my daily Nursing Step By Step routine actually looks like when I'm running a full shift: I begin with a head-to-toe assessment on every new admission, even when the chart says the patient is stable. Charts are records of past assessments, not current reality. I spend about fifteen minutes per admission doing this properly, checking skin integrity, lung sounds, circulation, neurological status, and pain levels. This initial work prevents most mid-shift emergencies because you already know what baseline looks like for that patient. For medication passes, I group drugs by route and timing. Oral medications come first, then intravenous, then injections. This reduces the cognitive load of switching between different procedures. I keep a laminated checklist in my workspace with the standard sequences for each drug category. It's not about forgetting steps. It's about creating a safety net so that even on a bad day, when you're mentally drained, the physical act of checking off items keeps you honest.
Wound care rounds happen during the mid-morning window when most patients are settled after breakfast. I carry a small kit with gauze, saline, tape, gloves, and a digital thermometer for measuring wound dimensions. Documenting wound size accurately requires measurement every time. Guessing leads to inconsistent progress reports that mislead the entire care team. The evening shift is where fatigue hits hardest. I've learned to slow down rather than speed up during those hours. A single medication error at 2 AM is worse than ten minor inconveniences during the day. I use the same checklist system throughout, which means my brain isn't constantly reconstructing the sequence from memory under pressure.
When the Standard Steps Fail
There are situations where following the standard Nursing Step By Step protocol exactly is the wrong move. An emergency code is one example. During cardiac arrests, the algorithm exists but requires adaptation based on patient response, available equipment, and team dynamics. Another example is palliative care, where aggressive intervention sequences may conflict with the patient's goals of care. I've had to modify standard procedures multiple times when the patient's condition made the textbook approach inappropriate or harmful. The skill isn't just in knowing the steps. It's in knowing when to deviate and when to stick strictly to the protocol. That judgment comes from experience and direct observation of outcomes. I can't teach that part. You have to live through enough clinical scenarios to build the pattern recognition that tells you when to break the rules. Until then, the steps exist for a reason. Follow them deliberately, document everything, and keep your head in the room even when your body is running on autopilot.



