Setting Up a Nursing Tracker That Actually Works on the Floor
I spent three years trying to get my unit's patient handoff system to not be a nightmare. Most of it came down to how we tracked medications, vitals, and fall risks in real time. A Nursing Tracker is just a system for logging patient data across shifts so nothing slips through the cracks. It sounds simple. The execution is where everyone screws up. Here is what I learned doing it wrong, then right. I am not going to give you a generic template. I will walk through the setup, the pitfalls, and the specific workaround that saved me when my first build collapsed under real-world usage.
What a Nursing Tracker Actually Is
At its core, a Nursing Tracker is a structured log that captures patient-specific data points across multiple shifts. Vitals, medication administrations, pain scores, fall risk status, IV sites, wound dressings, intake and output. The goal is continuity. When Shift B takes over from Shift A, they should not have to dig through three different charting systems to figure out what happened in the last eight hours. Most people start with a spreadsheet. I started with a spreadsheet. Within two weeks I had forty-seven tabs, three broken formulas, and a supervisor who thought I was doing something illegal because the color-coding looked like a ransom note. The spreadsheet approach fails for two reasons: version control and human error. Someone edits the wrong row. The file locks. You lose an entire shift of data because two people opened it at once.
The Setup
Here is the method I ended up using. It is not fancy. It does not require specialized software. It works because it was built around how nurses actually move through a shift, not how administrators wish they would move. The most common mistake I see is building the tracker first and figuring out what to track later. This reverses the priority and produces garbage. Sit down with your team and write out every data point you need to know at handoff. Not what looks nice. What you actually need. For my unit, the critical list was:
Get the Full Details

- Patient name and room number
- Current vitals with timestamps
- Medication administration times and doses
- Pain score on a 0-10 scale
- IV site location and status
- Fall risk classification (Morse score or equivalent)
- Intake and output totals per shift
- Wound care notes with dressing change times
- Special precautions (contact isolation, NPO status)
Anything outside this list can be added later. Do not try to include everything on day one. You will abandon the system within a month if it requires twenty fields per patient. Spreadsheets are fine for a small pilot. For actual clinical use, you need something with real-time sync and access controls. Google Sheets works if your organization allows it. Smartsheet is better for conditional formatting and automated reminders. Excel Online is acceptable but has clunky collaboration features. If your facility has an EHR system like Epic or Cerner, check whether there is already a built-in tracking module before building something external. Using an outside tool alongside the EHR creates dual-charting problems that will make audit season miserable. I learned this the hard way when our compliance officer asked why my spreadsheet data did not match the EHR for three of our patients.
Step 3: Build the Template
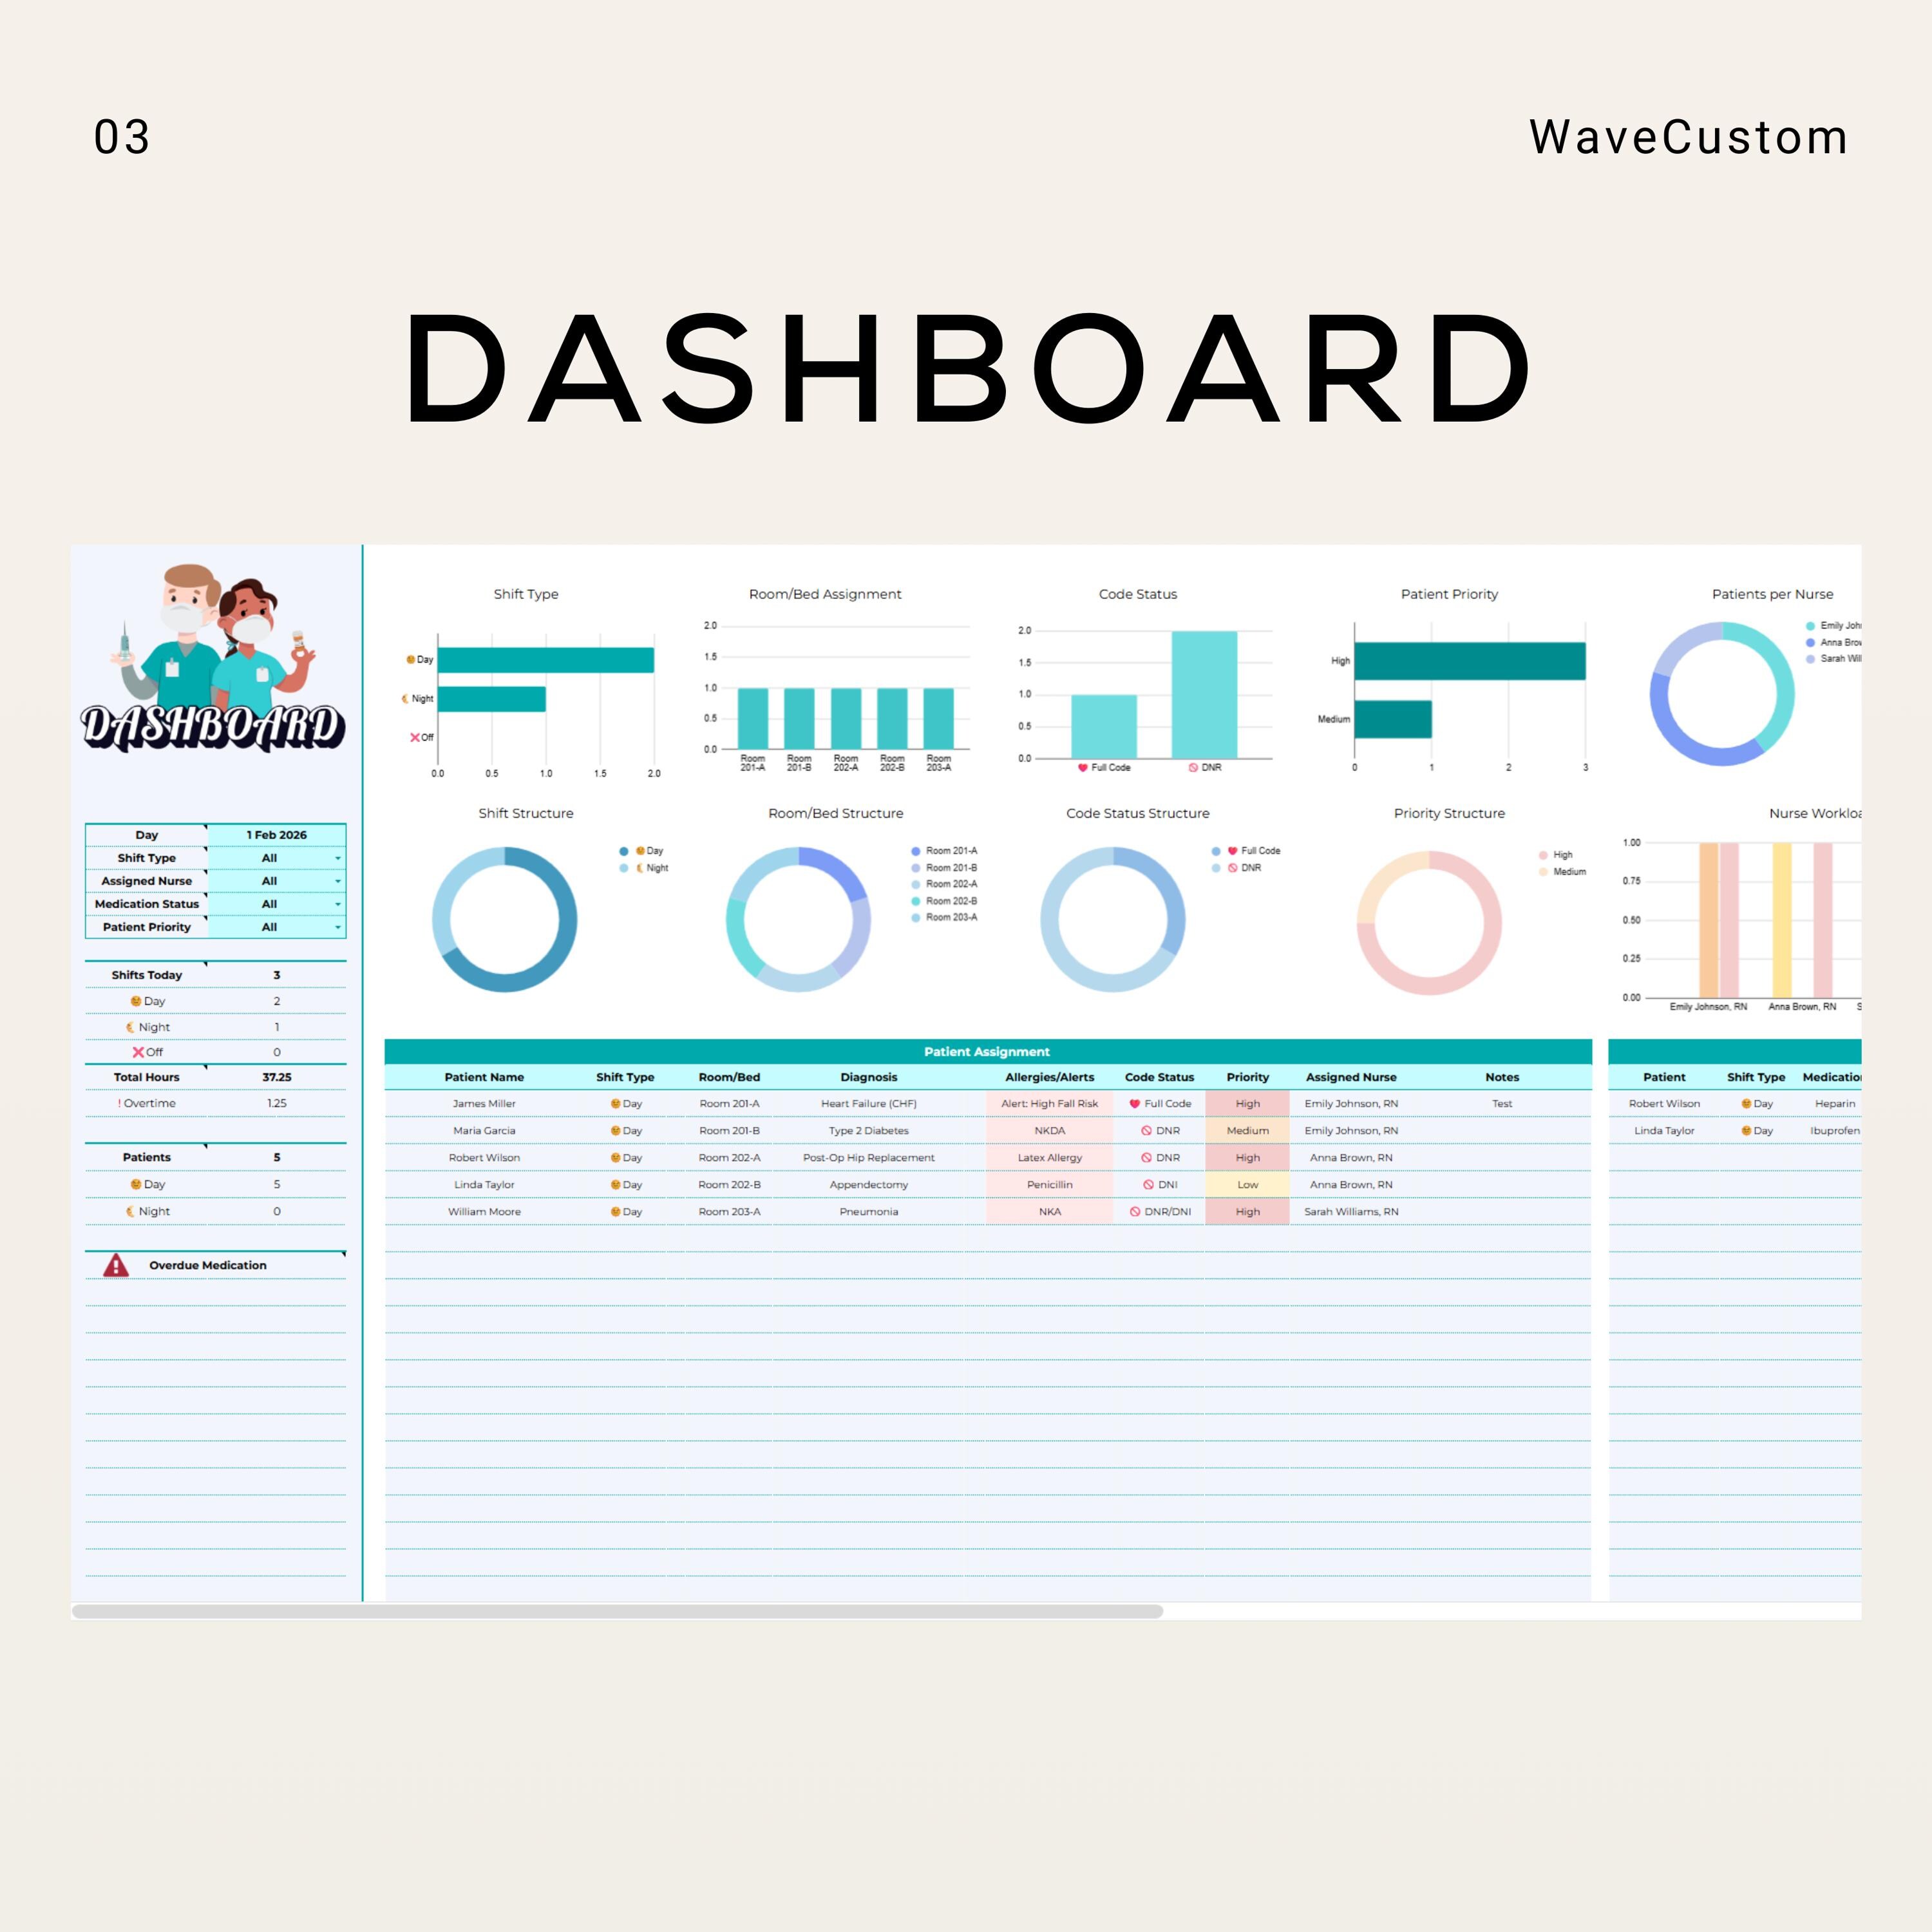
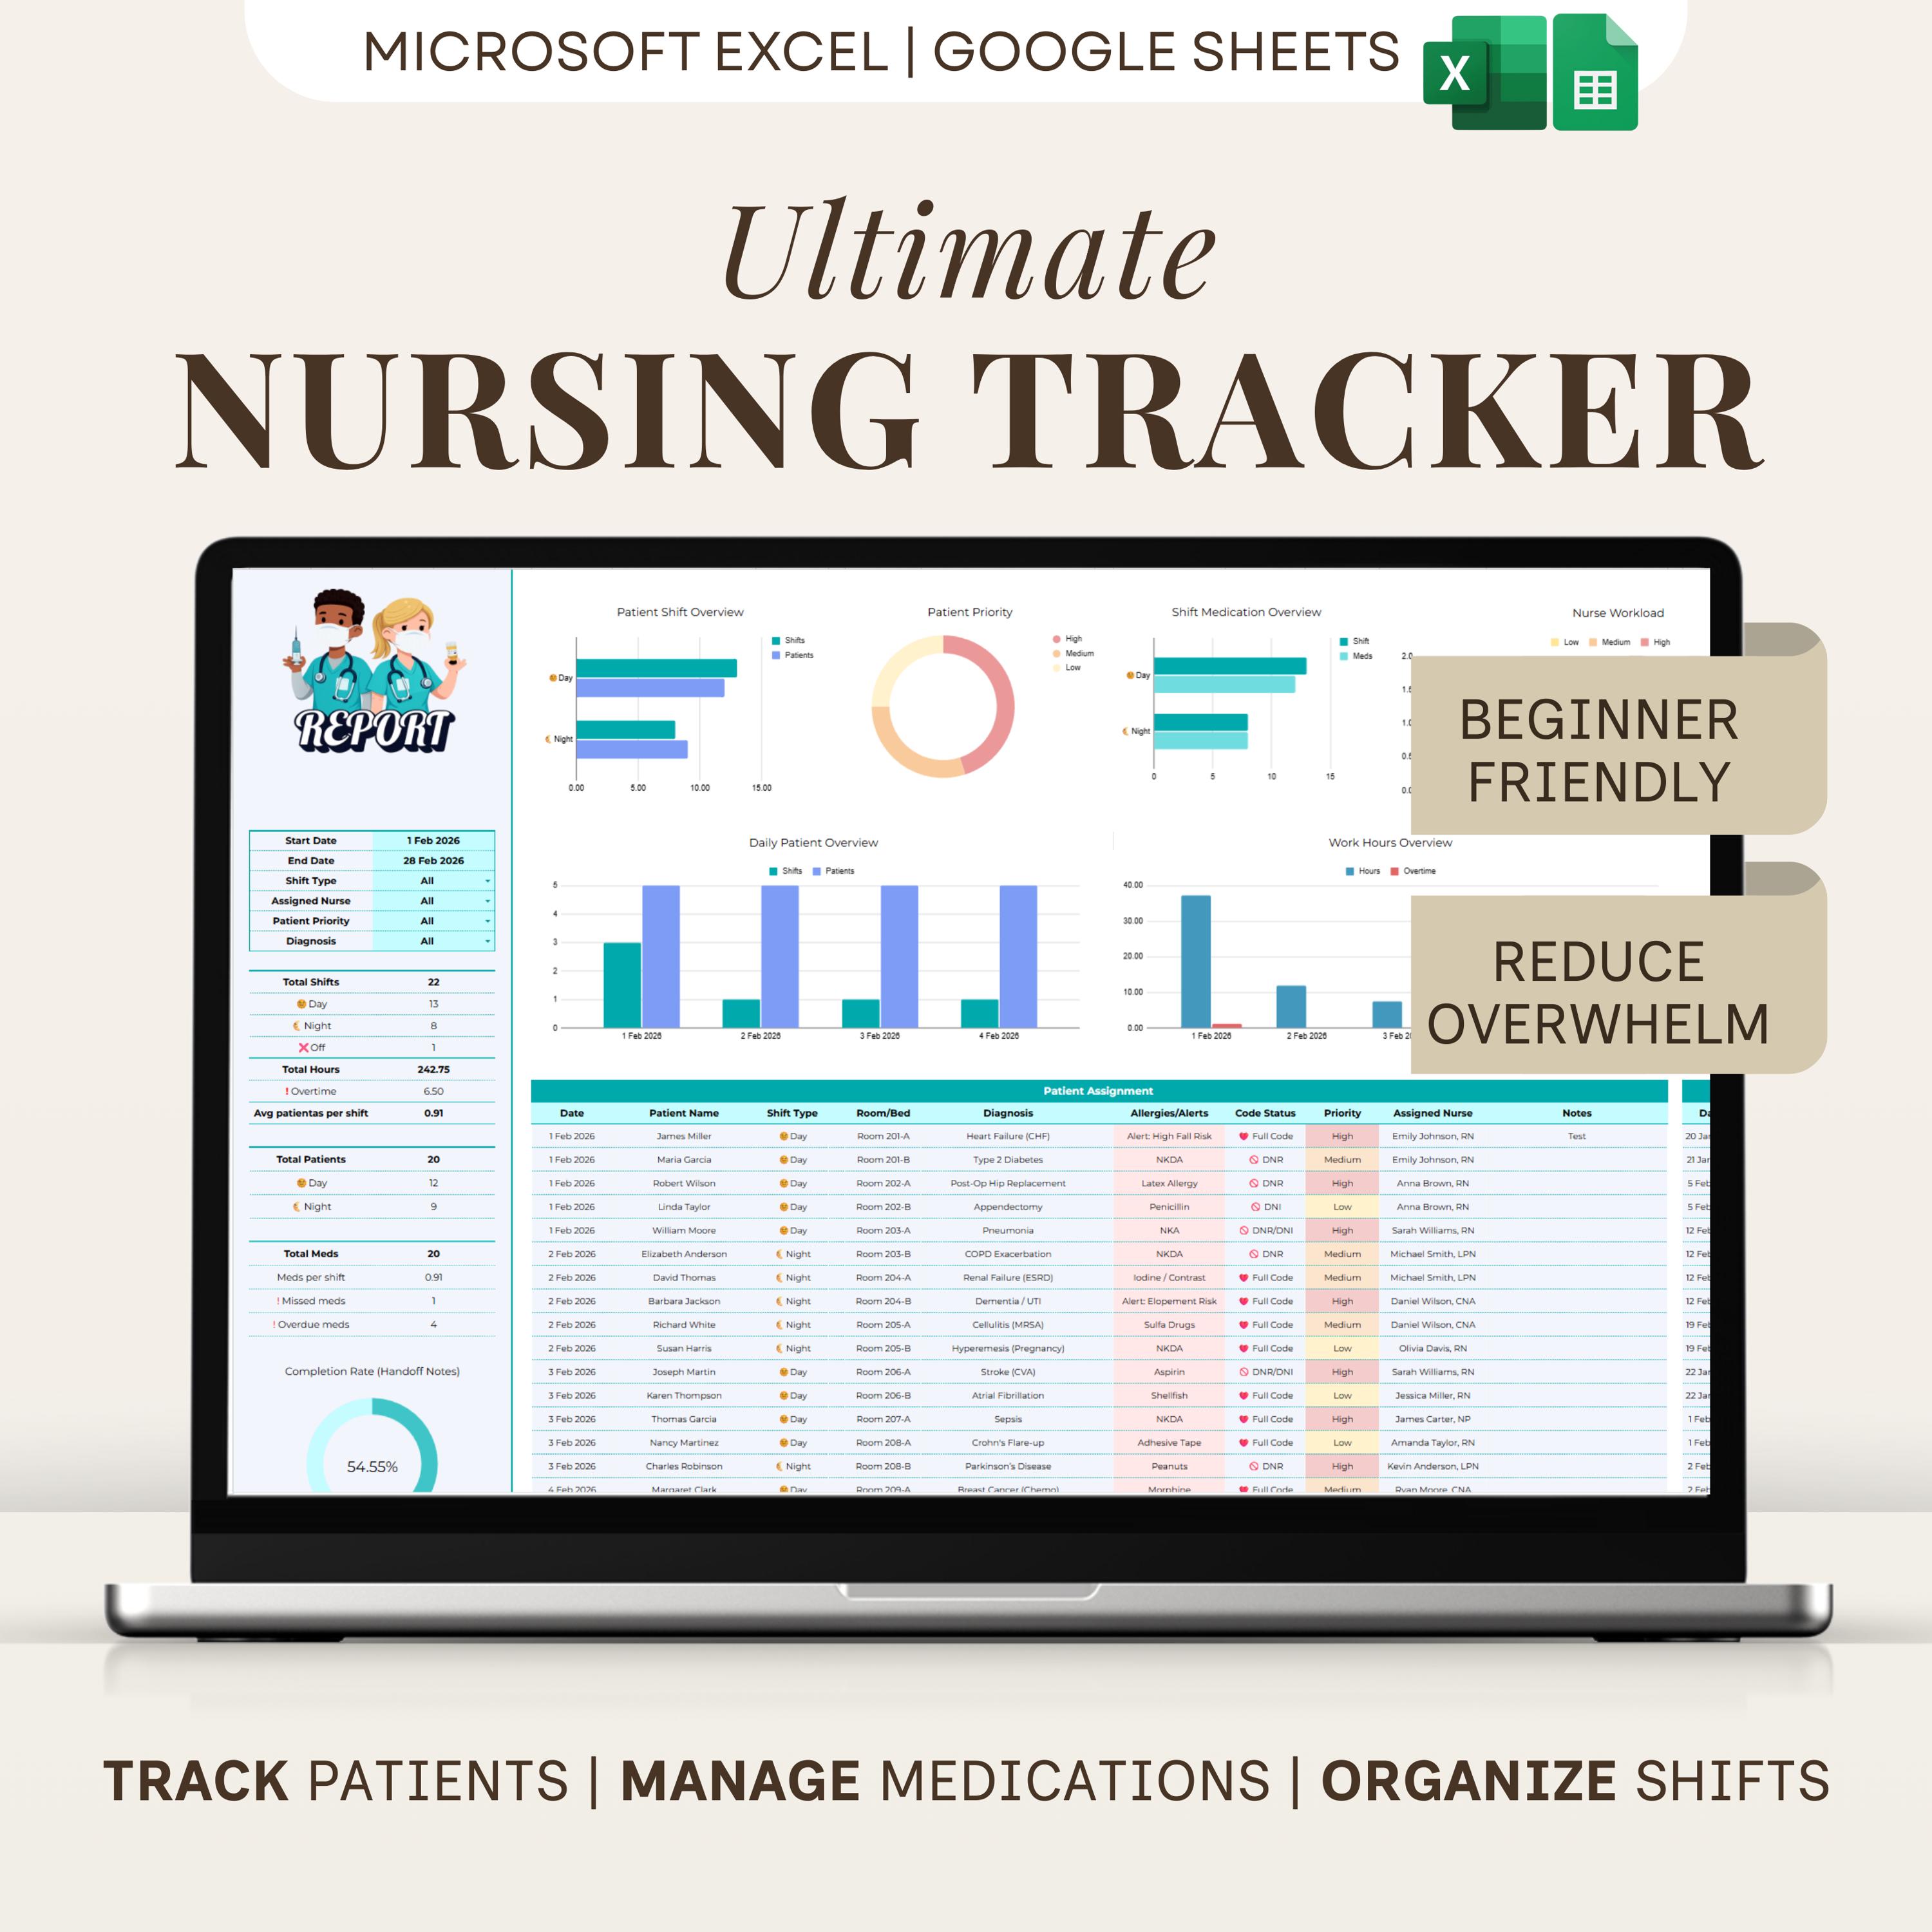
Start with one sheet per patient if you are using a spreadsheet platform. Each sheet should have the data points from Step 1 laid out in columns with rows for each shift entry. Include a summary tab that pulls the most recent values from each patient sheet using lookup functions. Set up conditional formatting that flags abnormal values. Blood pressure below 90 systolic turns red. Pain score above 7 turns orange. This takes about ten minutes to configure and saves you from scrolling through fifty rows to find something urgent. For medication tracking, I use a separate sheet linked by patient ID rather than embedding everything in one massive table. It keeps the file size manageable and makes it easier to audit medication administration records independently.
Step 4: Test It Before Live Use
Run the tracker for one full week with dummy data or one volunteer patient. You will find issues immediately. The formula for calculating intake and output assumes every entry is in milliliters, but someone enters ounces. The lookup function breaks when a patient is discharged and a new one takes their room number. These are solvable problems, but you need to solve them before an actual shift change reveals them. My unit ran a test with two patients for five days. We caught three major issues: a date format mismatch between sheets, a dropped conditional format rule, and a shared-cell conflict when two nurses edited simultaneously. Fixing these took about forty-five minutes total. Not fixing them would have cost us significantly more in corrected data and frustrated staff.
A Specific Problem and the Workaround
Here is a concrete example of something going wrong in practice. I was tracking fall risk using Morse scores updated every shift. The problem: when a patient's condition changed mid-shift, the score on the tracker did not reflect the change until the next nurse documented it. A patient was classified as low fall risk at 1400 hours after a fall assessment, but by 1800 hours they had become confused and restless due to medication side effects. The tracker still showed low risk until the night shift updated it. That six-hour gap was unacceptable. The workaround was adding a timestamp field alongside the Morse score and creating a simple conditional rule that highlighted any score unchanged for more than four hours in amber. This does not prevent the issue entirely, but it makes it visible. The night shift nurse saw the amber flag and re-assessed the patient immediately. The updated score was high risk, and we implemented additional precautions before anything bad happened. This is the kind of edge case you only find after the system is live. Plan for it.
Common Pitfalls and How to Avoid Them
Overcomplicating the fields. Every extra field is a chance for someone to skip it or enter wrong data. Keep the required fields to the minimum that covers safety-critical information. Optional fields can be added in a notes column. Not training the team. A tracker is only as good as the people entering data. Spend one shift doing a walkthrough with everyone on the floor. Show them where to enter data, how to interpret the color coding, and what to do when the system flags something unusual. Do not assume they will figure it out from a printed one-page guide. Ignoring data security. If you are tracking real patient information, HIPAA compliance is not optional. Use encrypted cloud storage. Limit access to authorized personnel only. Do not keep paper copies of the tracker in a break room. I saw a unit do all three of these things in the same month.
Not establishing a review cadence. The tracker becomes useless the moment someone stops updating it. Schedule a brief end-of-shift check where the incoming nurse verifies the data against the EHR before taking over. This takes about five minutes and prevents the situation where you discover three days of missing data on a Monday morning.

When a Nursing Tracker Is Not the Right Tool
There are scenarios where building a custom tracker is the wrong choice. If your facility already has a robust EHR with built-in clinical dashboards, adding an external tracker creates redundancy and increases the chance of data inconsistency. In that case, invest time in learning the EHR's reporting and alerting features rather than building something outside it. Small teams of three or fewer nurses managing a low-acuity patient population may not need a formal tracker. Simple shift notes in a shared document can suffice. The overhead of maintaining a dedicated tracking system is not justified when the data volume is low and the risk profile is minimal.
Files and Resources
I do not have a direct download link to share here, but the template structure I described can be built in any spreadsheet platform. Start with the fields listed in Step 1, add the conditional formatting rules, and iterate based on your team's feedback. The key is starting simple and expanding only when you have a proven need for additional fields. Several nursing informatics groups on professional forums share template files. Searching for "nurse shift handoff tracker template" on sites like Reddit's r/nursing or specialized nursing informatics communities will surface files that other nurses have already tested in real clinical settings. These tend to be more practical than anything I or anyone else could design in a vacuum.
The Bottom Line
A well-built Nursing Tracker reduces handoff errors, improves communication between shifts, and gives you a visible record of patient trends across days. It does not replace clinical judgment. It does not automate anything. It is a tool for organizing information that already exists in your head and in your EHR into something that transfers cleanly from one person to another. Build it slowly. Test it before relying on it. Keep the fields minimal. Train your team on it. Review it regularly. These are not tips. They are the difference between a tracker that gets used and one that becomes digital clutter.