Documenting Progress in OASAS-Compliant Systems
I spent three weeks last year trying to figure out why my clinic's reimbursement claims kept getting rejected on documentation grounds. It turned out to be a single progress note that didn't meet Oasas Guide For Progress Notes standards. One patient encounter, one sloppy note, and about $4,200 in denied claims. That experience changed how I approach every single chart entry after that. OASAS progress notes are the daily written record of client interaction in addiction treatment settings regulated by New York State's Office of Addiction Services and Supports. They serve as both clinical documentation and billing evidence. The system requires specific elements to be present in each note or the entire encounter can be considered undocumented for audit purposes. This matters because OASAS audits are real and they can recover funds retroactively for up to three years.
The Oasas Guide For Progress Notes Structure
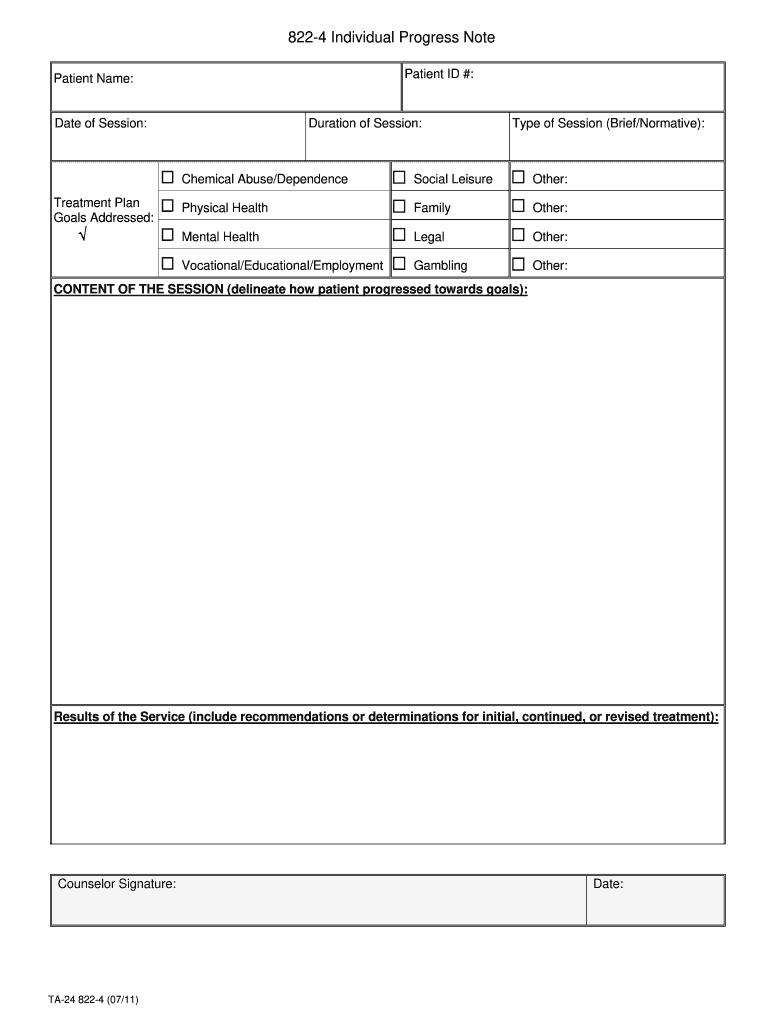
A compliant note needs five core components: identifying information, the intervention delivered, the client's response, the clinical assessment of that response, and the plan moving forward. That's it. Most people overcomplicate this. I've seen notes that read like novels with 30 paragraphs about a medication check that took eight minutes. That's not better documentation. That's just harder to defend when an auditor asks whether the note supports the billed CPT code. The identifying information section means date, time in, time out, client name or ID, and the staff member writing the note. Time in and time out matter more than people realize. OASAS cross-references documented minutes against billed units. If you wrote 45 minutes but billed 60, that's a red flag. If you billed 30 minutes and documented 15, you just committed fraud whether you meant to or not. I had a supervisor once who used to tell new staff to clock out, read the note, then clock back in to verify the math matched. It took 30 seconds and prevented problems.
Interventions and Response Documentation
The intervention section should name what actually happened. Group counseling session with CBT techniques focusing on relapse prevention. Individual motivational interviewing. Case management meeting. Medication check. Each intervention type maps to different billing codes and each has different documentation expectations. A group note does not need the same depth as an individual session note, but it does need to demonstrate that every billed participant was actually present and engaged. I ran into a specific problem last spring where a client was marked present in group attendance but had walked out at the 20-minute mark because they were having a panic attack. The note just said "client presented appropriately throughout session." An auditor flagged that as unverifiable. My workaround was to add a brief behavioral descriptor when clients left early or showed significant distress. "Client exhibited anxious affect, remained in group for 40 of 60 minutes before departing." It didn't require extra billing steps and it gave auditors something concrete to look at instead of guessing. That one habit alone probably saved us from two denial letters in the following audit cycle. The client response section is where most notes fail. Writing "client was cooperative" tells an auditor nothing about what actually occurred during the intervention. You need observable, documentable behavior. "Client identified three trigger situations from the morning's worksheet" is specific enough to defend. "Client discussed feelings about recovery" is not, because anyone can discuss feelings and it proves nothing about the intervention's delivery or the client's engagement level.
Get the Full Details

Clinical Assessment and Forward Planning
The assessment portion requires you to evaluate the client's progress toward their treatment plan goals. This doesn't need to be a novel. Two or three sentences connecting what happened in the session to the documented treatment objectives is sufficient. "Client demonstrated ability to identify cognitive distortions related to substance use, progressing toward goal of reducing automatic negative thoughts by 50 percent as measured by weekly self-report scales." That's one sentence that does three jobs: it references the intervention skill, it ties to a treatment plan goal, and it includes a measurable indicator. The plan section is often afterthoughted. It should state what happens next and why. "Continue weekly individual MI sessions with focus on ambivalence around sobriety. Schedule probation officer consultation next week to address testing compliance concerns." This shows continuity of care and justifies why the next encounter is clinically necessary. Without this, an auditor might question whether subsequent sessions were redundant or unnecessarily prolonged.
Common Pitfalls and Workarounds
Copied notes are the biggest problem. OASAS systems have template features and some electronic health record platforms allow note borrowing. Both are legitimate tools when used correctly. They become problematic when staff copy a note from three weeks ago and only change the date and the client's name without updating the content. I reviewed a batch of notes last fall where four different clients had nearly identical intervention descriptions word for word. The auditor didn't need a forensic specialist to spot that pattern. The workaround is simple: use templates for structure, not content. Fill in the intervention and response sections each time based on what actually happened that day. Another issue is the timing gap between when notes are written and when encounters occur. OASAS expects contemporaneous documentation, meaning notes should be completed within the same shift or within 24 hours at most. I've seen clinics allow notes to sit in a "draft" queue for up to a week. This creates two problems. Memory fades and you forget details that matter for specificity. Second, if an audit lands and you're producing notes dated weeks after the encounter, you're defending a practice that doesn't meet the standard regardless of whether the content was accurate. There's also the staffing documentation problem. When a client is seen by a clinician who isn't the one entering the note, the note needs to reflect who actually provided the service. I worked at a site where a supervisor would complete notes for counselors who were out on personal leave. The notes were clinically sound but the signature block showed the counselor's name while the supervisor did the data entry. OASAS audits sometimes flag this as billing misrepresentation because the documented provider wasn't the documented note-taker. The fix was having the absent counselor complete a brief verbal summary that the supervisor then transcribed, with both names reflected appropriately in the encounter record.
Billing Alignment
Every progress note must align with the billing code submitted for that encounter. This is where people get tripped up because OASAS doesn't just want documentation to exist. It wants documentation that supports the specific code. A 90-minute group session billed as a standard group counseling code needs a note that reflects the full duration and the group format. If the note only documents 45 minutes of actual activity because half the group was on break, billing the full code is unsupported documentation. Don't do that. The reverse problem is just as common. Clinicians will write extensive individual therapy notes and then accidentally bill a group code because they selected the wrong service type in the billing module. The note and the code don't match and the claim gets denied. I suggest a simple pre-bill check: open the note, confirm the service type, confirm the duration, confirm the CPT code matches both, then submit. It adds roughly 90 seconds per client and prevents the 30-day denial turnaround that follows.
What the System Doesn't Cover Well
The Oasas Guide For Progress Notes framework was designed for structured outpatient and residential programs. It doesn't handle telehealth encounters as cleanly as it handles in-person sessions. Several regions have struggled with whether a telehealth note needs additional documentation about the technology platform used, the client's location, and consent for telehealth delivery. Some auditors expect this. Some don't. The safest approach is to include a telehealth documentation line in every virtual session note: "Telehealth session conducted via secure video platform. Client consented to telehealth services per policy dated [date]." It takes five seconds and closes a common audit gap. The framework also doesn't account well for concurrent services. When a client receives case management and counseling in the same appointment window, documenting both as separate encounters requires clear time segmentation in the note. "Case management portion: 8:00 to 8:30. Counseling portion: 8:30 to 9:15." Without that segmentation, an auditor may view the combined time as a single encounter billed twice, which is technically double billing even if both services were genuinely provided. I've found that the most efficient way to maintain compliant OASAS progress notes is to build a personal checklist and run through it before signing out of any note. Identifying info complete, intervention clearly named, response specifically described, assessment tied to treatment goals, plan states next steps, duration matches billing, provider matches service. That's it. Takes about 20 seconds per note and it's the difference between clean audit results and three weeks of scrambling to fix documentation gaps.
If you need the current official guidance, the OASAS website publishes their documentation standards directly. Search for "OASAS progress note requirements" on oasas.ny.gov and you'll find the latest version. These guidelines update periodically so treat them as living documents rather than one-time reading material. The core structure hasn't changed much in years but the billing code mappings and telehealth provisions have shifted a few times since I started doing this work.