Why Everyone Keeps Asking About Ob Gyn Coding Cheat Sheets
Most people looking for Ob Gyn Coding Cheat Sheets are either new coders who got burned on a complex delivery claim or billing managers who need something faster than flipping through the CPT manual for the fifteenth time that day. The reality is that ob/gyn coding has some of the narrowest margins in the entire E/M landscape, and being wrong by even one digit on a C-section type or a modifier can trigger a denial that takes three weeks to reverse. I spent years doing this work, and the cheat sheet you actually need isn't a single printable PDF. It's a living document that tracks CPT code families, ICD-10-CM combination codes for OB encounters, and the modifier combos that auditors actually flag. Here's how to build one that survives real-world use.
Building Ob Gyn Coding Cheat Sheets That Actually Work
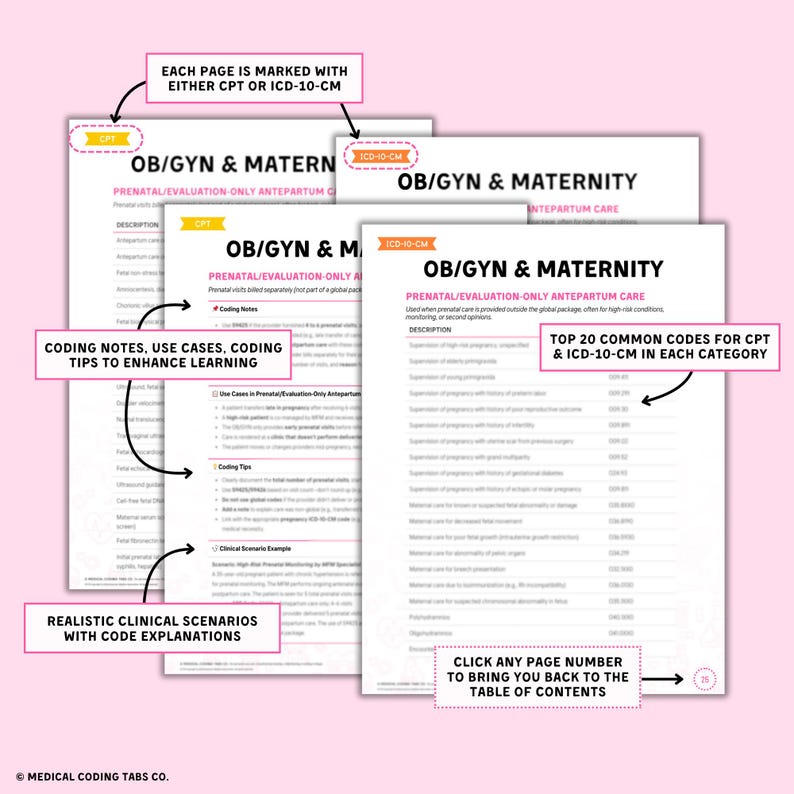
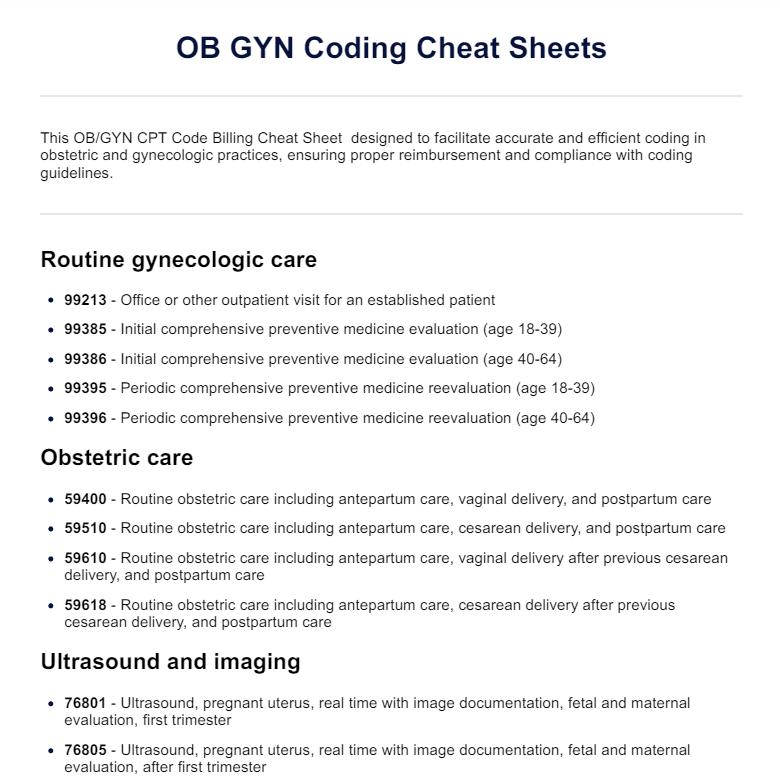
Start with the three code families that will eat your day if you get them wrong: obstetric delivery codes, antepartum/postpartum bundling rules, and the gynecological surgical package guidelines. Don't add anything else until those are locked down. The most common mistake I see is people including every CPT code that ever appears in an ob/gyn clinic. That creates a 40-page reference nobody reads. The effective cheat sheets are structured by encounter type, not alphabetically. A prenatal visit, a high-risk pregnancy management visit, a colposcopy with biopsy, a D&C — each gets its own section with the correct CPT, the typical ICD-10-CM codes that pair with it, the documentation requirements, and the modifier situations. For the OB delivery section specifically, here's what matters. Codes 59400 through 59618 are split by whether it's vaginal or cesarean, whether there were complications, and whether the physician provided only the postpartum portion. Modifier 54 goes on the surgical portion when another provider handles postoperative care. Modifier 55 goes the other direction. Get these swapped and the claim doesn't just get denied — it looks like fraud to a scraper algorithm.
I learned this the hard way on a triplet delivery in 2019. The chart clearly showed a primary surgeon and a co-surgeon working together. I coded it with modifier 62 initially, then caught myself because co-surgery modifiers don't belong on delivery codes. The correct path was 59620 with appropriate split-surgery documentation. That single correction saved the practice about four thousand dollars on that claim alone. The cheat sheet I rebuilt after that error now has a dedicated modifier flowchart for multiple-provider scenarios. For antepartum care, the ICD-10-CM chapter 15 codes (O09 through O48) are where most errors accumulate. Each trimester has specific default codes, and Zcodes for routine prenatal visits only work when there are no complications documented. A coder who puts Z34.00 against a chart showing gestational hypertension is going to get flagged in an audit. The cheat sheet needs a cross-reference table showing which complication codes override the routine prenatal codes.
Get the Full Details

The Gynecological Side and the Surgical Package Trap
Gynecology coding is less confusing than OB but has its own landmines. The key is understanding the global surgical package defined in the CPT book. A standard D&C, hysteroscopy, or colposcopy with biopsy is bundled into a 90-day global period for most of these procedures. That means any follow-up visit, diagnostic test, or minor procedure during that window is already paid for in the original code. Billing it separately is an overpayment risk. Here's a detail most cheat sheets skip: the exception for medically necessary E/M visits during the global period. If the patient returns with a new problem unrelated to the surgical indication, you can bill that E/M with modifier 24. But the documentation has to explicitly separate the surgical issue from the new issue. Vague notes like "patient returns for follow-up, complains of headaches" won't satisfy a reviewer. You need a separate diagnosis, a separate assessment, and a clear statement that the headache management is unrelated to the recent procedure. The colposcopy-to-LEEP sequence is another area where coders consistently lose money or create compliance exposure. If a colposcopy with directed biopsy is performed and the same physician later does a LEEP on the same anatomical site during the global period, the colposcopy is included in the LEEP. You code only the LEEP. But if a different physician did the colposcopy, or if the LEEP was on a completely different site, then both codes may be appropriate with modifier 59 or XP as needed. This distinction isn't obvious unless you've seen a denial for unbundling and another for missed separate billing.
What No Cheat Sheet Covers (And Why You Need More Than One)
The honest limitation of any Ob Gyn Coding Cheat Sheets resource is that it can't keep pace with annual CPT and ICD-10 updates without active maintenance. The 2024 changes to E/M visit selection for office visits affected some ob/gyn follow-up coding, and the 2025 updates shifted coverage policies around certain maternal-fetal surgery procedures. A static PDF is a liability after December 31st every year. Another blind spot is payer-specific variation. Medicare has one set of rules for gestational diabetes management (O24.41), but many commercial payers still follow older guidance that bundles glucose tolerance testing into prenatal visit codes. A cheat sheet that works for one payer will fail for another. The workaround is maintaining a payer matrix as a separate tab alongside the clinical coding content. If your volume is low enough that a custom cheat sheet isn't worth building, the closest ready-made option is the ACOG-coded reference materials combined with the CMS Physician Fee Schedule lookup tool. Neither is perfect. ACOG's materials are clinically comprehensive but thin on billing mechanics. CMS gives you the payment rules but assumes you already know which codes apply to which conditions. Using both together covers roughly eighty percent of daily coding scenarios.
The remaining twenty percent is where you need the modifier flowchart and the ICD-10 cross-reference table I mentioned earlier. Those two elements are what separate a functional reference from a printed CPT excerpt that sits on someone's desk and gets used exactly once. A practical note on file format. Build yours as a searchable spreadsheet rather than a PDF. When a coder is mid-claim and needs to verify whether modifier 50 applies to a bilateral salpingectomy versus a unilateral with contralateral procedure, a search function beats a flip-through every time. Name the columns clearly: CPT, description, global days, common ICD-10 pairings, modifiers, bundling notes, and payer exceptions. Six columns is enough. More than that and nobody maintains it.