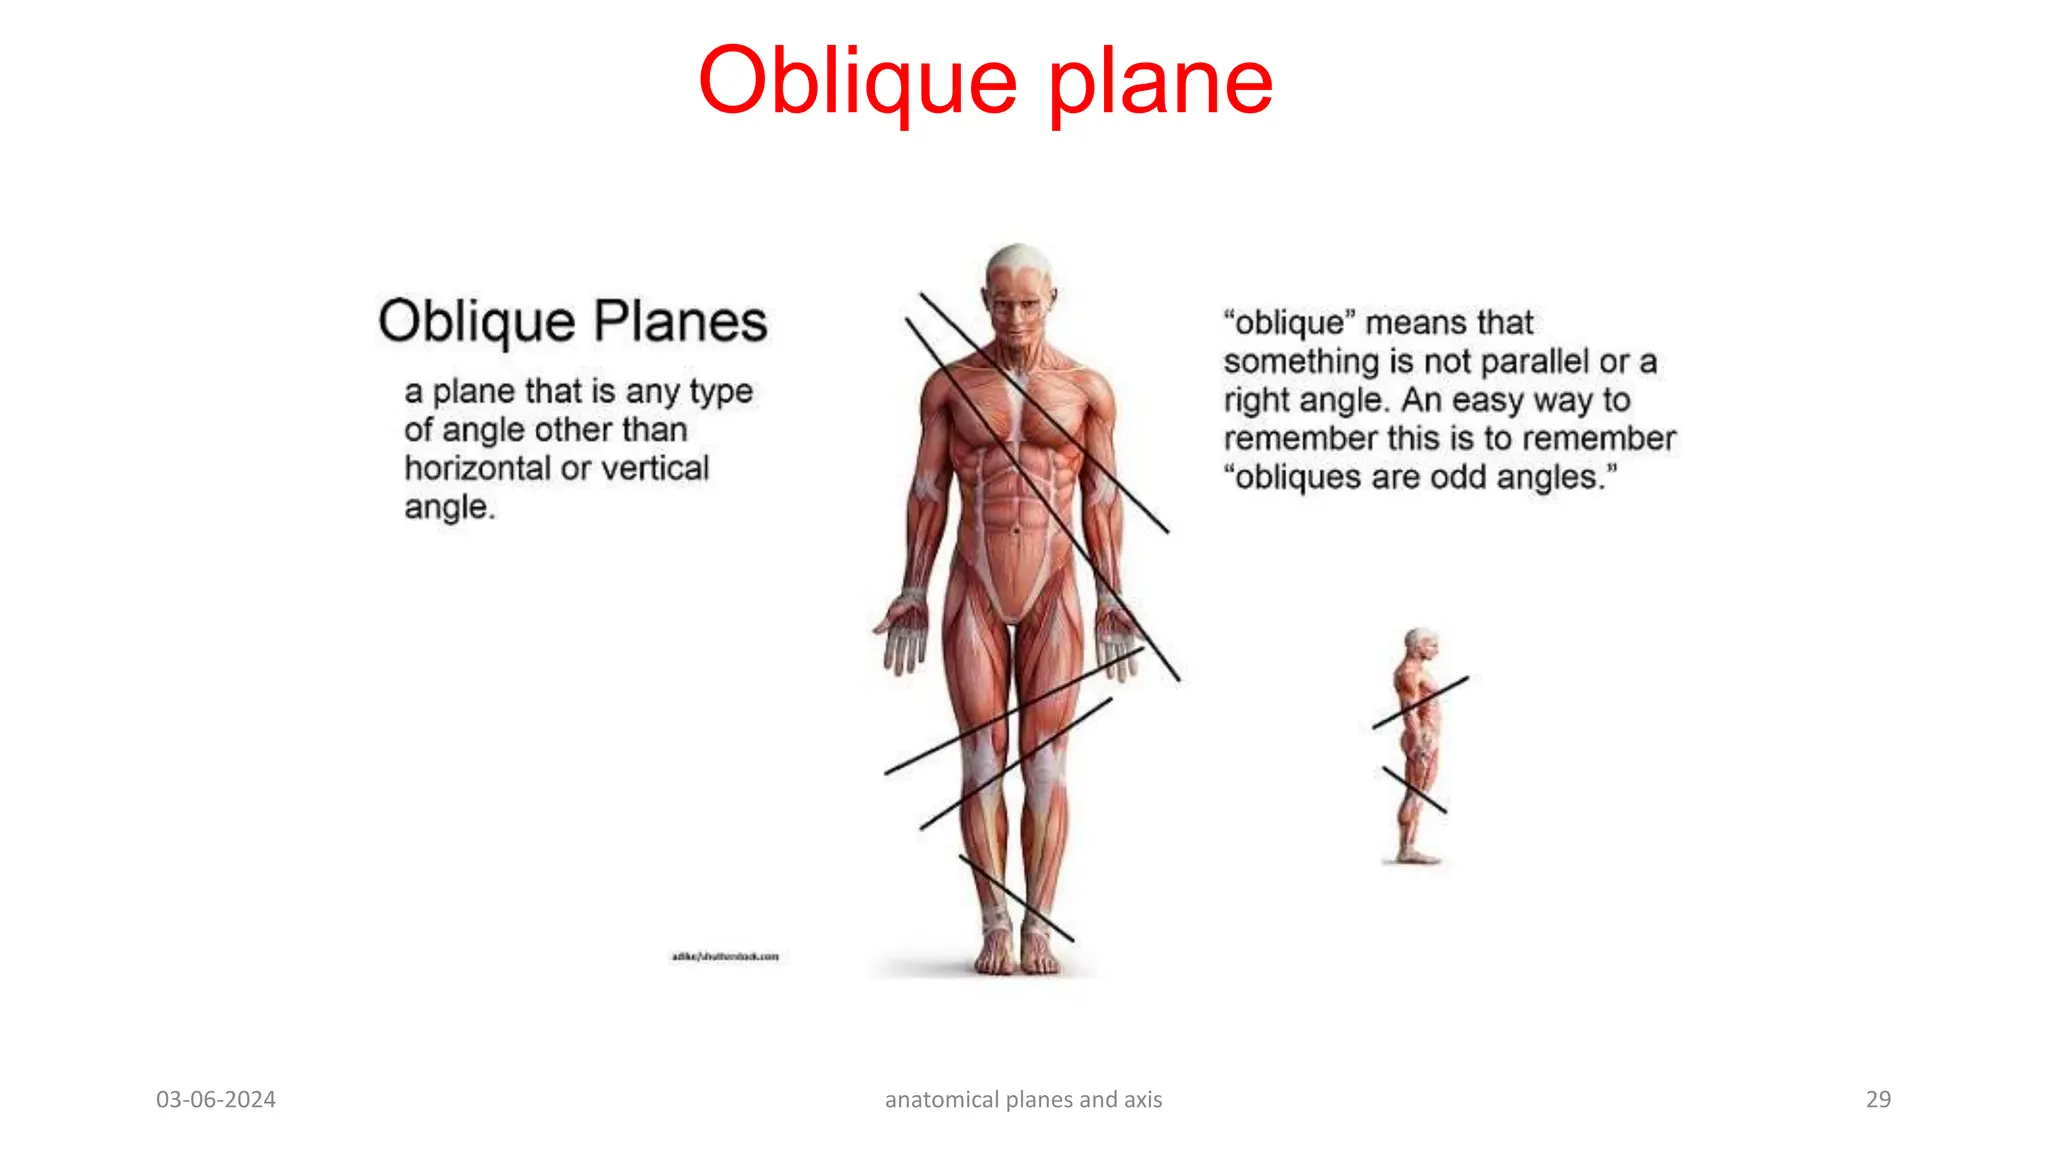
Understanding Oblique Planes in Anatomical Imaging
The standard anatomical planes—sagittal, coronal, and axial—are the foundation of medical imaging, but they don't capture everything. Oblique planes cut through the body at angles that don't align with those three primary axes, and they matter more than most people give them credit for. When you're trying to visualize the heart valves, the liver vasculature, or certain joints, straight-up axial or coronal slices just miss the geometry of the structure you're looking at. I spent years reading cardiac MRIs before I really understood why my radiology colleagues would reformat a scan in oblique views. The interventricular septum, for instance, runs at roughly a 45-degree angle relative to the standard anatomical planes. If you're measuring septal thickness on a plain axial slice, your numbers are going to be wrong because you're not getting a true cross-section. You get a foreshortened view that underestimates the actual dimension. This is exactly the kind of thing that trips up residents early on and sometimes even experienced techs who stick rigidly to standard planes out of habit. The way to approach oblique imaging is pragmatic. You start with a standard localizer or scout view, identify the structure you care about, and then manually tilt the imaging plane to align with the long axis or short axis of that structure. On modern CT and MRI systems, this is straightforward—most scanners let you define oblique cuts directly from the initial sagittal or coronal localizer. The trick is knowing which structure to align with and what angle you're actually aiming for.
When and Where Oblique Planes Actually Help
Certain anatomical regions routinely demand oblique reformatting. The heart is the big one. Short-axis, two-chamber, and four-chamber views are all oblique by nature. Cardiac CT and MRI protocols build these in automatically now, but if you're doing a routine abdominal CT and want to look at the hepatic veins draining into the IVC, you're going to need an oblique plane that follows the actual trajectory of those vessels. The same goes for the portal vein and its branches, which course obliquely through the liver. Knee imaging is another area where oblique planes show up constantly. The ACL inserts on the posterior aspect of the lateral femoral condyle at an angle that standard sagittal slices can partially miss depending on patient positioning. Many protocols prescribe a dedicated sagittal-oblique plane aligned to the ACL's long axis, and when you do that, you see the entire ligament course instead of intermittent partial-volume appearances. Shoulder MRIs use oblique axial and oblique coronal planes routinely. The supraspinatus tendon, which is the most commonly torn rotator cuff tendon, doesn't run purely medial-to-lateral in most people. It has an oblique trajectory, and the standard axial plane cuts through it at an angle that makes tendinopathy harder to grade accurately. The oblique coronal view, sometimes called the "true coronal" oblique, gives you a cleaner look at the full width of the tendon.
Common Pitfalls and What I Learned the Hard Way
One edge case that cost me a lot of time early in my career involved a liver lesion. I was reviewing a CT for metastatic workup and kept finding a suspicious area in segment VII that looked more prominent on oblique reconstructions than on the standard axial images. I initially thought this was a real finding, so I marked it and flagged it. Turns out it was a partial volume artifact caused by the diaphragm curvature intersecting the liver dome at an angle. On the oblique plane, the artifact was exaggerated because I was cutting through the interface at a shallower angle, creating a band of mixed signal that looked like a mass. The workaround was simple once I knew what I was looking for. Always correlate oblique findings back to the original axial data. Never diagnose from a reformatted plane alone. If something shows up on an oblique view, switch back to the unprocessed axial slices and see if it persists. Most of the time it either disappears or becomes clearly artifactual. That rule has saved me from chasing false positives ever since. Another pitfall is assuming that oblique means better for everything. It doesn't. Oblique planes introduce interpolation artifacts because the scanner's raw data is acquired in a standard grid, and any reformation away from that grid requires mathematical interpolation. The more oblique you go, the more you're relying on the system to estimate what's between the actual acquisition slices. At extreme angles, you start losing spatial resolution and introducing streak artifacts, particularly on CT. In practice, I find that anything beyond 30 to 40 degrees from a standard plane starts degrading image quality noticeably on most clinical scanners.
Get the Full Details

How to Set Up Oblique Planes Correctly
The process varies slightly between modalities, but the principle is the same. On MRI and CT post-processing workstations, you typically enter a multiplanar reformation (MPR) mode. You'll see the standard three orthogonal views displayed simultaneously. You then place calipers or a line on one of the reference views to define your new plane. For cardiac work, the system usually has preset templates. For everything else, you're doing it manually. Here's the practical part that textbooks don't always emphasize: define your oblique plane from the first available image, not from a reformatted image. If you build an oblique plane off of an already-reformatted oblique, you're compounding interpolation errors. Go back to the original source data every time. This is especially important on thin-slice CT where the z-axis resolution is already limited. For ultrasound, oblique planes aren't a post-processing decision—you're setting them at the point of acquisition. The sonographer tilts the transducer to angulate the beam. This is where proper technique matters most because unlike CT and MRI, you can't reformat retrospectively. If the probe angle is wrong, the structure you're trying to see will be cut obliquely in an uncontrolled way, and you'll just get a confusing cross-section. I've seen this constantly with gallbladder imaging where the sonographer doesn't angulate enough to get the true long axis, and the gallbladder appears foreshortened and the wall looks artificially thickened.
Limits of Oblique Reformatting
Oblique planes are useful but they have hard constraints. The biggest one is that they don't create new information. If your original acquisition has 5mm slices and there's a 3mm lesion oriented perpendicular to the plane, reformmingating obliquely won't make it visible. You need adequate through-plane resolution to begin with. For that reason, thin-slice acquisition—1mm or less on CT, high-resolution sequences on MRI—is almost always worth the extra scan time if you anticipate needing oblique views. Another limitation is inter-reader variability. When two sonographers measure the same structure using different oblique angles, their measurements can differ significantly. This is a well-documented problem in echocardiography and applies to any imaging where the oblique plane is defined manually rather than by a rigid template. Standardization helps, which is why professional societies have published guidelines for plane alignment in cardiac and musculoskeletal imaging. Following those guidelines reduces variability but doesn't eliminate it entirely. If you're working in a resource-limited setting where retrospective reformating isn't available, the alternative is to optimize your acquisition planes during the initial scan. This means learning to anticipate which oblique angles you'll need and setting them up in real time. It takes more skill upfront but avoids the compromise of trying to reconstruct information that was never properly captured.