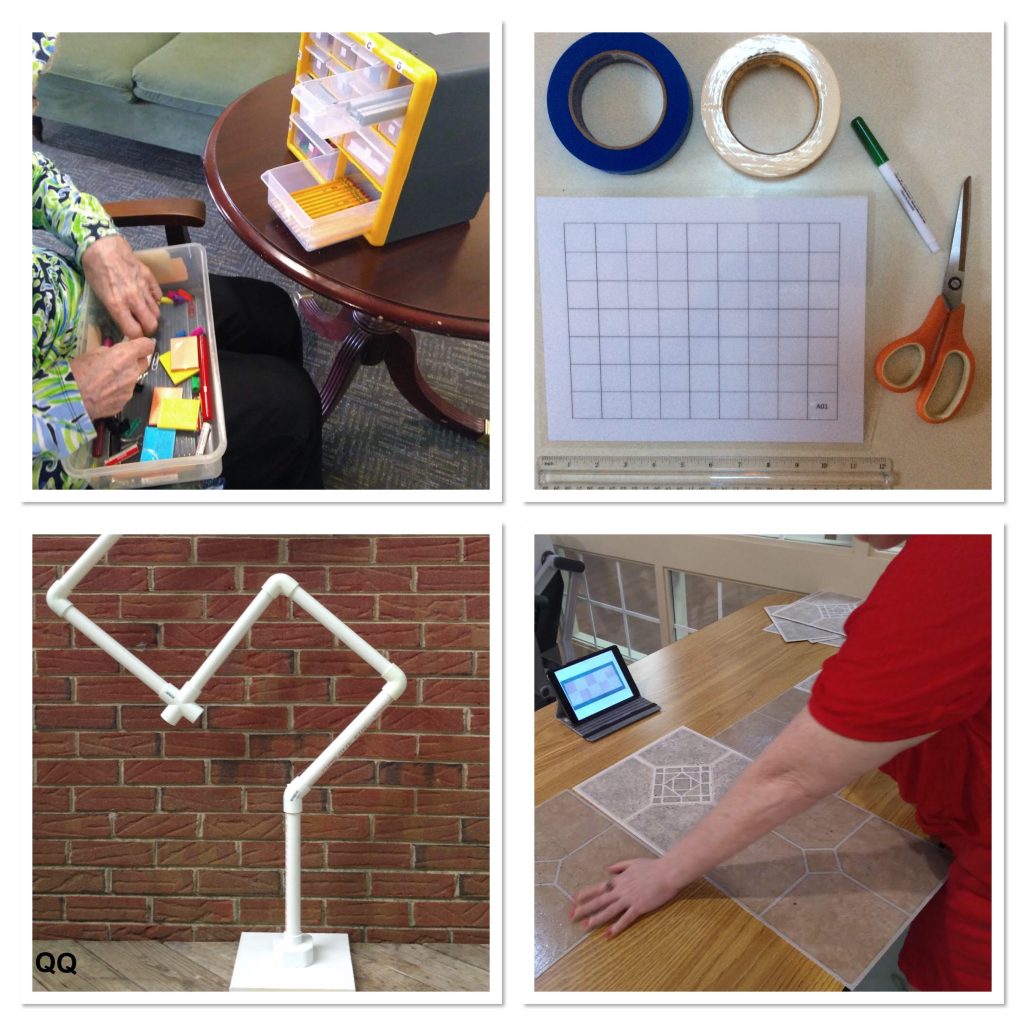
What Actually Happens in an Adult OT Session
Most people walk into occupational therapy expecting to be given crafts to do, but the reality is far more clinical. An adult patient isn't sitting at a table making friendship bracelets. They are working through functional movement patterns that have been compromised by stroke, injury, surgery, or neurodegenerative disease. The activities are exercises disguised as tasks, and the therapist has spent years learning how to make the distinction disappear so the patient doesn't check out mentally. I worked in a neurorehab unit for several years, and the hardest thing to manage wasn't the physical deficits. It was keeping patients engaged when the tasks felt meaningless to them. A patient recovering from a left MCA stroke doesn't care about buttoning a board. They care about dressing themselves so they can leave the hospital. The bridge between those two things is where the actual work happens.
How to Choose Occupational Therapy Activities For Adults
The selection process starts with a thorough evaluation of fine motor control, range of motion, cognitive load tolerance, and the patient's specific goals. I use the Modified Ashworth Scale for spasticity, the Fugl-Meyer Assessment for post-stroke motor recovery, and the Mini-Mental State Exam or MoCA for cognitive screening. These give you a baseline, but the baseline is just a starting point. The real guide is what the patient says they need to do in their daily life. Here is a practical breakdown of activity categories and what they target: Gross motor and coordination activities cover reaching, grasping, lifting, and weight shifting. These are essential for patients with hemiparesis or deconditioning after prolonged hospitalization. Adaptive equipment like weighted utensils, built-up handles, and reachers fall into this bucket. A common pitfall is underestimating how much fatigue impacts gross motor performance in the first three weeks of rehab. Patients often have decent strength on day one and cannot sustain it by day five. Pacing the activity blocks matters more than the activity itself.
Fine motor and dexterity activities involve finger isolation, pinch strength, and bilateral coordination. Therapeutic putty, pegboards, and simulated ADL (activities of daily living) tasks like stacking coins or turning keys are standard tools. The edge case I run into most often is patients with compensatory strategies that look successful but are actually reinforcing maladaptive movement patterns. A patient might complete a pegboard task using shoulder hiking and trunk rotation instead of isolated finger movement. I catch this by observing the proximal muscles, not just the distal outcome. If the shoulder is moving, the fingers aren't doing the work independently, and the carryover to real-world function is minimal. Cognitive and executive functioning activities address planning, sequencing, problem-solving, and attention. These are critical for traumatic brain injury patients and older adults with early-stage dementia. Cooking a simple recipe, managing a pretend medication schedule, and completing multi-step sorting tasks are common interventions. The counter-intuitive part here is that patients with memory deficits often perform better on familiar, routine-based tasks than on novel problem-solving exercises. Building activities around the patient's existing routines produces faster functional gains than introducing new cognitive challenges from scratch. Sensory integration activities target proprioceptive feedback, tactile discrimination, and vestibular processing. Weighted vests, textured surfaces, and resistance bands are commonly used. This category is heavily underutilized in adult settings because therapists are trained in medical models rather than sensory processing frameworks. Adult patients with peripheral neuropathy or phantom limb pain benefit significantly from graded sensory re-education protocols, but most generalist OT programs skip this entirely.
Get the Full Details

Structuring a Session That Actually Works
A typical 45-minute session follows a predictable arc, but the pacing within that arc is where most programs fail. I structure mine with a five-minute orientation and goal-setting period, twenty minutes of primary activity work, ten minutes of compensatory strategy training, and the remainder for cool-down and documentation. The primary activity block is where the measurable progress happens, and it needs to be protected from interruptions. Temperature and environment matter more than people admit. A room that is too warm increases fatigue and reduces cognitive processing speed in stroke patients. I keep my therapy space between 68 and 70 degrees Fahrenheit. Ambient noise should be minimal. Background music sometimes helps with anxiety but frequently distracts patients working on cognitive tasks. I turn it off during precision activities and leave it on during gross motor work if the patient prefers it. The documentation burden is real. Every minute spent charting is a minute not spent treating. I use template-based notes with structured data fields rather than free-form narrative. This cuts my documentation time from roughly twenty minutes per patient to about six minutes without losing clinically relevant information. The key is capturing metrics at the point of care rather than reconstructing them afterward from memory.
Common Mistakes and What to Do Instead
The most frequent error I see is activity selection based on equipment availability rather than patient need. Just because a clinic has a complete set of TheraBand tubes and balance boards doesn't mean those tools are appropriate for every patient. A post-fracture wrist patient cannot safely use resistance tubing until the fracture is fully consolidated and the therapist has cleared progressive loading. Using the wrong modality at the wrong time delays recovery and can cause re-injury. Another mistake is pushing through fatigue instead of managing it. I had a patient with multiple sclerosis who had impressive strength metrics at the start of each session but deteriorated rapidly once her core temperature rose. We switched to shorter, more frequent sessions with active rest periods built in, and her functional gains doubled compared to the previous protocol. The activity load wasn't the problem. The recovery intervals were. Over-reliance on assistive devices is a third pitfall. When a patient is given a shower chair, grab bars, and a long-handled sponge, there is a natural tendency for both the therapist and the patient to stop attempting the movements that would restore independence. I set a rule early in treatment: assistive devices are temporary bridges, not permanent solutions. We reassess device dependence every two weeks and deliberately create opportunities for unassisted attempts within safe parameters. It slows the initial progress because the patient struggles more, but the long-term outcomes are consistently better.
Adapting Activities for Different Populations
Adult occupational therapy spans a enormous range of conditions, and no single activity set works across the board. Here is how I adjust for the most common populations I encounter: Stroke survivors need activities that address both hemiparesis and neglect. For hemiparesis, constraint-induced movement therapy principles apply even in outpatient settings. Restrainting the unaffected limb for twenty-minute blocks forces the affected side to engage, which accelerates neuroplasticity. For unilateral neglect, I use visuospatial scanning drills paired with functional tasks like reading a menu or navigating a store aisle simulation. The combination of targeted drill and real-world application produces better transfer than either method alone. Patients with hand injuries or post-surgical conditions require careful progression from edema control to range of motion to strengthening. I use a Kessler or DASH questionnaire at baseline and at two-week intervals to track subjective improvement alongside objective goniometric measurements. The DASH score tends to correlate poorly with early-range-of-motion gains, which surprises people. A patient can have full extension and flexion but still report significant disability on the DASH because grip strength and fine motor control haven't caught up. Both measures matter, and neither alone tells the full story.

Older adults with age-related functional decline benefit most from activities that simulate household management, personal care, and community mobility. I incorporate budgeting exercises, medication organization, and simulated kitchen tasks because these directly predict independent living outcomes. Fall risk assessment using the Timed Up and Go test should accompany any lower-body activity program. A patient who scores above twelve seconds on the TUG has a statistically significant fall risk, and the activity plan should include balance training before advancing to more complex tasks. Patients with psychiatric conditions require a different framework entirely. Schizophrenia, bipolar disorder, and severe depression affect motivation, executive function, and social engagement in ways that standard motor activities don't address. I use structured group activities with clear roles and predictable outcomes. Social skills training, vocational readiness exercises, and daily scheduling practice are more useful than pegboards. The pace is slower, and the metrics are qualitative rather than quantitative. Progress is measured in consistency of attendance, ability to follow multi-step instructions, and reduction in behavioral dysregulation during sessions.
Tracking Progress Without Obsessing Over It
Data collection is necessary but to overdo. I track three metrics per patient per session: activity completion rate (percentage of prescribed repetitions completed), quality of movement (rated on a simple three-point scale), and subjective effort (patient-rated on a modified Borg scale). That is it. Anything more than that creates administrative overhead without improving clinical decision-making. The review cadence matters. I do a formal progress review every two weeks, comparing current metrics to the baseline and adjusting the activity plan accordingly. Informal adjustments happen daily based on the patient's presentation that session. If a patient arrives with increased swelling or reported pain, I drop the intensity that day regardless of what the two-week plan says. The schedule is a guide, not a contract. When a patient plateaus, which happens frequently, I change one variable at a time. Usually it is the task difficulty, the repetition count, or the environmental demands. I never change three variables simultaneously and then wonder why the outcome shifted. Controlled experimentation is slow but it produces reliable data.
The field of occupational therapy for adults continues to evolve, and the evidence base keeps growing. What hasn't changed is the fundamental requirement: activities must be meaningful to the patient, appropriately challenging, and systematically progressed. Everything else is decoration.