Acute Care OT Moves Fast and Most People Are Not Ready For It
I spent over a decade on acute care floors before moving into inpatient rehab. The pace is brutal and the clinical decision-making window is often measured in minutes, not hours. A proper Occupational Therapy Acute Care Cheat Sheet is less about nice-to-have reference material and more about survival. This guide walks through what it should cover, how to use it, and where it genuinely falls apart in real hospital settings. You are seeing patients who just had surgery, who are medically unstable, who may have sepsis, who may be on pressors, and who you will likely never see again if they transfer to SNF or long-term acute care. The volume is high. The cognitive load is higher. Most new grad programs do maybe two weeks of acute care clinical. That is not enough time to build pattern recognition for which patients can tolerate a chair transfer versus which ones will desat to 82 percent on the way to the commode. An effective cheat sheet organizes by medical condition first, then by intervention type, because that is how you encounter patients. You do not think "here is a gait training opportunity." You think "here is a post-sternotomy patient with a left lower lobe pneumonia who needs to go to the bathroom in bed because she cannot safely ambulate yet." The tool should mirror that thought process.
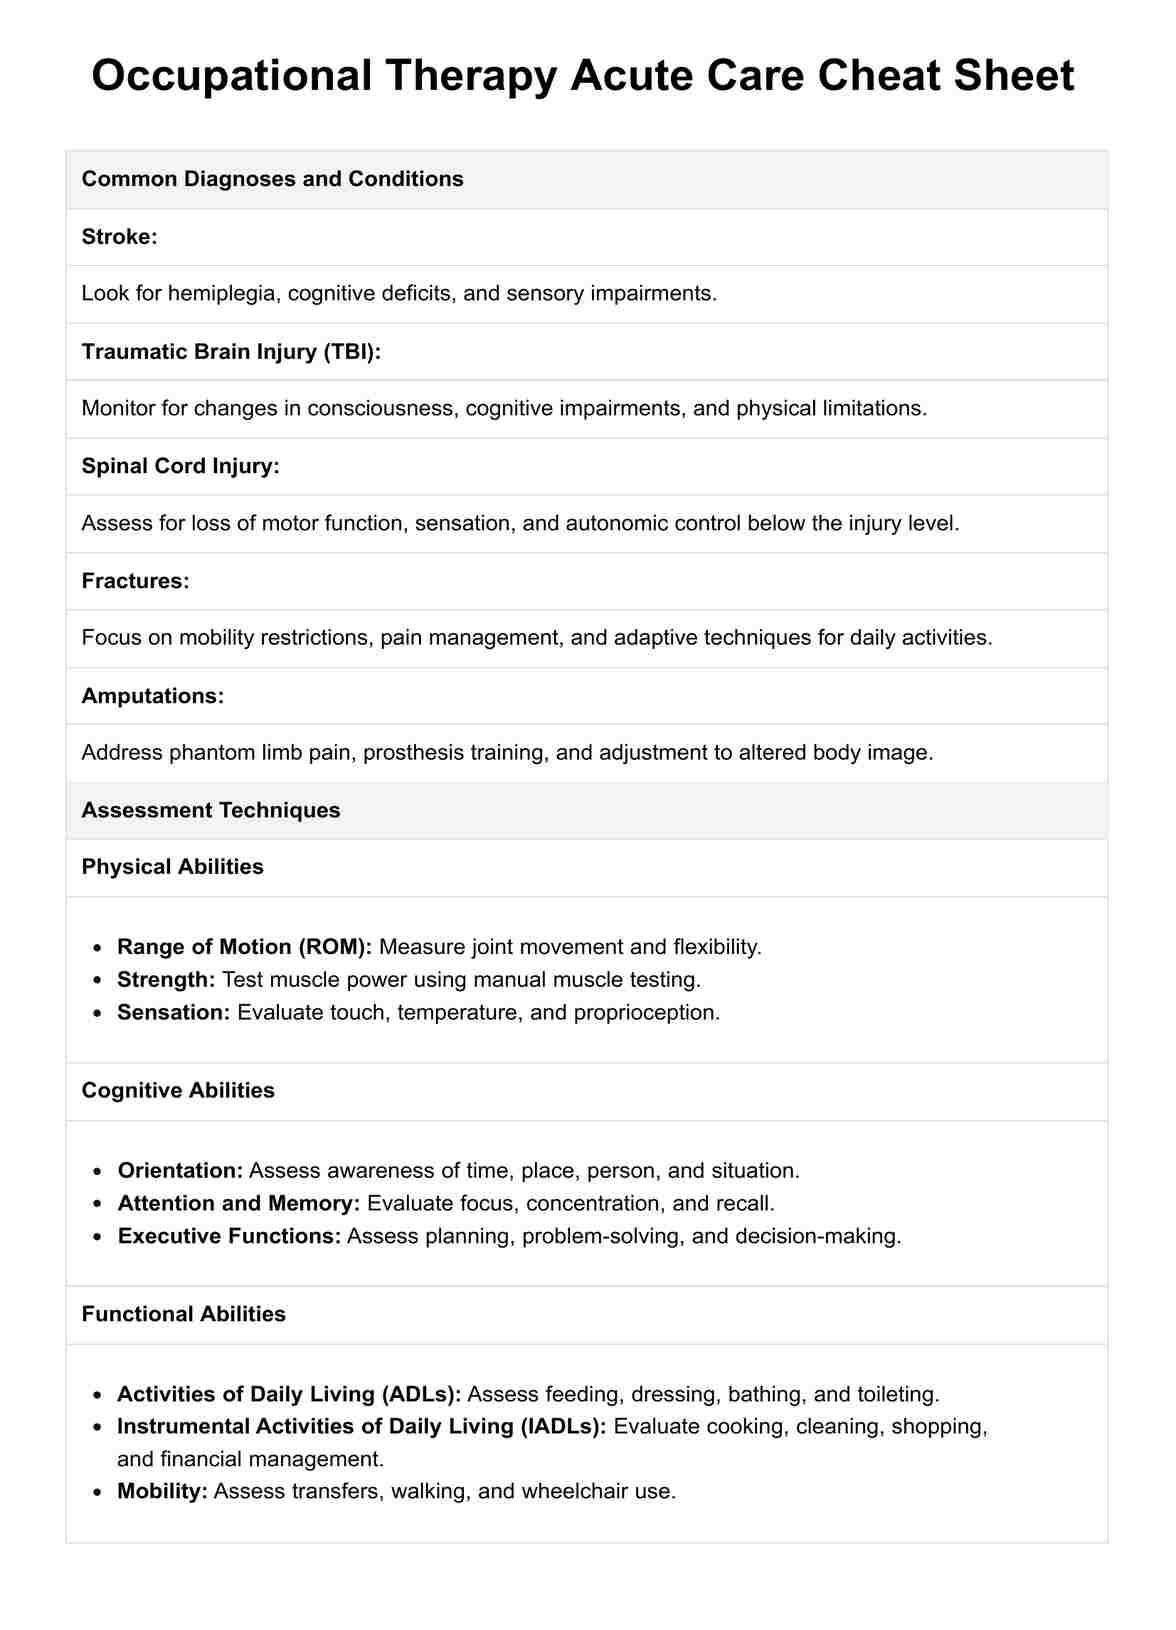
Occupational Therapy Acute Care Cheat Sheet
Here is the breakdown you actually need to have at your fingertips during a 7 a.m. start. Total joint replacements follow predictable weight bearing restrictions but the timelines vary by surgeon preference. A standard total knee arthroplasty protocol allows weight bearing as tolerated immediately in most cases, but some surgeons order partial weight bearing for a week depending on bone quality and intraoperative findings. I once saw a PT team refuse to mobilize a TK patient because the documentation said WBAT but the surgeon's order actually specified touch down weight bearing. The cheat sheet should flag that surgeons sometimes write conflicting orders and you must verify directly rather than assume. Sternotomy patients require strict sternal precautions. No pushing, pulling, or lifting more than five to ten pounds. The cheating sheet needs to specify whether that prohibition includes ADLs like lifting a bedpan, because bedpan transfers absolutely violate sternal precautions and you have to teach a bridge or slide technique instead of rolling through the bed.
Neurological Conditions
Stroke patients in the acute phase are a minefield of blood pressure fluctuations. Transferring a patient with a systolic over 200 can be dangerous. The cheat sheet should include MAP thresholds. Keeping MAP below 130 mmHg during early mobilization is generally safe for ischemic stroke, but after a hemorrhagic stroke the thresholds shift and some neurosurgeons want tighter control. The nuance matters because one size fits all advice causes problems. Spinal cord injuries in the acute phase come with spinal shock and autonomic dysreflexia risk. A patient with a lesion above T6 can have their bladder distended by a bowel movement program and their blood pressure can spike to 220 over 110 within seconds. The cheat sheet should list autonomic dysreflexia triggers in plain language without burying them in clinical jargon. Common triggers are a blocked urinary catheter, a pressure injury, and impaction. The workaround is always the same: sit the patient up, check the catheter tubing for kinks, and call the nurse immediately.
Get the Full Details
Medical Stability Parameters
The cheat sheet should list objective criteria for when not to treat. Oxygen saturation below 88 percent is a universal red flag. Heart rate above 120 or below 50 is concerning depending on the clinical picture. Systolic blood pressure below 90 usually means hold and call the provider. These are not hard rules for every single patient but they are the baseline decision tree most therapists should run through before ordering a transfer. I had a patient with pneumonia and COPD who dropped to 89 percent on room air during a sit-to-stand trial. The quick decision was to apply 2 liters via nasal cannula and recheck. Saturation came back to 92. We continued the session with breaks every three minutes. This is exactly the kind of edge case the cheat sheet should address rather than leaving it to textbook generalities.
What the Cheat Sheet Must Include
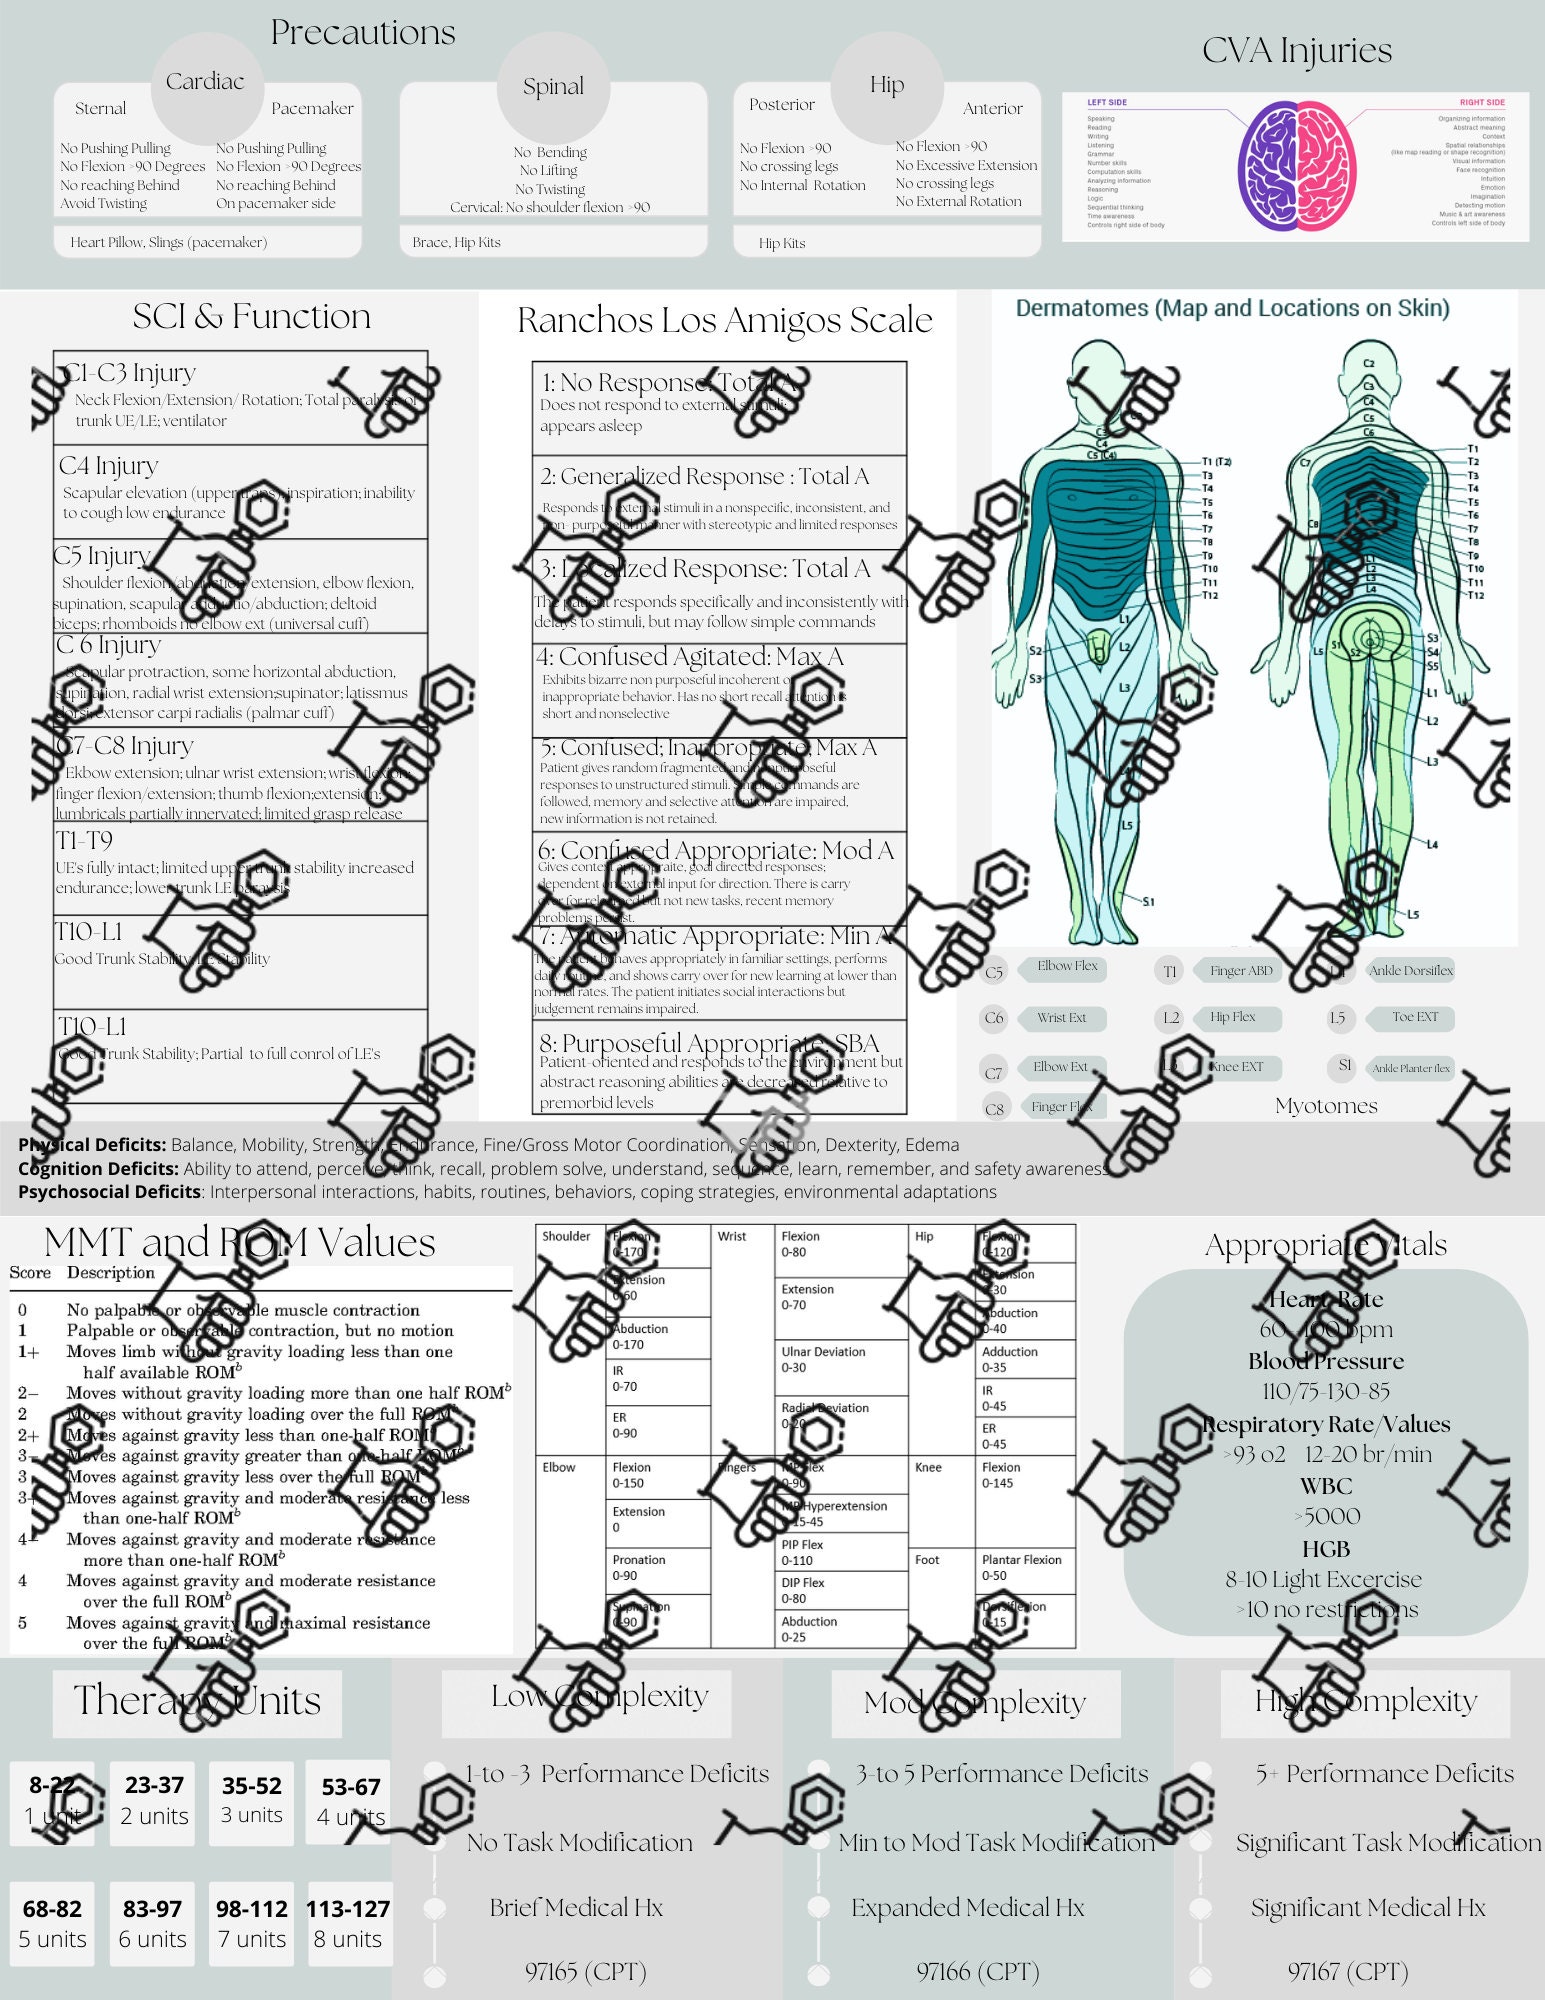
A useful document covers three areas: precautions, interventions, and contraindications. Here is the practical structure I use. Precautions for each condition. What you cannot do. Sternal precautions, hemodynamic instability parameters, fall risk indicators, and DVT precautions after major orthopedic surgery. The DVT part is often overlooked. Compression stockings and sequential compression devices do not prevent DVT on their own, but early mobilization does. The cheat sheet should reinforce that bed rest in acute care is actively harmful beyond the immediate postoperative period for most patients. Interventions by condition. What you can do safely. Bed mobility for post-sternotomy. Seating tolerance assessment for ICU patients. Early ambulation protocols for joint replacement. Energy conservation techniques for pulmonary patients. Cognitive screening for delirium, which is present in roughly 30 to 40 percent of ICU patients and often missed entirely by medical staff who assume it is just confusion.
Contraindications. When to stop. Chest tube drainage above 100 milliliters per hour indicates possible bleeding. Drain output that suddenly turns sanguineous and increases in volume is a warning sign. Unstable spinal fractures without clearance. Active myocardial ischemia. These belong in a prominent section, not buried in footnotes.
Realistic Workflow Integration
The cheat sheet should fit on one page if possible. You are not reading it at the patient's bedside with a magnifying glass. You glance at it during documentation or between patients. Two pages maximum. Anything longer gets ignored. I carry a laminated version folded into my coat pocket. It covers the top ten conditions I see weekly: stroke, hip fracture, pneumonia, heart failure exacerbation, COPD, post-splenectomy, abdominal surgery, sepsis recovery, traumatic brain injury, and ACL repair. That covers roughly 80 percent of my caseload. The remaining 20 percent requires quick lookups for rarer conditions like post-liver transplant or burn care. Documentation time drops significantly when the cheat sheet standardizes your assessment approach. You spend less time deciding what to assess and more time actually assessing. In my experience this saves about 15 minutes per patient chart, which adds up to roughly an hour over a full day of seven patients.
Where the Cheat Sheet Completely Fails
It does not account for institutional variation. One hospital may have an occupational therapy scope that includes gait training for post-operative patients while the same hospital down the street restricts OT to upper extremity function only and defers transfers to physical therapy. The cheat sheet is useless if you do not know your facility's policy. I learned this the hard way when I started at a new hospital and attempted a standing transfer that the nursing staff loudly objected to because OT had never done that there before. It cannot replace clinical judgment. A patient on the cheat sheet might say "safe to mobilize" based on their diagnosis, but if they are confused, pulling at lines, and screaming every time you touch them, the diagnosis is irrelevant. The cheat sheet lists parameters. It does not read the patient. It is also limited by outdated evidence. Medical protocols change frequently. Sternotomy weight limits were ten pounds for years and some institutions recently shifted to five pounds. A cheat sheet printed in 2019 with outdated precautions could cause real harm. Refresh it annually or whenever major guideline changes occur.
Counter-Intuitive Things Beginners Miss
First, earlier is usually better but not always. Mobilizing a patient four hours after a hip fracture repair is standard and improves outcomes. Mobilizing a patient two hours after a laparotomy with an epidural in place and an unexplained drop in hemoglobin is not. The cheat sheet should emphasize checking labs and surgical notes before assuming early mobilization is appropriate, even for conditions where it normally is. Second, fatigue is a legitimate medical limitation in acute care. You will see patients who perform adequately on a single transfer test but cannot repeat it. This is not noncompliance. This is physiologic exhaustion from being critically ill. The cheat sheet should include pacing strategies and recommend breaking sessions into multiple shorter attempts rather than one prolonged effort. A patient who transfers twice with rest breaks between is often better served than one who attempts a single prolonged session and crashes afterward. Third, family presence during therapy sessions in acute care is both beneficial and disruptive. It can motivate a confused patient to cooperate. It can also introduce unnecessary variables if family members are arguing or emotionally distressed. The cheat sheet should have a brief note about assessing family dynamics quickly and adjusting the environment accordingly, such as asking non-essential visitors to step out during the safety-critical portion of the session.

Creating Your Own Version
Start with your current patient population. Review the last three months of charts and identify the conditions you treated most frequently. Build the cheat sheet around those. Do not include conditions you see once a year. That bloats the document and reduces its utility. Use bullet points. Full sentences waste space. Write abbreviations you understand but not abbreviations that require external reference. If you need a legend to read your own cheat sheet, it is too complicated. Get input from a physical therapist and a nurse. PTs see different aspects of the same patients. Nurses see the data that determines medical stability. Both perspectives improve the accuracy of your precautions and parameters.
I have found that carrying a printed version alongside a digital PDF on your phone works best. The paper version is for quick reference during rounds. The phone version is for detailed lookups when you have a moment at the desk. Having both reduces the chance of consulting the document at all because you assume it is somewhere else.
Downloadable Template
A free editable template is available at the end of this guide. It is formatted for a standard letter-size page with columns for condition, precautions, interventions, and contraindications. The template includes the top ten acute care diagnoses as pre-filled examples so you can modify rather than build from scratch. Download it, customize it for your facility, and update it annually. The file is shared as a Google Docs template so you can copy it into your own account and edit without formatting issues. There is no registration required. It is provided as-is because I am not building a product company out of a clinical reference tool.


