What the AOTA framework actually looks like when you're billing insurance
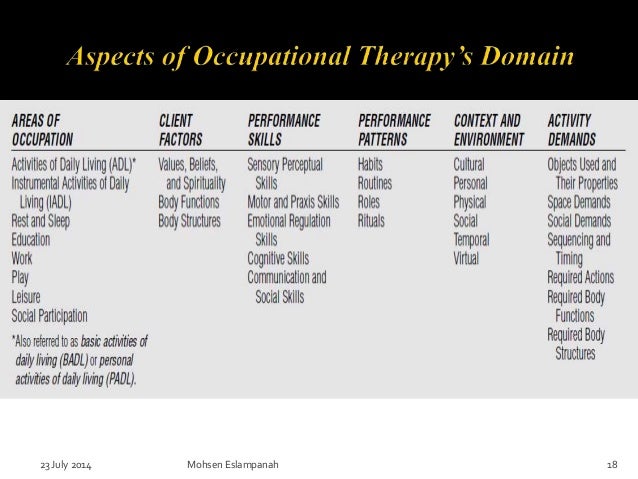
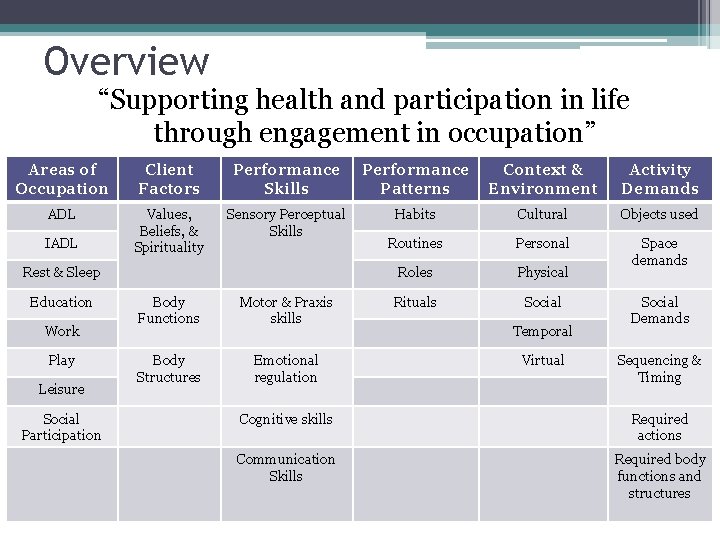
The Occupational Therapy Areas Of Practice are defined by the AOTA's Occupational Therapy Practice Framework: Domain and Process (OTPF-4), which organizes everything into seven domains and covers client factors, body functions, body structures, activities, participation, environments, and contexts. That's the textbook definition. The way it shows up in real clinics is messier. I worked in pediatric neuro rehab for six years before moving to inpatient stroke units, and the gap between the framework and actual billing was where most new OTs struggled. They'd document perfectly against the OTPF-4 but still get rejected because the payer wanted to see a specific area of practice tied to a functional outcome they could understand.
Occupational Therapy Areas Of Practice: The Seven Domains In Reality
Daily Activity Support is probably the most common area you'll encounter. This covers dressing, feeding, grooming, and toileting. The nuance nobody tells you is that insurance reviewers differentiate between "assistance" and "supervision" in ways that aren't obvious from the framework. A patient who can feed themselves but needs verbal cues for safety counts as supervision, not assistance. That distinction changes your CPT code selection and your documentation requirements entirely. Therapeutic Activities and Exercise is the second broad area. This includes range of motion, strengthening, balance training, and gait. Here's the part that trips people up: if you're doing therapeutic exercise alongside an occupational goal, you still need to document the OT side. A lot of younger therapists will write "therapeutic exercise for ROM" without connecting it to a specific occupation. That's a red flag for auditors. The exercise isn't the intervention, it's the means to the intervention. Specialized Skills and Strategies covers things like wheelchair management, adaptive equipment training, and home modification assessments. This area gets under-documented because it's easy to assume a patient just "gets it" after one session. I had a case where a patient with T6 paraplegia was discharged to SNF without any documented training on pressure reliefs or wheelchair propulsion efficiency. They returned two weeks later with a stage 4 sacral ulcer. The documentation gap was avoidable and it wasn't even close.
Community Reintegration and Employment is where OT really distinguishes itself from PT. We assess work hardening, vocational readiness, driving evaluations, and community mobility. The blind spot here is mental health carryover. Patients who've had a stroke often have executive function deficits that make job readiness impossible to assess without formal tools. Using the Model of Human Occupation or Work Environment Importance Performance Assessment can save you from writing vague goals that don't hold up in review. Health Management and Wellness is increasingly relevant with value-based care models. This includes diabetes self-management, stress reduction, sleep hygiene, and chronic disease education. What people miss is that wellness interventions need the same outcome measurement as restorative work. Documenting "patient educated on fatigue management" without a baseline and follow-up measure is documentation theater. It won't survive an audit. Early Development and Learning supports pediatrics specifically — play, school readiness, fine motor development for young children. The challenge in this area is that developmental norms change quickly and payers often want to see progress measured against age-referenced standards, not just arbitrary improvement. Using the Peabody orBruininks isn't always necessary, but having a standardized reference point at intake and discharge protects you.
Get the Full Details

Psychosocial Intervention rounds out the list. This covers group therapy, individual counseling techniques, social skills training, and cognitive-perceptual work in mental health settings. The counter-intuitive thing here is that psychosocial OT is often reimbursed at lower rates despite requiring as much clinical reasoning as physical rehabilitation. The workaround I found was bundling specific CPT codes for group psychotherapy with occupational therapy evaluations when the patient presented with both cognitive and behavioral barriers. It required careful timing but it was legitimate and well-supported by payer policies.
Where the framework falls apart and what to do about it
The OTPF-4 organizes practice beautifully on paper. It does not account for the fact that most patients present with problems spanning three or four areas simultaneously. A geriatric patient with hip fracture might need daily activity support, therapeutic exercise, community reintegration, and health management — all in one admission. The framework doesn't tell you how to prioritize or sequence those interventions when you have 21 days to show meaningful progress. I developed a quick matrix system during my SNF years where I mapped each patient's primary area of practice against their secondary needs on a single page. This wasn't required by any policy but it helped me allocate treatment time realistically. Instead of spending 40 minutes on transfers and ignoring the fact that the patient would never return to their hobby garden, I'd shift 15 of those minutes to a simulated gardening task that also loaded the upper extremities. Same movement pattern, different occupational meaning. The patient was more engaged and the outcomes looked better on paper. Another practical issue is how payer definitions of "occupational" sometimes diverge from the AOTA framework. Medicare, for instance, has historically been strict about requiring direct personal care or functional training. Some regional carriers have expanded coverage to include cognitive rehabilitation and pain management more generously, but you won't find that in the national policy documents. I learned to check each carrier's local coverage determination before committing to a treatment plan, especially for areas like specialized skills and strategies where the line between OT and physical agent modalities gets blurry fast.
Documentation in the area of environmental and contextual factors is another place where people cut corners. The OTPF-4 places heavy emphasis on environment and activity demands, but most insurance forms don't have a structured field for it. I started including a one-line environmental modifier in my subjective notes — something like "returns to job requiring sustained kneeling and overhead reach" — and tying it directly to the goals. It took ten extra seconds per note and it dramatically reduced my denial rate on vocational cases. If you're just getting started with Occupational Therapy Areas Of Practice, pick one domain you're least comfortable with and build your case load around it for a few months. You'll learn faster by being forced to document in areas outside your comfort zone than by staying in the pediatric or geriatric bubble where most new therapists land. The framework is broad by design, and using it broadly is what separates competent OTs from ones who just run protocols.