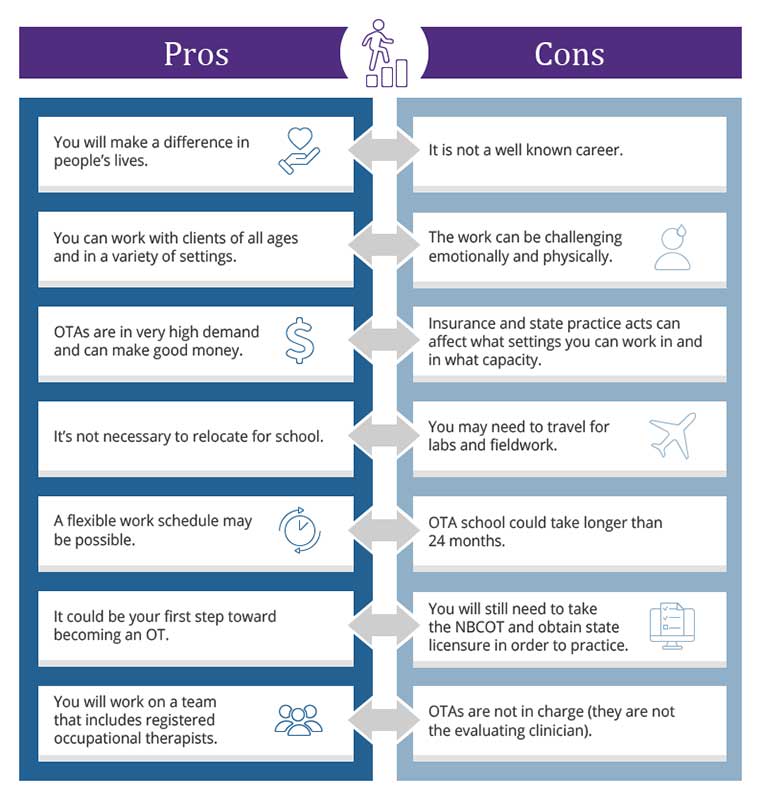
The actual day-to-day of being an OTA
I have been doing this for twelve years across three different settings. The reality is less glamorous than the career-fair pamphlets suggest and significantly more frustrating than people expect when they look into Occupational Therapy Assistant Pros And Cons before committing to it. The pay is stable. In my market, full-time OTAs at the 40-hour level sit between 62,000 and 78,000 depending on whether you work in a school system, outpatient clinic, or home health. Benefits stack up if you stay somewhere long enough. The caseloads in hospitals are heavy but the schedules are predictable. You clock in, you document, you go home. The work itself clicks for the right person. I spent four years in pediatric outpatient and there was a strange satisfaction in watching a kid with hand dystonia finally grasp a fork without dropping it after six weeks of graded activity. That kind of visible progress happens constantly if you pay attention to it. You are not treating disease. You are helping people redo basic functions that used to be automatic. The outcomes are measurable and most patients improve.
There is also a shortage. Not the dramatic shortage headlines suggest but real enough that many practices cannot fill shifts. If you are willing to float or pick up PRN hours, finding work is not difficult. Rural areas often offer sign-on bonuses and relocation assistance because nobody wants to move there. The tradeoff is usually lower pay and fewer senior colleagues nearby.
What the job actually drains from you
Documentation eats everything. A standard 40-minute treatment session takes roughly 25 to 40 minutes of charting afterward. That includes progress notes, billable time stamps, goal updates, and any incident reports. If your clinic uses an EHR that requires you to click through six different dropdown menus for every intervention, you are looking at a full hour per patient on bad days. I have left late because the system lagged and I still had two notes to finish. It happens weekly. The physical toll is real. I tore my rotator cuff in year six from repetitive overhead reaching while assisting a 240-pound stroke patient through transfer training. Your body takes a beating. Knees, lower back, wrists. Some days your shoulders feel like they are packed with gravel by 2pm. You buy good support shoes and stretch during breaks or you pay for it later. Scope creep is another one people do not talk about enough. Patients and families will ask you to do things outside your role because you are the one spending the most time with them. I had a spouse hand me a prescription bottle one afternoon and ask if I could call the pharmacy to request a refill ahead of schedule. I was not their prescriber. I had to explain that gently and direct them to the supervising OT or the physician's office instead. These conversations happen regularly.
Get the Full Details

A specific problem I ran into and how I handled it
Last fall I was working in a subacute rehab unit with a patient who had a C5 cervical spinal cord injury and an indwelling Foley catheter. He was progressing well with upper extremity functional training until he started developing autonomic dysreflexia triggers from a knot forming in the tubing. The protocol said to sit him upright, check the catheter line for kinks, and monitor blood pressure every five minutes. I did all of that within three minutes and his BP came down from 188 over 112 to 142 over 86. The supervising OT was not on the floor at that moment. By the time she arrived, the episode had resolved. I documented the entire timeline, the interventions, the response, and the notification. The facility's risk management team reviewed the note later and confirmed it was appropriate for OTA scope. Still, it was a stressful four hours. The workaround is simple but critical: know your facility's protocol for emergency escalation before you need it, keep a blood pressure cuff at your station, and never pretend you can handle something outside your training because the supervisor is busy. Call it in. It protects the patient and it protects you. The best OTAs are not the ones with the strongest clinical technique. They are the ones who manage their supervisors well. The supervising OT signs off on your evaluations, approves your plans of care, and is ultimately liable. If you send them vague notes or bring problems without proposed solutions, they start micromanaging you. I learned to send a three-bullet summary before each shift with the plan for the day and any red flags. My evaluatons got faster, my schedule became more predictable, and my supervisors stopped hovering. It sounds minor. It changes everything. Another thing: billing compliance matters more than most OTAs realize. In outpatient settings, modifiers, units of service, and medical necessity documentation are audited heavily. I once had a claim denied because I documented therapeutic activities for a hamstring stretch but coded it under a neuromuscular re-education modifier. The payer rejected it on review. Fixing it required the supervising OT to rewrite the note and resubmit. Took two weeks. Always double-check that your documentation language matches your billing codes before you close the encounter. It saves headaches.
Occupational Therapy Assistant Pros And Cons laid out plainly
The pros are straightforward. Meaningful patient interaction, predictable hours in most settings, solid job availability, and a clear career ladder if you want one. You can move into case management, instructor roles, or specialty areas like lymphedema certification or hand therapy after gaining enough hours. The work is tangible. You see people get better at feeding themselves, dressing, walking to the bathroom without falling. That does not fade. The cons are also straightforward. The pay ceiling is low compared to other healthcare roles requiring similar education. Physical strain accumulates. Documentation burden is heavy and rarely discussed during orientation. Scope boundaries get blurry in understaffed facilities. You will deal with difficult family members, insurance companies that deny claims for arbitrary reasons, and supervisors who do not respect your input. If you need high earning potential quickly, this is not the path. If you can tolerate repetitive documentation and physical work in exchange for steady employment and visible patient outcomes, it is a reasonable career. Just go in with your eyes open.




