
Setting Up Joint Protection After RA Flares
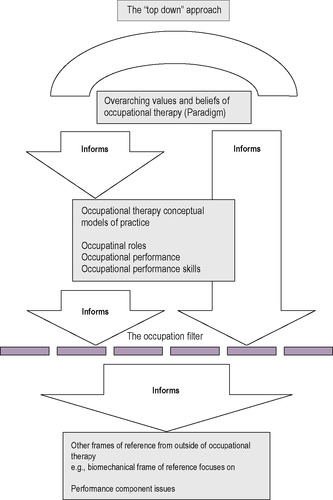
The biomechanical frame of reference in occupational therapy deals with how we approach clients who have physical limitations, whether from arthritis, injury, surgery, or neurological conditions affecting movement. I spent years working in orthopedic and rheumatology settings where this was basically our default framework. It is not flashy, but it works when you understand what it actually means rather than just following protocols. This framework is rooted in anatomy, physiology, kinesiology, and biomechanics. The premise is straightforward: if a client has impairments in body function or structure, we intervene using techniques that address those impairments directly. We work on range of motion, strength, endurance, and functional movement patterns. The goal is restoring or maintaining physical capacity so the person can perform their daily activities. What most new grads miss is that this is not just about stretching a tight joint or strengthening a weak muscle. You have to understand the mechanical principles underlying why something is limited in the first place. A contracture is not simply a tight muscle. It could be capsular restriction, muscle imbalance, scarring, or a combination of all three. The intervention changes completely depending on which factor is actually driving the problem.
I had a client with a total knee replacement who came in with what looked like a straightforward flexion contracture. Standard protocol would suggest aggressive stretching. But when I assessed the tissue quality around the patella and noted significant adhesions tracking through the extensor mechanism, I realized the limitation was not purely muscular. I modified the approach to include soft tissue mobilization and neuromuscular re-education before pursuing end-range stretching. That client gained 15 more degrees of flexion in four weeks than the previous similar cases I had worked with where we just pushed harder on the stretching side.
Assessment Protocols That Actually Matter
Range of motion measurement is the bread and butter here, but goniometry alone will not give you enough information. You need to understand end-feel, tissue resistance, and the quality of movement throughout the arc. A client with rheumatoid arthritis presents differently than someone with osteoarthritis or a post-surgical population. The tissue tolerance, pain response, and inflammatory status all factor into your treatment decisions. Strength assessment goes beyond manual muscle testing. Dynamic strength, eccentric control, and functional strength under load are what actually translate to ADL performance. I typically use dynamometry when available because it gives you repeatable numbers. If you do not have access to equipment, functional strength measures like sit-to-stand repetitions or grip strength with a handheld dynamometer can work reasonably well. Edema assessment is critical for anyone working with this framework. Swelling changes joint mechanics, reduces force production capacity, and increases pain. The standard circumferential measurement technique with a tape measure is reliable if you mark your landmarks correctly. I use a permanent marker to note measurement sites on the client so subsequent sessions are comparable. Volume displacement method with water is the gold standard but rarely practical in clinic settings.
Get the Full Details
Treatment Approaches Within This Framework
Therapeutic exercise is the primary intervention. The key principle here is specificity. You have to target the actual impairment, not just guess what might help. If someone has reduced scapular stability contributing to shoulder impingement symptoms, doing rotator cuff strengthening alone will not resolve the issue. You address the scapular stabilizers first, then reassess shoulder mechanics. Joint protection techniques are essential for clients with inflammatory conditions. This involves teaching energy conservation, proper body mechanics, and modification of activities that place excessive stress on vulnerable joints. For rheumatoid arthritis clients, I typically introduce joint protection principles early, often during the acute phase when pain and swelling are highest. The education component is not optional. Clients need to understand why certain movements are being restricted and how the modifications will serve them long-term. Splinting is another tool in the biomechanical toolbox. Static splints, dynamic splints, and functional splints each serve different purposes. I generally prefer starting with static positioning splints for joint protection and motion limiting, then progressing to dynamic options if active range of motion remains limited. The decision to splint should be based on specific clinical findings, not just because a protocol says so.
One thing I learned the hard way: splinting for contracture management in rheumatoid arthritis clients requires careful monitoring. I had a client who developed skin breakdown under a static resting splint because we were focused on achieving and maintaining a functional position without regularly checking skin integrity. The compromise was reducing wear time to two-hour increments initially and incorporating frequent skin checks. The contracture improvement was slower but we avoided iatrogenic complications.
Common Pitfalls and Limitations
The biomechanical frame of reference can become too narrow if applied in isolation. Focusing exclusively on impairments without considering the client's activity limitations and participation restrictions misses important context. A client may have excellent range of motion and strength but still cannot perform their desired activities due to environmental barriers, pain beliefs, or other factors outside the biomechanical domain. Overemphasis on impairment-level outcomes can lead to treatment plans that look good on paper but do not translate to meaningful functional gains. I have seen clients progress nicely through ROM and strength milestones only to struggle significantly when returning to work or home tasks. The gap between impaired function and actual performance is real and must be addressed explicitly in treatment planning. Pain is another complicating factor. The biomechanical framework assumes that improving physical capacity will reduce disability, but this is not always linear. Chronic pain conditions, central sensitization, and psychosocial factors can maintain disability even when impairments improve. In these cases, integrating cognitive behavioral approaches or pain neuroscience education alongside biomechanical interventions produces better outcomes than either approach alone.

The evidence base for some common biomechanical interventions is weaker than we would like. Therapeutic exercise has decent support, but the specific dosing parameters, progression criteria, and optimal intervention sequences are still being refined. Splinting evidence is mixed depending on the condition and splint design. Joint protection education shows promise but long-term adherence data is limited.
Practical Application Notes
When designing a treatment plan using this framework, start with your assessment findings and work backward to specific interventions. Do not start with interventions and hope the assessment will justify them. Every exercise, every splint, every education topic should trace directly to a documented impairment or clinical finding. Frequency and intensity matter more than you might expect. I typically prescribe bilateral upper extremity exercises for arthritic clients three times per week at moderate intensity, monitoring inflammatory response closely. Pushing too hard on initial visits can trigger flares that set treatment back by weeks. The conservative approach usually wins out over time because it maintains momentum without major setbacks. Documentation should reflect the biomechanical reasoning clearly. Impairment identified, intervention selected, response to intervention, and plan adjustment. This creates a logical treatment chain that others can follow and that supports medical necessity reviews. Vague documentation like "worked on strength and ROM" does not meet reasonable standards.
If you are new to this framework, spend time on the assessment side. Your treatment decisions are only as good as your clinical reasoning about what is actually wrong. The biomechanical frame gives you a solid foundation, but applying it effectively requires understanding the underlying mechanics of each client's specific situation.


