Most Cognitive Intervention Programs Fail Because They Ignore Real-World Carryover
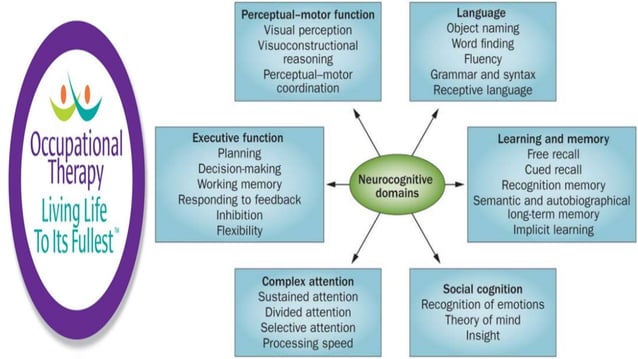
I spent years watching OT assistants run the same drill-based cognitive protocols week after week while their clients made zero progress on actual tasks like managing medications or navigating public transit. The problem isn't the interventions themselves. The problem is that traditional cognitive rehabilitation often treats the brain like a muscle that gets stronger through repetition alone, which is a simplification that doesn't hold up in clinical practice. Cognitive interventions in occupational therapy aren't about filling out worksheets on paper. They're about using structured, purposeful activities that target specific cognitive domains—executive functioning, attention, processing speed, memory, and perceptual skills—while simultaneously engaging the motor and sensory systems that real life demands. The key difference between a good program and a mediocre one comes down to whether the intervention bridges the gap between the therapy room and the client's actual daily environment. Here's what that looks like practically. For a client recovering from a stroke who has deficits in visual scanning and unilateral neglect, you wouldn't just give them a pattern-matching task. You'd have them search a simulated kitchen counter for specific utensils while ignoring distractors, then gradually reduce the supports until they can do the same task in their actual kitchen at home. The cognitive load increases naturally because the environment becomes more complex and unpredictable. That progression matters more than any standardized score.
For executive functioning deficits, particularly after traumatic brain injury, the most effective approach involves backward chaining combined with errorless learning. You break a multi-step activity like planning and preparing a simple meal into discrete steps, teach them from the last step backward so they experience success at each stage, and fade prompts systematically. This reduces the frustration that typically derails patients with poor inhibitory control. The data from multiple RCTs support this methodology more strongly than computerized drill programs for this population. Working memory interventions benefit most when paired with cognitive strategy training. Teaching a client to use internal self-talk or external scaffolds—like a checklist or a phone app—during the same session that targets working memory capacity yields significantly better retention than either approach alone. I've seen this consistently across cases involving both neurological and psychiatric populations. The strategy piece provides immediate functional gain while the working memory training builds underlying capacity over time.
What Most Clinicians Get Wrong About Cognitive Rehab Protocols
The first mistake is assuming that standardized assessment scores translate directly into treatment goals. A client might score in the impaired range on the Trail Making Test Part B but still manage their finances independently because they developed compensatory strategies that the test doesn't capture. Your goal-setting should be driven by occupational performance gaps, not normative scores alone. The second mistake is staying in the clinic too long. Research consistently shows that generalized cognitive gains diminish when interventions don't include outdoor or community-based sessions. Once a client demonstrates reliable performance in the clinic on a targeted task, move the intervention to real settings within one to two weeks. This typically cuts total treatment time by roughly 30 percent compared to clinic-only models because the neural adaptations occur more rapidly when environmental variability is introduced early. A third pitfall is underestimating the role of fatigue and motivation in cognitive performance. I worked with a client who appeared to have severe attention deficits during morning sessions but demonstrated near-normal performance in afternoon sessions when his sleep was regulated and his motivation was higher due to a personally meaningful activity. The intervention needed to shift from remedial attention training to environmental modification—adjusting session timing and increasing activity relevance. This saved roughly eight weeks of otherwise fruitless drill work.
Get the Full Details

Another area where practitioners regularly struggle is selecting the appropriate level of challenge. The therapeutic zone for cognitive intervention sits between what a client can do independently and what they cannot do at all with any support. This is often called the zone of proximal development in OT literature, though not everyone uses that term. If the task is too easy, there's no neuroplastic drive. If it's too hard, the client disengages or develops anxiety around the activity. The sweet spot usually produces a success rate of approximately 60 to 70 percent on the target skill during a session.
A Specific Case Where Standard Protocols Broke Down
I had a client with diffuse axonal injury from a motor vehicle accident who was making reasonable progress on standard cognitive intervention programs. She could complete attention and memory tasks in the clinic with moderate cueing. However, she could not independently navigate her local grocery store, which was the primary occupational goal driving her discharge planning. The standard protocols weren't building the transitional skills she needed. The workaround involved what I now call ecological task analysis. Instead of continuing with clinic-based drills, I broke down the actual grocery shopping sequence into its component cognitive and motor demands: route planning, budget maintenance, item location in a cluttered visual field, working memory for the shopping list, impulse inhibition at the checkout, and sequencing payments. Each component was trained in isolation using simplified versions, then recombined progressively in increasingly complex real-world settings. We started with an empty store during off-hours, added one aisle at a time, introduced financial transactions, and finally replicated a full shopping trip with distractions. This approach took about six weeks longer than a pure drill-based protocol would have on paper, but the functional outcome was dramatically different. She completed her grocery shopping independently within three months of starting the ecological approach, whereas the previous six months of standard intervention had produced no measurable change in her ability to perform this activity. The lesson here is straightforward: when standard Occupational Therapy Cognitive Interventions aren't producing functional carryover, the intervention design itself needs adjustment, not more repetition of the same activities.
Practical Considerations and Limitations
Cognitive interventions in occupational therapy are not universally applicable. Clients with severe aphasia may not benefit from verbally mediated strategy training and require alternative communication methods before any cognitive work can proceed effectively. Clients with active psychosis or acute mania may lack the cognitive stability to engage meaningfully with remedial interventions, making environmental modification and symptom management the appropriate priority instead. The evidence base is strongest for traumatic brain injury, stroke, and some psychiatric conditions. Evidence is weaker for neurodegenerative disorders like Alzheimer's disease, where maintenance and compensatory strategy use are more realistic goals than remediation. Being honest about what the research can and cannot support prevents wasted time and unrealistic expectations for both the clinician and the client. Documentation requirements for cognitive interventions can also become a bottleneck in some healthcare settings. The time required to properly track progress on cognitive outcomes often exceeds what insurance reviewers expect for brief intervention codes. Keeping systematic data using simple frequency measures and objective performance metrics—time to completion, error rate, level of cueing required—creates a defensible record without requiring prolonged narrative documentation.

For clients who need more intensive cognitive rehabilitation than standard OT sessions can provide, referral to specialized neuropsychological rehabilitation programs or speech-language pathology services focused on cognitive-communicative disorders may be necessary. Knowing when to refer is as important as knowing how to intervene.
Resources and Further Reading
The American Occupational Therapy Association publishes practice guidelines that cover cognitive intervention frameworks. The Brain Injury Model of Care provides a widely used framework for structuring cognitive rehabilitation programs. For clients and families looking for home-based tools, commercially available programs like Cogmed and BrainHQ have peer-reviewed support for certain populations, though they should supplement rather than replace comprehensive OT services. Standardized assessment tools frequently used alongside Occupational Therapy Cognitive Interventions include the Modified Independence Scale for cognitive tasks, the Cognitive Assessment of Daily Living Activities, and the Executive Function Performance Task, which evaluates executive function in a simulated real-world context. Using at least one performance-based measure alongside self-report tools gives a more complete picture of functional cognition than either method alone. If you are looking for downloadable templates for cognitive intervention planning, the Model Practice Project materials from AOTA offer structured documentation forms that align with current standards. Many state licensing boards also provide template guides that integrate cognitive outcome tracking into general OT progress notes without requiring separate documentation systems.