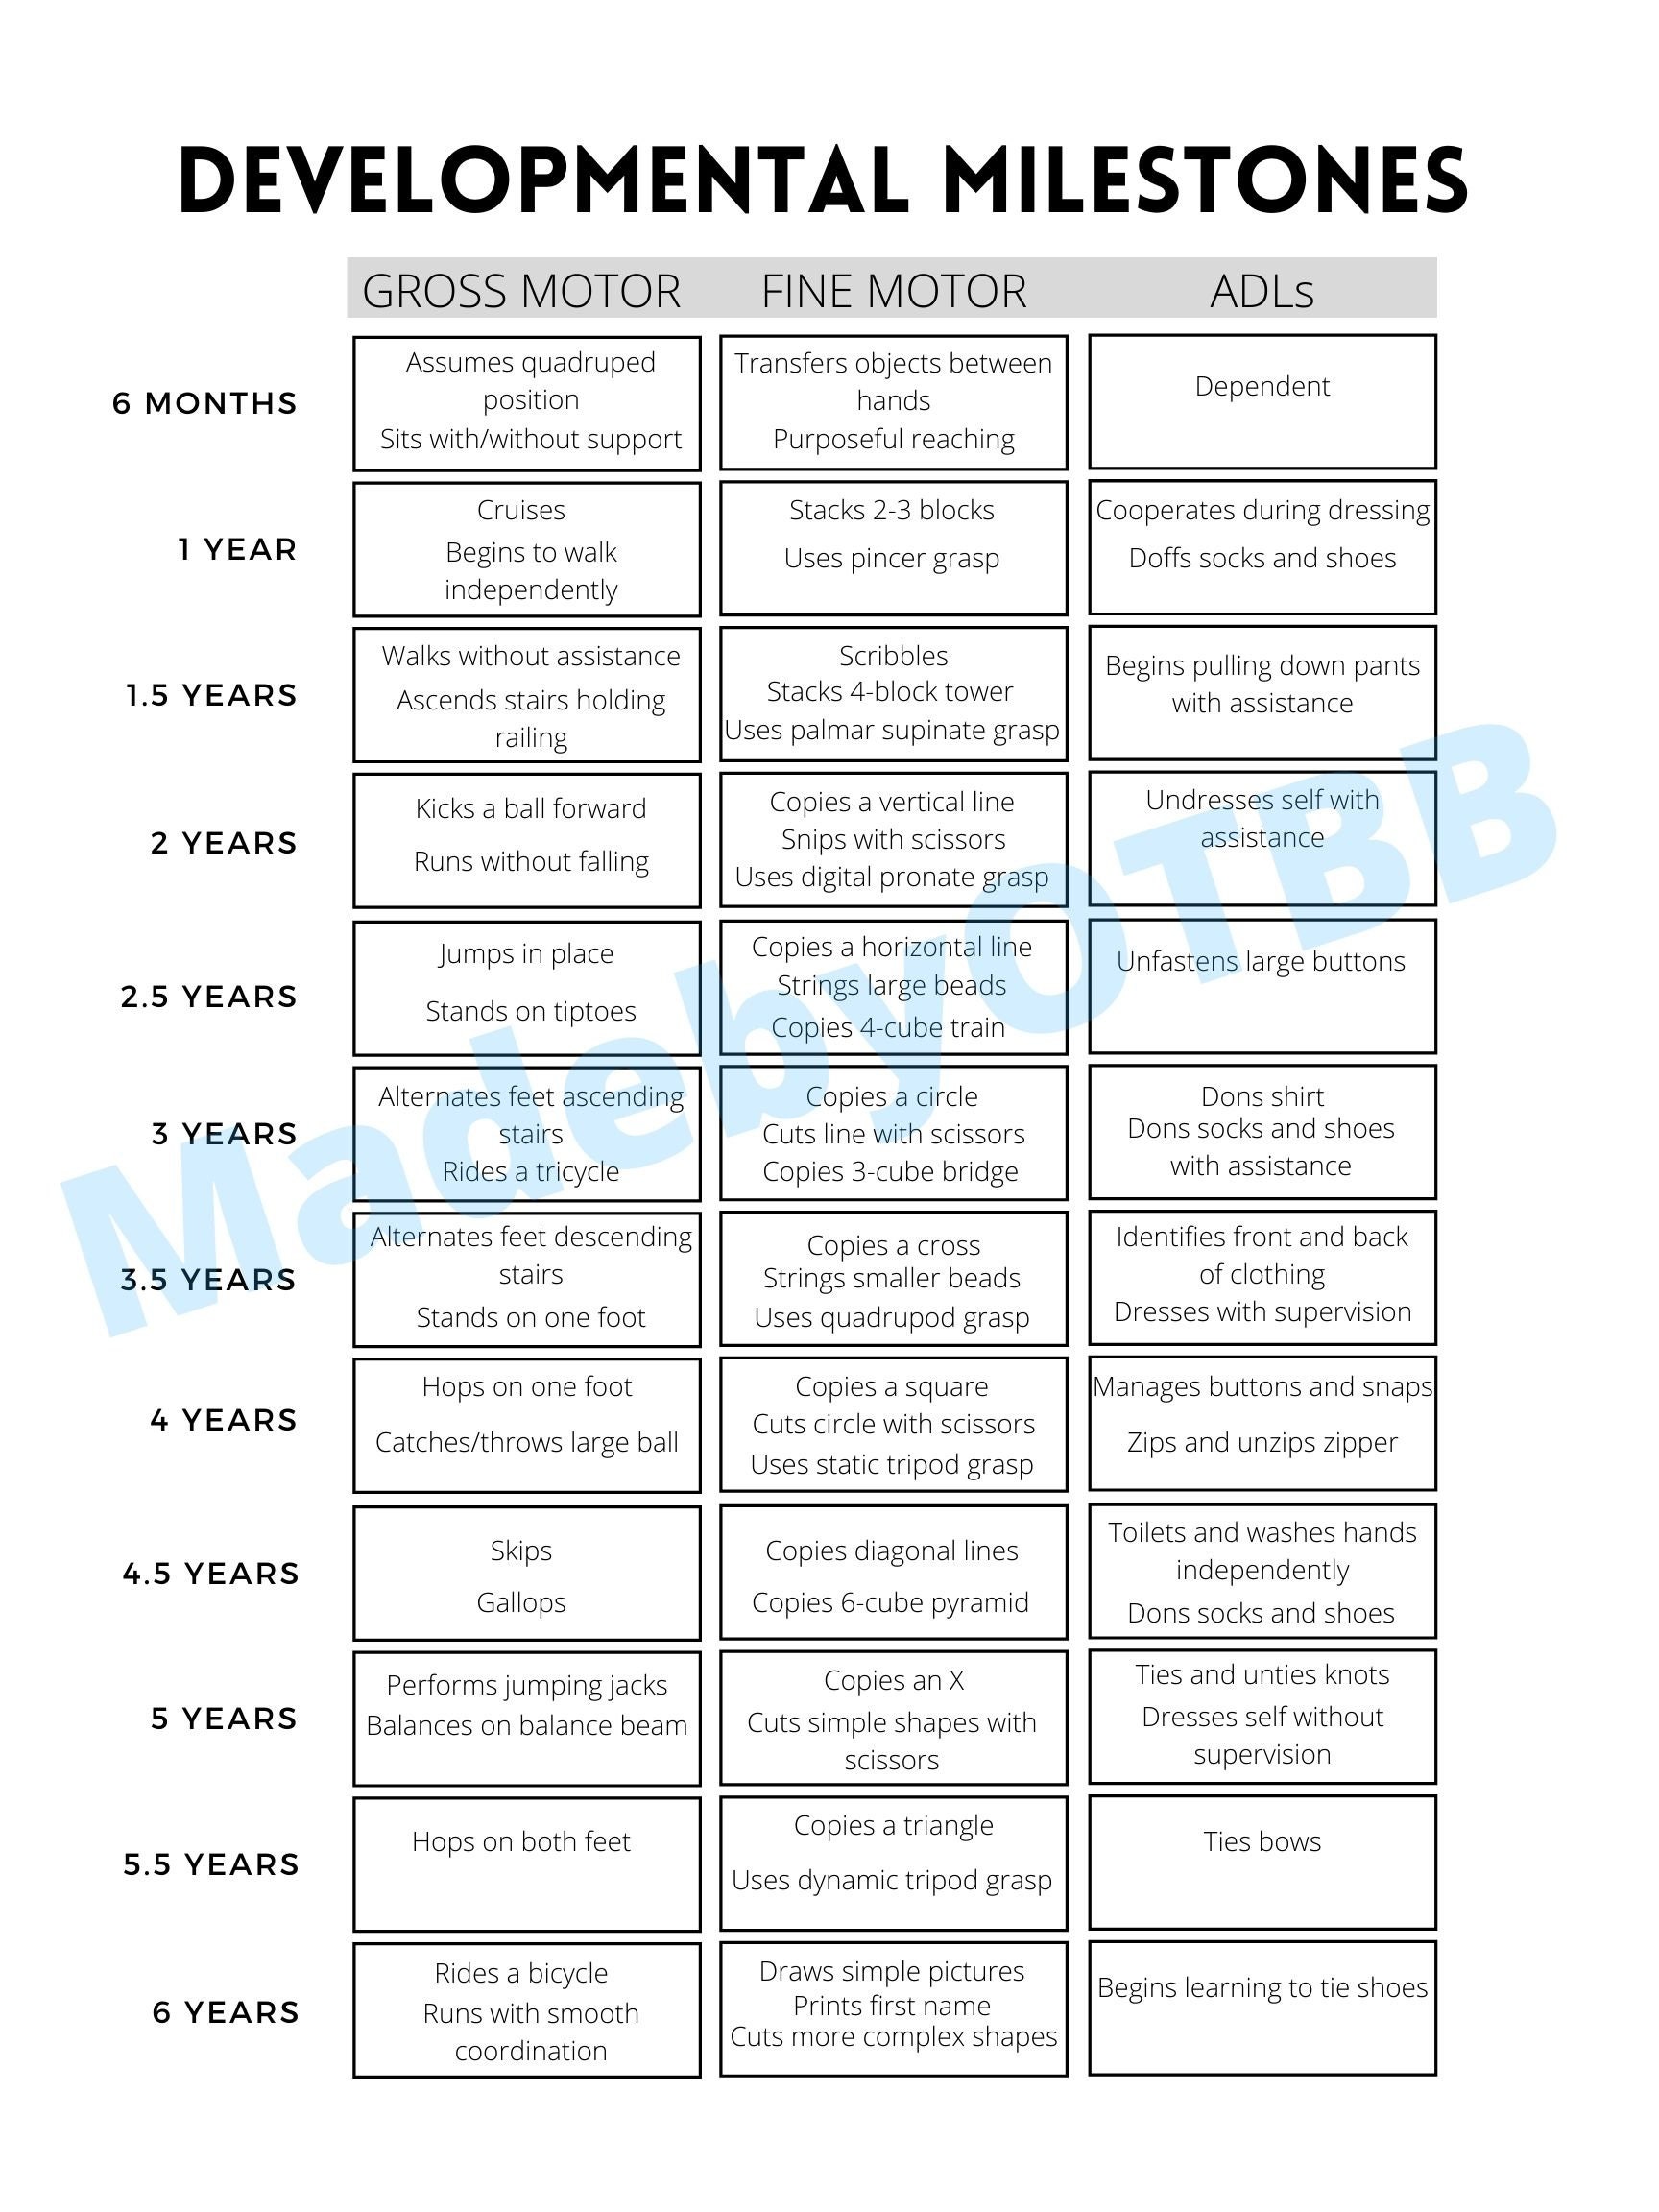
What Occupational Therapy Developmental Milestones Actually Mean in Practice
Most people think OT milestones are just a checklist of skills kids should hit at certain ages. That's not wrong, but it's incomplete. The way I actually use them is different. I look at what a child can do independently across three domains—fine motor, self-care, and play/academic readiness—and then I figure out where the gaps are and why they exist. The developmental milestones in occupational therapy aren't about perfect scores on a test. They're about whether a kid can feed themselves, dress themselves, hold a pencil well enough to form letters, and engage with toys or schoolwork at a level that matches their age group. When those things don't align, that's where we start digging.
Why Occupational Therapy Developmental Milestones Matter More Than You Think
Here's something most parents and even some new therapists miss. A child can score average on standardized motor tests and still struggle profoundly with daily tasks. I had a kid come to me last year who passed the BOT-2 with a score right in the middle of the range. Perfectly average. And he couldn't button a shirt. Not because his fingers were weak, but because his brain couldn't sequence the steps. Fine motor strength had nothing to do with it. That's the gap between a test score and real function, and it's everywhere. The ASQ-3, which is the standard screening tool most people know, takes about 20 minutes and costs nothing. It catches obvious delays well. But it misses kids who are bright but struggling socially, and it has documented cultural bias that skews results for non-white, non-English-speaking families. I've seen it happen. A kid gets flagged as "on track" because his family checked boxes that don't reflect what's actually happening at home, then comes to us six months later unable to hold crayons or manage classroom demands. The screening missed him. The checklist didn't lie, but it wasn't enough either. That's why I never rely on one tool. I layer in the PDMS-2 for gross and fine motor assessment, the Sensory Profile 2 when there's any hint of sensory issues, and the VMI for visual-motor integration. Then I watch what the kid actually does over three sessions before I write anything down. Behavior in context beats a single score every time.
Where Kids Typically Struggle and How to Spot It Early
Fine motor comes up the most. Not because it's the hardest thing to assess, but because it's the first thing parents notice. Holding a spoon past 18 months, struggling with utensils at 3, inability to grip a pencil by 4—those are red flags I take seriously. Not because a kid can't draw perfectly at age 3, but because the transition from palmar grasp to digital grasp should be happening between 18 and 24 months, and if it hasn't started by 30 months, something's going on. Self-care milestones are where most families realize there's a problem. Dressing, feeding, toileting. These seem basic, but they're massive. A kid who can't manage their own clothes at 5 is likely carrying fine motor, sequencing, and proprioceptive processing issues all at once. I had a 5-year-old who cried every morning at getting dressed because his brain couldn't plan the sequence. Not resistance. Actual neurological difficulty. We worked on it for four months. He was buttoning his own shirt by October. Play and academic readiness is the third domain, and it's the one people talk about least but affects the most kids. Sorting blocks, building towers, turning pages in a book, cutting with scissors—these look like simple play skills. They're not. They're the foundation for handwriting, reading readiness, and classroom participation. A kid who can't turn pages one at a time probably has finger isolation issues that will become handwriting problems by first grade. You can catch this at 3 if you're looking for it.
Get the Full Details

The Real Markers I Watch For
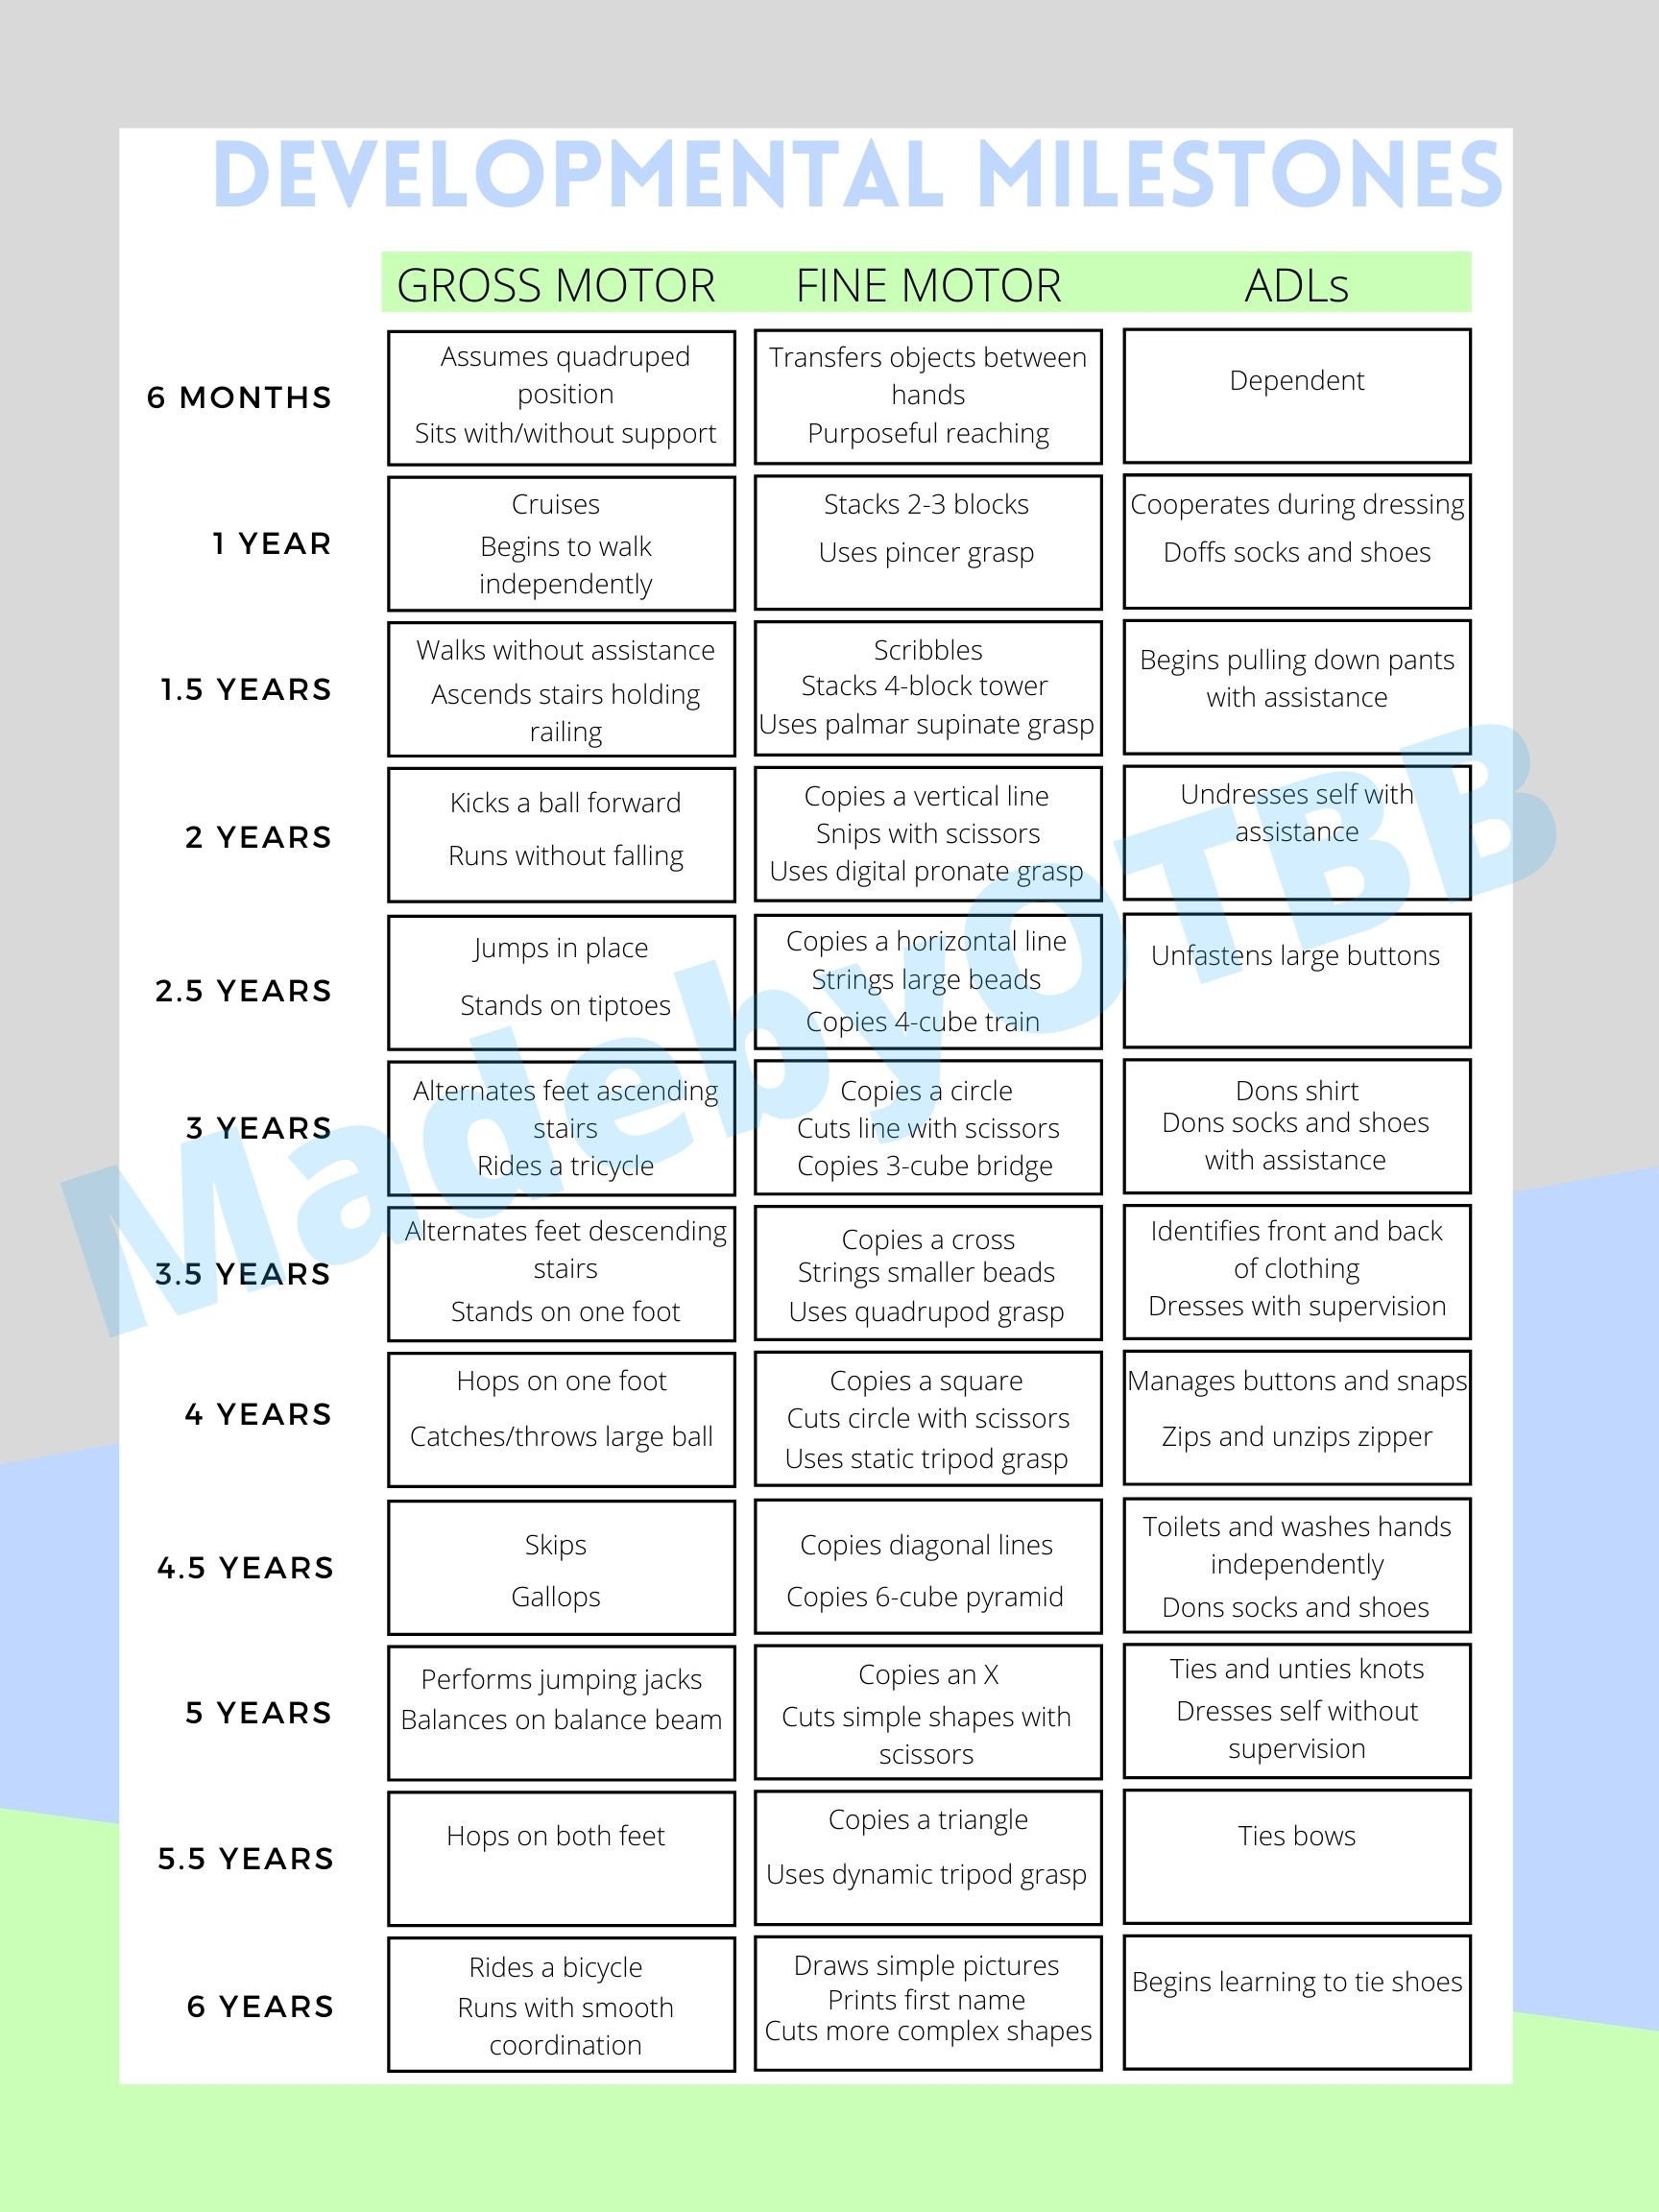
By 12 months, a child should be able to transfer objects from hand to hand voluntarily. Before that, they might carry two things simultaneously, but that's coincidence, not coordination. By 15 months, they should be able to place objects into a container without dropping them. By 18 months, they should be using a mature palmar grasp on crayons. By 24 months, they should be stacking eight blocks. These aren't strict deadlines, but they're the rough timeline that shows whether motor development is tracking normally. Hand preference is another marker. Kids shouldn't show strong handedness before 18 to 24 months. If a child seems ambidextrous past age 3 without any clear preference, that's worth noting. It's not always a problem, but it can signal underlying motor planning difficulties that affect writing development later. I also watch the transition from reflexive to voluntary movement. Newborns have the palmar grasp reflex—put something in their hand and they hold on. That disappears around 6 months. If it hasn't, that's a neurological red flag. Same with the Babinski reflex, which should resolve by 24 months. I'm not diagnosing here, but these are the kinds of things I notice during screening and flag for further evaluation.
What Standardized Tests Can't Tell You
The PDMS-2 is comprehensive. It covers reflexes, stationary balance, locomotion, manual dexterity, and grasping. It takes about 45 minutes to administer. It's one of the most useful tools we have for motor assessment in young children. But it still doesn't tell you whether a kid can handle the demands of a typical classroom. A child might score in the 50th percentile for fine motor and still freeze when asked to color inside lines. Why? Because coloring inside lines requires visual-motor integration, sustained attention, and emotional regulation—not just finger strength and coordination. The Sensory Profile 2 fills that gap for kids who have sensory processing issues. It doesn't measure motor ability directly, but it tells you whether a child is over-responsive, under-responsive, or seeking sensory input in ways that interfere with function. A kid who can't sit still in class might not have an attention problem. They might be seeking proprioceptive input that their body craves. The assessment changes the intervention completely. Instead of behavior management, you're giving them a weighted vest or a chew tube and seeing if they can focus better. It works. The VMI measures visual-motor integration, which is basically how well a child can copy shapes and letters. It predicts handwriting difficulty better than almost any other single measure. A low VMI score at age 5 is a strong predictor of handwriting problems through third grade. Early identification here saves years of frustration. I start intervention at 5, not 7, because by then the habits are already forming and they're much harder to change.
When Milestones Mean Something Different
Not every delay is the same. A kid who's 6 months behind in fine motor but catching up on their own usually just needs support. A kid who's 6 months behind and plateauing needs a different approach. The difference is progression versus stagnation. I track milestones using month-by-month goals over three months. If there's no change after six weeks of targeted intervention, I reconsider the diagnosis. Maybe it's not a motor planning issue. Maybe it's visual processing, or it's sensory, or it's something else entirely. Another thing people get wrong is assuming all kids develop milestones at the same pace. They don't. Some kids master fine motor skills early and lag in self-care. Others hit self-care milestones fast and struggle with motor planning. Both are normal variations. The problem is when a child lags across multiple domains simultaneously. That's when I start looking for broader neurological or developmental concerns and refer out if needed.
How I Actually Use This Knowledge Day to Day
My process starts with observation. I don't hand a parent a checklist and ask them to fill it out. I watch the child interact with materials for 10 minutes before I say anything. How do they hold the crayon? Can they manipulate small objects? Do they avoid certain textures? Do they finish a task or abandon it? The answers tell me more than any questionnaire. Then I do a formal screening if needed. ASQ-3 for general development, PDMS-2 for motor, Sensory Profile 2 for sensory, VMI for visual-motor. I don't do all four on the first visit. That's unnecessary. I pick based on what I observed. If the kid struggles with utensils, I do the ASQ-3 plus fine motor observation. If they're avoiding sensory input, I add the Sensory Profile. Targeted assessment beats comprehensive assessment most of the time. After that, I write goals that are measurable and time-bound. Not "improve fine motor skills." That's meaningless. It's "the child will stack eight blocks within 30 seconds by the end of 8 weeks" or "the child will use a digital grasp on crayons with correct thumb placement during 10-minute coloring activities." Specific. Observable. Trackable.
I revisit goals every two weeks. If a child isn't making progress after four weeks, I adjust. The milestone framework is a guide, not a law. Kids don't read rubrics. They develop at their own pace, and our job is to meet them where they are and move forward from there. The biggest mistake I see is rushing intervention. A kid who's slightly behind at 2 doesn't need a year of therapy. They need targeted support and re-screening in three months. Over-treating normal variation is as harmful as under-treating real delay. You have to know the difference, and that comes from experience, not textbooks.