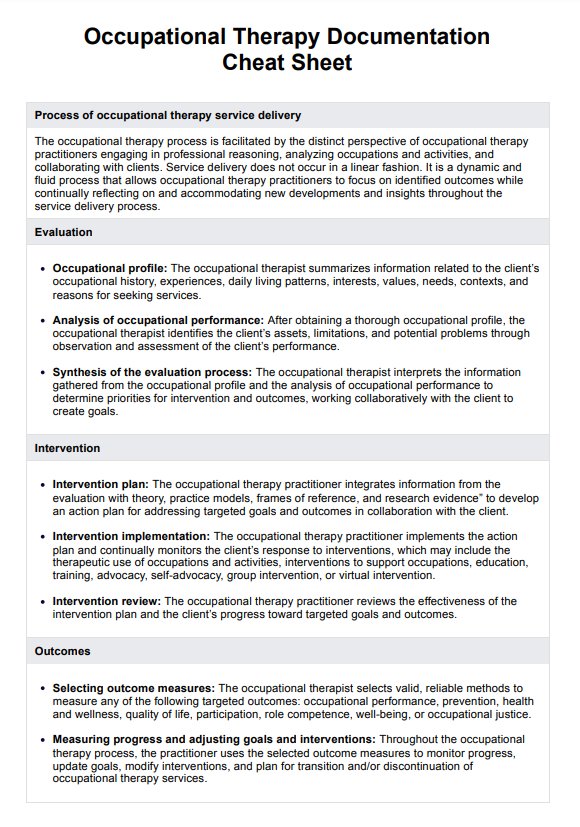
Why We Even Need These Templates
Occupational therapy documentation templates are structured frameworks that help OTs capture patient evaluations, interventions, and outcomes in a consistent way. They're not glamorous, but they save you from starting every note from a blank page. The alternative is either rewriting the same paragraphs over and over or forgetting to include something your auditor will later flag. I've used both approaches. The blank-page method got old fast. You end up spending more time formatting than actually documenting. Templates fix that by giving you a skeleton to fill in.
Occupational Therapy Documentation Templates: What They Actually Are
At their core, these templates are just organized fields. Some are free-form with prompts. Others lock you into specific sections like chief complaint, assessment findings, plan of care, and progress notes. The best ones adapt to different settings—acute care, pediatrics, outpatient, skilled nursing—because the documentation requirements shift depending on where you're practicing. Don't confuse templates with forms. A form is something you fill out for billing or compliance. A template is something you build your clinical narrative around. They overlap, but they're not the same thing. Here's what most templates share: a section for baseline function, measurable goals tied to ICD-10 codes, intervention details with frequency and duration, and outcome measures showing change over time. That's it. Nothing fancy.
How to Build One That Actually Works
Start with your payer requirements. Medicare, Medicaid, private insurers—they all want slightly different things. If your template doesn't account for what each payer needs to see, you'll get denials. That happened to me in 2019 when I was at a rehab facility. We had a solid internal template, but it didn't include the specific functional limitation language that a particular commercial insurer required. We lost three claims in one month. I rebuilt the template with payer-specific fields and the denials stopped. The process goes like this: First, gather your current notes. Pull five recent evaluations and five progress notes. Look for patterns. What sections keep appearing? What do you always forget? That tells you what your template needs to include.
Get the Full Details

Second, map it to your electronic health record. If you're using Epic or Meditech, build the template inside the system. Don't create something outside and try to copy-paste it in. That takes twice as long and you'll stop doing it after a week. Third, add conditional logic where you can. If the patient is pediatric, show the developmental domain fields. If they're geriatric with cognitive decline, show the safety and caregiver training sections. Most EHR platforms support branching logic now. Use it. Fourth, test it on three patients before rolling it out. Write full notes with the template. Time yourself. If it takes longer than your old method, something is wrong. Cut the fluff.
Common Mistakes I See People Make
The biggest problem is overcomplication. I once saw a template with forty-seven fields. Forty-seven. Most of them were never filled in. The therapist just scrolled past them and moved on. Now she had two versions—one with everything and one she actually used. That's not a template. That's clutter. Another mistake is making templates too rigid. I had a colleague who built a trauma rehabilitation template that worked great for stroke patients. Then she tried to use it for hand surgery cases. The language didn't fit. The outcome measures were wrong. She spent an hour trying to force it to work instead of just making a second template. There's no rule that says you need one template per patient type. Make as many as you need. Here's a nuance beginners miss: documentation templates should reflect your clinical reasoning, not just your paperwork habits. Every field should answer a question an auditor or another provider might ask. If a field doesn't serve that purpose, remove it.
What Good Templates Look Like in Practice
A solid evaluation template has these sections at minimum: Patient identity and referral source. Name, DOB, date of service, referring provider. Basic stuff, but I still see people skip the referral source and then get asked for it during a chart audit. Chief reason for evaluation. One or two sentences. Not a paragraph. If you can't summarize why this person is here in two sentences, you don't understand the referral yet.

History of present condition. Mechanism of injury, date of onset, previous treatments, comorbidities that affect function. Keep it relevant to occupational performance. Assessment findings. This is where most templates fail. They list tests without context. A good template prompts you to connect the finding to the functional impact. ROM is 45 degrees of elbow flexion, therefore patient cannot lift utensil to mouth without compensatory trunk movement. That connection matters. Cognitive and perceptual screening. Even if you're not formally testing cognition, document that you considered it. I had a case where a patient failed to recognize the purpose of a dressing tray because of visuospatial deficits we hadn't caught. The template should have a checkbox or prompt for cognitive/perceptual screening so you don't skip it.
Goals. SMART goals with measurable criteria and timelines. Not "improve fine motor skills." That's not a goal. That's a hope. Write "Patient will independently button a shirt with buttons larger than one centimeter within four weeks as measured by OT task analysis." Plan of care. Frequency, duration, type of interventions, modalities, and who will provide them. This section drives your billing. Be specific.
A Template for Progress Notes
Progress notes are where templates matter most because you're writing them constantly. A streamlined progress note template should include: Patient response to today's session. What did they do? How well did they do it? Changes from previous session. Did they improve, plateau, or regress? Why?

Barriers encountered. Pain, motivation, fatigue, caregiver absence. Document these because they affect medical necessity arguments. Plan adjustment. Continue, increase, decrease, or modify intervention. Change goals if needed. That's it. Four elements. If your template has more than six fields for a daily progress note, it's too much.
Where to Get or Build Templates
You have a few options. The American Occupational Therapy Association offers some resources, though they lean toward general guidance rather than ready-to-use templates. Many EHR vendors include template libraries that come pre-loaded. Check yours first before building from scratch. If you build your own, start simple. Use a word processor or a shared document. Iterate. Share with colleagues and ask what they'd change. Templates improve through use, not through perfect design on the first try. There are commercial template vendors online. Some are decent. Some are expensive and locked into specific platforms. I recommend trying to build a basic version yourself first. If it saves you fifteen minutes per note, you'll know it's worth investing in a more polished solution.
The Limits of Templates
Templates don't replace clinical judgment. They won't catch every documentation error. They can't write the note for you. And in some cases, they actively hurt your documentation quality if you treat them as a checkbox exercise rather than a thinking tool. I've seen therapists complete a template in under two minutes by auto-filling every field with "continued" or "same as yesterday." That's dangerous. It creates the illusion of thorough documentation without actually documenting anything. Auditors spot this quickly. The real value of a template isn't speed. It's consistency. It ensures that every note contains the essential elements so that when someone reads your chart—whether it's a physician, a billing reviewer, or a lawyer—they can follow your clinical reasoning without guessing.

Build your templates to support that goal. Keep them clean. Update them when your practice changes. And never stop questioning whether each field earns its place.

