How Occupational Therapy Evaluations Actually Work in a Real Clinic
Most people I talk to think an occupational therapy evaluation is just filling out a clipboard form and then deciding if someone qualifies for treatment. That is not how it goes. The evaluation is a structured process that pieces together what a person can do, what they struggle with, and what environmental or physiological barriers are standing in the way. It is equal parts clinical reasoning, observation, and documentation that has to hold up under insurance review.I have watched OTs rush through evaluations because of patient volume and then get sent back by insurance because the notes did not clearly link the client's deficits to functional goals. It happens constantly. The difference between a clean write-up and a denied claim usually comes down to how specifically the evaluator ties standardized scores to real-world tasks.
The OT Evaluation Process Explained
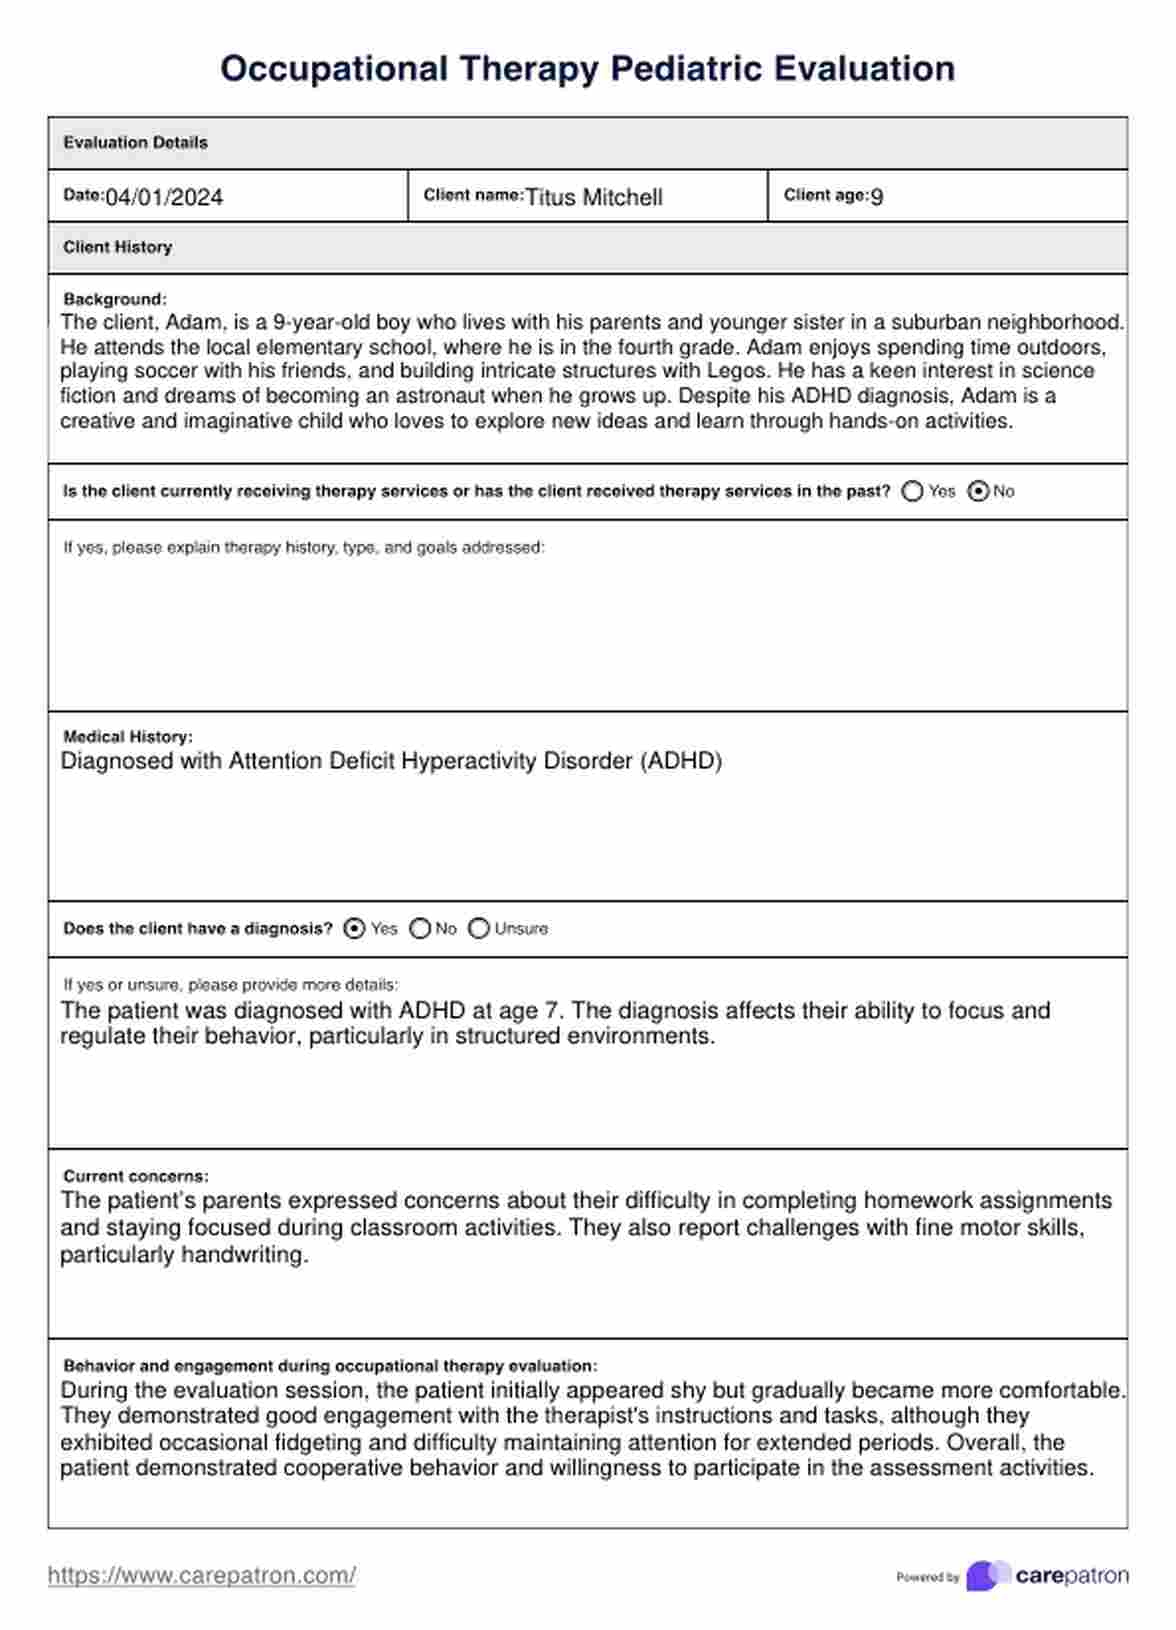
An Occupational Therapy Evaluation Example starts with a review of medical history and referral reason. Then you move into performance-based assessment. You observe the client doing actual tasks, administer standardized tools when relevant, and interview the client or their caregiver about daily routines. All of that feeds into an analysis of occupational performance, followed by a written report and plan of care.The timeline varies. A comprehensive initial evaluation typically takes between 60 and 90 minutes. A follow-up evaluation might take 30 to 45 minutes if you are reassessing specific areas rather than redrawing the whole picture. In pediatric settings, observations often stretch longer because you need to watch play-based interactions that reveal function differently than direct testing does.
Key Components of an Occupational Therapy Evaluation
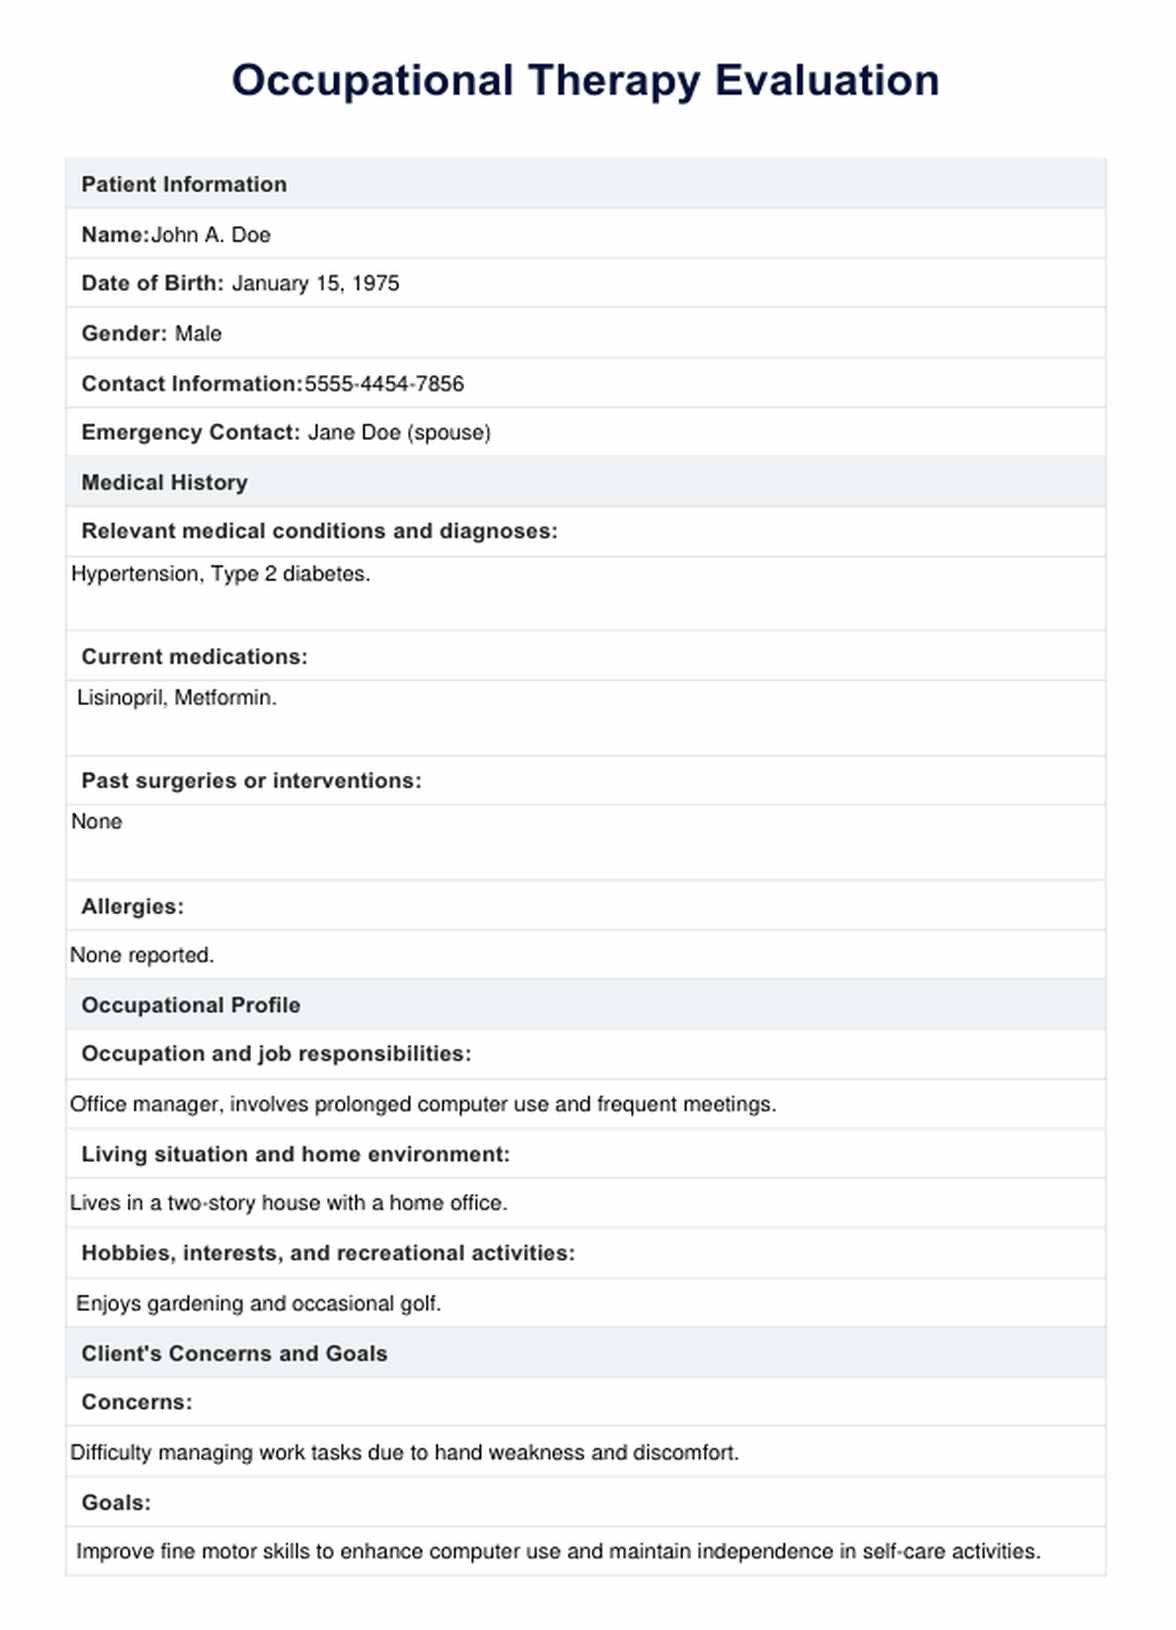
The core components break down into several categories. Medical history and current diagnoses set the foundation. You need to know what medications the client is on, prior surgeries, pain levels, and any cognitive or sensory diagnoses. Next comes the occupational profile, which is essentially a conversation about what the person actually needs and wants to do. This is where you learn whether a stroke survivor wants to feed themselves independently or whether a child needs to participate in classroom activities without meltdown behaviors.Performance-based assessments come next. These might include the Berg Balance Scale, the Fine Motor Section of the Peabody, the Sensory Processing Measure, or the AMPS. The tool you pick depends entirely on the client population and the referral reason. Picking the wrong instrument because it is easier to administer rather than because it fits the clinical question is a mistake I see repeatedly.
Get the Full Details
Standardized Tools Commonly Used
A lot of evaluators default to the same three or four tools regardless of the client. That approach gets old fast and produces shallow reports. For motor dysfunction, I often reach for the Action Research Arm Test for stroke clients because it is sensitive to change in upper extremity function and directly maps to tasks like reaching, grasping, and lifting. For pediatric sensory integration concerns, the Sensory Integration and Praxis Tests give you more depth than generic checklists, but they require proper certification to administer and score correctly.The Short Physical Performance Battery works well for older adults in community settings. It covers gait speed, chair stands, and balance in about five minutes and predicts fall risk with decent accuracy. Do not skip the cognitive screening either. Even in pure motor cases, a quick MoCA or MMSE can change the entire treatment approach.
Documenting Findings and Writing the Report
Documentation is where most evaluations fall apart under scrutiny. I had a case last year where a client with a TBI was evaluated using standard language that described poor short-term memory but did not capture the specific environmental modifications needed for his return-to-work goals. Insurance denied the initial plan because the evaluation did not clearly justify the number of sessions requested. I rewrote the report to include a detailed analysis of his computer use tasks, the specific memory errors he made during simulated work activities, and the compensatory strategies we planned to teach. It took two extra hours but cleared the authorization for 24 sessions without further appeal.Every finding should tie directly to a functional deficit and a proposed intervention. Vague statements like client demonstrates deficits in self-care do not survive payer review. Write what the client cannot do, under what conditions, with what level of assistance, and why it matters to their daily routine. Include baseline scores from standardized tools and describe the qualitative behavior you observed during performance tasks. Numbers without context are useless in these reports.
Common Mistakes That Ruin an Evaluation
One mistake that costs jobs is relying solely on self-report when the client has limited insight. After a stroke or traumatic brain injury, anosognosia is real and common. If the client says they can dress themselves independently and you document that without observing the task, you are setting yourself up for a failed plan of care. Always verify self-report with actual performance data when possible.Another frequent error is over-testing. Some evaluators feel pressure to administer every available tool because they think more data equals a stronger case. It does not. Ten poorly selected tests produce more noise than three targeted ones. Pick instruments that address your specific clinical questions and move on.

What Makes an Evaluation Stand Out
The best evaluations I have read share one trait. They tell a story that is completely defensible. The narrative flows from history to observation to standardized results to a logical plan. You can see exactly how the clinician moved from each piece of data to the next conclusion. A client with multiple sclerosis who cannot button shirts because of fatigue and decreased fine motor control should have that chain of reasoning laid out clearly, with the standardized scores and the observed task performance directly supporting the need for adaptive equipment and energy conservation training.Insurance reviewers do not have time to hunt for your logic. Build the bridge between your findings and your recommendations so it is impossible to miss. I keep a mental checklist of six items that must appear before I consider an evaluation complete: referral reason addressed, relevant history summarized, appropriate standardized tools administered and scored, objective performance data documented, clear functional limitations identified, and a plan of care with measurable goals directly linked to those limitations. If one of those is missing, the evaluation is not done.



