
What Occupational Therapy Exercises Actually Are
Occupational Therapy Exercises are the specific, purposeful movements and activities prescribed by a licensed occupational therapist to help someone regain the physical or cognitive function needed for daily living. They're not generic gym workouts. They're targeted at things like buttoning a shirt, carrying a tray, gripping a utensil, or maintaining balance while walking across a room. The goal is always functional, never theoretical. I've seen countless people confuse these with regular physical therapy exercises, and that mistake matters. Physical therapy tends to focus on range of motion and strength in a general sense. OT exercises are built around the actual tasks a person needs to perform in their own life. If someone can't tie their shoes after a stroke, the exercises are designed to rebuild the specific coordination and grip strength that makes shoe-tying possible, not just "improve hand function" in some vague way.
How to Build an Effective Occupational Therapy Exercises Routine
Here's the part most people get wrong: you don't just pick random exercises from a PDF and expect results. The process starts with a functional assessment. I once worked with a client who had mild carpal tunnel syndrome and was frustrated because her hands felt weak. Her OT had her do standard grip strengthening exercises for three weeks with no improvement. The issue wasn't grip strength. It was positional stability in the wrist during fine motor tasks. We switched the entire routine to wrist stabilization drills combined with task-specific practice — stacking small blocks while keeping the wrist neutral, transferring pennies from palm to fingers without bending the wrist, and practicing zipping a jacket with a built-in wrist brace for proprioceptive feedback. Within two weeks she could button her shirts again. The exercises changed completely once we identified what was actually broken. A proper routine follows a few hard rules: 1. Identify the broken link between impairment and function. This means mapping the deficit directly to a real-world task. Can't hold a coffee cup without spilling? That's a combination of grip, wrist extension, and shoulder stability working together. Isolate which part fails first. I usually have clients try the actual task while I observe, not while they describe what happens. Descriptions are unreliable under pain or fatigue.
2. Start at the impairment level, not the activity level. If a patient can't flex their fingers beyond ten degrees, having them try to zip a jacket every day will frustrate them and reinforce compensatory patterns that cause secondary problems. Fix the range of motion first with passive and assisted movements, then progress to active range, then to weight-bearing, then to the actual task. 3. Use graded repetition, not maximum effort. Most OT exercises should be done in multiple low-intensity sets with rest between them. A set of twenty repetitions done with correct form at thirty percent of maximum effort produces more neural retraining than ten hard reps that leave the joint inflamed. I tell clients to aim for "noticeable but not exhausting." If they can't repeat the exercise the next day without soreness, they did too much the day before. 4. Embed exercises into actual daily tasks as soon as possible. This is where occupational therapy diverges sharply from physical therapy. The exercise isn't the end goal. The exercise is a bridge. As soon as a patient can perform the isolated movement reliably, you pair it with a real activity. Gripping therapy putty is fine. Gripping the putty while simultaneously practicing picking up a remote control is the actual treatment. The dual-task nature forces the brain to integrate the new motor pattern into functional context.
Get the Full Details
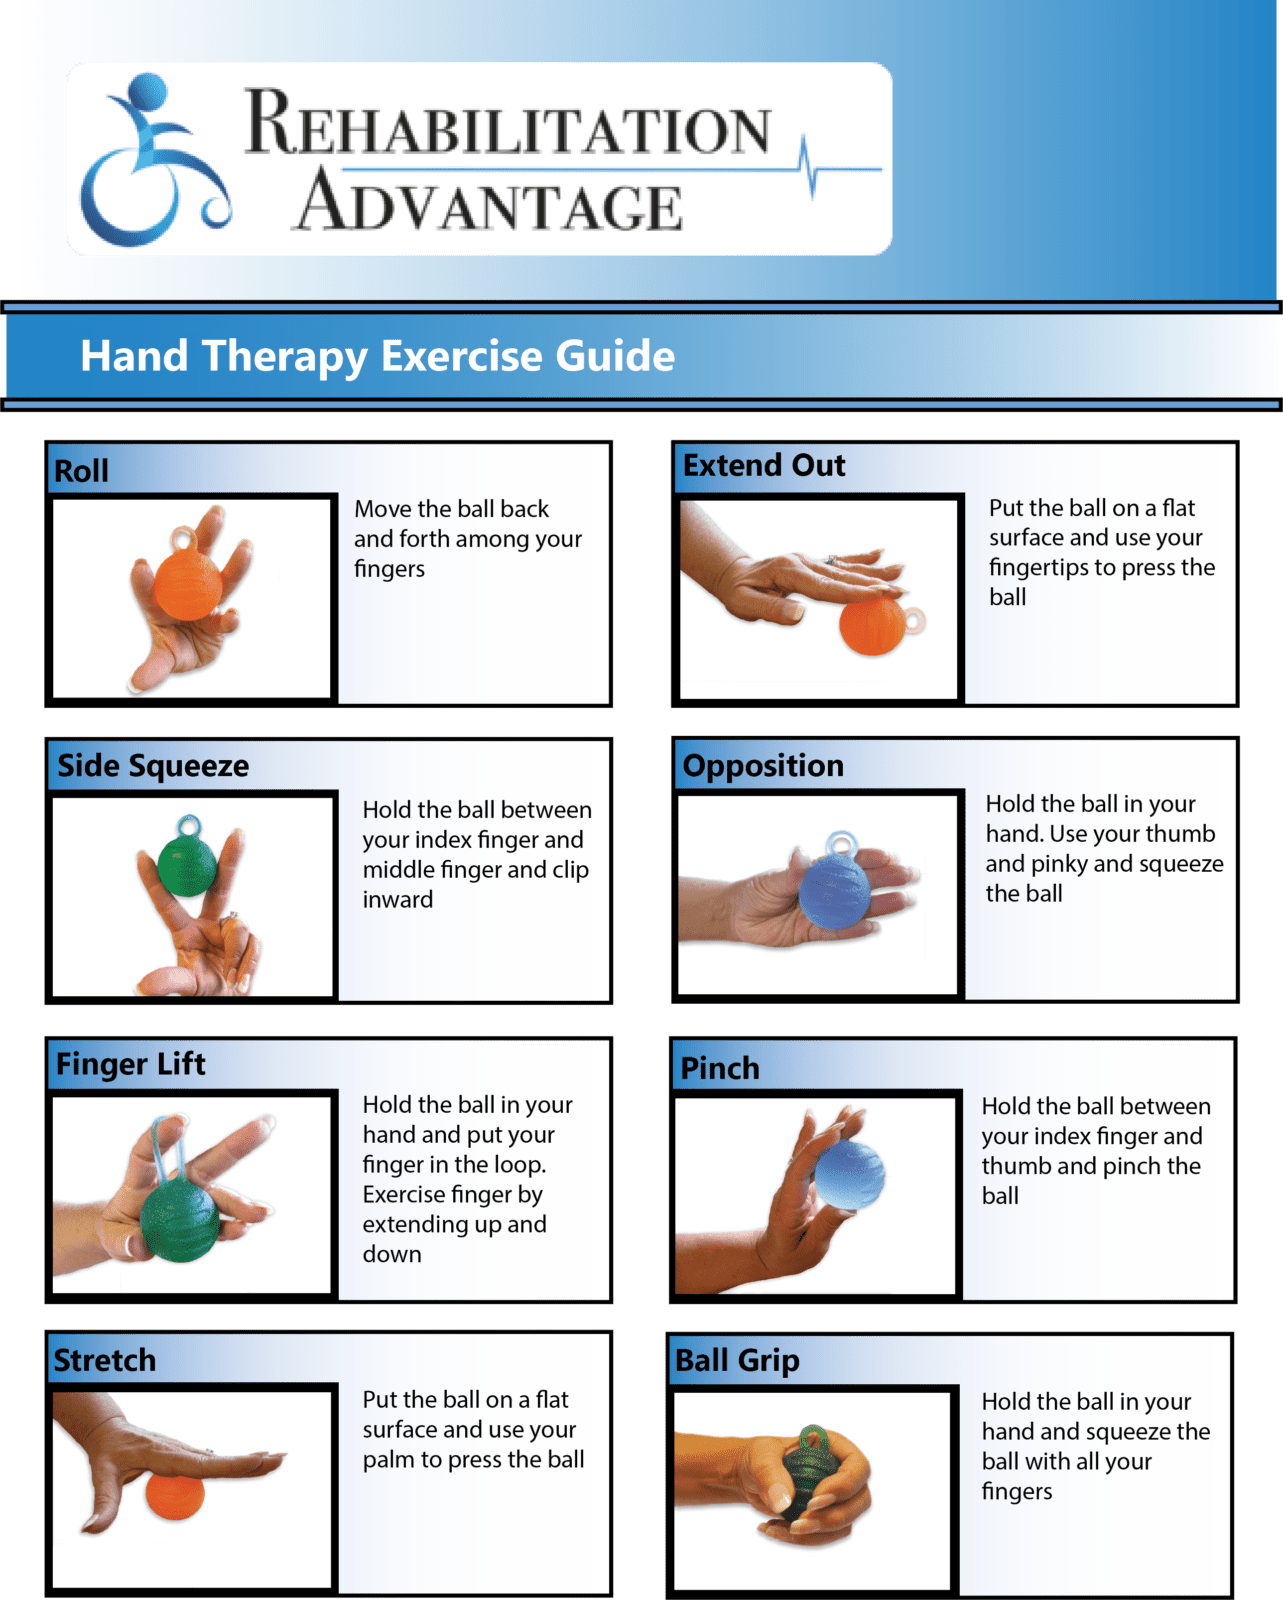
Common Exercise Categories and What They Actually Treat
Fine motor exercises target the small muscles of the hands, fingers, and wrists. These include tasks like picking up small objects with the thumb and index finger, manipulating buttons or zippers, folding coins, and writing practice. The key detail most guides skip: the size of the object matters enormously. A patient who can pick up a marble but not a paperclip has a specific precision grip deficit that's very different from someone who can handle a paperclip but can't manipulate a marble. The treatment for each is different. Gross motor exercises address larger movement patterns — reaching overhead, balancing on one foot, transferring from sitting to standing, walking while carrying an object. Balance exercises specifically are often underutilized in home programs. A simple single-leg stand while brushing teeth builds the kind of automatic postural control that prevents falls, and it costs nothing in equipment or time. Cognitive-exercise hybrids are probably the most important category and the most neglected. These include sequencing tasks like following a multi-step recipe, sorting objects by multiple criteria, timed organization challenges, and memory tasks under motor load. After a TBI or in early-stage dementia, these exercises do more neurological work than pure motor drills. The combination of cognitive demand with physical execution is what drives real plasticity.
Sensory integration exercises are relevant for conditions like autism spectrum disorder, sensory processing disorder, and some neurological injuries. Weighted vest use, textured surface exploration, vestibular input through controlled swinging, and deep pressure techniques all fall here. I've found that weighted blankets and compression sleeves can reduce hand tremor enough for a patient to complete meals independently, but the effect varies significantly between individuals and shouldn't be assumed to work universally.
Equipment You Actually Need and What to Skip
The basic toolkit for a home-based Occupational Therapy Exercises program includes therapy putty or stress balls, a set of therapy putty in varying resistances, a balance pad or folded towel, a tray for carrying practice, a collection of everyday objects of different sizes and textures, and a timer. That's it. You do not need expensive gadgets. I've seen clients spend hundreds on grip dynamometers and fancy sensor-based devices. Most of those tools give you data that doesn't translate to better function. A $15 resistance putty set paired with actual task practice will outperform a $200 device that isolates grip force without context. The data from a dynamometer tells you the number. It doesn't tell you whether that number helps the person open a jar at home. One item that does earn its keep: a mirror. Mirror therapy, where a patient performs movements while watching their reflection in a mirror placed to create the illusion of the affected limb moving normally, has legitimate evidence behind it for stroke recovery and phantom limb pain. It's cheap, it's simple, and it works through visual feedback to reduce pain and improve motor output. The protocol is straightforward — place a mirror vertically between the limbs, hide the affected side, and perform movements while watching the reflection of the healthy side. Fifteen to thirty minutes a day.

The One Problem Nobody Warns You About
Compensatory strategies are the silent enemy of progress. I worked with a patient recovering from a rotator cuff tear who was assigned finger isolation exercises to rebuild intrinsic hand muscle control. Within three sessions, he started using his entire arm and shoulder to compensate for weak finger muscles. He could complete the reps, but he wasn't actually exercising the target muscles. He was reinforcing the wrong pattern. The workaround was visual biofeedback. I had him film his own hand during the exercise and review the footage with him frame by frame. Seeing his shoulder shrug and his elbow extend while he thought his fingers were moving alone was the moment the awareness clicked. Once he could see the compensation, he could inhibit it. Mirror feedback, video recording, or even just placing a towel under the shoulder to prevent elevation during finger exercises are all low-tech fixes for this problem. The principle is the same: make the compensation visible so the brain can correct it. Another frequent issue is symptom flare-ups masquerading as progress. Some days the exercises will feel harder than the day before, and the patient assumes they're regressing. Often this is just inflammation from tissue adaptation. I recommend a simple rule: if symptoms stay elevated for more than twenty-four hours after a session, reduce the volume by half next time. If they spike and resolve within twenty-four hours, that's normal adaptation and the volume can continue to increase gradually.
When These Exercises Won't Help and What to Do Instead
Occupational Therapy Exercises have real limitations. They won't fix structural damage that requires surgical intervention — a complete tendon rupture, a severely narrowed cervical canal causing myelopathy, advanced osteoarthritis with bone-on-bone contact. They also won't produce meaningful gains if the patient has no baseline ability to perform the movement at all and no medical clearance to attempt it. In those cases, the priority is diagnosis and treatment planning, not a home exercise program. Another scenario where OT exercises fail: when the primary barrier is pain, not impairment. A patient with severe osteoarthritis in the hands may have intact motor control but can't execute tasks because of pain. Pushing through with strengthening exercises in that situation just reinforces pain avoidance. The right first step is pain management — splinting, heat therapy, medication adjustment, activity modification — before returning to exercise. The exercises aren't wrong. They're just the wrong tool for the current phase. For patients with progressive neurological conditions like MS or Parkinson's, the ceiling for improvement is lower and the rate of decline may outpace the gains from exercise. In those cases, the goal shifts from restoration to maintenance and adaptation. The exercises become about preserving whatever function exists and finding new ways to accomplish tasks within the current capacity. This is where adaptive equipment and environmental modification matter as much as the exercises themselves. A reacher tool, a jar opener, a weighted utensil — these aren't concessions. They're legitimate therapeutic interventions that extend independence longer than exercise alone would.
The protocol I follow for building a program is straightforward and takes about an hour for a complete beginner plan. I start by listing the five most important daily tasks the patient wants to return to. I break each task down into its component movements. I identify which components are impaired. I select exercises that address those specific components. I stack them into daily sessions of twenty to forty minutes total, split into two or three shorter bouts if fatigue is an issue. I schedule progression checkpoints every two weeks to assess whether the exercise is still appropriate or whether the task difficulty should increase. The whole process is iterative. If an exercise isn't producing noticeable improvement after three weeks at the appropriate difficulty level, it's probably not the right exercise for that patient, and it gets swapped out.



