Doing the OT home health eval properly saves you denials later
The initial Occupational Therapy Home Health Evaluation is not the place to wing it. You're building the entire certification record, and every goal and functional deficit you document becomes the justification for the next period of care. One sloppy visit can cascade into a 30-day recertification fight or a Medicare audit flag. I used to rush through the home environment portion because I thought the patient's clinical presentation was what mattered most. That changed after a denial where the auditor said I documented "patient reports difficulty with stairs" without describing the actual stair configuration, handrail presence, or whether the patient attempted it during the visit. The note read like a referral, not an evaluation. It cost me two weeks of delayed payment.
Prepping for the Occupational Therapy Home Health Evaluation
Before you walk through the door, pull the physician's order and verify the certification of need is on file or being processed. Check whether the agency requires a specific assessment tool — some payers and facilities have preferences. Bring your standard OT eval kit: goniometer, dynamometer, reflex hammer, penlight, a stopwatch, and blank forms. Most platforms now use electronic documentation, but having paper backups matters when the Wi-Fi dies in a basement apartment. The key insight nobody tells new therapists is that the home environment itself is a clinical variable. Lighting, flooring type, clutter, stair design, bathroom configuration, and kitchen layout all affect what you can legitimately claim about functional independence. A patient who scores "modified independent" on the Modified Barthel Index in a clinic may be dependent in their actual home because of a three-step entrance with no ramp and a bathtub without a transfer bench. Documenting that gap is what justifies the plan of care.
Structuring the actual visit
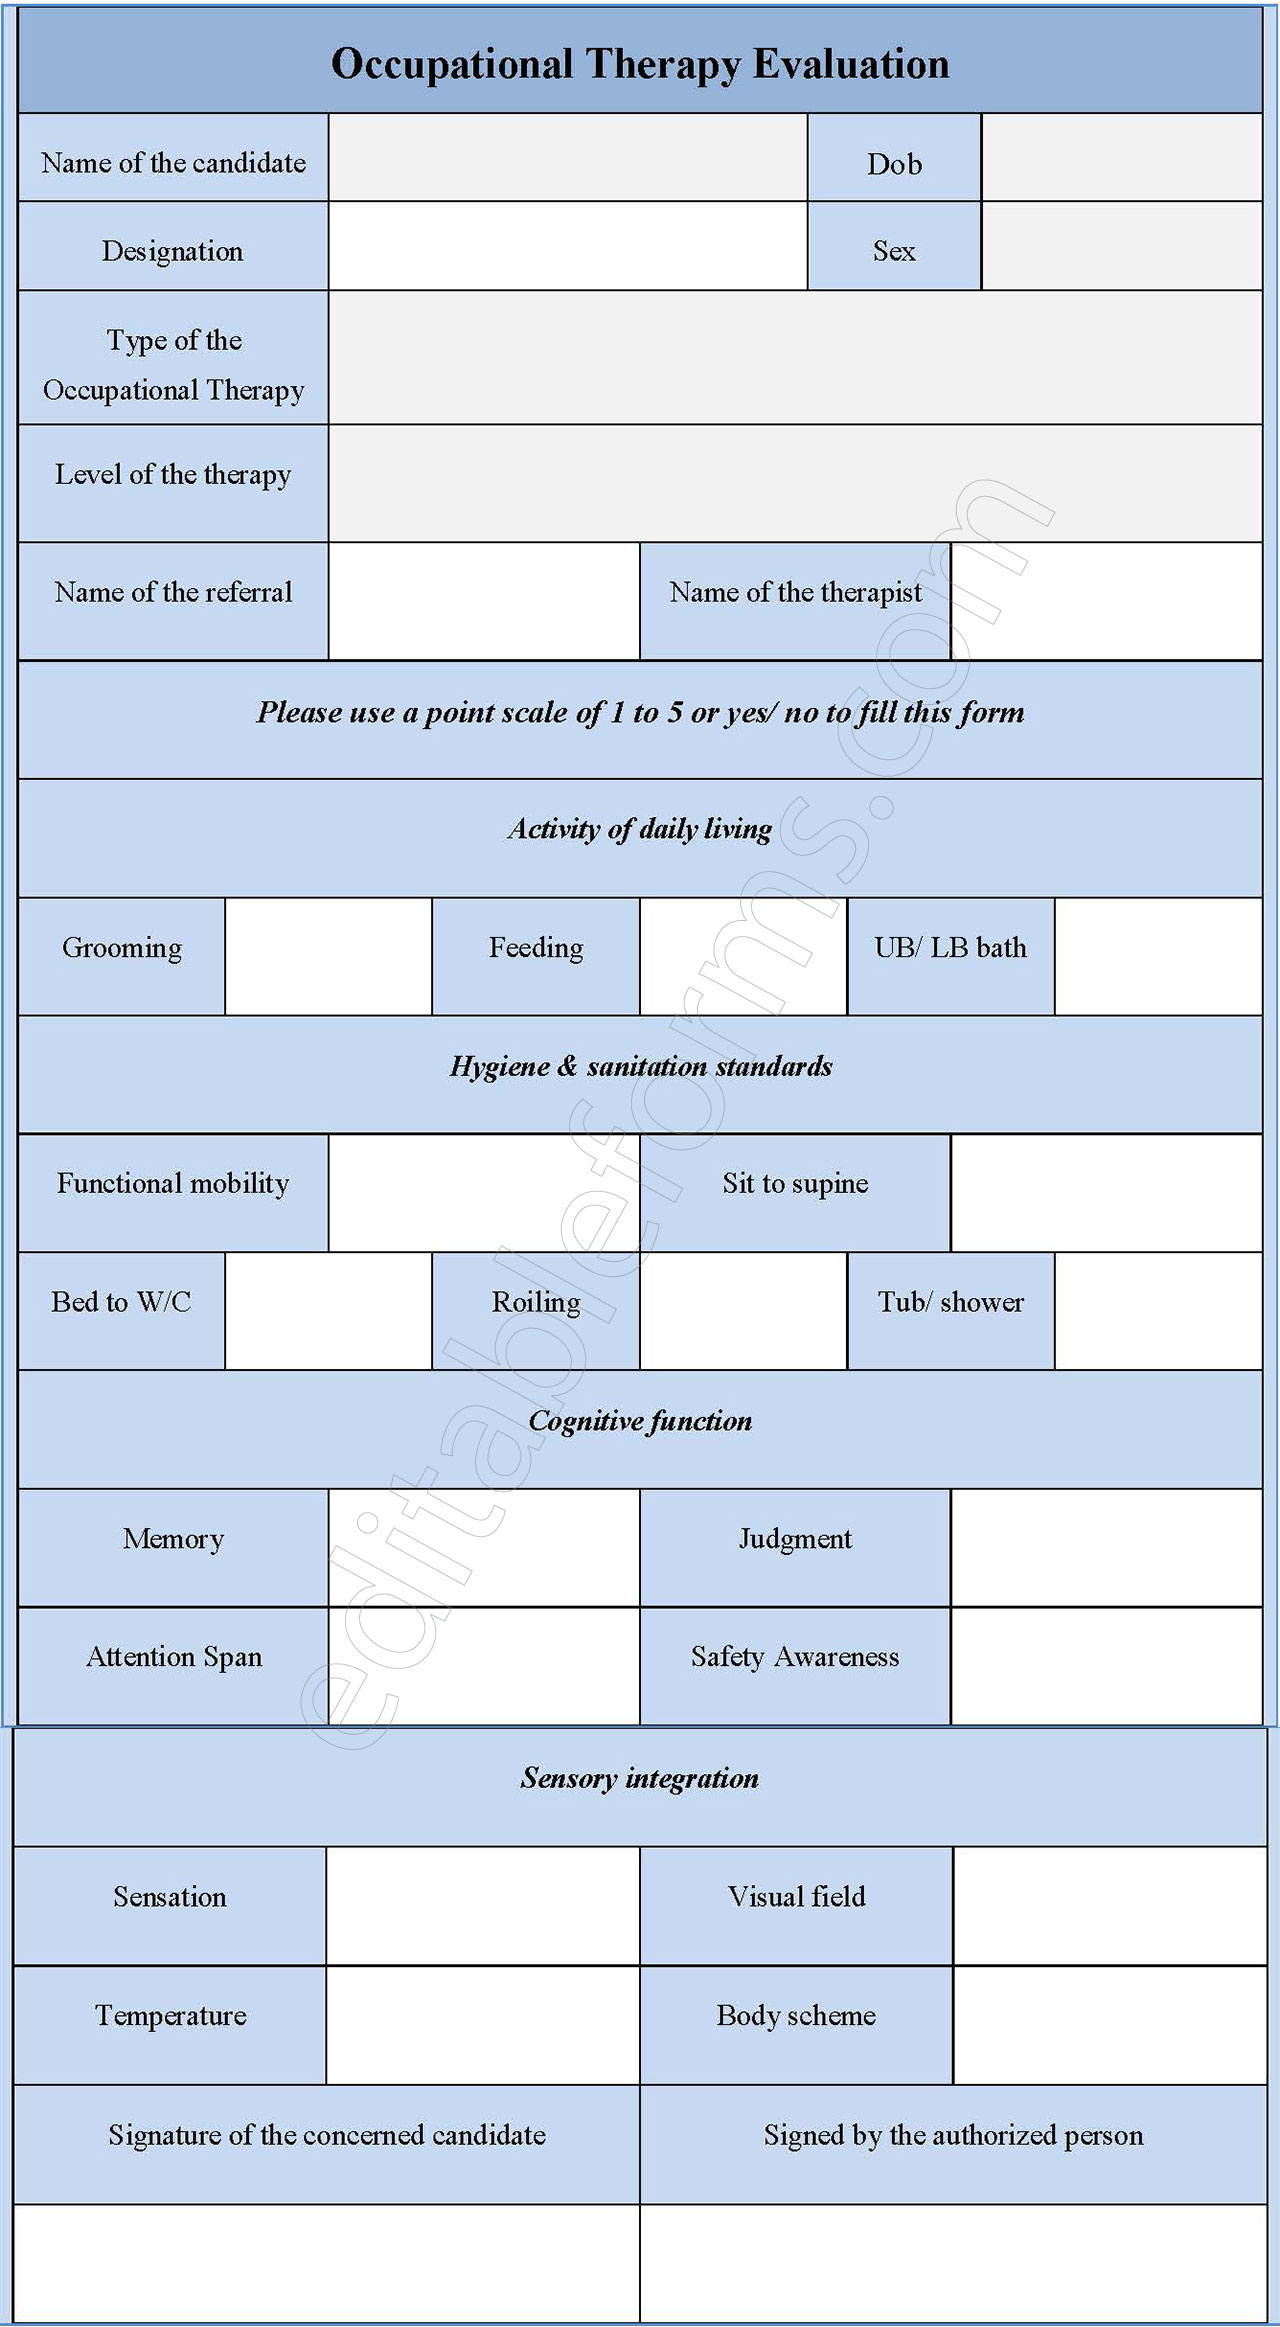
Start with the chief reason for referral and the physician's stated diagnosis. Then move through Activities of Daily Living and Instrumental ADLs in the order the patient encounters them during a typical day. Wake up, toilet transfer, hygiene, dressing, feeding, mobility through the home, meal preparation, medication management. This chronological flow catches problems that checklist-style assessments miss. For ADLs, I use the Modified Barthel Index or the FIM, depending on what the payer recognizes. For cognition and perception, the MoCA or MMSE gives you a baseline, but I always pair it with a functional observation — can the patient find their pills, can they follow a two-step command while cooking, do they recognize the danger of a hot stove they haven't used in weeks. Standardized scores alone don't carry certifications. Environmental assessment takes 10 to 15 minutes and should include: bathroom grab bar presence and stability, shower chair or tub bench feasibility, stair condition and handrail availability, clearance for walkers or wheelchairs in hallways and doorways, kitchen counter height and reachable storage, bed height relative to the patient's leg length, and any throw rugs or cord hazards. I photograph the setup when permitted and when the patient consents. Photos in the record prevent "he said she said" disputes during audits.
Get the Full Details

Documentation specifics that matter
Every functional limitation needs three things: the specific task, the actual performance level with qualifiers, and the medical reason linking it to the diagnosis. "Lower extremity weakness secondary to left CVA" is not enough. Write "Patient requires minimal contact guard assistance for sit-to-stand from a standard-height toilet due to right lower extremity quadriceps strength rated 3/5 on manual muscle testing following left MCA stroke." IADL documentation gets short-changed more often than anything else. Cooking, managing medications, telephone use, financial tasks, laundry — these determine whether a patient can safely remain at home or need placement. Document what the patient actually attempted, what they could not do, and what adaptive strategies or equipment would bridge the gap. A patient who cannot safely operate a stove does not need handwriting therapy. They need a single-burner electric warmer and meal delivery referral. Match the intervention to the actual barrier. Equipment recommendations must include HCPCS codes whenever possible. "Shower chair" is not documentation. "Shower chair, non-upholstered, standard width (K0014)" is. Payers deny claims for vague DME descriptions constantly. Being specific in the evaluation note speeds up the supply chain and reduces follow-up calls.
Common pitfalls I've seen destroy claims
The most frequent error is documenting both a safe and unsafe performance level for the same task. If the patient performed a transfer with modified independence AND with moderate assistance during the same visit, pick one and justify it. Auditors read that as inconsistent and will question the entire note. Use the higher assistance level — it's safer from a compliance standpoint and reflects the true daily risk. Another pitfall: goals that are not measurable or not tied to functional outcomes. "Improve upper extremity function" will get rejected. "Patient will independently transfer from bed to chair using a slide board with minimal verbal cues within 14 days, as measured by observation during daily treatment sessions" is what you write. For cognitive-communicative cases, the pitfall is assuming the standard psychometric tests capture home safety. A patient can score 26 on the MoCA and still leave the stove on every morning. Always pair the score with a direct observation of a relevant functional task, even if it's just making a cup of tea in the home kitchen.
Recertification and ongoing evaluation
The initial eval sets the trajectory. The 30-day and 60-day recertifications reference the original baseline. If your initial documentation is thin, every subsequent period of care looks like guesswork. Reassess with the same tools you used initially so progress and decline are quantifiable. A patient who went from 45 to 62 on the Barthel Index between visits is demonstrably improving. That drives payer confidence. Not every case fits this model. Patients with severe advanced dementia, active hospice, or rapidly deteriorating neurological conditions may not benefit from intensive functional measurement. In those situations, a symptom management and caregiver support focus is more appropriate, and the evaluation should reflect that shift explicitly rather than forcing standardized ADL scores that will read as artificially low regardless of intervention. The bottom line is that a well-executed home health OT evaluation is equal parts clinical assessment and environmental audit. The home tells you what the clinic never will, and the note needs to prove it with specific, observable, billable detail.