Why the OT Framework Actually Matters in Daily Charting
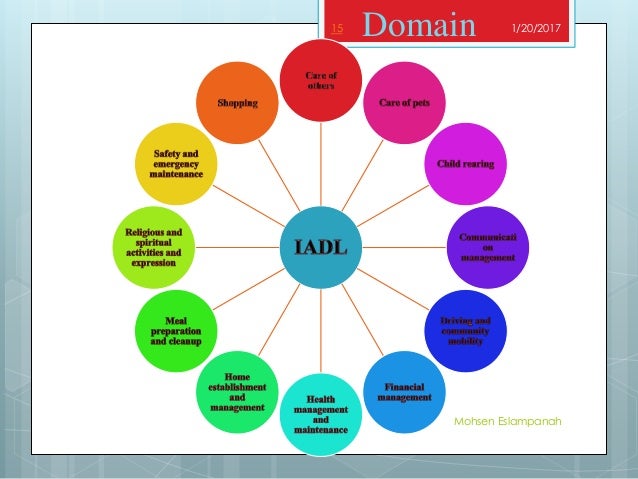
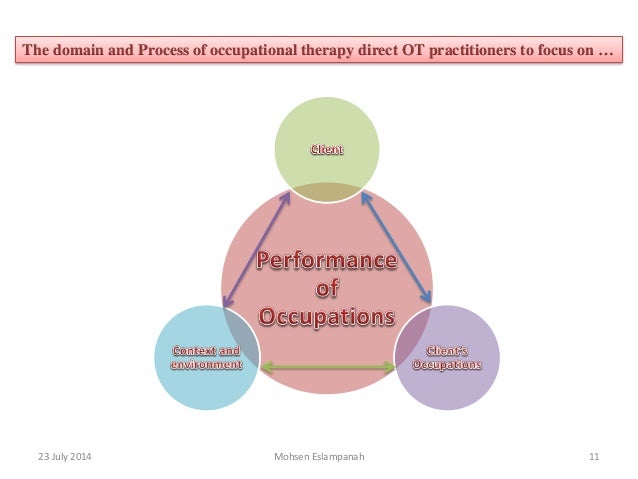
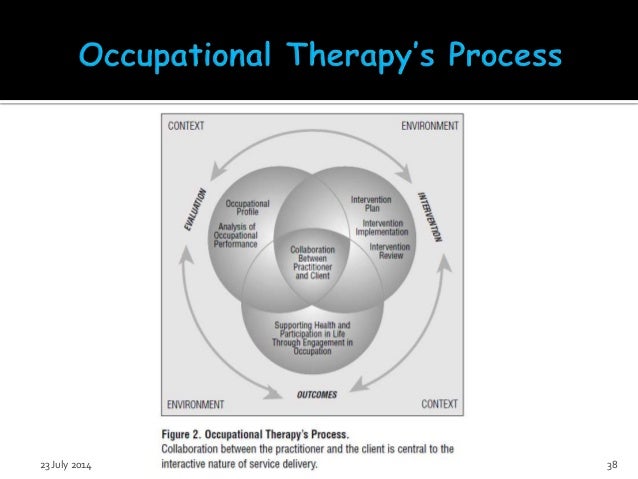
The Occupational Therapy Practice Framework Domain And Process is your actual roadmap for documentation, treatment planning, and insurance justification. It is not a suggestion box. When you pull it apart, it breaks into two buckets: the Domain, which is what OT does, and the Process, which is the sequence of how you do it. The Domain section covers five main areas. Occupations, meaning the actual activities people need or want to do. Client factors like body functions and body structures. Performance skills, which are the clinician-observable behaviors. Performance contexts, both environmental and personal. And interventions, the activities you actually select. The Process side follows a linear path that most therapists compress in practice. Evaluation, analysis of results, intervention plan, intervention implementation, and outcomes reassessment. You can skip steps if you are doing short-term work, but skipping evaluation entirely is why your denials pile up.
I spent years watching new OT grads treat the process as a checklist. They would complete an evaluation using standard measures, write a plan that read like a wish list, then document intervention as if they were recording grocery items. The framework was completely invisible in the chart. Insurance reviewers noticed immediately.
What Actually Happens When You Apply It Correctly
Here is where the framework gets useful, not just theoretical. When you link each intervention activity back to a specific occupation and a measurable client factor, the clinical reasoning becomes visible on paper. You are not saying the patient did balance exercises. You are saying the patient worked on truncal control during stair climbing because they need to safely navigate their home environment before discharge. The process section gives you a repeatable structure. Start with evaluation using both standardized tools and clinical observations. Move to analysis where you identify gaps between current performance and desired outcomes. The intervention plan should specify frequency, duration, intensity, and the specific techniques you will use. Implementation gets documented in real time, not recreated from memory three weeks later. Outcomes reassessment happens at predetermined intervals, usually every 10 sessions or at discharge. I ran into a real edge case last year involving a stroke patient with severe unilateral neglect. The standard framework application would have you document deficit retraining for visual scanning, but the actual problem was that the patient refused to eat because they could not find food on their plate. I had to reframe the intervention around the occupation of eating rather than the impairment of visual scanning. We used a plate with a red rim on the affected side and structured feeding sessions around that modification. The framework still applied, but the occupation took priority over the impairment. Documentation reflected that choice explicitly, and the payer accepted it without pushback.
Get the Full Details
Where the Framework Fails You
The biggest limitation is that it assumes a logical sequence that rarely exists in real clinics. You will often start intervention before finishing the full evaluation because scheduling pressure forces your hand. You will reassess outcomes when the patient misses appointments, not because you planned to. The framework does not account for the chaos of actual practice. Another issue is the personal performance context factor. It requires you to document things like motivation, habits, and values, which most insurance forms do not have fields for. You end up writing paragraphs that nobody reads. Focus on observable performance contexts instead of speculative ones.
Practical Tips That Actually Work
Use the framework language when writing objectives. Instead of writing improve patient strength, write facilitate upper body function during self-feeding to increase independence in activities of daily living. The specific occupation ties the intervention to the Domain and makes the clinical reasoning defensible. Keep your process steps visible in the chart. A simple header for each session noting which step you are in, evaluation or intervention or reassessment, helps both you and any reviewer follow the logic. I use a one-line header at the top of each note that states the current process phase and the targeted occupation. When using the framework for billing, the process section is your protection. Payers reject claims when the connection between the evaluation findings and the intervention choices is missing. Document the gap you identified and the specific technique you used to address it. Four lines of reasoning beat four pages of procedure notes.