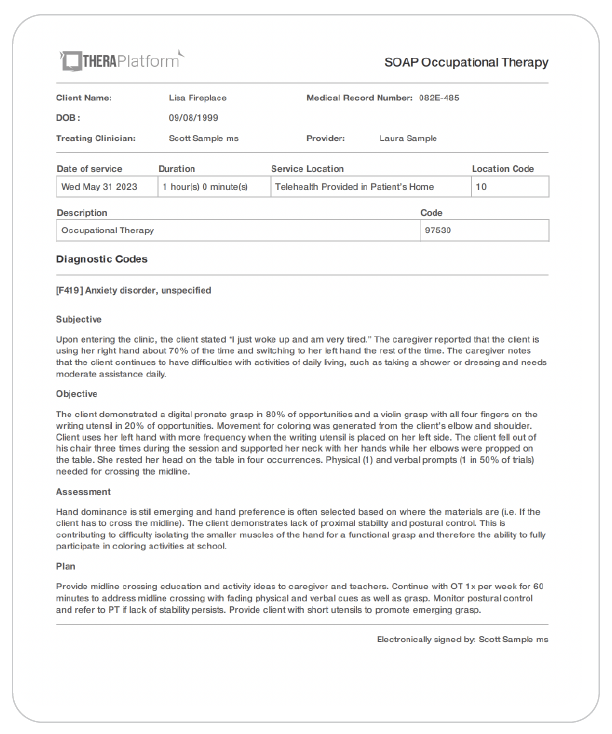
Why Your SOAP Notes Keep Getting Flagged
I spent four years getting my documentation rejected or partially approved before I stopped fighting the format and actually learned how to write for it. The problem isn't knowing what you did in a session. It's translating that into something a payer reviewer, a compliance auditor, and your treating OT can all read and agree on within three minutes. Here's how the process actually works when you're doing it for real. SOAP stands for Subjective, Objective, Assessment, and Plan. That part you already know. What nobody tells you is that each section has a different audience and a different standard of what counts as sufficient documentation. Subjective is for the patient and anyone reading the clinical story. Objective is for the payer who is looking for medical necessity. Assessment is where you connect the dots. Plan is where you justify the next visit. I used to write subjective notes that were paragraphs long because I wanted to capture the patient's experience. Then an auditor told me it was vague and unsupported. The fix was simple: I started listing exactly what the patient reported using their own words in quotation marks, then stopped. "I can't lift my arm to brush my hair anymore" is a subjective statement. It's also defensible. I kept it at one to two sentences per relevant complaint. The rest of the space went to measurable data.
The Objective section is where most people fail. Not because they can't measure things, but because they measure the wrong things. You need range of motion numbers, strength grades, functional task scores, and time on task. But the key insight is this: payers don't care about your perfect goniometer readings if you don't tie them to a functional outcome. I learned that the hard way when a Medicare review denied a claim because I had documented wrist ROM but never showed how that ROM translated to the patient dressing themselves. After that, I started including at least one standardized measure in every Objective section. Quick Disabilities in Upper Extremities, nine-hole pegboard, or grip strength depending on the population. One measure per note is enough. Two is better. It takes about ninety seconds to administer and thirty seconds to record. Assessment is the shortest section and the one people overthink. A good Assessment answers three questions: is the patient improving, is the diagnosis still valid, and is continued therapy medically necessary? I used to write pages here. Now I write four to six sentences maximum. The structure is improvement trajectory, barrier to progress, and rationale for continuation. That's it. If you can't answer those three things, your note is a report, not an assessment. Plan is straightforward but frequently sloppy. Most OTs just write "continue weekly OT" and call it done. That's not a plan. A real plan specifies frequency, duration, and the specific interventions planned for the next session, plus any home program updates. "Continue OT 2x/week for 45 minutes, focusing on ADL training with adaptive equipment and upper extremity strengthening" gives a reviewer everything they need. It also gives you a defense if a payer questions the frequency.
Here's something most guides won't tell you about Occupational Therapy Soap Notes: the Subjective section can be written by the patient or a caregiver in many outpatient settings, and that's often more defensible than your paraphrase. I started having patients fill out a brief subjective prompt on clipboards before sessions. "What has been difficult since your last visit?" takes them ten seconds and gives you a contemporaneous record. Auditors prefer that over your interpretation of what they told you three weeks ago. Another thing nobody mentions is the problem of documentation lag. If you write your notes at the end of the day, or worse, at the end of the week, your Objective data becomes unreliable. I've had situations where a patient's pain level changed between sessions and my note didn't reflect that because I wasn't writing it in real time. The workaround was brutal but effective: I kept a blank SOAP template on my tablet during each session and filled in the Objective data while the patient was still in the room. Subjective came right after. Assessment and Plan went home with me because they required clinical judgment that couldn't be rushed. This cut my average note completion time from about twenty-five minutes per chart down to roughly eight minutes of actual writing time, with the rest being data capture during the session itself. There are downsides to this approach. Real-time data capture means you're less available to the patient during the session. I solved that by embedding data collection into the treatment activities. Grip strength measurements happen during strengthening. Range of motion checks happen during stretching. The nine-hole pegboard becomes the fine motor task. It's not a separate assessment period. It's the treatment period with a clipboard nearby. Some clinics don't allow tablets at the treatment table, and that's a legitimate constraint. In those cases, paper templates with check boxes work almost as well and take less time to fill out than free-form writing.
Get the Full Details

The biggest mistake I see in Occupational Therapy Soap Notes is mixing Interventions with Objective data. When you write "performed UE strengthening with theraband" under Objective, you're documenting treatment, not outcomes. That belongs in your Plan or in a separate Treatment column if your EHR supports it. Objective should contain only what you observed and measured. If your facility's template doesn't separate these clearly, add a divider line or a subheading. It costs nothing and prevents a category error that reviewers catch immediately. Another nuance: time-based billing requires you to document total direct contact time, not just treatment time. If you spend twelve minutes on evaluation and thirty-three minutes on intervention, your total is forty-five minutes. Write it as total time with a breakdown. Most EHR systems have a timer field. Use it. Manually calculating time from memory is how people lose billable minutes and raise red flags during audits. If you're working with pediatric populations, the Subjective section needs to include caregiver report since the child may not be a reliable historian. I once had a note rejected because I only documented the child's self-report on a gross motor task, and the auditor noted that a six-year-old's perception of functional ability is not clinically valid without caregiver corroboration. After that, I always include at least one parent or guardian statement in the Subjective for any patient under eight years old. It's a small addition that prevents a major compliance issue.
There's no universal template because EHR systems vary too much. What works in Epic doesn't map cleanly to Meditech, and neither matches the paper forms some rural clinics still use. The core structure stays the same regardless of platform. Subjective is what the patient says. Objective is what you measure. Assessment is what it means. Plan is what happens next. Everything else is formatting decoration.