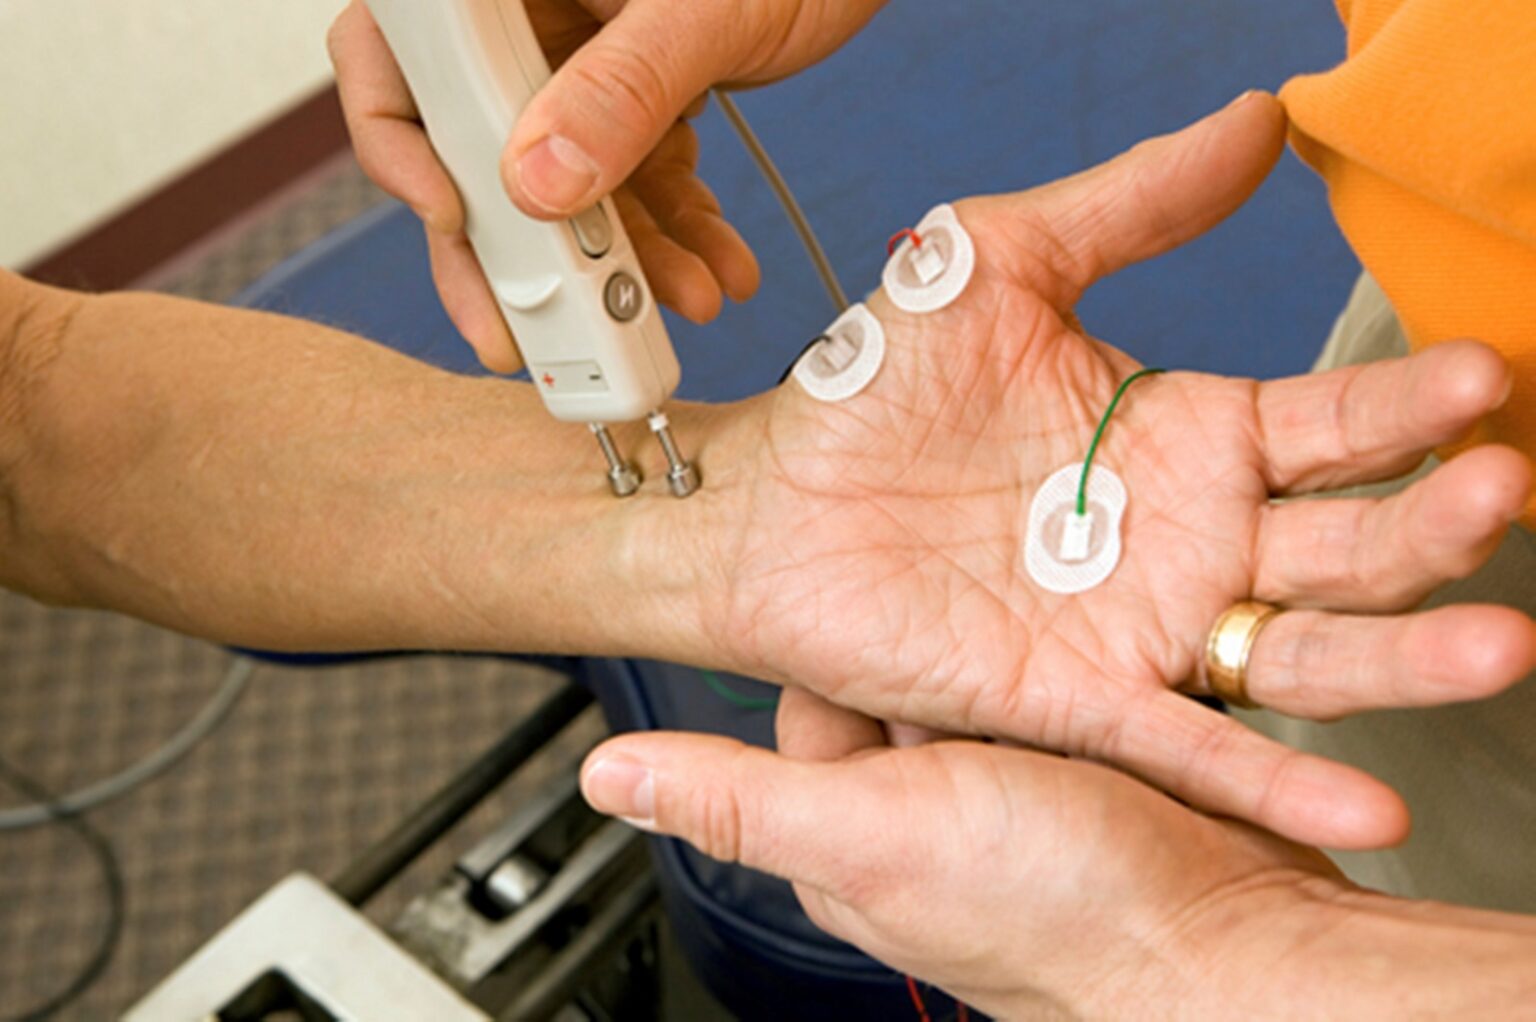
What actually happens in an OT session for hand neuropathy
Most people walking into occupational therapy expect someone to massage their hands and hand them a grip strengthener. That is not remotely what happens. A proper program for neuropathy in the hands involves desensitization work, sensory re-education, functional task training, and often some bracing or adaptive equipment recommendations. The goal is not to cure the nerve damage — nerves heal slowly and sometimes not at all — but to rebuild whatever function remains and protect the hands from further injury. Session structure depends heavily on the severity and cause. Diabetic peripheral neuropathy, compression neuropathies like carpal tunnel, and chemotherapy-induced neuropathy all present differently and require different approaches. In my experience, starting with a thorough sensory mapping is non-negotiable. You need to know exactly what is still working before you build a program on top of it. I use a monofilament set, texture discrimination materials, and temperature testing — cold and warm objects separated by touch alone. The patient closes their eyes and identifies locations on the hand and fingers when touched. This takes about ten minutes but gives you a baseline that tells you everything you need to know about where to focus. From there, desensitization techniques come first for most patients. Hypersensitivity to touch is one of the most common and most frustrating symptoms. It makes everyday tasks unbearable. Lightly rubbing the affected areas with different textures — cotton, wool, silk, then gradually introducing coarser materials like a towel or soft brush — helps the nervous system recalibrate. This is not something patients typically want to do because it is uncomfortable at first. But it is one of the most effective interventions available and it works if you push through the initial resistance. I usually have patients spend five to ten minutes per session on this, progressing every one to two weeks based on tolerance.
Sensory re-education follows once hypersensitivity decreases enough for the patient to tolerate it. This involves two-point discrimination training, shape recognition with objects placed in the hand, and matching exercises. The patient identifies coins, buttons, or small household items by touch alone. Then they progress to more complex tasks like sorting peas from beans or buttoning shirts. Each step builds on the last. Progress can be painfully slow — I have seen patients improve from zero two-point discrimination to around eight millimeters over four to six months with consistent daily practice. That is not a failure. That is a realistic timeline for nerve regeneration. Functional training is where things get practical. Patients practice exactly the tasks they struggle with in daily life. Typing on a keyboard with reduced sensation. Picking up fragile objects without crushing them. Opening jars. Zipping coats. Doing makeup or applying lotion without visual compensation. These tasks feel mundane but they are the actual reason someone comes to therapy. If you skip them, the treatment becomes abstract and patients lose motivation within three sessions. I always tie every exercise back to a real-world task the patient identifies at intake. Adaptive equipment and bracing are part of the conversation too. Wrist orthotics for daytime or nighttime use, jar openers, button hooks, built-up utensil handles, and key turners can make a massive difference in independence. Some patients resist these heavily because they associate them with being "disabled." That is a cultural problem we deal with constantly. I just present them matter-of-factly as tools that buy you function back. Most patients accept them quickly once they see someone else using them successfully.
I ran into a tricky case last year with a patient whose neuropathy was primarily affecting proprioception — she could feel touch but had no sense of where her fingers were positioned in space. Standard desensitization and texture work did almost nothing for her. What actually helped was weight-bearing through the palms on a therapy table with feedback, combined with rubber band resistance exercises for finger positioning. Giving the joints compressive input reactivated the proprioceptive pathways enough for her to start regaining coordination. It took about eight weeks of dedicated work. This is the kind of edge case that proves you cannot follow a rigid protocol and expect results. You have to assess, adapt, and try something different when the standard approach stalls.
Get the Full Details

Pitfalls and what usually goes wrong
The biggest mistake patients make is inconsistency. Nerve-related interventions require daily engagement. Twenty minutes of sensory work at home every day beats one grueling hour in the clinic once a week. I see this constantly. Patients show up, do the exercises, feel fine, then disappear for three weeks. The nervous system does not retain gains the way muscles do. You lose progress faster than you gain it. Another common problem is overloading sensitive hands. Patients with reduced protective sensation are at real risk of burns, cuts, and abrasions because they cannot feel damage happening. I always recommend testing water temperature with the elbow or forearm first, wearing gloves for any task involving sharp or hot objects, and inspecting the hands daily for injuries they may not have felt. This is not optional advice. It is the part of treatment that prevents serious complications. Some patients also expect faster results than nerves can deliver. Peripheral nerves regenerate at approximately one millimeter per day, which means recovery from the wrist to the fingertips can take six to twelve months minimum. Patients who want a quick fix either drop out or get disillusioned. Being upfront about timelines at the first session saves everyone time and frustration. A typical progression looks like this: desensitization over four to eight weeks, sensory re-education over three to six months, and functional gains continuing to improve for up to a year depending on the underlying cause and severity.
Therapy will not reverse axonal loss. If the nerve has been severely damaged or transected, no amount of exercise will restore sensation. Surgical intervention may be necessary in those cases. OT complements medical treatment but it is not a substitute for it. Patients who believe therapy alone will fix structural nerve damage end up disappointed. Make sure that boundary is clear from the start.
What you can do outside of sessions
Home programs are where treatment actually sticks or fails. Beyond the prescribed exercises, I recommend avoiding prolonged static positions that compress the nerves. Taking micro-breaks every thirty minutes during repetitive tasks like computer work. Managing blood sugar levels if diabetes is the cause. Reducing alcohol consumption, which accelerates nerve damage. These are not exciting recommendations but they directly affect outcomes. No amount of hand exercises will outperform uncontrolled glucose or continued alcohol exposure. Massage and self-myofascial release of the forearm and wrist can help reduce secondary muscle tension that may be contributing to compression. A simple ten-minute forearm massage before doing sensory exercises can make a noticeable difference in how well the exercises land. I tell patients to focus on the flexor and extensor muscles along the forearm, not the hand itself. The hand is already overloaded with work. Nutrition plays a role too. B vitamin deficiencies, particularly B12, are linked to peripheral neuropathy. Checking levels and supplementing when low is a straightforward medical step that some patients overlook. Omega-3 fatty acids and alpha-lipoic acid have some evidence supporting nerve health, though the effects are modest and individual. Worth mentioning but not worth overselling.

If neuropathy is progressing despite treatment, if sensation is spreading to the feet or legs, or if you develop weakness alongside the numbness, that warrants re-evaluation. It may not be simple peripheral neuropathy anymore. Entrapment, systemic disease, or other neurological conditions can present similarly in the early stages. Getting the diagnosis right matters more than starting the right exercises.