Setting Up a Realistic OT Workload Model
An Occupational Therapy Workload Calculator is a tool—usually a spreadsheet, sometimes a small app—that takes your patient list, session durations, and scheduling constraints and produces a daily or weekly hour estimate so you can see whether your caseload fits inside your actual clinical clock. The math is straightforward, but the details matter. Raw formulas without the right inputs produce numbers that look precise and mean nothing. Here is the calculation I actually use. Total Patient Load Hours equals the sum of each patient's session time across all scheduled visits. You then add Administrative Time, which I calculate at 15 percent of direct care hours. Divide by Available Clinical Hours—the time between when your doors open and when you have to sit down for charting—and you get a daily utilization ratio. Adjust for Concurrent Sessions by subtracting the weighted overlap, and adjust for Travel Time between sites by adding roughly 8 minutes per transit segment.
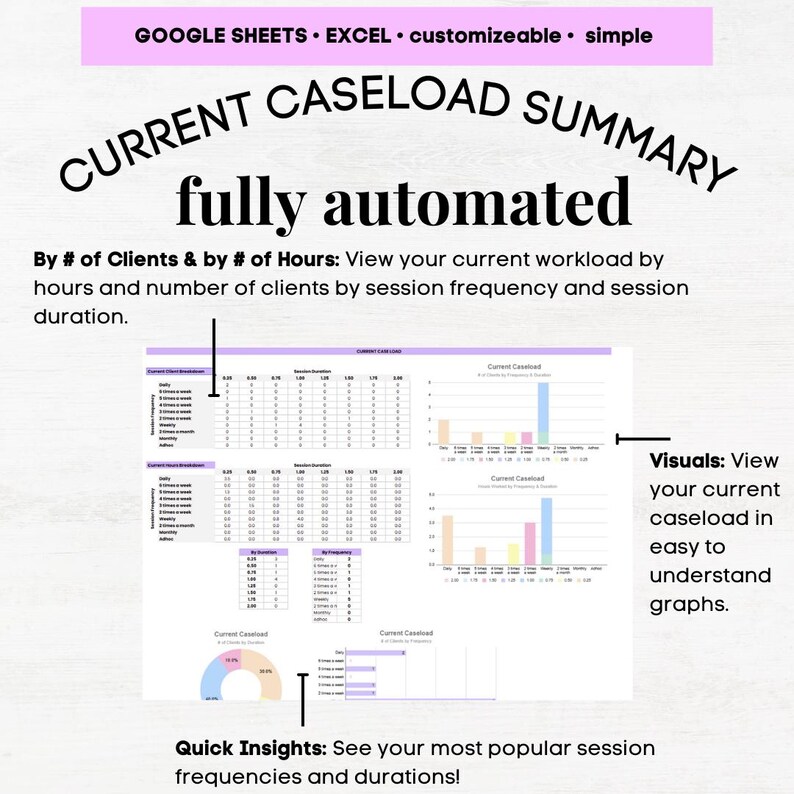
Occupational Therapy Workload Calculator: Setting Up the Spreadsheet
Most people build this in Excel or Google Sheets. The core columns you need are Case ID, Primary Diagnosis, CPT Code, Session Duration in minutes, Expected Attendance Rate, Concurrent or Solo flag, and Travel Minutes to and from the site. Then you add calculated columns for Billable Units per Day, Effective Load Hours, and Daily Overrun. For billable units, take your session frequency per week, multiply by units per visit, and divide by your authorization cap. That tells you whether the scheduler can book the next patient or whether you have to drop a referral. A 30-minute OT evaluation runs two CPT units. A 60-minute re-evaluation is also two units but consumes double the clock time, which most templates miss entirely. I ran into a specific problem last year with a multi-site geriatric rehab program. The EMR exported clean session data, but the tool had no field for inter-facility transport because the schedule manager assumed all patients were on one floor. The calculator reported I had 38 clinical hours available on a Tuesday. In reality, I spent 47 minutes driving between buildings and couldn't see anyone in the afternoon block. My workaround was adding a manual override column called Actual Gap Time, where I logged non-patient minutes at the end of each shift and fed that back into the weekly average. Once I did that, the weekly projection matched my actual available hours within 4 percent.
The more stubborn issue I hit involved concurrent sessions in acute care. The model treated every occupied chair as a full unit of capacity. When two patients shared a room for balance training, the calculator counted 12 patients on the board but my cognitive load was equivalent to handling eight. I started applying a 0.7 weight multiplier to concurrent cases, which brought the effective load much closer to what I actually experienced minute by minute.
Get the Full Details

Where the Calculator Actually Fails
The first failure mode is unpredictability in pediatric populations. A child with severe spasticity may require 45 minutes of setup time before treatment begins, and the tool cannot predict that from the CPT code alone. You have to add a diagnosis-specific buffer. I keep a hidden column with manually adjusted durations for high-acuity cases, and the rest of the sheet pulls from the standard baseline. The second failure mode is mental health days. A scheduled 30-minute session can turn into a 75-minute intervention if a patient decompensates. The calculator has no variable for behavioral escalation, so the hour projection stays accurate on paper and completely wrong in practice. I flag these days with a manual risk multiplier of 1.4 and accept that some variance is unavoidable. A third failure mode involves documentation burden. The model assumes 15 percent admin overhead, but insurance audits and prior authorization responses routinely push that to 22 or 25 percent on heavy Medicaid days. When that happens, your clinical hours shrink without any visible signal from the tool. I learned to run a monthly reconciliation where I compare the projected admin percentage against the actual time I spent on paperwork, then adjust the overhead constant for the following month.
Exporting Data and Working Around EMR Limits
Epic and Cerner both support schedule exports, but the formats differ. Epic pushes a CSV with visit timestamps and provider IDs. Cerner tends to group by unit rather than by individual therapist, which means you have to manually disaggregate the data before it is useful. If your system does not allow a direct export, you can pull a screenshot of the weekly schedule and use a simple macro to extract the relevant fields, though that adds about ten minutes per week to your setup time. There are a few free templates floating around from professional associations, but most of them are outdated. They assume a 40-hour week with no travel, no concurrent cases, and no documentation load, which makes them useful only as a starting point rather than a functional tool. The better approach is to take a blank sheet and populate it from your own exported schedule, which usually takes about 20 minutes the first time and then becomes a recurring five-minute task.
When to Stop Using the Calculator and What to Use Instead
Stop relying on this model when your schedule involves seasonal demand spikes that exceed normal variation by more than 30 percent, because the tool cannot forecast surges without manual input. It also breaks down when staffing changes mid-week, since the projection is static and will not recalibrate automatically. In those scenarios, a rolling two-week moving average based on actual logged hours works better than any forward-looking formula. The biggest mistake I see is applying this calculator to individual therapists instead of to the department level. Individual schedules are too noisy. Running the model across the entire OT caseload smooths out the outliers and gives you a usable signal. The numbers become actionable when you are looking at department-wide capacity, not at one person's particularly bad week. Once you have the calculator running, the actual value comes from comparing the projected overload days against the days you can redistribute or defer. A typical setup cycle takes about 15 minutes once the template is built, and it usually prevents at least two scheduling conflicts per month that would otherwise show up as weekend catch-up work or rushed documentation. The tool does not fix bad scheduling practices, but it makes them visible fast enough that you can adjust before the month closes.