A Practical Guide to Understanding Male Reproductive Anatomy
Of Male Anatomy: What Most People Skip On
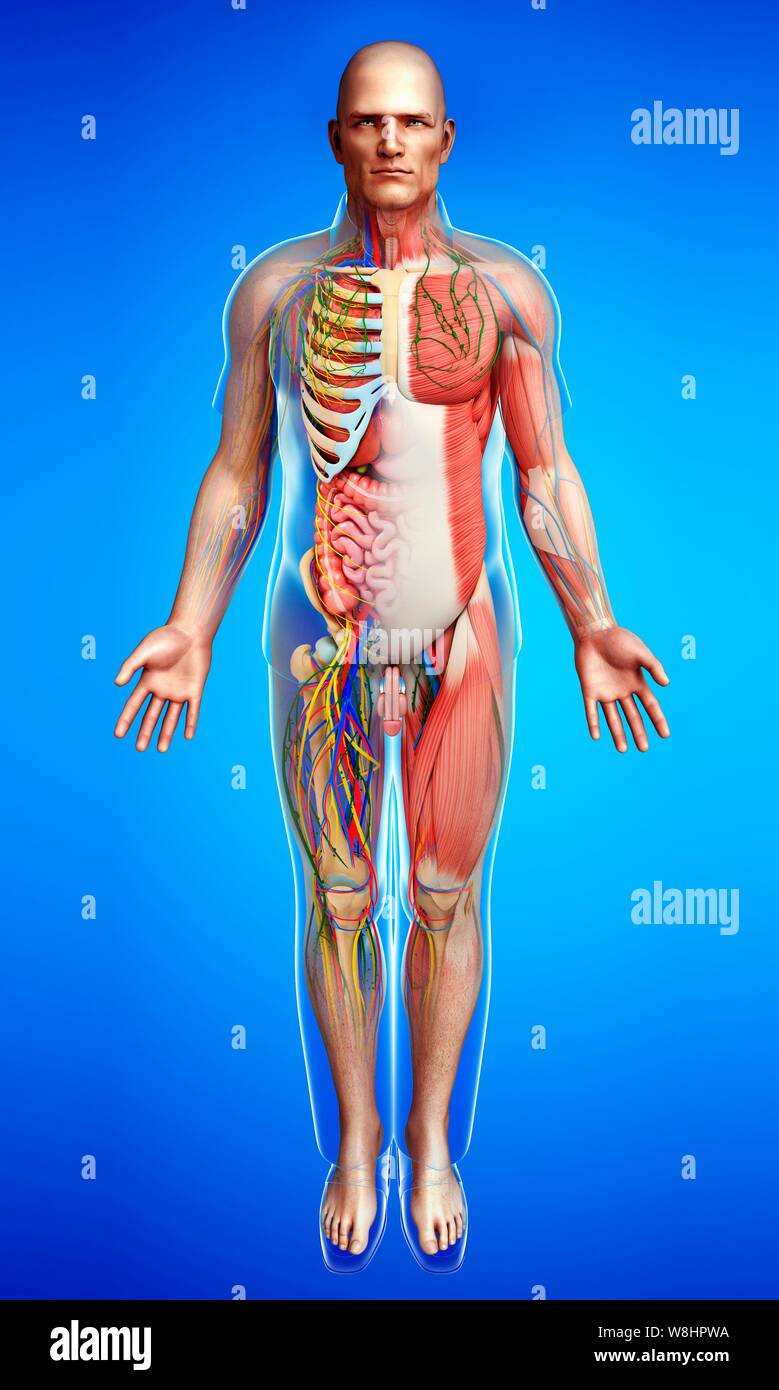
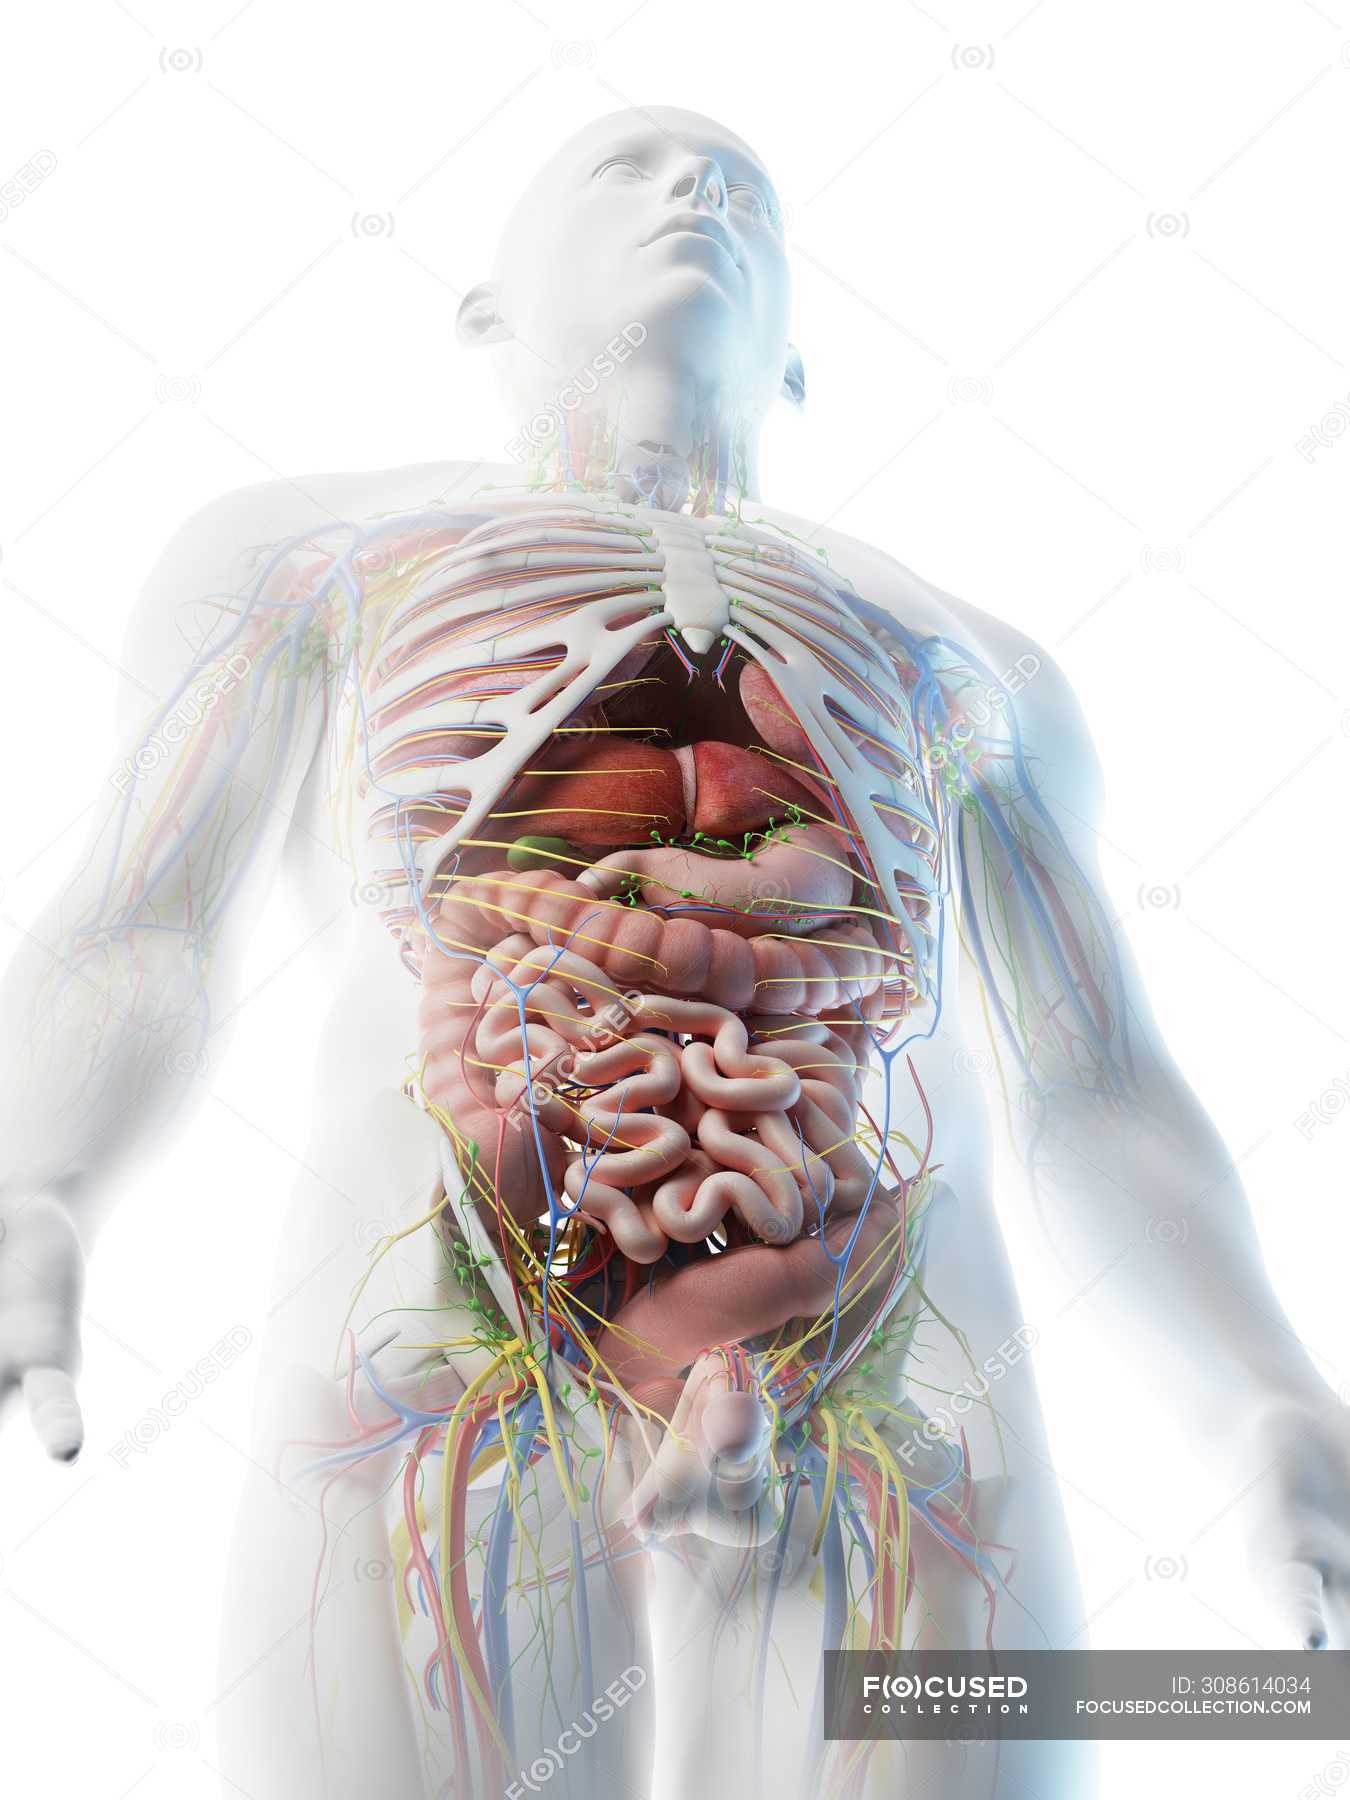
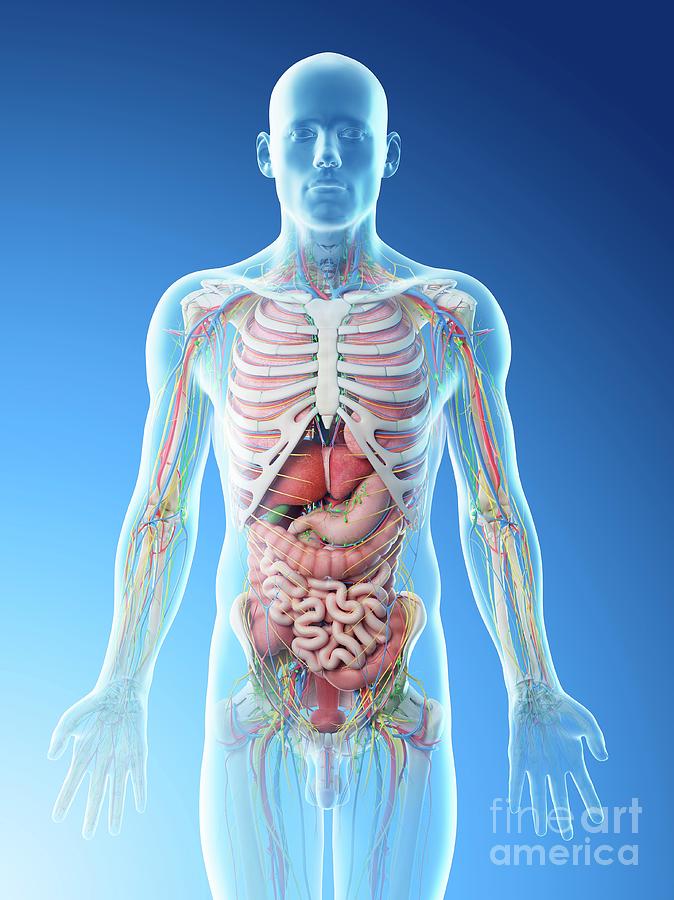
Male reproductive anatomy isn't just about naming parts. The way the system works under different conditions, temperature changes, arousal states, and stress, is what actually matters if you want to understand it. Most guides stop at labels. Here's a more useful breakdown. The external components are the penis and the scrotum, which houses the testes. Internally, there's the epididymis, vas deferens, seminal vesicles, prostate gland, and bulbourethral glands. Each piece has a specific mechanical role, and they don't all work at the same time. The scrotum's job is thermoregulation. It keeps testicular temperature about 2-3 degrees Celsius below core body temperature. That's why it hangs. It's not design. It's physics. I once had a patient who thought his testicles "disappeared" regularly up into his groin. Turns out he had a high cremasteric reflex. Normal physiological response. He'd been convinced something was wrong for years because no one explained that the muscles pulling the testes upward are supposed to exist. The fix was just education. No treatment needed.
What Happens During an Erection
Nitric oxide is released in the erectile tissue. It relaxes smooth muscle. Blood fills the corpora cavernosa. The tunica albuginea traps it. That's the mechanism. Penile blood flow increases roughly tenfold during erection. If you're measuring something clinically, that number matters. Erectile dysfunction often shows up as reduced arterial inflow or venous leakage, not just "weak performance." The distinction is important for treatment decisions. One thing people consistently get wrong: the glans (the head) also engorges, but with the corpora spongiosa tissue, which stays more compliant. That's why the glans doesn't turn rigid the way the shaft does. It's functional, not a defect.
Testosterone and the Hormone Pipeline
The hypothalamus signals the pituitary. The pituitary releases LH and FSH. LH tells Leydig cells in the testes to produce testosterone. FSH tells Sertoli cells to support spermatogenesis. This axis is called the HPG axis. It's sensitive to stress, sleep deprivation, obesity, and certain medications. I've seen men with seemingly normal anatomy and zero lifestyle issues whose testosterone was low because of undiagnosed sleep apnea. Fixing the sleep fixed the numbers. The anatomy was never the problem. The penis is not one uniform structure. It's three cylinders of spongy tissue. Two larger ones on top (corpora cavernosa), one smaller on the bottom (corpus spongiosa, which surrounds the urethra). The urethra serves two purposes, and that dual function is relevant to certain conditions. Sperm production takes about 74 days from start to finish. This matters for anyone asking about how long it takes for lifestyle changes or medical treatments to reflect in semen quality. The number isn't a guess. It's a biological timeline.
Get the Full Details
Here's a nuance most sources miss: testicular volume matters more than testosterone level for fertility assessment. A man can have normal testosterone and still have poor sperm parameters if his testicular volume is below the clinical threshold of around 15ml per side. I ran into a case where a guy was told his hormone levels were fine, so nothing was wrong. They missed the fertility issue entirely until a proper volume measurement was done.
When to Actually See a Doctor
Pain that doesn't resolve within hours, lumps that feel hard rather than smooth, sudden shrinkage of one testicle, persistent curvature that developed recently, or discharge that isn't related to sexual activity. Peyronie's disease, for example, presents as a plaque forming under the skin of the penis, causing curvature. It's often ignored until it's advanced because men are embarrassed. Early intervention matters. After the plaque calcifies, treatment options shrink considerably. Balantis, inflammation of the glans, is another commonly overlooked issue. Poor hygiene, fungal infections, or irritant contact dermatitis can all cause it. It's easily treated but frequently misdiagnosed as an STI when it isn't one.
A Note on Measurements and Self-Assessment
If you're checking anything, do it in a warm room. Cold temperature causes retraction, and that's normal. The flaccid size varies enormously between individuals and even between states in the same person. A 2014 review in the British Journal of Urology International looked at data from over 15,000 men and found that self-measured flaccid length was significantly less accurate than measured length. If you're monitoring something, use a rigid ruler, press into the pubic bone to account for fat pad variation, and measure stretched length rather than flaccid. The average erect length from that same study was about 13.12 cm (5.16 inches). The average flaccid length was about 9.16 cm (3.61 inches). Those are averages. The distribution is wide. Most variation is normal.
What Most Guides Won't Tell You
The most common urological complaint in men under 50 isn't cancer. It's not even erectile dysfunction. It's premature ejaculation and performance anxiety. These aren't purely psychological. They have physiological components involving serotonin receptors and penile sensitivity. The first-line treatment is usually behavioral, not pharmacological. SSRIs are used off-label because they delay ejaculation as a side effect. That's not a hack. It's the mechanism, redirected. Another thing: circumcision status doesn't meaningfully affect sensitivity or function for most men. The foreskin has specialized nerve endings, yes, but studies comparing sexual function in circumcised and uncircumcised men show minimal difference in outcomes. It's a detail worth knowing because the cultural debate around it often obscures the actual medical evidence.
Final Practical Thoughts
Understanding male reproductive anatomy means understanding it as a system, not a collection of parts. The hormone axis, the vascular mechanisms, the neural pathways, and the structural components all interact. When something goes wrong, the problem is rarely isolated. That's why general practitioners sometimes miss things. They're looking at symptoms in isolation instead of the whole system. A urologist or a well-informed primary care doctor who thinks in systems tends to catch what others miss. If you're dealing with a specific concern, the best first step is a proper physical exam and basic labs. Not an internet search. The anatomy is straightforward. The pathology underneath it is where things get complicated.


