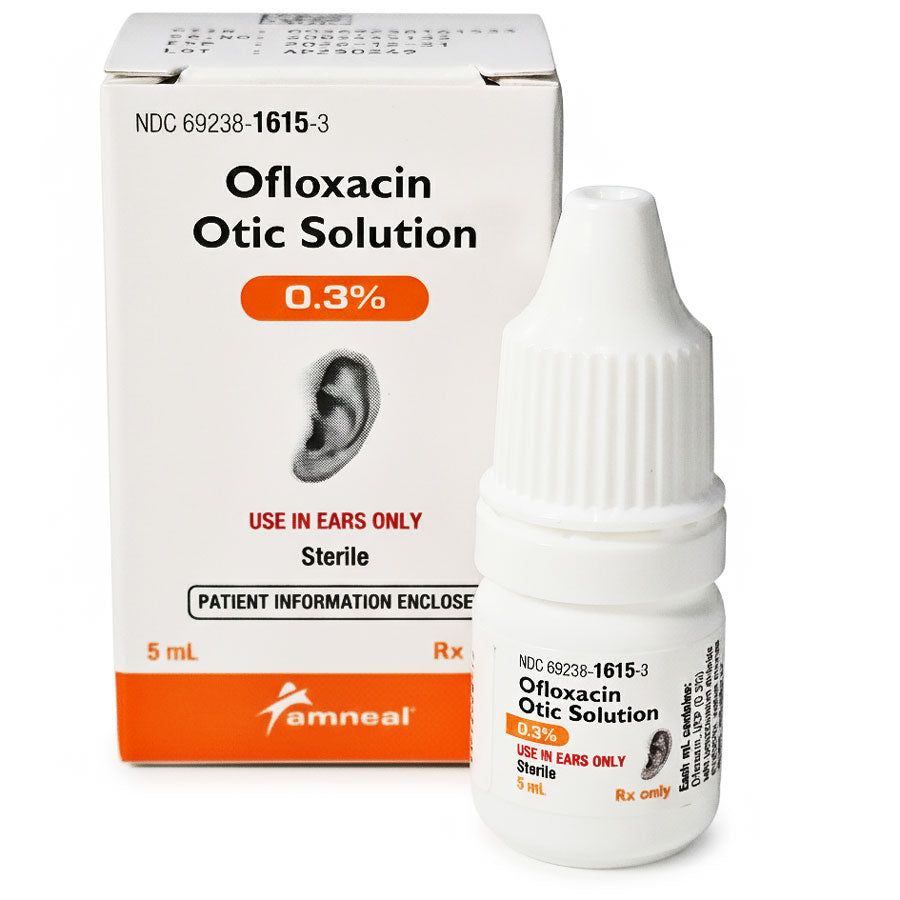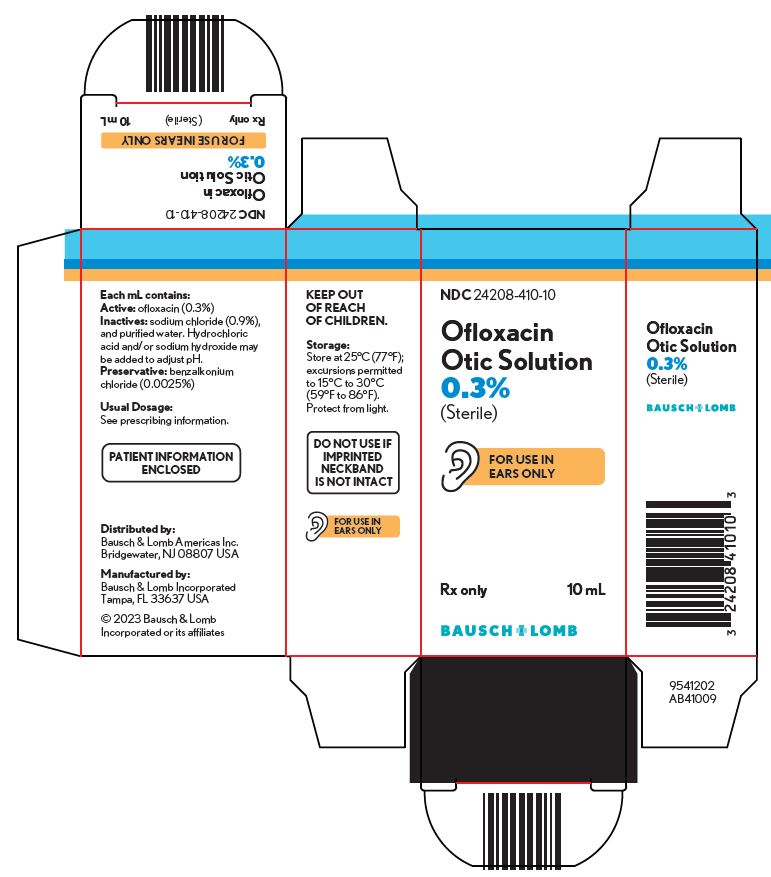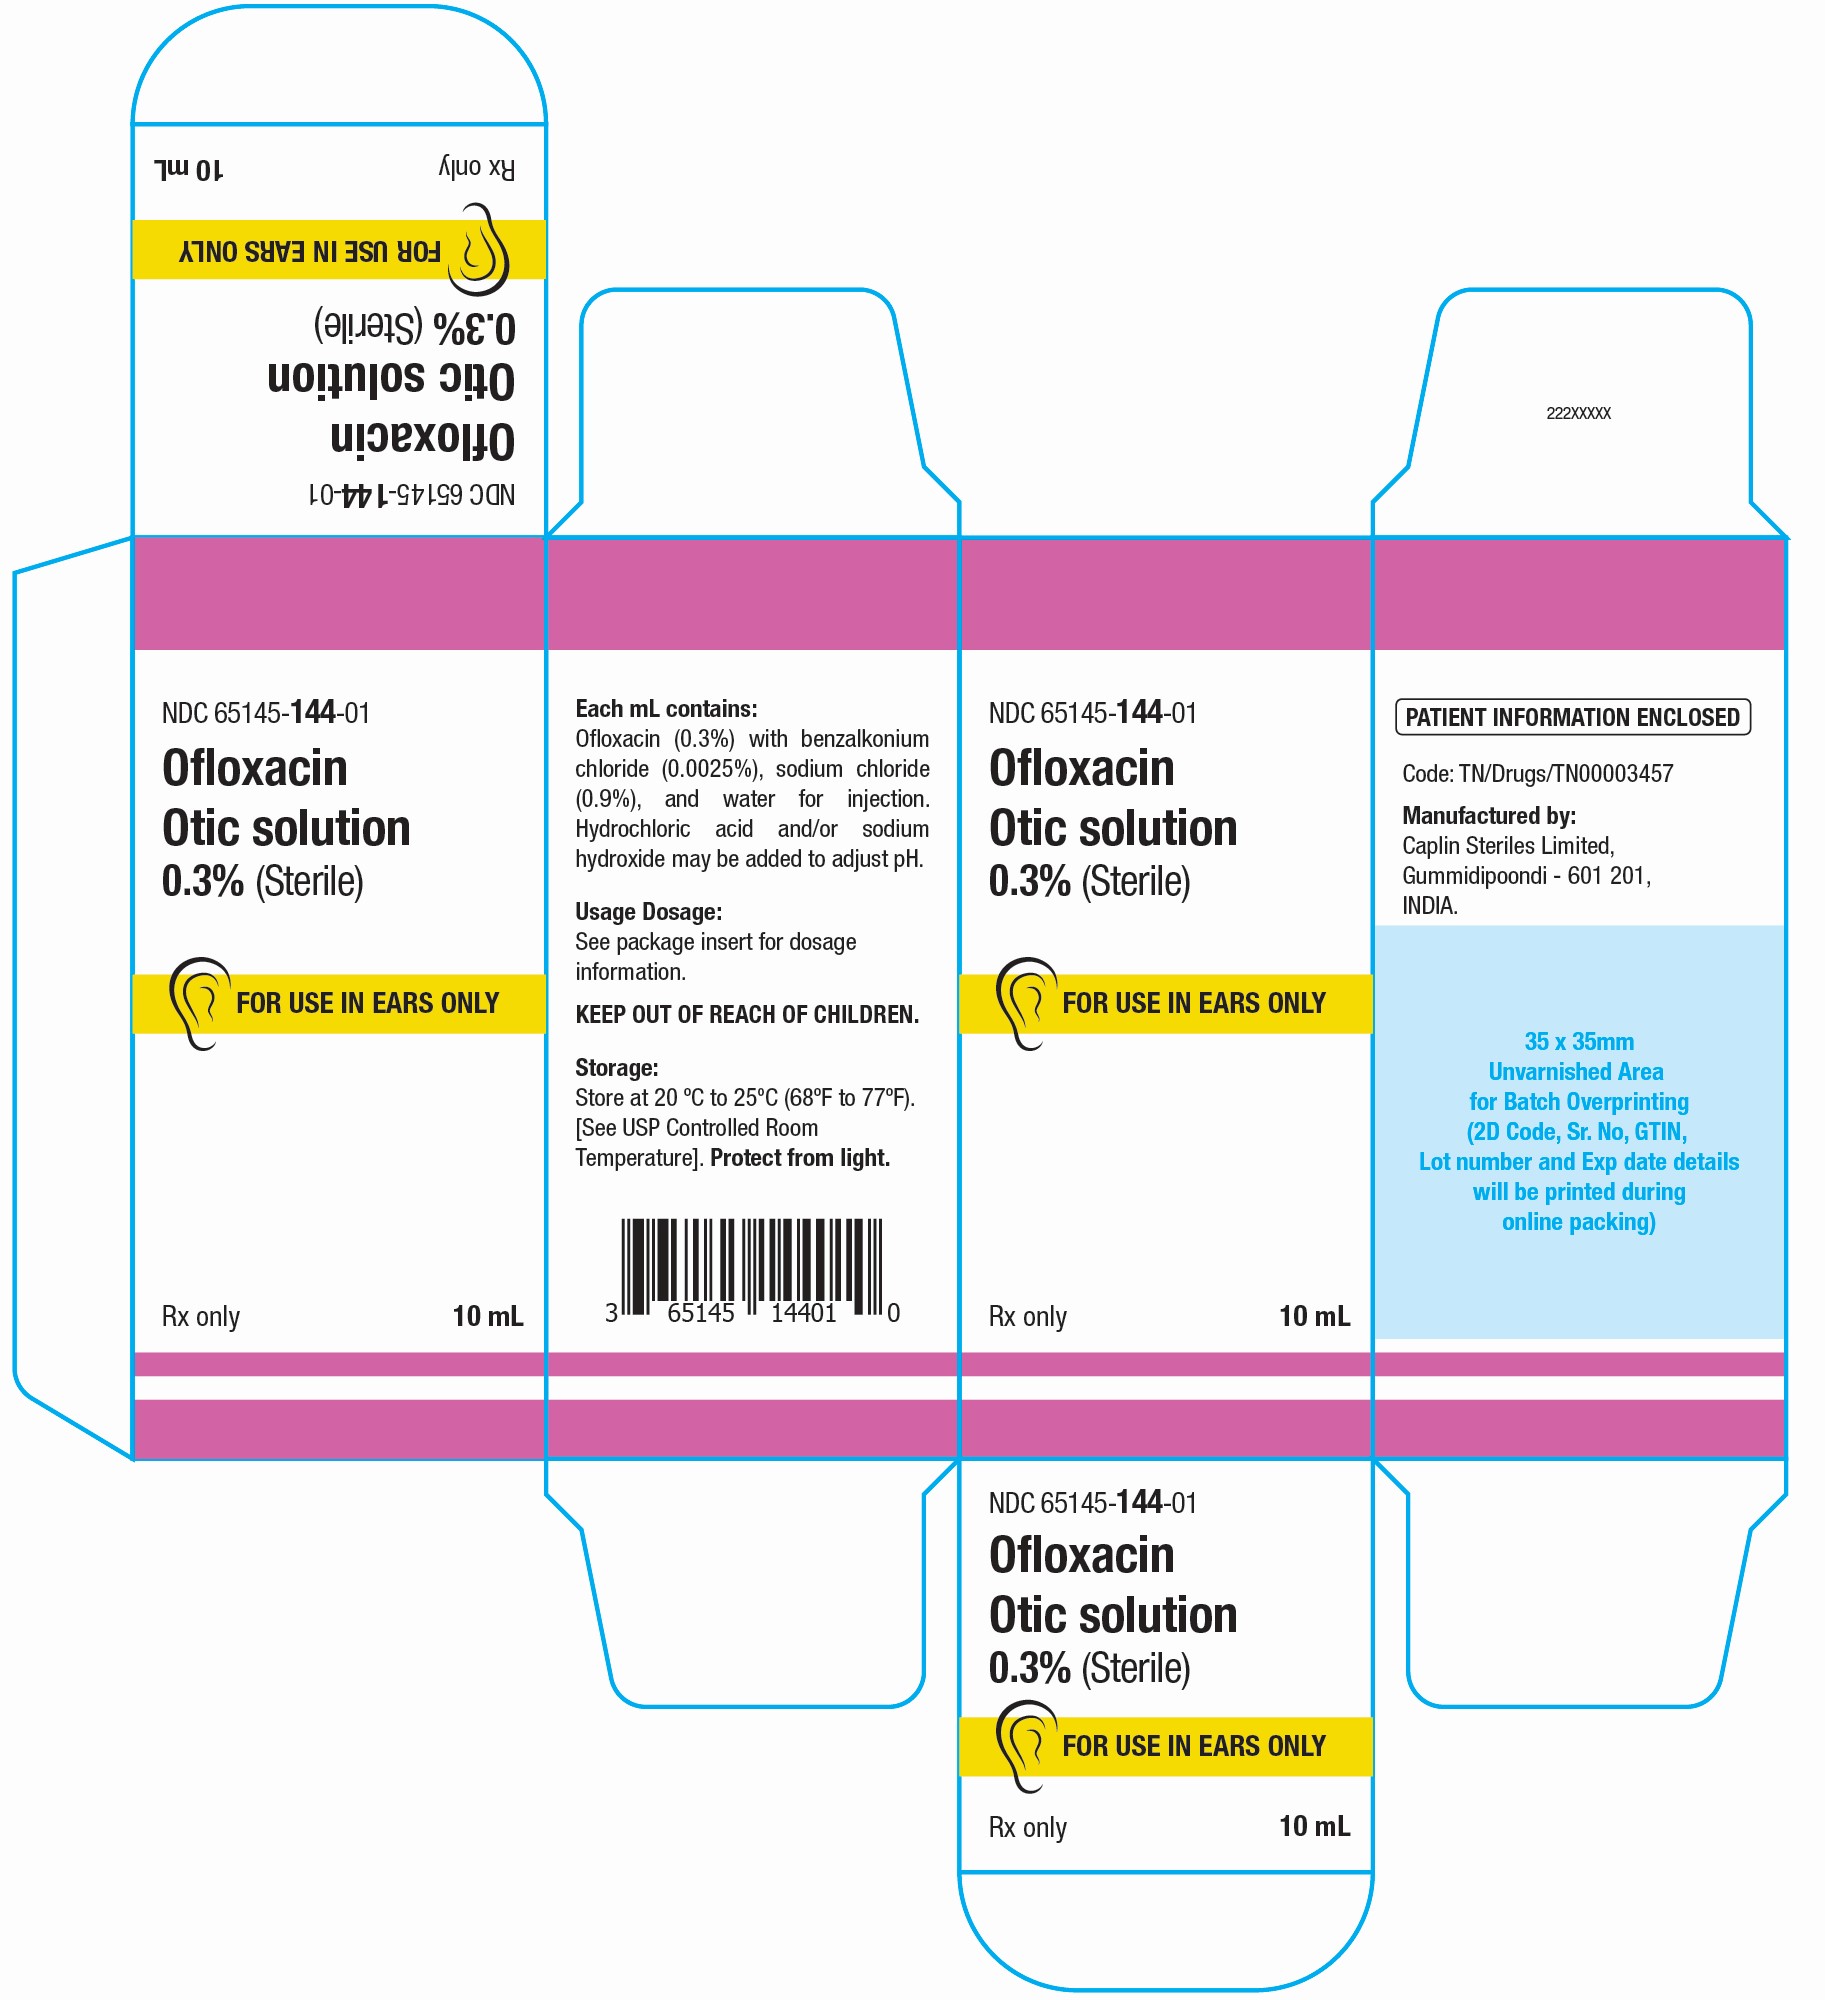
Setting up Ofloxacin Otic drops isn't hard, but the dosing gets messy fast if you don't know what you're looking at.
The standard adult dose for otic ofloxacin 0.3% is 10 drops into the affected ear once daily for 7 to 14 days depending on the infection type. For acute otitis media with tympanostomy tubes, it's also 10 drops once daily, typically for 10 days. Pediatric dosing follows the same volume — 10 drops, once daily — regardless of age or weight. There's no weight-based adjustment because the drug is delivered topically into the ear canal, not systemically. I've seen people overcomplicate this by trying to taper the drops or switch to twice-daily dosing thinking it'll work faster. It doesn't. The manufacturer label says once daily. The drug has a long enough residence time in the ear canal that splitting the dose doesn't improve outcomes and actually makes compliance worse. Patients forget the second dose and then complain it's not working.
Ofloxacin Otic Solution 03 Dosage
Here's the practical breakdown. For adults with otitis externa — that's the common "swimmer's ear" infection — instill 10 drops into the affected ear once a day for 10 days. For otitis media with PE tubes in patients 1 year and older, 10 drops once daily for 10 days. The key instruction that gets ignored: the patient needs to keep the ear tilted upward for about 60 seconds after instillation. If they don't, the medication runs right back out and they're basically paying for ear water. I had a patient last year who kept calling in frustrated because her ear pain wasn't improving after three days on ofloxacin otic. Turns out she was instilling the drops and immediately getting up to make coffee. The medication was draining out within 20 seconds. I told her to lie down, put a tissue in the ear canal just to catch the overflow, and stay there for a full minute. She came back two days later saying it was like a different drug. The formula hadn't changed, only the administration had. One thing nobody tells you about ofloxacin otic: the solution is slightly viscous and cold when it comes out of the refrigerator. Instilling cold drops into an infected ear canal causes immediate vertigo and discomfort. The workaround is simple — roll the bottle between your palms for 30 seconds before opening it. Don't microwave it. Don't leave it on a radiator. Just body temperature is fine and it prevents that spinning sensation that makes half my patients refuse to use the drops at all.
Another counter-intuitive point: you can use ofloxacin otic concurrently with topical steroid combinations if the prescribing information allows it, but do not mix them in the same application. Instill the ofloxacin, wait at least five minutes, then instill the steroid if ordered. The two solutions can interact physically in the canal and reduce efficacy. I learned this the hard way when a patient on combined therapy was still symptomatic and I initially blamed antibiotic resistance before realizing she was squirting both drops in back-to-back without any waiting period. There are real limitations to this approach. Ofloxacin otic solution 0.3% will not penetrate through an intact tympanic membrane in significant concentrations. If the eardrum is intact and the infection is middle-ear based, you're essentially treating the surface while the pathology sits deeper. In those cases, oral antibiotics may be more appropriate. The product is also contraindicated in patients with known hypersensitivity to fluoroquinolones — and I mean that broadly, including ciprofloxacin and levofloxacin due to class cross-reactivity. A patient who had a reaction to oral cipro won't necessarily test positive on skin prick, but the risk is real enough that I avoid it entirely in that population. The most common error I see in practice is dosing for chronic suppurative otitis media. The labeled indication is acute otitis externa and acute otitis media with tubes. Using it off-label for chronic conditions is something I've done when culture data supports it, but it's not FDA-approved for that and insurance often denies the claim. You end up doing a prior authorization that takes two weeks while the patient's ear continues to drain. In those situations, I sometimes pivot to ciprofloxacin-dexamethasone otic because it has a broader label coverage for chronic cases and the steroid component addresses the inflammatory component that ofloxacin alone doesn't touch.
Get the Full Details

Storage matters more than people think. Ofloxacin otic should be stored at controlled room temperature between 20 and 25 degrees Celsius. If it's kept in a hot bathroom cabinet in summer, the potency degrades faster than the expiration date suggests. I've had bottles that were six months past expiration still be clinically effective when stored properly, and bottles that were two months out that failed because they sat in a sauna environment. Don't store it in the shower caddy. The bottle itself contains 10 mL which is roughly 300 drops. At 10 drops per day, one bottle lasts 30 days. That's more than enough for a standard 10-day course, which means patients have leftover medication. They should discard any unused portion after the treatment course is complete. Not because the drug becomes toxic, but because once the bottle is opened, sterility of the solution can't be guaranteed indefinitely. A used bottle sitting in a medicine cabinet for three months is a contamination risk. If you need the prescribing information, it's available through the FDA's Orange Book database or directly from the manufacturer's site. But the actual label is dense and full of regulatory language that doesn't help with clinical decision-making. The short version is what I've outlined above — 10 drops once daily, keep the ear tilted for a minute, warm the bottle first, don't use it through an intact drum for middle ear infections, and switch to a steroid combination if you're dealing with chronic otorrhea and need broader coverage.