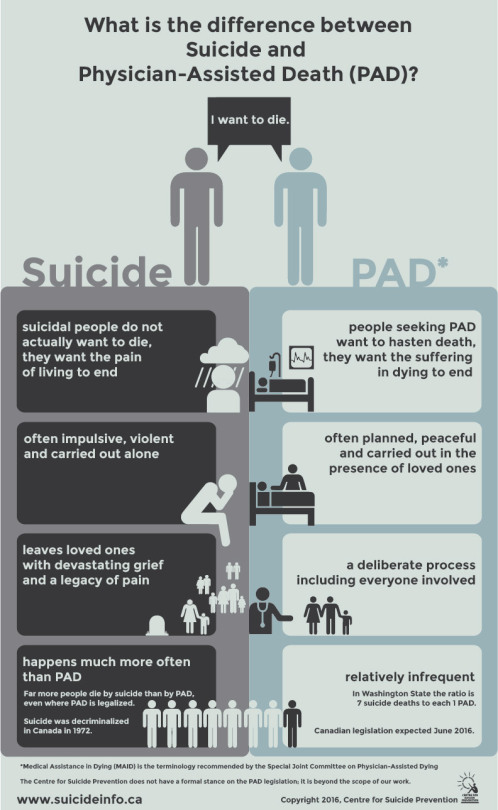
What It Actually Is
Medical aid in dying, often called assisted suicide or physician-assisted dying, is a legal medical process available in a small number of jurisdictions. The core mechanism is straightforward: a physician diagnoses a terminal illness, confirms the prognosis, and prescribes a life-ending medication. The patient then self-administers the medication voluntarily. The physician does not administer it. It sounds simple. It is not simple in practice. I worked with hospice and palliative care teams for years, and assisted dying requests came up more often than most people realize. Some were philosophical questions. Some were genuine practical needs. Most people get the legal framework wrong.
The Legal Reality
As of my last update, only a handful of places allow this process legally. In the United States, that means states like Oregon, Washington, Vermont, California, Colorado, Hawaii, New Jersey, Maine, New Mexico, and the District of Columbia. Canada has federal MAID (Medical Assistance in Dying) legislation. Some countries in Europe have similar laws. Everywhere else, it remains illegal and carries criminal penalties. The specific requirements vary by jurisdiction but typically include: - A formal diagnosis of a terminal illness with a limited life expectancy, usually six months or fewer
- The patient must be a resident of the jurisdiction
- The patient must be mentally competent and making the request voluntarily
- Multiple verbal requests are required, spaced apart by set time intervals
- A written request must be witnessed, often by two people who meet specific criteria
- Two physicians must evaluate and confirm eligibility independently
- A psychiatric or psychological evaluation may be required if there is any question about decision-making capacity
How It Works in Practice
The medication prescribed is almost always a barbiturate, typically a powder form of phenobarbital or secobarbital mixed into a liquid. The patient drinks it. Death usually follows within minutes to a few hours, depending on the dose and the patient's metabolic state. It is generally described as inducing unconsciousness followed by cardiac arrest. Not by coincidence, the patient is expected to be at home or in a hospice setting, not in a hospital. Here is the part nobody talks about enough: the process is designed to protect the system from abuse, not to accommodate the patient's convenience. The waiting periods, the multiple requests, the evaluations — these create a timeline that can stretch from days to weeks. For someone in active agony, that is a brutal detail. For someone whose suffering is existential rather than physical, it can feel like bureaucratic cruelty. Both experiences are valid and both are common. I once had a case where a patient's insurance denial for palliative sedation pushed him toward requesting MAID before his pain was properly managed. The physicians recognized the sequence and flagged it. We paused the process, arranged urgent palliative care consultation, and he ultimately did not proceed. The safeguard worked. Another time, a patient waited until the very last allowable window to request MAID because his initial pain management wasn't adequate, and by the time everything was sorted, he was too weak to self-administer the medication. That one stayed with me.
Get the Full Details

What the Data Actually Says
Oregon, which has been collecting data since 1998, publishes annual reports. The numbers are consistent. In any given year, roughly 150 to 200 people in Oregon receive a prescription. About 90 percent of them actually ingest the medication. The remaining 10 percent do not, for reasons including death before ingestion, change of heart, or inability to self-administer. The most commonly cited reason for choosing MAID is not uncontrolled pain. It is loss of autonomy and the inability to engage in activities that make life feel worth living. Loss of dignity. Dependence on others. This is important because it challenges the assumption that MAID is primarily a pain-management issue. It is usually about something broader and harder to solve with medication alone.
On Assisted Suicide: Common Misunderstandings
Misconception 1: It is used widely. It is not. In Oregon, it accounts for less than two percent of all deaths. The vast majority of terminally ill people do not request or use it. This matters because policy debates often treat it as a common practice or a slippery slope, when the data shows it is rare and narrowly used. Misconception 2: Palliative care and MAID are the same thing. They are not. Palliative care manages symptoms and quality of life. MAID intentionally ends life. Some jurisdictions explicitly separate them. Oregon law prohibits physicians from administering lethal medication, which creates a structural distinction even when both services come from the same clinic. Misconception 3: Once you request it, you cannot change your mind. You can withdraw at any point. The process is entirely voluntary. A significant minority of patients who begin the evaluation do not end up receiving a prescription. Some change their minds. Some become ineligible due to clinical changes. Some simply decide they do not want it after all.
The Practical Problems Nobody Discusses
The biggest operational headache I encountered was pharmacy access. Even in legal states, not all pharmacies will fill MAID prescriptions. Some will not dispense barbiturates at all due to internal policy. Some pharmacists object on moral grounds. Patients sometimes need to travel to a specific pharmacy or use a mail-order service. I dealt with one case where the prescribed medication had to be sourced through a compounding pharmacy in another state because no local pharmacy would touch it. The delay added a week to an already constrained timeline. Another issue is documentation. Physicians must maintain detailed records for annual reporting to the health department. This is not optional. It means chart notes, prescription logs, witness statements, and evaluation forms all have to be complete and consistent. Errors or gaps can trigger audits. For physicians, this adds administrative burden to an already emotionally complicated decision. There is also the question of who is eligible and who is not. Patients with psychiatric conditions as their primary diagnosis are generally excluded in U.S. states. In Canada, the law has expanded over time to include some non-terminal conditions, which has generated significant professional debate. The boundary between suffering that justifies MAID and suffering that requires psychiatric intervention is not clean. Clinicians have to navigate it case by case, and the answers are rarely satisfying.

What I Would Tell Someone Considering It
First, talk to your physician honestly. If they are not comfortable with the process, ask for a referral to someone who is. Not all doctors participate, and that is a legal right they hold. Second, understand that the process will test your patience. The safeguards are deliberate. They slow things down. Third, consider whether your suffering is primarily physical, psychological, or existential, because each type requires a different approach and not all of them are addressed equally by the current legal framework. Fourth, involve your family if you can. This is not a decision most people make alone, even when the law says it is solely theirs. The people who go through this process consistently describe it as peaceful. The medication works. But the journey to get there is often stressful, confusing, and emotionally exhausting. The outcome may be calm. The path is rarely easy.
Resources
For factual, jurisdiction-specific information, Death with Dignity (deathwithdignity.org) maintains current legal details for U.S. states. In Canada, the Canadian Mental Health Association and MAID resource guides provide updated information. If you or someone you know is experiencing suicidal thoughts that are not tied to a terminal illness, the 988 Suicide and Crisis Lifeline in the United States is available by calling or texting 988. This is a different pathway than MAID and serves a different purpose, but the distinction matters. The topic is legally narrow, medically complex, and personally weighty. It deserves honest discussion, not outrage or romanticization. Both extremes obscure what the data and the people involved actually show.



