What You Need to Know Before You Start
The One Stool Test is a diagnostic procedure used to check for gastrointestinal parasites, bacterial overgrowth, and sometimes certain pathogens that standard stool cultures miss. It is not a single test but rather a panel — typically looking at ova and parasites, PCR markers, and sometimes calprotectin depending on the lab. The instructions you receive will vary by laboratory, which is why getting the Spanish-language version matters for patients who are more comfortable in that language. I have seen too many people skip the test or submit a contaminated sample because the prep instructions were unclear or lost in translation. That wasted both their money and weeks of waiting. Once you understand the flow, it takes about five minutes to complete the actual collection part. The hard part is the prep, and honestly, some labs make that harder than it needs to be.
Where to Find One Stool Test Instructions In Spanish
Most major laboratory chains in the United States — LabCorp, Quest Diagnostics, and several regional labs — provide patient instructions in Spanish on their websites. You do not always need to ask for them. Look for a section labeled "Patient Instructions" or "Instrucciones para el Paciente" on the test ordering page. If you are through a physician's portal, they often attach a PDF directly. Some clinics just hand you a paper copy at check-in, which is fine if you can read it at that moment and don't lose it. If you cannot find them online, call the lab's patient services line. Ask for the "instrucciones del paciente en español" for the specific CPT code of your test. Getting the CPT number ahead of time saves about ten minutes of phone tag. The common codes for a stool O&P panel are 87046 and 87086. A GI PCR panel might be 87591. Keep those handy.
The Actual Collection Process
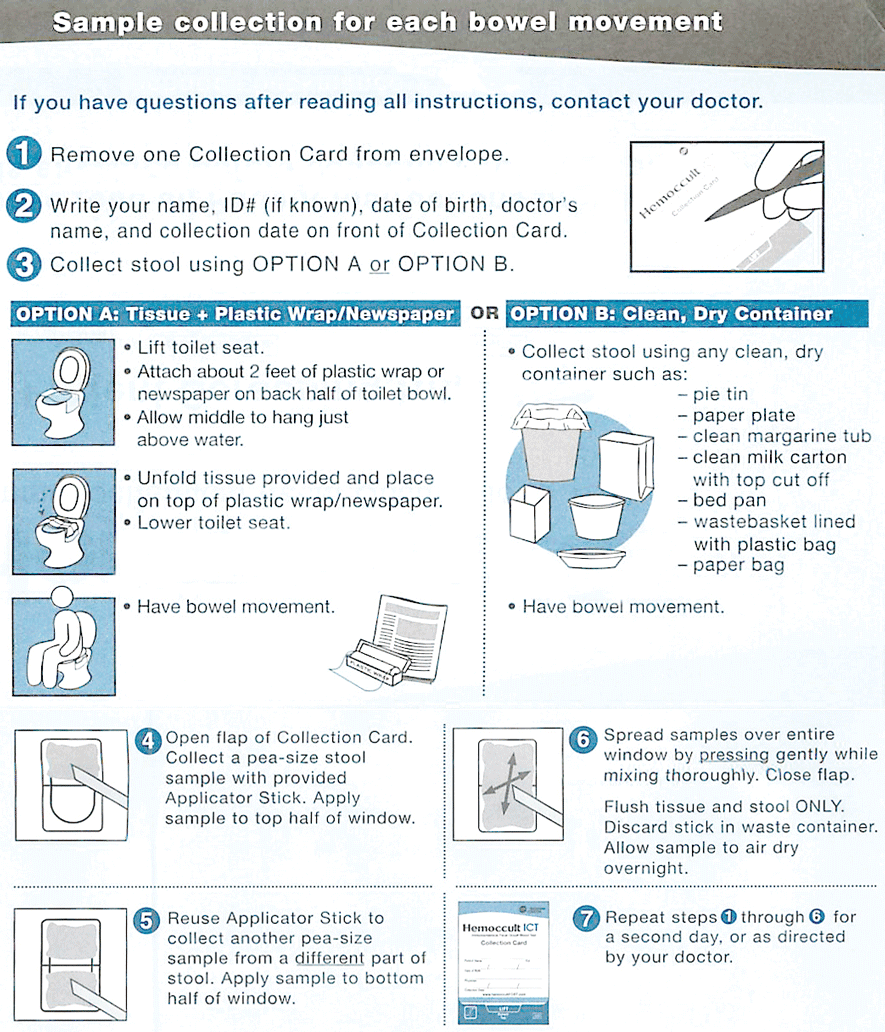
Here is how it works in practice. You will receive a kit that contains a collection container, a spatula or stick for transferring the sample, and a preservative vial if the lab requires one. Some labs use a small plastic bag instead of a vial. The difference matters for transport time. Step one is bowel movement into a clean, dry container. Do not collect from the toilet bowl. Water, toilet cleaner, and urine all ruin the sample. I had a patient once who used a plastic lid she placed in the bowl beforehand. The residue from the cleaning spray she used the day before killed most of the parasites in the specimen. The lab reported a false negative. She had to come back. We switched her to a clean hat container from the pharmacy — the kind you place over the toilet seat — and that solved the problem entirely. Step two is transferring the sample. You need about the size of a grape, or roughly one teaspoon. If the instructions say otherwise, follow those. Some PCR-based tests require less. More is not better here — excess sample can overflow the container and contaminate the outside, which delays processing.
Get the Full Details

Step three is sealing and labeling. Write the date and time on the container if the label does not already have a field for it. Temperature matters. Most labs want the sample at room temperature unless they provide a preservative. If you are driving to the lab and it is hot outside, keep the sample out of direct sunlight. A cooler bag without ice packs is sufficient for transport times under two hours.
Common Mistakes That Ruin the Test
The biggest issue I see is timing. Parasites and their eggs degrade quickly once outside the body. If you cannot get the sample to the lab within two hours, you need to use the preservative vial. The preservative stabilizes the organisms but it also prevents some motility-based detection. So there is a trade-off: fresh sample gives the lab the best chance to see moving organisms, but it has to be processed fast. Preserved sample is more forgiving on timing but loses some diagnostic sensitivity for certain species. Another mistake is contamination from menstruation or hemorrhoid bleeding. A small amount of blood is fine — in fact, it can be diagnostically useful. But heavy menstrual flow during collection can dilute the sample and introduce foreign material. I recommend noting on the requisition form if there was significant menstrual blood in the sample. The lab will interpret accordingly. Antibiotics and antiparasitic medications can cause false negatives. If the patient has taken antibiotics within the past two weeks, tell the ordering provider. They may need to adjust the interpretation or recommend a different testing window. This is not always obvious from the instructions alone, which is why having a conversation with the clinician matters more than just following the collection sheet.
What the Results Mean
A positive result for ova and parasites does not automatically mean treatment. Some organisms like Entamoeba histolytica require immediate medication. Others like Giardia lamblia usually do, but the clinical context matters. A few parasites found incidentally in an asymptomatic patient might not need intervention. The lab report will specify the organism and sometimes the quantity — slight, moderate, or heavy infection. That detail helps the provider decide on treatment urgency. Negative results are not always final. If symptoms persist after a negative test, repeating the test three times on consecutive days increases detection rates significantly. Some parasites are shed intermittently. One negative sample misses about 50 percent of infections. Three samples catch closer to 90 percent. This is something most patient instruction sheets do not mention clearly.

When the Test Does Not Work
The One Stool Test has real limitations. It does not detect all gastrointestinal pathogens. If someone has a viral infection, a bacterial infection that is not part of the O&P panel, or functional disorders like IBS, the stool test will come back normal. That is not a failure of the test — it is a mismatch between what the test looks for and what the patient actually has. In those cases, providers often move to fecal calprotectin, stool culture with extended panels, or breath testing for SIBO. The test also struggles with certain protozoa that do not shed eggs or cysts consistently. Blastocystis hominis, for example, is frequently reported as a contaminant or incidental finding even when it may be contributing to symptoms. The clinical significance is still debated, and the instructions will rarely address this nuance. If a patient keeps getting positive results for this organism and no treatment helps, it is worth discussing with the provider whether further evaluation is warranted. Cost is another factor. Without insurance, a stool O&P panel can run between seventy-five and two hundred dollars depending on the lab and location. Some telehealth platforms offer it for less, but the specimen handling standards may vary. If price is a concern, calling around or checking community health centers can bring the cost down considerably.