Optokinetic Stimulation in Vestibular and Neurological Rehabilitation
Optokinetic exercises use moving visual fields to drive nystagmus and train the vestibulo-ocular reflex. In physical therapy, they're most commonly prescribed for vestibular hypofunction, concussion-related visual dysfunction, and certain cervical contributors to dizziness. The equipment is straightforward — a strip of vertical stripes moving across a screen or a dedicated OKN drum — but getting the dosing right is where people fumble.The basic mechanism is simple enough. When you watch alternating black and white stripes scroll past you, your eyes naturally track one stripe and then snap back to the next. That tracking-saccadic pattern is optokinetic nystagmus. The brainstem circuits that generate it overlap heavily with the pathways that keep your vision stable during head movement. Strengthening those pathways is the whole point of the exercise. I generally start patients on a laptop or tablet running a free OKN video. YouTube has plenty of them — search for "optokinetic stimulation stripes" and pick one that's at least two minutes long. The stripes should move horizontally at a moderate speed. Too fast and the patient gets nauseated immediately. Too slow and you're not providing enough stimulus to the system. Here's the practical setup. The screen goes about arm's length away. The patient sits in a chair with back support and watches the stripes scroll from left to right for one minute, then right to left for one minute. That's one set. Most protocols call for two to three sets per session, once or twice daily. The whole thing takes maybe five to ten minutes.
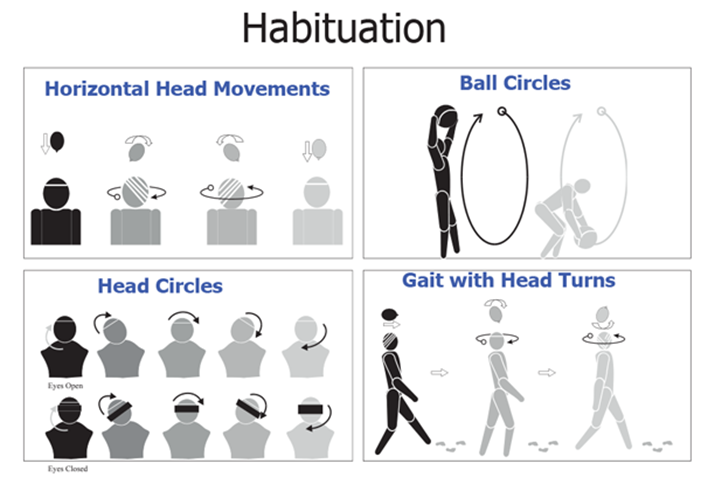
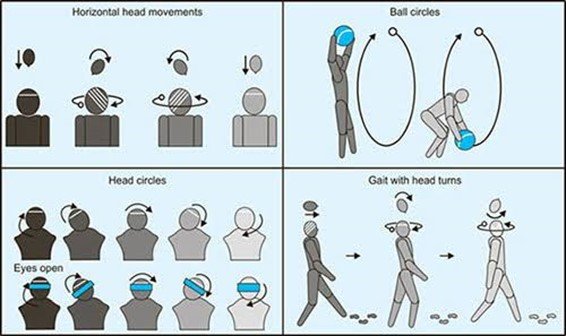
The progression isn't about making the stripes move faster. It's about adding head movement while the eyes stay locked on the display. Start with the head gently nodding up and down while watching, then progress to slow horizontal head turns. The harder part comes when you have them walk while looking at the screen, which sounds trivial until someone gets visibly unwell within thirty seconds. I've seen therapists skip the head movement progression entirely and just put the patient on a treadmill facing a screen. That's cutting straight to the hardest version and guaranteeing early dropout. The symptom response is too intense, the patient quits, and you haven't built the foundation. One detail most guides miss: the ambient lighting matters more than people realize. A bright room washes out the contrast on most consumer screens and effectively cuts the stimulus intensity by half without anyone noticing. Dim the lights or position the screen so no window light hits it directly. The stripes need to look sharp against the background for the reflex to engage properly.
I had a patient once — post-concussion, persistent oscillopsia, failed multiple times on standard VOR cancellation drills. We switched to optokinetic training with a high-contrast tablet running at reduced brightness in a darkened room. The first three sessions she couldn't complete a single minute without reporting severe nausea. The workaround was to halve the duration, do two thirty-second bouts instead, and gradually extend. By session seven she was tolerating full minutes. By session twelve the oscillopsia had dropped from a 7 out of 10 to a 3 out of 10 on her subjective scale. It wasn't dramatic, but it was real and it was the only visual training modality that moved the needle for her. Another counter-intuitive thing: frequency beats duration. Three short sessions a day produce better adaptation than one long session. The neural plasticity signal from OKN stimulation appears to decay within a few hours, so spacing matters. I structure my usual protocol as two sessions daily, morning and afternoon, with at least six hours between them. There are limitations worth stating plainly. Optokinetic exercises don't help everyone. Patients with central neurological lesions — stroke, MS plaques in the brainstem — may not benefit or could even worsen, because the issue isn't a peripheral vestibular deficit but a central processing problem. In those cases OKN drilling is basically useless and sometimes aggravating. Screen-based OKN also requires sufficient visual acuity. If a patient can't resolve the stripe edges clearly due to uncorrected refractive error or macular disease, the stimulus is compromised and you're wasting time.
Get the Full Details

The biggest practical bottleneck is compliance. These exercises are boring and the initial symptom provocation is unpleasant. Patients want something faster-acting. I've found that framing it as "five minutes, twice a day, you'll know in two weeks if it's working" keeps retention acceptable. Without that kind of expectation management, people stop after four days. For the actual videos, I don't charge for access. The same effect you get from expensive clinical OKN systems is available on any free video. Look for one with high-contrast stripes, horizontal movement direction, and a steady speed around 20 to 30 degrees per second of visual angle. Anything advertised as a "diagnostic" or "therapy" app with a subscription is usually just repackaged free content with a nicer interface. The evidence base is decent but not overwhelming. Systematic reviews show moderate-quality support for OKN in vestibular rehabilitation, particularly for gaze stabilization and symptom reduction in peripheral vestibular disorders. The effect sizes are modest — roughly in the 0.4 to 0.6 range — which means it's a useful tool in the toolbox but rarely a standalone cure. Combine it with VOR exercises, balance retraining, and graded aerobic exposure and you get something closer to what a full program should deliver.
If a patient presents with pure bilateral vestibular hypofunction and no central signs, optokinetic training is worth including from day one. If they have cervicogenic dizziness or a migraine component, the value drops considerably and you'd be better off prioritizing cervical manual therapy and migraine management first, adding OKN later if visual motion sensitivity persists.