Why This Stuff Matters When You're Actually Looking At It
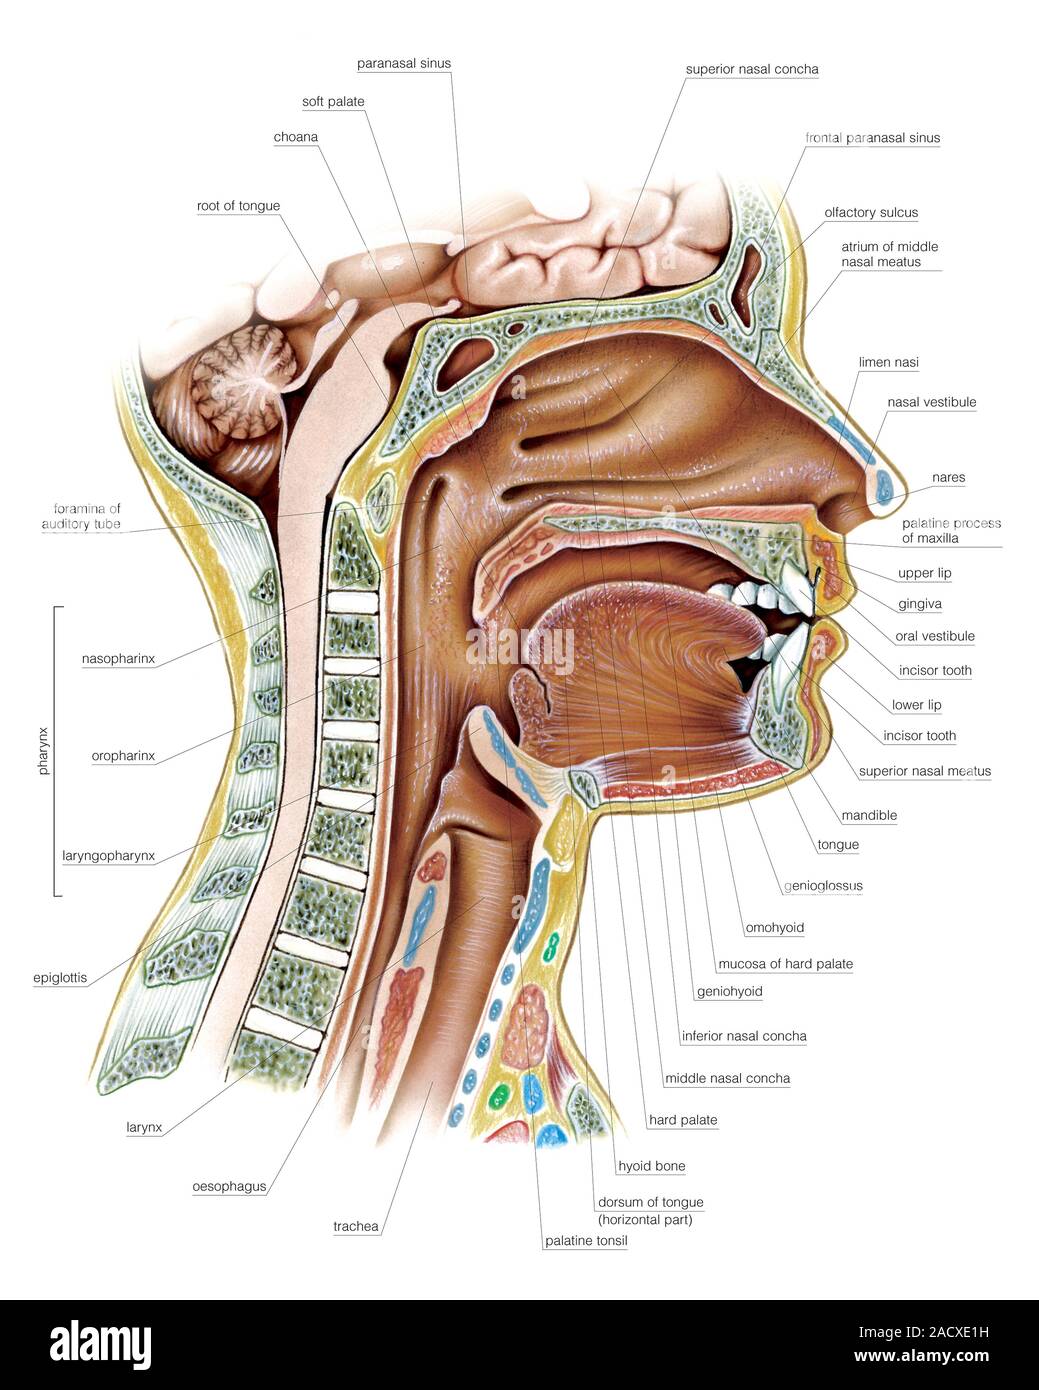
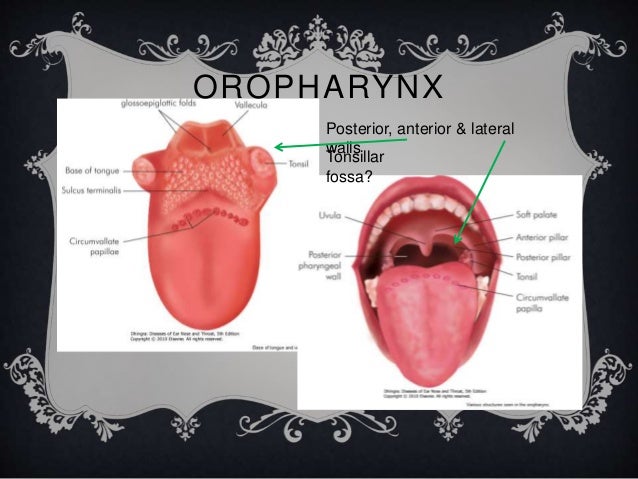
Most people learning this just memorize labels. It doesn't work that way when you need to actually use the knowledge. I spent a lot of time over the years going back through cadaver dissections and clinical cases where superficial understanding caused real problems. The oral cavity and pharynx are not separate topics - they connect in ways that matter clinically, and missing those connections is how you get things wrong.The oral cavity itself breaks down into three spaces: the oral vestibule, the proper oral cavity, and the oropharynx. Most textbooks separate them cleanly, but in practice you're never just looking at one. The vestibule sits between the lips/cheeks and the teeth. The proper oral cavity is inside the dental arches. The oropharynx begins at the palatoglossal arches and extends down to the epiglottis level. That's basic stuff, but here's what I've seen people miss: the boundary between the oral cavity proper and the oropharynx isn't a hard anatomical line you can trace on a diagram. It's functional. When a patient opens their mouth, those structures move relative to each other. If you're doing anything surgical or diagnostic that crosses that plane, you need to think about it as a dynamic space, not a fixed one.
Oral Cavity And Pharynx Anatomy: What Actually Comes Up in Practice
Let me tell you about a case that stuck with me. A patient came in with dysphagia, and the initial imaging was read as normal. The problem was a small submucosal lesion in the posterior pharyngeal wall, right at the level where the nasopharynx transitions into the oropharynx. On standard CT, it was nearly invisible. It took a dedicated MRI with contrast and someone who actually knew where to look to find it. This happens more often than you'd think. The pharynx has a lot of overlapping tissue planes, and small lesions hide in the spaces between them. The walls of the pharynx are made up of three constrictor muscles - superior, middle, and inferior. They overlap like shingles on a roof, which is intentional. That overlapping design creates a seal during swallowing. But here's the thing most people don't tell you: the gap between the superior and middle constrictors is a natural weak point. It's called Killian's triangle, and it's where pharyngeal diverticula form. If you're evaluating someone with regurgitation of undigested food hours after eating, this is the first place you should be thinking about. The lingual tonsil at the base of the tongue is another area that gets misunderstood. It's not just "tonsil tissue." It has a different lymphoid organization than the palatine tonsils, and it drains through different pathways. Infections here don't present the same way. I had a patient with a lingual tonsil abscess that was initially misdiagnosed as a peritonsillar abscess because the swelling pattern was similar. The treatment approach would have been completely wrong. The key difference is that lingual tonsil pathology often causes referred otalgia through the glossopharyngeal nerve, while peritonsillar issues tend to cause trismus. Moving down to the laryngopharynx, the mucosa here is continuous with the esophagus posteriorly and the larynx anteriorly. That continuity matters for understanding how pathologies spread. A squamous cell carcinoma in the hypopharynx can invade the cricoid cartilage or track upward into the postcricoid region. The blood supply comes from branches of the superior and inferior thyroid arteries, which also explains why these tumors metastasize to the upper cervical lymph nodes early. The innervation deserves a proper look because this is where exams consistently trip people up. The pharynx gets sensory input from the pharyngeal plexus, which is formed by contributions from the glossopharyngeal nerve (CN IX) and the vagus nerve (CN X). But the branchiopharyngeal branch of CN IX handles most of the sensation, while CN X takes care of motor function to the pharyngeal constrictors except for the stylopharyngeus, which is CN IX. If you're testing the gag reflex and someone doesn't respond, you need to figure out whether it's a sensory issue (CN IX) or a motor issue (CN X). The difference changes your entire differential diagnosis.The lymphatic drainage is equally important and equally confusing. The oral cavity drains to the submandibular and submental nodes for the front two-thirds of the tongue and the lower lip. The posterior one-third of the tongue and the oropharynx drain to the jugulodigastric node, which is just deep to the posterior belly of the digastric muscle. That node is palpable in many people and enlarged it's a significant finding. Beyond that, everything drains to the deep cervical chain. The reason this matters is that metastatic patterns follow these pathways predictably, and knowing where to look for spread saves time during staging.
I want to be straightforward about limitations here. Imaging can miss early lesions in the pharynx, especially in the piriform sinuses and the postcricoid region. Direct visualization with a flexible scope is often necessary even when CT or MRI looks clear. There's no substitute for looking directly. Conversely, direct visualization has its own limitations - superficial lesions can look deceptively benign, and biopsy sampling error is real. A negative biopsy doesn't rule out pathology if the clinical suspicion is high. Another practical issue is that anatomical variation is more common in this region than people admit. The palatoglossal arch can sit at different heights. The position of the larynx varies with age and body habitus. In elderly patients, the larynx sits higher and the pharynx is longer, which changes how you approach intubation or surgical access. I've seen practitioners use the same technique on every patient regardless of anatomy, and it shows. When you're studying this, stop drawing isolated diagrams and start thinking about what happens when these structures work together. Swallowing involves coordinated contraction of at least twelve muscles across three anatomical regions. Breathing involves maintaining patency of the pharyngeal airway against negative pressure. Speaking requires fine-tuned adjustments of the velopharyngeal port. These aren't separate functions - they share the same anatomical real estate and the same neural pathways. If you understand one system well, the others become much easier to learn.