Why You Need This and What It Actually Looks Like in Practice
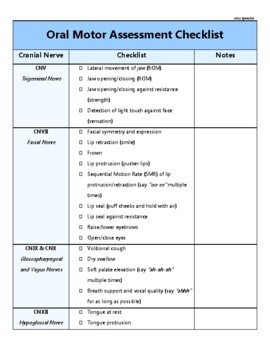
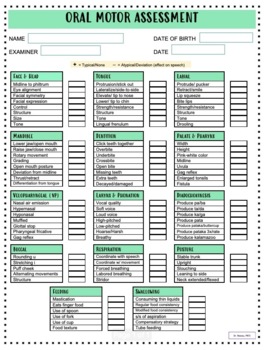
I stopped doing blind referrals for feeding disorders about four years ago after watching three kids get misclassified because nobody checked the oral motor baseline properly. The Oral Motor Exam Checklist is basically a structured way to document what you can see and measure when you look at someone's mouth, lips, tongue, and jaw movement before jumping into swallow or speech assessments. It saves you from that scenario. The checklist covers rest posture, range of motion, strength, coordination, and sensory response. Most versions I've seen break it down into about 30 items. That's fine on paper. In practice, you're looking at something that takes 8 to 12 minutes per patient if you move efficiently, longer if they're not cooperative.
How to Use the Oral Motor Exam Checklist
Start with observation before you touch anything. Watch the face at rest. Note mouth opening, lip seal, any asymmetry, drooling, or bruxism. Then move to passive range of motion — jaw depression, lateral movements, lip retraction. Use a tongue depressor and your gloved finger for this. Then active movement. Ask them to protrude, elevate, lateralize the tongue. Check lip closure against resistance. Test the gag reflex lightly if relevant. Document everything. I keep a small notebook in the room and scribble the raw scores during the exam so I'm not relying on memory afterward. The checklist becomes a scoring sheet at that point. Rate each item on a standard scale — usually 0 to 2 or 0 to 3 depending on your system. Add comments for notable findings like reduced lingual elevation on the left side or delayed pharyngeal trigger. One thing most people skip and shouldn't: pre-feed oral sensory screening. Tap the lips, stroke the buccal area, place a cold mirror under the nose. I had a kid who failed every swallowing task until I realized he had a hyposensitive orofacial profile. He needed desensitization work before we even talked about bolus management. Without that step in the checklist process, I would've wasted two sessions chasing the wrong problem.
Another pitfall I've seen repeatedly: people treating tongue thrust as the primary diagnosis when it's actually a compensatory strategy for weak anterior tongue elevation due to cranial nerve involvement or structural anomaly. The checklist will show you if the thrust is voluntary or reflexive depending on how you score the items. That distinction changes the entire treatment plan.
Get the Full Details

Where the Checklist Falls Apart
It doesn't work well for patients who are intubated, sedated, or have significant cognitive impairment that prevents following commands. In those cases, you're relying almost entirely on passive observation and the checklist becomes more of a documentation framework than a scoring tool. I supplement with video recording in those situations so I can review subtle movements I might miss in real time. The scoring itself is subjective. Two clinicians looking at the same patient can assign different ratings on tongue strength and coordination items. If you need reliability, use video and have a second rater score independently. It adds about 20 minutes to the process but the inter-rater agreement jumps significantly. I keep a downloadable version of the checklist I use at the bottom of this post. It's the one I printed out and laminated back in 2019 and have been modifying since. The core structure hasn't changed much.