How to Actually Use Oral Motor Exercises For Infants Without Freaking Them Out
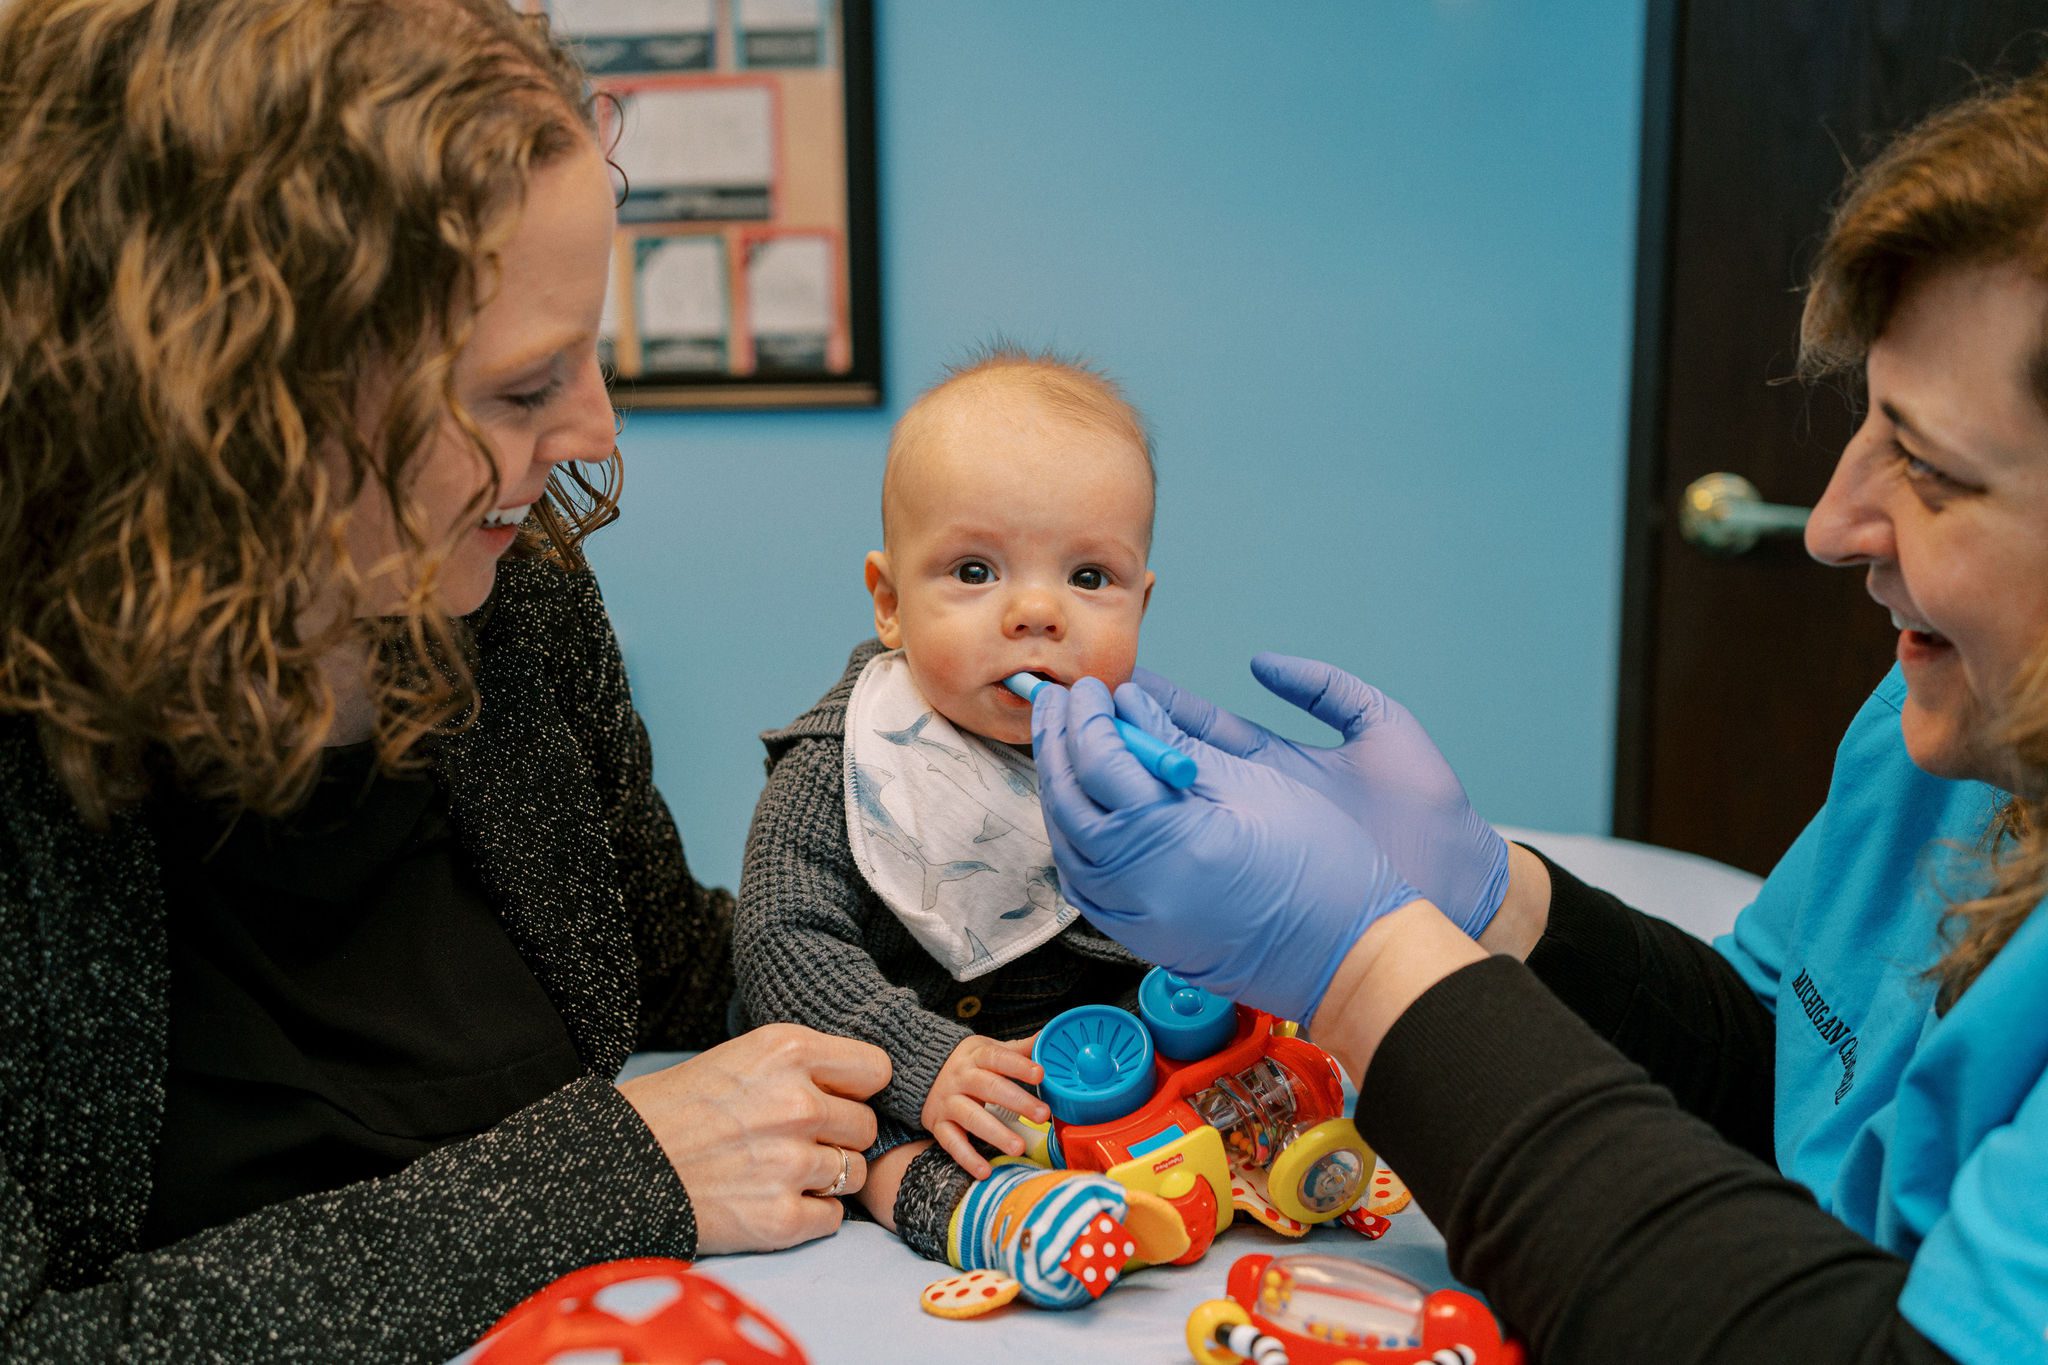
My first year dealing with infant oral motor issues, I watched a parent spend forty-five minutes trying to stimulate their baby's gag reflex with a cold spoon. The kid ended up in respiratory distress and we were sending them to the ER. That was one of those moments that changes how you approach this work. Oral Motor Exercises For Infants isn't about force or duration. It's about finding the threshold where stimulation helps without triggering a negative reflex response. What these exercises are supposed to do The premise is straightforward. Babies who have low oral tone, sensory processing issues, or neurological differences often struggle with feeding. Swallowing, sucking, and maintaining an open mouth require coordinated muscle activity. When that coordination is weak or delayed, oral motor exercises provide targeted stimulation to build that neuromuscular pathway. Think of it as physical therapy for the mouth, but adapted for infants who can't exactly sit through a session on a mat.
The tools are simple. A silicone toothbrush, a vibrating toothbrush meant for babies, gauze wrapped around a finger, or specialized oral stimulators if you have access to them. The technique involves applying firm but gentle pressure to specific areas of the mouth in a systematic pattern.
Oral Motor Exercises For Infants: The Basic Sequence
Here's what a typical session looks like in practice. The baby needs to be in a relatively calm state. Not full, not starving, not exhausted. I always tell parents the sweet spot is somewhere between feedings when the infant is alert but not overstimulated. Most babies will tolerate maybe three to five minutes of this before their frustration spikes past a useful point. Start at the lips. Use a circular motion with whatever tool you're working with. Move the tool around the outer lip ring for about ten seconds. Then move to the inner lip area, still using gentle circles. Next, move to the cheeks. Apply firmer pressure here than you would on the lips. The cheek tissue is more robust and can handle a bit more stimulation. Work from the outside of the cheek inward toward the mouth. The tongue gets more complicated. Place the tool on the center of the tongue and apply downward pressure. Hold for a couple seconds. Then drag from front to back. This is where you need to watch the baby's response closely. If you see gagging starting, stop immediately. Back off to a lighter touch or switch to the lips for a few seconds before trying again. The back of the tongue is extremely sensitive in most infants.
Get the Full Details

After the tongue, do the gums. Up and down, then side to side. Firm pressure here. The gums don't have the same gag reflex vulnerability, so you can be more aggressive with the stimulation. End by returning to the lips with light pressure. Closing the session with a gentler area gives the nervous system something less threatening to register last. A complete session typically takes four to six minutes. Most parents I work with are doing something closer to two minutes because they stop too early, or fifteen minutes because they don't know when to quit. Both extremes are wrong.
What Nobody Tells You About Doing This at Home
The first counter-intuitive thing is that consistency matters far more than intensity. A lightly done session every day beats a hard session twice a week. The neural pathways involved in oral motor function are built through repetition, not through brute force. I've seen parents push hard because they felt guilty about skipping days, and the results went backward. The infant develops a negative association with mouth stimulation and becomes more resistant over time. It's counterproductive in a measurable way. The second thing people miss is that oral motor exercises should never be done right before a feeding. At least not for most babies. Stimulation changes the oral landscape. Saliva production increases, the tongue position shifts, and the sensory receptors in the mouth become temporarily hyperactive. If you do the exercises and immediately try to feed, the baby may refuse the breast or bottle because the sensation feels strange or overwhelming. I recommend waiting at least twenty minutes after a session before offering food. In some cases, especially with sensory-sensitive infants, waiting thirty to forty-five minutes is necessary. I ran into a specific edge case last winter that made me rethink how I approach this entirely. A mother came in with her eight-month-old who had been on a puree diet exclusively due to oral motor delays. The kid had zero gag reflex response to almost anything, which is actually more concerning than having an overactive gag reflex. Most protocols assume you're working with an infant who needs to activate a dormant reflex. This baby's reflex was essentially absent.
The workaround was to incorporate food texture gradually during the exercises themselves rather than keeping them separate. I had her use a tiny amount of infant cereal mixed with breast milk on the oral stimulator. Instead of stimulating an empty mouth, we were stimulating a mouth with a trace of familiar taste. The sensory input from the mild sweetness and the texture seemed to lower the threshold for gag reflex activation. After three weeks of doing this, the baby responded to a thin puree with a normal swallow pattern. It wasn't in any of the standard protocols, but it made clinical sense. The association between oral sensation and taste feedback may help wire the swallowing reflex in kids who aren't getting it through stimulation alone.

When Oral Motor Exercises Won't Help and What to Do Instead
These exercises are not a universal solution. If the infant has a structural issue like a tethered lingual frenulum, no amount of stimulation will fix the underlying problem. The range of motion is physically limited. I've seen parents do exercises religiously for months while the real issue was a tongue tie that needed a quick outpatient release procedure. Get a proper evaluation from a pediatric SLP or a pediatric dentist who specializes in oral ties before investing significant time in exercises alone. Similarly, if the infant has significant gastroesophageal reflux, oral motor work can sometimes make things worse. The stimulation increases saliva and the baby may swallow more air, which aggravates reflux symptoms. In those cases, managing the reflux takes priority. I usually tell parents to get the GI issue under control first and then reassess whether exercises are appropriate afterward. Another limitation is age. Most oral motor exercise protocols are designed for infants between four and twelve months. Below four months, the oral reflexes are still developing naturally and intervention can interfere with that process. Above twelve months, the infant may have already developed compensatory patterns that make standard exercises less effective. At that point, you're often working with a feeding therapist who can design a more individualized plan rather than following a general protocol.
The bottom line is that oral motor exercises are a tool, not a treatment plan. They work well for certain categories of infants and do nothing for others. The key is knowing which category your baby falls into before you start. If you're unsure, a single evaluation with a pediatric speech-language pathologist who has feeding specialization will save you months of guessing. Those evaluations typically run between one hundred and two hundred fifty dollars depending on your location and insurance coverage, and they cover everything from oral anatomy assessment to observed feeding trials. It's better to spend that money upfront than to waste six months on a protocol that wasn't designed for your child's specific issue. Frequency-wise, most infants benefit from two sessions per day, spaced at least three hours apart. Doing it once a day is acceptable if that's what the family can sustain consistently. The harm comes from inconsistency, not from doing it on a lighter schedule. An infant who gets exercises three times a week for a month will show less progress than one who gets them once a day for the same period, but both will likely show some improvement over time. Just don't expect dramatic changes in the first two weeks. Neuromuscular adaptation in infants operates on a different timeline than adult rehabilitation. Give it a minimum of six to eight weeks before judging whether the approach is working for your baby.