What actually happens when you try to build oral motor strength
Most people approaching oral motor strengthening exercises think it's about making bigger mouths or stronger cheeks. It isn't. The problem is almost always coordination first, strength second. You can have a perfectly healthy set of structures and still not be able to sequence the movements needed for clear speech or safe swallowing. I spent years watching people do lip blubbering exercises and never see functional carryover because the underlying sensory feedback loop was broken. The mouth doesn't know what position it's in.
Let me start with the actual mechanics. The oral cavity has three functional zones. The front zone handles articulation precision — lips and anterior tongue. The middle zone manages pressure equalization and bolus control — the tongue body and velum. The back zone is where the swallow reflex triggers. Most exercises people try only address the front zone. That's why they seem pointless.
The core principle is isometric resistance. You're not opening and closing quickly. You're holding against resistance and slowly releasing. A quick repetition doesn't build the neural pathways needed for sustained control. Here's the setup most guides skip.
Oral Motor Strengthening Exercises
Start with the straw exercise. Use a thickened liquid — nectar consistency, not thin water. Have the person sip through a standard drinking straw. The resistance of the narrow tube forces the tongue to flatten and seal, the lips to maintain a tight closure, and the cheeks to stay stable rather than collapse inward. Do four to six slow sips per set, two to three sets. That's it. The thickened liquid is the key. Thin liquid lets the person cheat by using negative pressure, creating a vacuum that pulls the liquid through without any actual tongue control. Thickened liquid removes that crutch entirely.
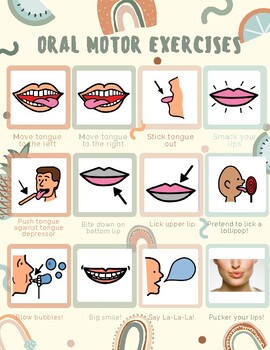
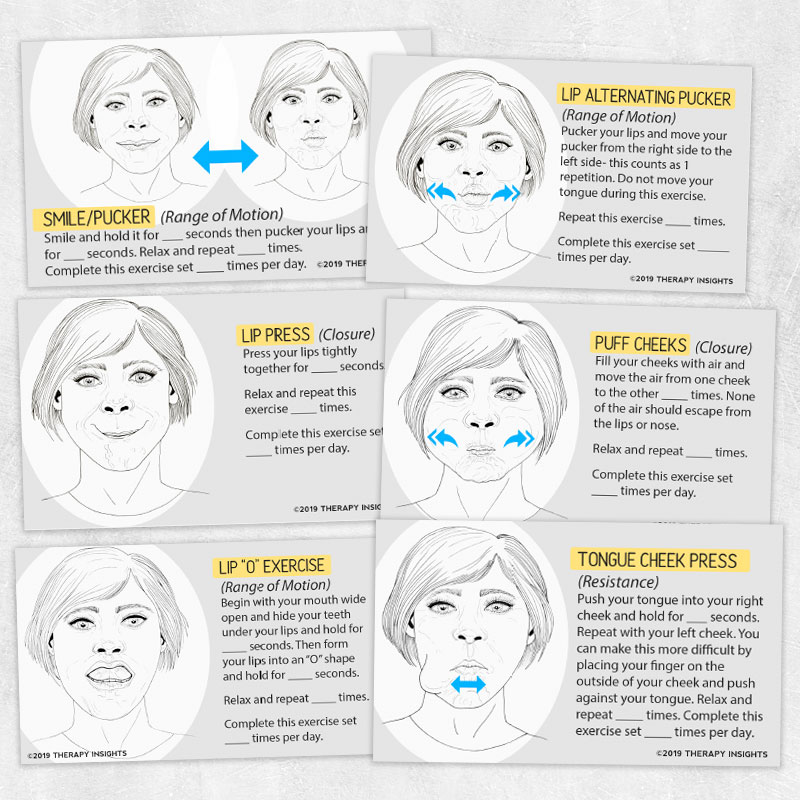
For tongue strength, use the tongue depressor technique. Place a wooden stick horizontally against the tip of the tongue. The person presses their tongue up and against it while you apply gentle downward resistance. Hold for five seconds. Release. Repeat eight times. Switch to lateral presses — tongue against the inside of each cheek while you push back with your finger on the outside of the cheek. Three reps per side. This builds the transverse and longitudinal tongue muscles that are critical for bolus manipulation during chewing and swallowing.
is often ignored but it's where most people fail. Have them puff air into their cheeks and hold it for ten seconds. Then slowly release through pursed lips. If the cheeks collapse immediately, the buccinator muscles are weak or poorly recruited. Work up to thirty-second holds over several weeks. Not days. Weeks.
Lip seal work comes next. Place a small soft object — a cotton roll or a specialized silicone disc — between the lips. The person maintains a sealed grip without using their teeth. Hold for ten seconds. Ten repetitions. This is deceptively hard. Most people who can't close their lips around a straw can't maintain this either. They'll try to bite down instead of using orbicularis oris contraction.
Jaw stability is the foundation everything else sits on. While chewing soft food like a banana or scrambled egg, the person keeps the jaw moving in a controlled vertical pattern without lateral deviation. Side-to-side grinding indicates temporalis and masseter imbalance. You want pure up-and-down with minimal horizontal drift. Twenty chew cycles per sitting.
Tongue elevation against the palate is probably the single most important exercise for swallowing safety. Press the entire tongue flat against the roof of the mouth — not just the tip, the whole surface — and hold for five seconds. Ten reps. This activates the suprahyoid muscles and prepares the swallow reflex properly. Most people with dysphagia never do this correctly because they press only the tip or they lift the back of the tongue without the anterior seal.
Here's the counter-intuitive part nobody mentions. The most effective oral motor strengthening exercises aren't the hardest ones. They're the ones that match the person's current baseline by about ten percent. If someone can barely hold a lip seal for two seconds, making them try thirty seconds will cause compensatory strategies — grimacing, head tilting, shoulder shrugging — that reinforce bad patterns. You build from the actual baseline, not the target.
I encountered a specific case that illustrates this perfectly. A client had severe oral apraxia after a stroke. Her tongue strength was adequate on paper but she couldn't sequence the movements for a safe swallow. I tried the standard tongue press protocol for two weeks and saw zero improvement. She'd press hard but the timing was wrong — the swallow triggered before the tongue even completed its elevation. The workaround was to add a tactile cue. I used a cold metal spoon against her tongue tip before each press. The thermal stimulus activated proprioceptive receptors and slowed her motor planning enough for the sequence to land correctly. After three weeks of that, the cold stimulus was no longer needed. The neural pathway had reorganized. Standard protocols never would have addressed the timing deficit because they only measure force, not sequence.
Sensory stimulation is another area people underweight. A cold mirror or an ice-cold cotton swab brushed along the anterior faucial pillars and the soft palate can activate sensory branches of the trigeminal and glossopharyngeal nerves. This primes the swallow reflex in people with hyposensitive pharyngeal responses. Do it for thirty seconds before feeding or exercise. Not after. The timing matters because you're trying to raise the threshold for trigger, not suppress it.
The biggest mistake I see is rushing the progression. People move from sip-through-a-straw to drinking from a cup within a week. The carryover doesn't exist. A study-level estimate: functional carryover from structured exercises to spontaneous use typically requires six to eight weeks of daily practice, thirty minutes per day, at the correct resistance level. Less than that and you're building strength that only exists in the exercise context.
There are also hard limitations. Oral motor strengthening exercises will not help if the underlying issue is structural — cleft palate, significant tongue tie with restricted movement, or neuromuscular disease like myasthenia gravis. In those cases, the tissue itself is the problem, not the motor control. Surgical or medical intervention needs to happen first. Similarly, if someone has pure sensory aphagia where they simply don't feel the bolus in their pharynx, strengthening the tongue won't restore the sensation. You'd need sensory retraining or electrical stimulation instead.
Another limitation most guides ignore is fatigue. The muscles involved in oral motor control are small and slow-twitch dominant. They fatigue differently than bicep curls. Doing twenty reps in one sitting is usually counterproductive because the last ten are done with poor form and reinforce the wrong patterns. Six to eight reps per exercise, with rest between, produces better outcomes than grinding through a high rep count. I usually cap sessions at forty-five minutes total because after that, the motor learning curve flattens significantly and errors accumulate.
For sequencing, start the session with the easiest task that still requires real effort. Lip seal. Then straw sips. Then tongue presses. Then palate elevation. End with the most complex integration task — which is usually sustained chewing with proper jaw alignment. The warm-up exercises prime the neural circuits without exhausting them, so the final task gets the best motor output.
The evidence base is mixed at best. A 2019 systematic review in
International Journal of Speech-Language Pathology found moderate evidence for tongue pressure exercises improving swallow safety in stroke survivors, but weak evidence for lip and cheek exercises improving articulation clarity. The takeaway isn't that these exercises don't work. It's that they work selectively and you need to match the exercise to the specific deficit. Blindly doing a full oral motor circuit rarely produces results across the board.
If you're designing a routine, assess first. Find out which specific movement is weak, not just which zone. A person might have strong lips but weak velar elevation. Or strong tongue propulsion but poor lip seal under load. The exercises then become targeted rather than generic. Track progress by measuring hold time and accuracy, not just whether the person completes the set. Five seconds of correct hold beats ten seconds of compensatory grimacing every time.