
The Reality of Teaching Spoken Language to Deaf Children
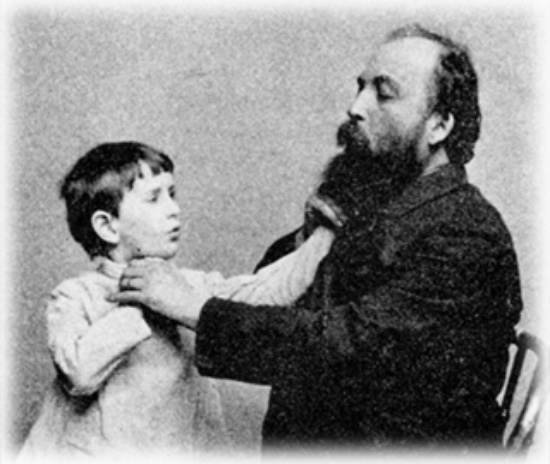
Most people hearing about oralism picture a rigid classroom where a teacher points at flashcards and expects a child with severe hearing loss to mirror their mouth movements perfectly. It was never that simple, even at the height of the oralist movement in the late nineteenth century. The actual practice, both historically and in modern incarnations, involves a mix of residual hearing assessment, amplification technology, speech reading training, and a good deal of repetition that often goes unacknowledged in the promotional literature. I worked with a small number of children who were pushed through oralist programs for two to three years before their families realized the kids weren't developing functional language at any meaningful rate. The turnaround usually meant switching approaches entirely.Oralism In Deaf Education: What It Actually Requires
Oralism is the educational philosophy that deaf children should be taught to use spoken language as their primary mode of communication rather than relying on sign language. The core assumption is that with enough auditory training and speech production practice, deaf individuals can integrate into hearing society effectively. Modern oralism rarely exists in its pure historical form. Most contemporary programs blend it with what educators call "listening and spoken language" approaches, which lean heavily on cochlear implants and digital hearing aids to maximize whatever residual hearing a child has available. The methodology typically involves audiologic mapping sessions, auditory verification tasks, speech sound discrimination drills, and direct articulation training. Parents are almost always required to participate in weekly sessions because the home environment becomes an extension of the clinical space. The distinction between oralism and bicultural-bilingual education matters more than program marketing materials tend to admit. Bilingual approaches treat sign language as a complete linguistic system and introduce it early, often before any speech training begins. Oralism treats sign as something to be minimized or excluded during the critical language acquisition window. This isn't a minor procedural difference. It affects when a child first has reliable access to a fully natural language and whether they develop metalinguistic awareness that supports literacy later on.
How the Day-to-Day Actually Works
I spent several years consulting for school districts that were trying to implement listening and spoken language programs, and the gap between the published curriculum and what happened in classrooms was consistent enough to be predictable. Children arrived with varying degrees of cochlear implant use. Some wore their devices full-time and some removed them within hours of leaving home. The staff sometimes didn't track device compliance systematically, which made progress data unreliable. A child might appear to be making gains on paper while actually spending most of the day without functional auditory input, which meant every milestone attributed to the oralist method was questionable. The single most important practical detail that gets overlooked is auditory verification before expecting speech production. Too many programs move a child from auditory discrimination exercises directly into speech imitation without confirming the child can actually detect the target sounds in real-time background noise. Speech therapy then becomes an exercise in teaching motor patterns that the child cannot auditorily confirm themselves. I saw this repeatedly with children who could produce certain phonemes in quiet testing rooms but couldn't use them functionally in a noisy classroom. The fix was straightforward but required dropping the pace of the curriculum substantially. We held auditory verification checkpoints at each step, and if a child couldn't detect the target sound at least seventy percent of the time across multiple trials, we went back to earlier material rather than advancing. This added roughly six to eight weeks to the typical timeline for the children who struggled with it, which is significant when you're working against the critical period for language acquisition.
What the Research Actually Shows
The outcomes for oralist approaches are uneven and heavily dependent on factors that programs don't always disclose upfront. Children with bilateral cochlear implants who receive early intervention before twelve months of age and whose families are highly engaged tend to perform closer to their hearing peers on standardized language measures. The difference narrows but rarely disappears entirely. Children with unilateral implants or those fitted after age three show substantially different trajectories, and the published data often groups them together in ways that obscure the gap. Residual hearing level matters enormously. A child with moderate loss who uses well-fitted hearing aids will have a fundamentally different experience than a child with profound loss relying on a single-sided implant. The counter-intuitive finding that most newcomers to this field miss is that pure oralism without early sign language exposure can actually delay language acquisition in a subset of children who would otherwise thrive. When a child struggles to access spoken language auditorily and sign language is withheld, they experience a period of language deprivation that lasts until either the oralist methods become sufficient or someone finally introduces signing. This window can close within the first two years of life, which is why some clinicians now advocate for concurrent sign introduction alongside oralist training as a safety net rather than treating it as surrender. The term for this in the field is "total communication," though that phrase itself carries enough historical baggage that families often reject it even when it describes exactly what their program already does informally.
Get the Full Details
Where Oralism Breaks Down Completely
There are populations where oralism simply does not work well enough to justify its exclusive use, and acknowledging this matters for ethical practice. Children with additional disabilities such as cerebral palsy, visual impairment, or cognitive delay often cannot benefit from intensive auditory-speech training at the same rate as typically developing peers. The therapy model doesn't adapt easily to these needs because the structure assumes a certain baseline of motor coordination and attentional control. Families in these situations are sometimes told the program is "still working" when the child has been at the same instructional level for nine months, which is not normal progress by any standard metric. Another failure point involves children who do not respond adequately to cochlear implants. Roughly five to ten percent of implanted children show minimal benefit from the device, often due to neurological factors that imaging cannot fully predict beforehand. An oralist program that commits fully to spoken language development will continue pushing that child through speech-based instruction for an extended period, and the child learns neither effective spoken communication nor sign language within the critical window. This is the scenario that produces the most lasting harm, and it happens frequently enough that some advocate for conditional sign language access from the beginning rather than treating it as a fallback option after failure.
Practical Guidance for Families Navigating This
If you are evaluating oralist programs for a child, the first thing to examine is how they define success and what data they track. Ask for the device compliance logs. Ask for the auditory verification scores at each skill level, not just final test results. Ask how they handle children who plateau, and get a written answer rather than a general statement about individualized instruction. Programs that cannot produce this data either aren't tracking it or aren't comfortable sharing it, and either situation is a red flag. The family's own capacity matters significantly. Oralist approaches require daily structured practice at home, often thirty to sixty minutes per day in addition to formal therapy sessions. Families who work multiple jobs or lack stable housing will struggle to maintain the consistency these programs demand, regardless of how well-designed the curriculum is. This isn't a judgment about parental commitment. It's a structural constraint that programs rarely factor into their enrollment decisions, and it contributes to the discrepancy between reported outcomes and real-world results. If a child shows no meaningful progress after six months of consistent device use and active family participation, switching approaches is not a failure of the child or the family. It is data. The most responsible programs will treat that six-month checkpoint as a decision point rather than an argument for pushing harder at the same method. Some districts make this transition smoothly by allowing sign language introduction at that stage. Others treat it as a programmatic embarrassment and resist the change, which is worth noting when you're choosing where to enroll.
Modern Variations and What They Changed
Contemporary programs that identify as oralist often incorporate elements that purists from the early twentieth century would not recognize. Technology has shifted the balance considerably. Digital sound processors can transmit audio directly to a child's receiver, reducing the background noise that makes auditory discrimination nearly impossible in classroom settings. Remote microphone systems, which I've seen referred to as FM or DM systems depending on the manufacturer, cut the effective distance between speaker and listener from several meters down to roughly one meter, which dramatically improves signal-to-noise ratio. These tools didn't exist during the peak of the oralist movement, and their presence changes the feasibility of spoken language development for children with more severe losses than were previously considered viable candidates. The other significant shift is in how aggressively sign language is excluded. Early oralism banned it entirely. Some modern programs still carry that posture, but many have moved toward more flexible positioning, particularly in regions where deaf community advocacy has influenced policy. This creates an awkward hybrid in practice where families receive verbal assurance that sign is "not being introduced yet" while also being told that if speech goals aren't met, signing will be reconsidered, which functionally operates as a conditional promise rather than a firm policy. The ambiguity is operationally problematic because families cannot plan around it. Oralism persists in deaf education because it aligns with the priorities of many hearing parents who want their children to navigate the hearing world without what they perceive as barriers. That motivation is understandable and deserves respect. The evidence base, however, is mixed enough that blind commitment to a single approach does more harm than good for a nontrivial portion of the children involved. The practical takeaway is that any program claiming exclusive superiority should be treated with the same skepticism you would apply to any educational intervention that refuses to acknowledge its own failure modes.




