Working With Orem When Patients Can Tended Themselves
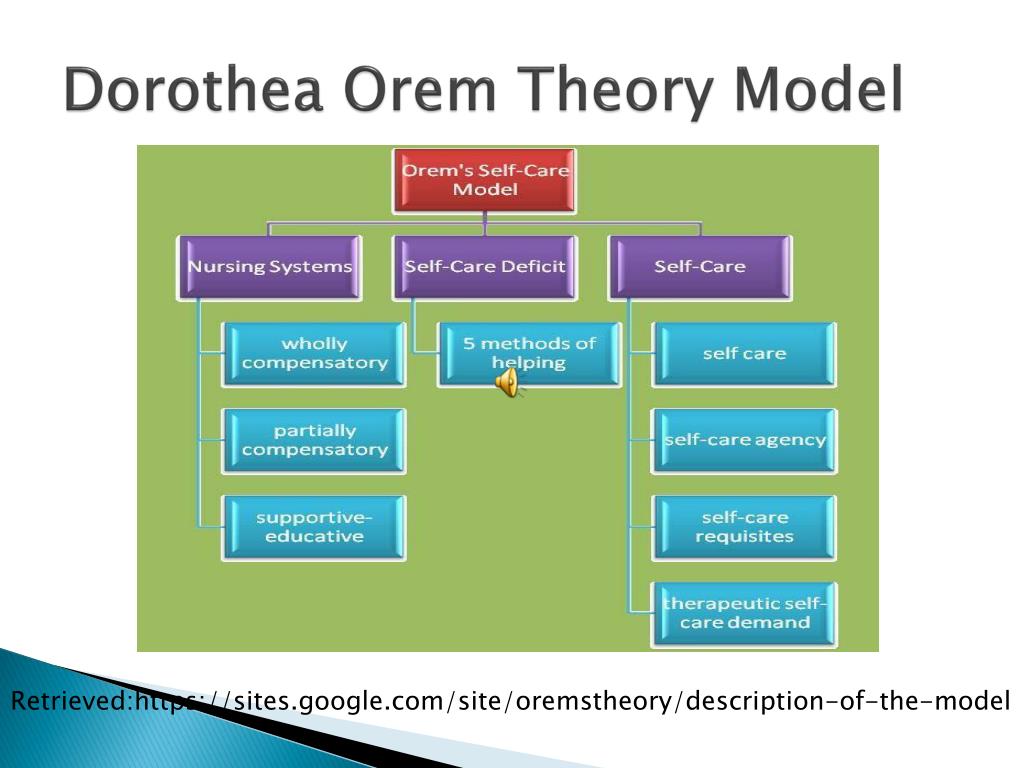
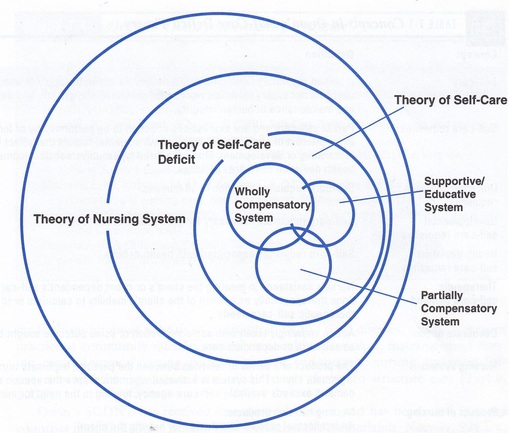
I spent three years on a med-surg floor before I ever really understood what Dorothea Orem was getting at. The theory sounds straightforward on paper — people have self-care needs, and when they can't meet those needs on their own, there's a deficit. But applying it in real practice is messier than most nursing textbooks let on. The core idea breaks down into three interrelated theories. The first is the self-care theory, which identifies what every human being needs to do to maintain life, health, and well-being. The second is the self-care deficit theory, which kicks in when someone cannot meet those needs. The third is the nursing systems theory, which describes how nurses should respond based on the level of deficit. The three nursing systems are wholly compensatory, where the nurse does everything for the patient; partly compensatory, where both nurse and patient contribute; and supportive-educative, where the patient can perform self-care but needs guidance and education to do so.
Here is where it gets practical. I once had a post-operative knee replacement patient who fell into the supportive-educative category on paper. She could walk with a walker, manage her medications, and dress herself. But she kept skipping her anticoagulant doses because she did not trust that blood thinners were necessary when she felt fine. The deficit was not physical — it was knowledge-based. Orem would call this a developmental self-care requisite. The workaround I used was having her review her own lab results from the previous admission, showing the elevated D-dimer that had prompted the prescription. Once she saw the actual numbers, compliance improved significantly. No lectures needed. Another thing nobody tells you about this theory is that the self-care Agency concept is easily miscalculated. Nurses tend to assess what a patient can physically do and assume that covers the whole picture. But Orem includes psychosocial dimensions in self-care agency too. A patient might be physically capable of changing a wound dressing but completely unwilling due to body image concerns after a mastectomy. That is still a deficit, and it requires a different intervention than a purely physical one. The common pitfall I see is applying the wholly compensatory system to patients who only need the supportive-educative approach. It happens all the time on busy shifts. A nurse will take over everything for an elderly patient who simply needs reminders and a clearer schedule. This creates learned helplessness, which Orem specifically warns against. The patient's self-care agency deteriorates because no one ever asks them to participate.
There is also a limitation worth noting. Orem's framework assumes a rational actor — someone who understands cause and effect between self-care behaviors and health outcomes. This breaks down with patients who have cognitive impairments, active substance use disorders, or severe depression. In those cases, the theory provides a useful scaffold for assessment but cannot drive the intervention on its own. I would pair it with Motivational Interviewing for behavioral barriers or a cognitive assessment tool when insight is questionable. When I use this theory now, I start by mapping the requisites. Orem divides them into three categories: universal self-care requisites (air, water, food, elimination, activity-rest balance, solitude-social interaction, hazard prevention, human functioning), developmental requisites tied to life stages and events, and deviant requisites arising from illness or medical conditions. Writing these out explicitly forces a more thorough assessment than a generic care plan would provide. The theory also helps communicate with the interprofessional team. Saying a patient has a partly compensatory need due to a self-care deficit is more specific than describing them as "non-compliant" or "struggling." It tells the dietitian, the physical therapist, and the social worker exactly where the gap is and who should fill it.
Get the Full Details

One edge case that trips people up: the theory does not give clear guidance on how to handle conflicting self-care demands within a single patient. A diabetic patient might need to follow a strict diet (universal requisite) while also managing insulin timing (developmental requisite tied to their condition). When these conflict — say, the patient values social eating over glycemic control — Orem's framework identifies the deficit but does not resolve the value judgment. That is where counseling and shared decision-making come in, not the theory itself. I have found the most reliable way to apply this is to document the assessment using Orem's actual terminology rather than translating it into modern nursing language. When a care plan says "patient lacks knowledge," it is vague. When it says "patient has a self-care deficit in the developmental requisite of chronic illness management, currently receiving supportive-educative nursing," the next nurse on shift knows exactly what system to continue and what the assessed gap is. The theory is not a substitute for clinical judgment. It is a structuring tool. Use it to make your assessments more complete and your care plans more precise, but do not expect it to tell you how to handle every situation. Some deficits are straightforward. Others require you to step outside the framework entirely.