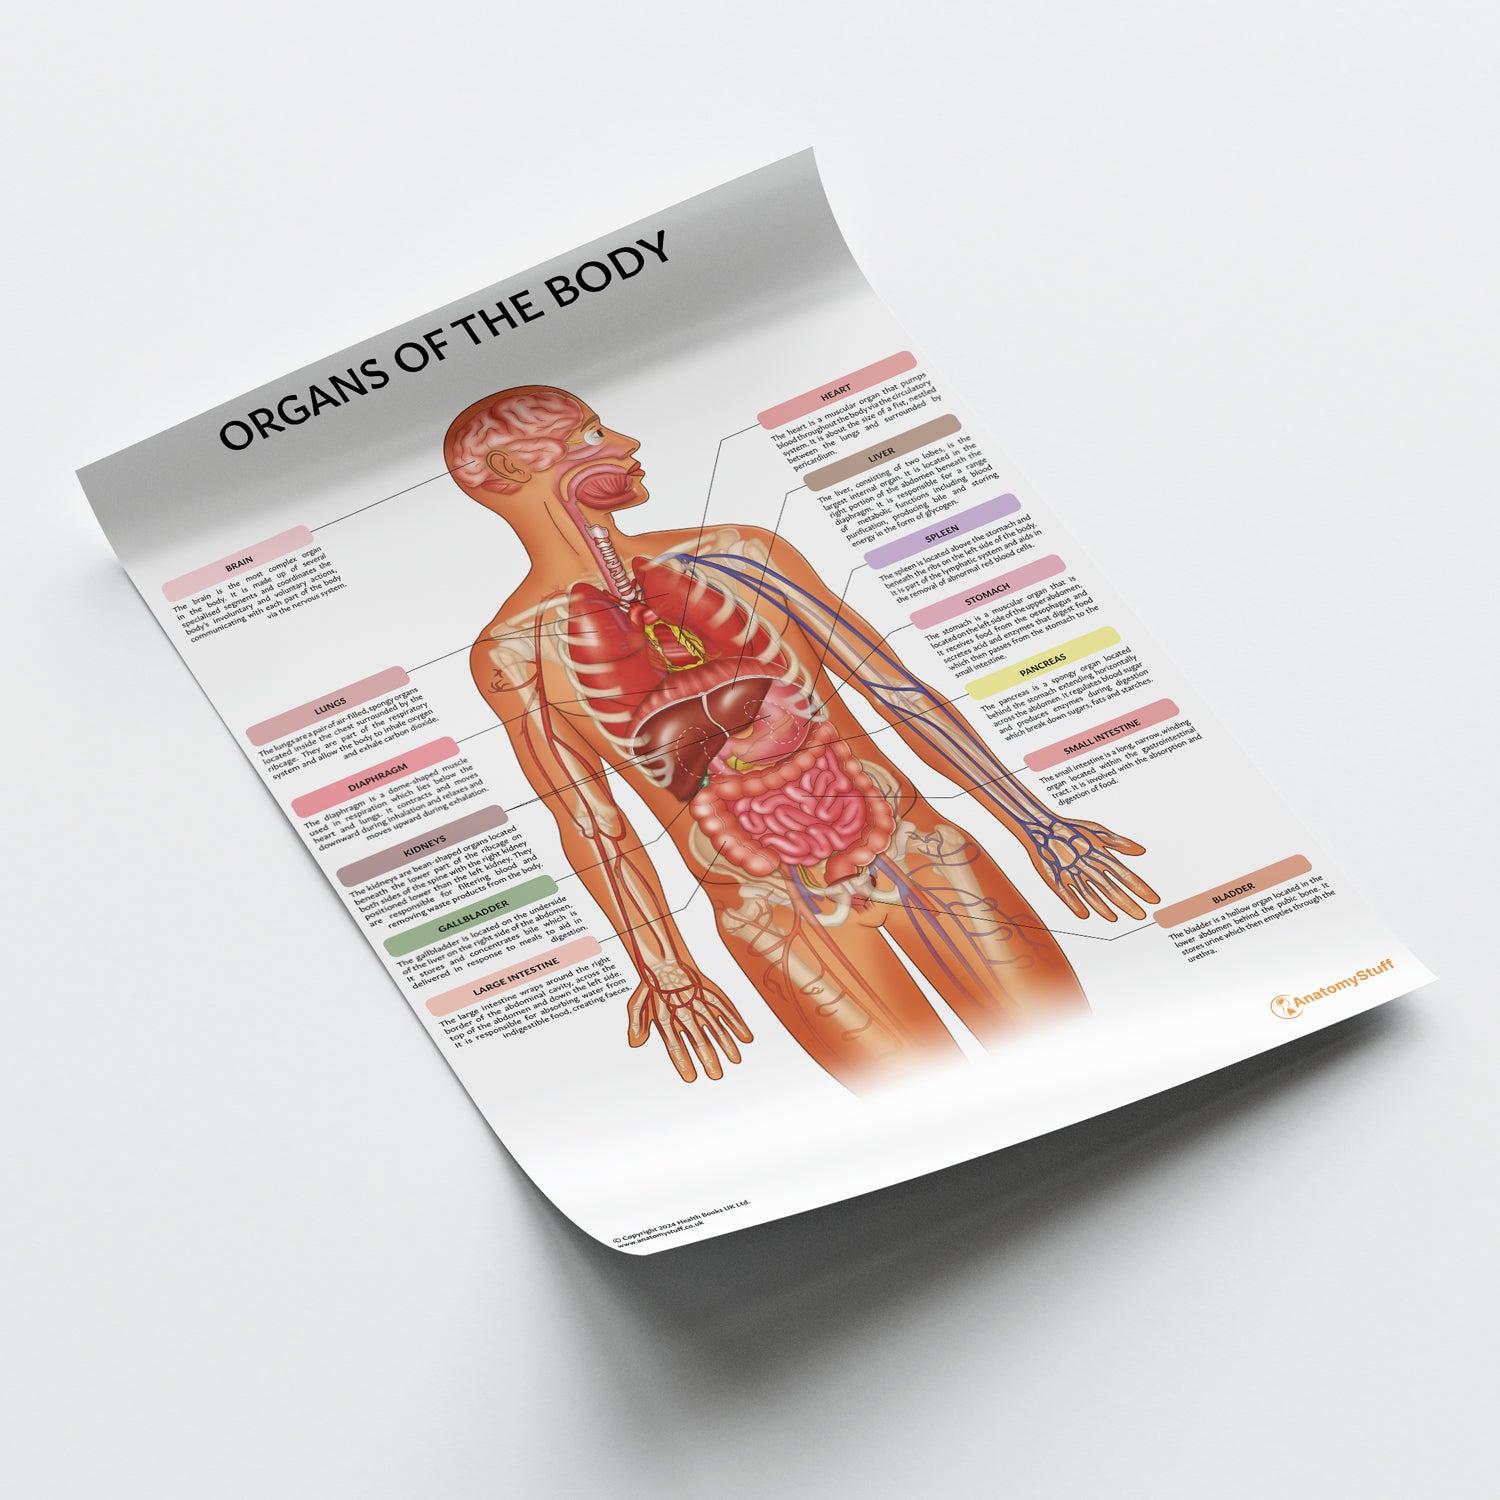
The Problem Nobody Talks About
Most people approach organ anatomy by memorizing static lists of names and definitions. This fails because the body doesn't store information in neat boxes. Organs are physically connected through fascial planes, vascular networks, and autonomic pathways that don't respect the boundaries between individual systems. Learning anatomy as isolated facts creates a fragile knowledge structure that collapses under clinical or practical application. I spent about six months trying to build a proper reference dataset for organ anatomy study, and the hardest part wasn't finding accurate information. It was organizing it in a way that actually reflects how the body functions. Standard textbooks organize by system — cardiovascular, respiratory, digestive. But in practice, nothing works in isolation. The hepatic portal system connects the gut to the liver in a way that makes the digestive and circulatory systems inseparable. Understanding organ anatomy this way takes considerably more time upfront but produces durable knowledge that you can actually use.
Organ Anatomy Of Human: A Working Framework
Here is the approach I ended up using, and one that has held up across different types of study and reference work. Start with spatial relationships, not definitions. Before you name an organ, understand where it sits relative to everything else. The duodenum isn't just a tube — it wraps around the head of the pancreas, crosses the inferior vena cava and aorta anteriorly, and shares its blood supply from the superior mesenteric artery. That spatial configuration explains why pancreatic pathology frequently involves duodenal symptoms, and why a superior mesenteric artery embolism affects both the small intestine and parts of the colon. Knowing the layout gives you predictive power that name memorization never will. Use cross-sectional imaging as your primary learning tool rather than atlas illustrations. Gross dissection atlases show relationships in idealized conditions. CT and MRI slices show what actually happens in living tissue with fat planes, variable organ size, and individual anatomical variation. When I was building reference materials, switching from Netter-style illustrations to axial CT interpretation cut my recall accuracy substantially within a few weeks. The brain encodes three-dimensional spatial information differently when it comes from real imaging data versus stylized drawings.
Learn the vascular supply first, then add everything else on top. The arterial supply to any organ tells you its embryological origin, which neighboring structures it shares developmentally, and where it is likely to be found anatomically. The celiac trunk supplies foregut derivatives — stomach, proximal duodenum, liver, gallbladder, pancreas, spleen. The superior mesenteric artery supplies midgut derivatives. This single organizational principle collapses what looks like dozens of disconnected facts into two coherent patterns. If you understand vascular anatomy, lymphatic drainage follows almost automatically since veins and lymphatics generally travel together.
Get the Full Details

Practical Study Protocol
Here is the method I used when building and studying comprehensive organ anatomy references. It is not elegant but it produces consistent results. Begin each organ system with a 3D anatomy application. I recommend apps that allow layer-by-layer dissection — you can remove skin, then fascia, then muscle, then observe the organ in its anatomical position without everything else distracting you. This visual layering builds spatial memory far more effectively than reading descriptions. Spend about ten to fifteen minutes per organ getting the lay of the land before moving to detailed study. After the spatial foundation, move to flashcards but only after you have done the visual work. Pre-made anatomy flashcard decks are widely available, but I found that creating your own cards while studying the 3D models produces significantly better retention. The act of deciding what goes on each card forces you to identify what you actually don't know versus what you think you know, which is a different cognitive process entirely. Typical retention improvement from this method showed up within two to three weeks of consistent daily practice, maybe twenty minutes per session.
Supplement with cadaveric or gross anatomy photographs when possible. Real tissue photographs show color, texture, and the slight asymmetry that exists between individuals. One specific issue I encountered repeatedly: students who only study idealized diagrams often cannot identify organs in real surgical or radiological images because actual tissue looks quite different from textbook representations. The liver is darker and more congested. Fat deposits obscure boundaries. Inflammation changes everything. Real images train you to deal with this variability.
Common Mistakes and What Actually Fails
There are several patterns I see people repeat that waste substantial time. The most common mistake is studying organs one at a time without understanding their connections. You can memorize the five lobes of the liver and all their biliary drainage patterns in a week. But if you don't simultaneously understand how the portal vein, hepatic artery, and bile ducts travel together through the hepatoduodenal ligament as the portal triad, you have memorized information that is functionally useless. The connections are where the actual learning happens. Another failure point is relying exclusively on mnemonics. Mnemonics are fine for initial recall — learning the branches of the external carotid artery with a phrase is genuinely useful — but they create dead knowledge. You can recite the mnemonic and still not understand why those particular arteries supply those particular structures. The body has reasons for its architecture. Embryological development, hemodynamic requirements, and evolutionary constraints all shape organ position and structure. Understanding the reasons makes the details stick without effort.

A third issue is skipping the retroperitoneal organs. The kidneys, adrenal glands, pancreas, and parts of the duodenum and colon sit behind the peritoneum, and this positioning has major clinical implications. Retroperitoneal organs move differently during respiration, are accessible from different surgical approaches, and their pathology presents differently. Many self-study programs barely cover retroperitoneal anatomy because it is less visually interesting than intraperitoneal organs. This is a significant gap. The retroperitoneum is where a lot of clinically important anatomy lives.
Reference Resources and Downloads
When I needed comprehensive reference material, I assembled a personal collection combining several sources. Here is what ended up being most useful, organized by type. 3D Anatomy Applications: Complete Anatomy, Human Anatomy Atlas (Visible Body), and Anatomy & Physiology by Kenhub all offer detailed organ visualization with layer dissection capability. These are subscription-based but worth the cost if you are doing serious study. Free alternatives exist — Zygote Body from Google and the National Library of Medicine's 3D Anatomy models provide basic visualization at no cost, though they lack the depth of the paid options. Atlas References: Gray's Anatomy for Students remains the most balanced textbook for dedicated study. Clinically Oriented Anatomy by Moore is better if you want the clinical correlation baked into every chapter. Netter's Atlas of Human Anatomy is the reference standard for illustrations but should supplement rather than replace text-based study. Using all three together covers roughly ninety-five percent of what you would need for comprehensive organ anatomy knowledge.
Image Banks: Radiopaedia.org offers thousands of free CT, MRI, and X-ray cases organized by organ system. This is an underutilized resource for anatomy study. Looking at real pathological and normal imaging teaches you more about organ appearance than any atlas illustration. The site also has comprehensive anatomy articles written by radiology residents and fellows, which tends to be more precise than general medical textbook language. Anatomy Question Banks: For testing your knowledge, UWorld's anatomy section and Osmosis question banks both provide well-constructed questions that test application rather than recall. Free alternatives include the OpenStax Anatomy and Physiology test banks and the University of Michigan's gross anatomy question repositories, which are openly available.
A Specific Problem I Encountered
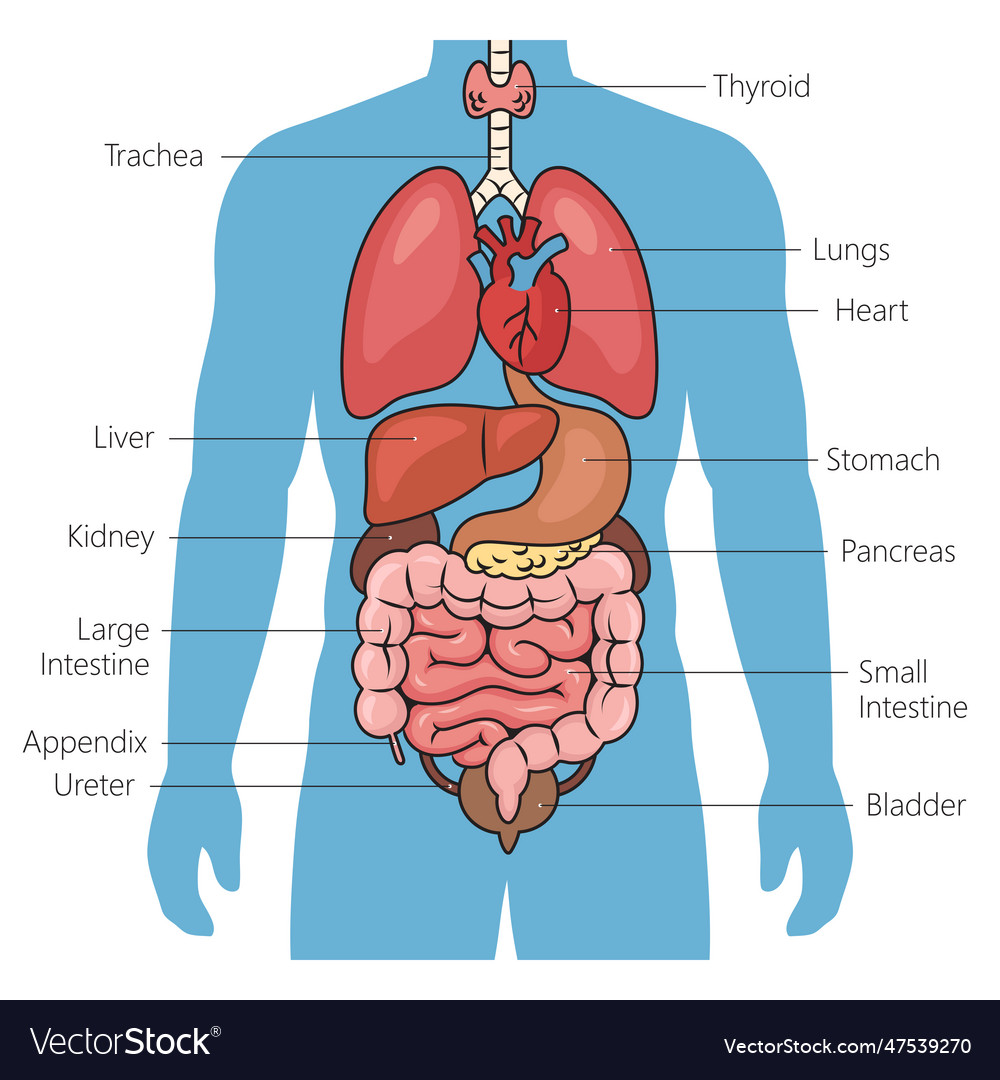
While building a detailed organ reference, I ran into a persistent issue with the hepatic venous drainage pattern. Standard textbooks show three main hepatic veins — right, middle, and left — draining into the inferior vena cava. In about fifteen to twenty percent of the population, however, there are accessory or short hepatic veins that drain directly from the posterior liver surface into the IVC, and these are completely absent from standard diagrams. This mattered because I was cross-referencing imaging findings with anatomical descriptions, and the discrepancy was causing errors in my reference material. The workaround was to switch to a combination of Cross-Sectional Anatomy of the Abdomen and Pelvis by Hricak and Segall plus targeted CT angiography case studies on Radiopaedia. Looking at actual axial CT slices with contrast in the venous phase revealed these accessory veins consistently. Standard atlases simply do not show them because they are variations, not the norm. But in practice, these variations are common enough that ignoring them creates blind spots in your understanding. This experience taught me that no single reference source is sufficient for thorough organ anatomy study. You need at least two sources that approach the material from different angles — one that emphasizes standard anatomy and another that highlights variation and clinical context.
Limitations You Should Know About
Self-studying organ anatomy has real constraints that nobody likes to admit. Without cadaveric dissection experience, your three-dimensional understanding will have gaps. Digital 3D models are impressive but they present idealized anatomy. Real tissue has variability — organ size, position, vascular branching patterns — that models smooth over. If you are studying for clinical purposes, this gap matters considerably. For general knowledge purposes, digital resources are adequate, but you should understand their limitations. The volume of detail required for comprehensive organ anatomy study is substantial. A full semester college course covers this material in approximately forty to fifty contact hours. Self-study typically requires two to three times that amount due to the lack of structured progression and immediate feedback. Expect to spend roughly one hundred fifty to two hundred hours to reach a solid foundational understanding. Anything less and you will have significant gaps, especially in less commonly studied areas like the retroperitoneum and pelvic organs.
Certification or professional credentialing in anatomy requires formal coursework and supervised laboratory experience. Online resources and self-study cannot substitute for this. If your goal is medical or allied health professional credentialing, you need accredited institutional training regardless of how thoroughly you study independently. The field also has ongoing debates about nomenclature. Terminologia Anatomica standardized much of the official Latin terminology, but regional variation in naming persists, particularly between European and American medical education traditions. Be aware that the same structure may appear under different names in different sources, and this can be confusing when cross-referencing material.

Building Your Own Reference System
One practical approach that worked well for me was creating a structured digital reference system rather than relying solely on published materials. I organized it by organ system with subdirectories for gross anatomy, histology, vascular supply, innervation, lymphatic drainage, and clinical correlations. Each organ got its own section with consistent headings, which made comparison between related organs significantly easier. I used a combination of annotated 3D model screenshots, labeled CT image references, and concise text summaries. The annotation process itself — deciding what to label and how to describe relationships — forced active engagement with the material that passive reading never achieves. A typical session involved spending twenty minutes on visual exploration, fifteen minutes creating reference entries, and ten minutes reviewing previously created entries to reinforce retention. This routine produced noticeable improvement in recall within about three weeks. The system I built eventually contained reference material on approximately two hundred distinct anatomical structures across all organ systems. Maintaining it required ongoing attention but the cumulative effect of building the reference was itself a powerful study method. The final product served as both a learning tool and a long-term reference that I continued to add to and refine over years.
If you are starting from scratch, consider the most efficient path: begin with a 3D anatomy app for spatial orientation, supplement with Cross-Sectional Anatomy for real tissue understanding, use a standard textbook for systematic coverage, and test yourself regularly with application-based questions rather than pure recall quizzes. This combination addresses the major limitations of any single resource and produces more reliable knowledge than any individual approach alone.

