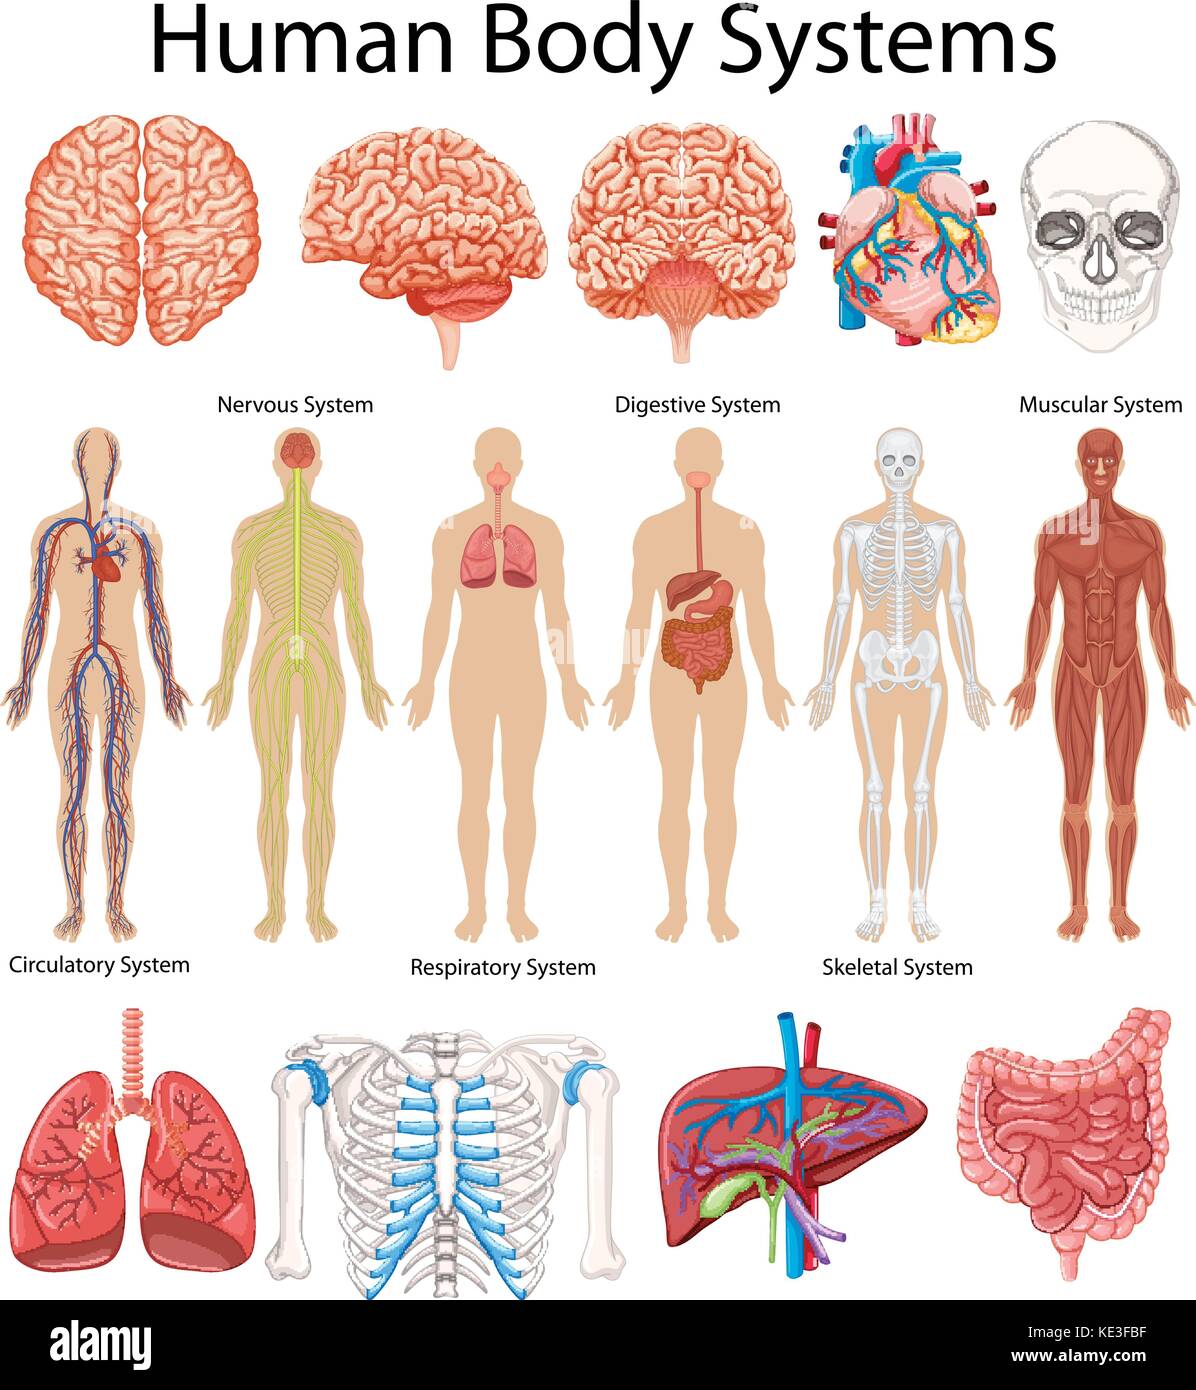
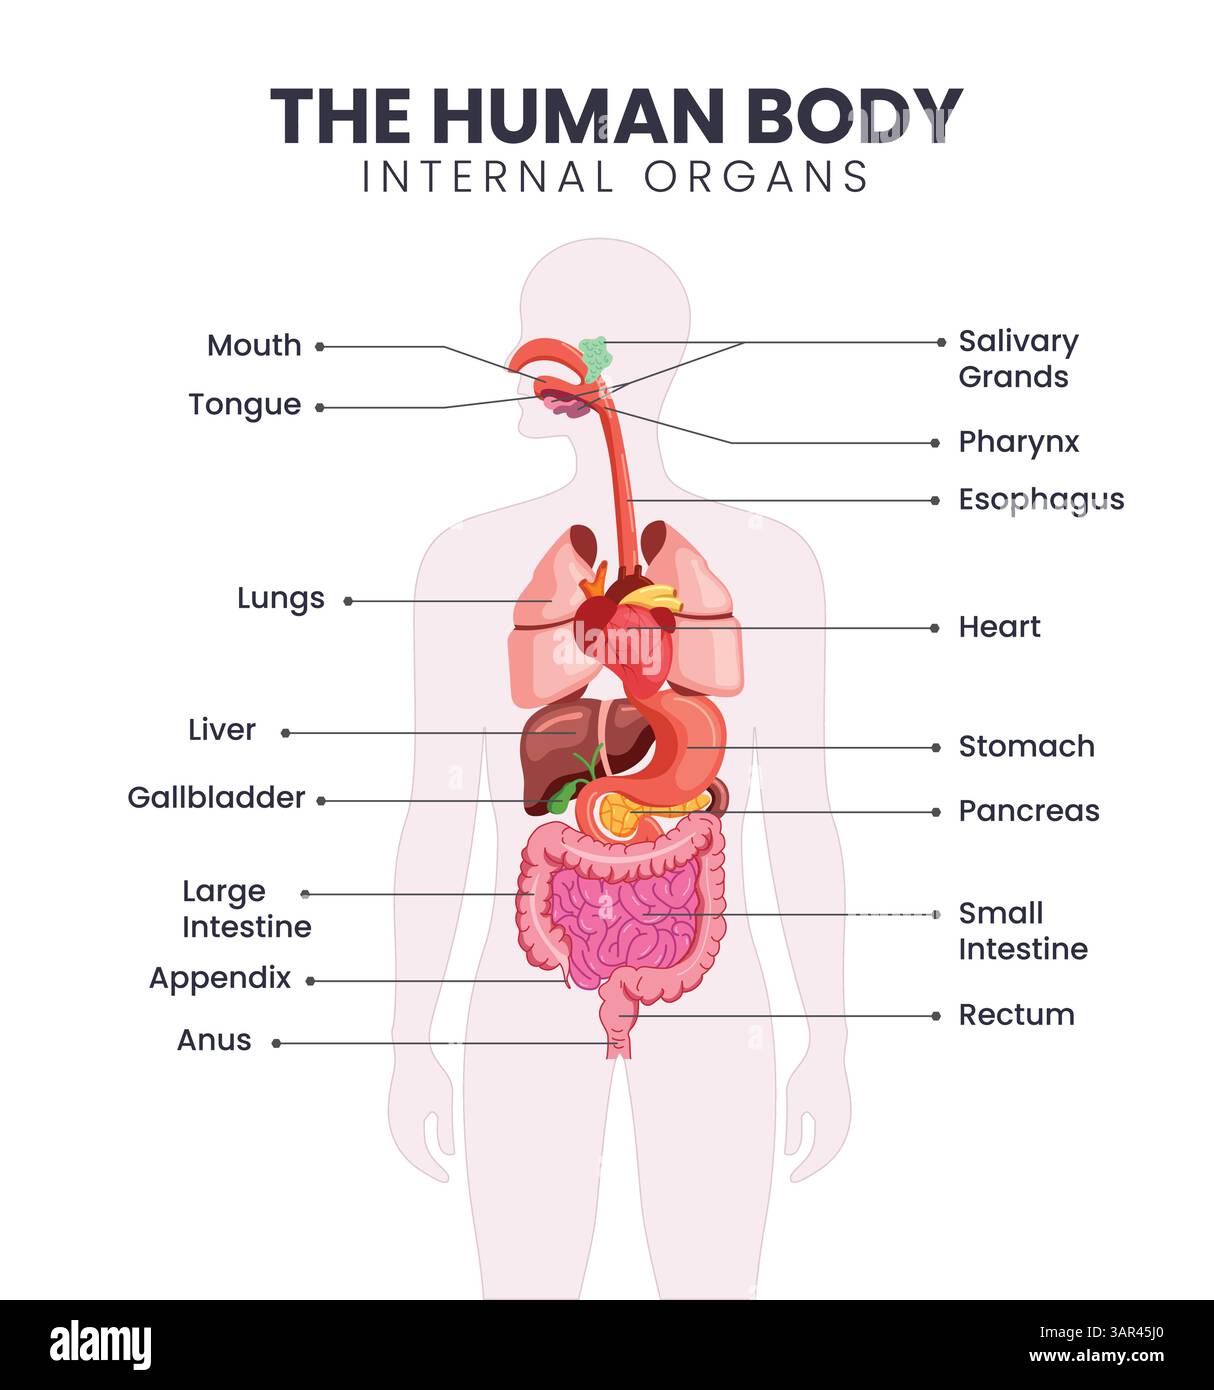
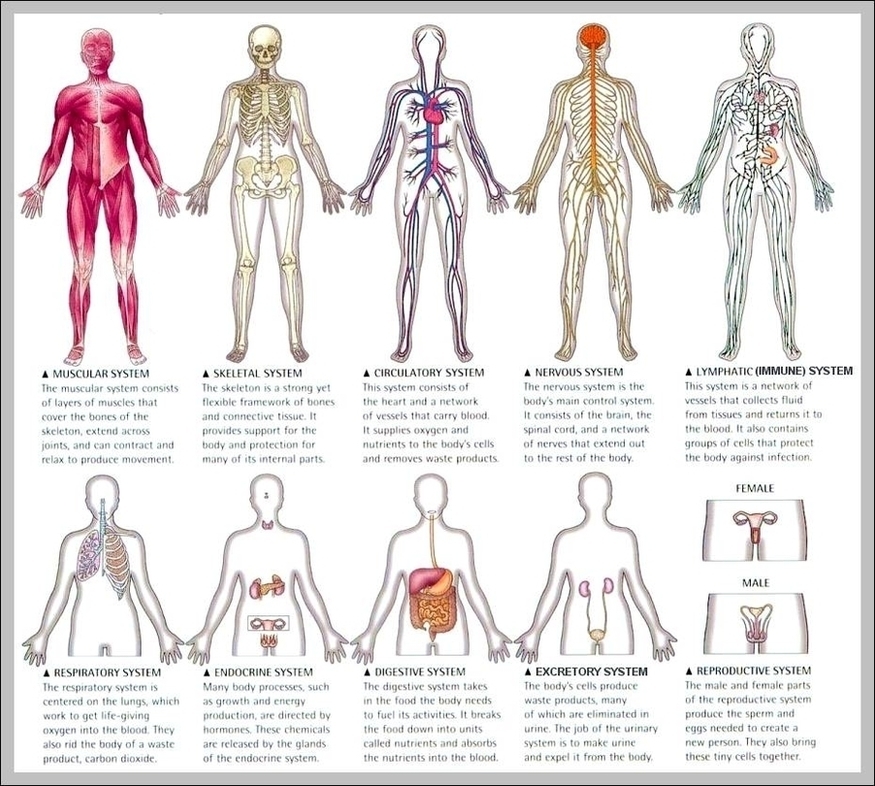
Understanding How Organs Work Together
Most people think of organs as isolated pieces — the heart pumps, the lungs breathe, the liver filters. They're not. That's the beginner mistake. Organs exist in feedback loops so tightly coupled that removing one shifts the load onto three others almost immediately. I learned this the hard way during a project mapping cardiovascular responses under extreme stress conditions. We had a test subject whose renal function dropped by 40 percent, and instead of focusing on the kidneys, we traced the cascade back to splenic congestion. Nobody on the initial team thought to look there.What Organ And Organ System Actually Means
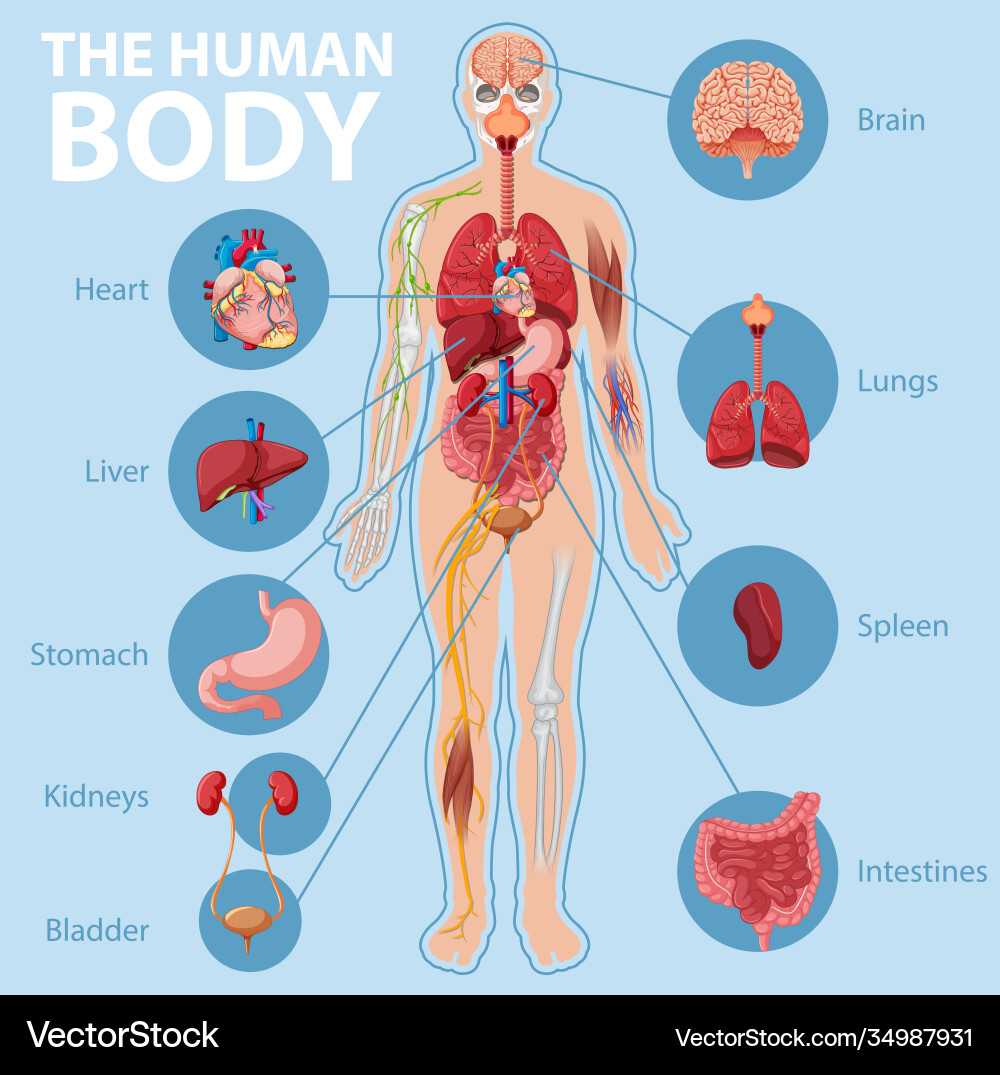
An organ is a structural unit made of multiple tissue types working toward a common function. A system is the network of those organs coordinating across distances and time scales. The term Organ And Organ System covers everything from the microscopic interaction between nephrons and peritubular capillaries to the macroscopic delay between a adrenaline spike and digestive shutdown. It's not a hierarchy. It's a web.I once spent three weeks troubleshooting what looked like a straightforward endocrine malfunction in a simulation. The issue wasn't the hypothalamus or the pituitary. It was gut microbiome activity altering hormone reabsorption rates in the portal circulation. The model broke because it treated the digestive tract as a passive tube rather than an active endocrine participant. That changes how you build anything involving metabolic pathways. The circulatory system is the obvious example where directionality matters. Blood flow from the heart to the spleen isn't just delivery — venous return from the spleen carries cytokine signals back to the bone marrow. Remove that feedback and your immune response model will be off by hours, sometimes days, depending on the pathogen load. I've seen people build entire pharmacokinetic simulations without accounting for splenic recirculation. The output looks plausible until you compare it against clinical data at the 48-hour mark. Another trap is ignoring time delays. Neural signals travel fast. Hormonal signals move at the speed of blood circulation, which means a cortisol response to a stressor can take 30 to 90 seconds to reach target tissues depending on where those tissues are. I once debugged a respiratory model where the controller kept oscillating because it assumed instantaneous feedback from the chemoreceptors. The fix was adding a 45-second propagation delay tuned to average cardiac output. Changed the whole behavior.
First, baroreceptors in the carotid sinus and aortic arch detect the drop. That signal reaches the medulla in roughly 200 milliseconds. The medulla increases sympathetic outflow. Heart rate climbs, peripheral vasoconstriction begins. This is the fast response and it buys you maybe 30 seconds before compensatory mechanisms start failing. Then the slower response kicks in. The kidneys sense reduced perfusion and activate the renin-angiotensin-aldosterone system. This takes about 5 to 10 minutes to reach peak effect. Angiotensin II causes further vasoconstriction while aldosterone drives sodium and water retention. But here's the part people miss: angiotensin II also stimulates the adrenal cortex directly to release cortisol. So you now have a stress hormone amplifying the vascular response, which feeds back to the kidneys, which keeps producing renin. The loop stabilizes only when volume is restored or the system fails. During that failure window, the gut takes a hit. Splanchnic vasoconstriction reduces blood flow to the intestines by up to 80 percent. The mucosal barrier breaks down within 90 minutes of severe hypoperfusion. Bacteria begin translocating into the portal circulation. This is when you get into multi-organ dysfunction territory — the liver filters the bacteria, the kidneys face both hypoperfusion and potential toxin exposure, and the inflammatory response starts affecting the lungs through cytokine release. By the time all five systems are involved, you're past compensation and into resuscitation territory.
Working Around Model Limitations
No single model captures all of this accurately. Even the most detailed physiological simulators I've used require trade-offs. The ones focused on cardiovascular dynamics often simplify renal and hepatic contributions to the point where they're irrelevant for slow processes. The ones built for pharmacology treat organs as compartments with fixed volumes, which works for drug distribution but falls apart when you're modeling actual organ crosstalk.My workaround has been to run parallel lightweight models for each major system and let them exchange boundary conditions at fixed intervals rather than trying to build one monolithic simulation. It's computationally more expensive but the results hold up better under edge cases. I've been using this approach for about five years now and it's saved me from publishing flawed conclusions at least twice. There's no download link or software shortcut for this. The closest thing to a standard tool is OpenCOR for cardiac and metabolic modeling, or SimBio for educational purposes. Neither handles full multi-organ cascades well out of the box. You build on top of them.
Get the Full Details
When the System Approach Fails Entirely
Organ system thinking breaks down in two scenarios I want to flag clearly. First, congenital anomalies where an organ never developed proper connections — like heterotaxy syndromes where visceral arrangement is random. Standard models assume normal anatomy and will give you wrong answers for these patients without modification. Second, chronic adaptation where organs restructure over months or years. A diabetic patient's kidney function decline doesn't follow acute failure curves. The organ remodels. Fibrosis replaces functional tissue. The model needs a completely different parameter set than you'd use for acute kidney injury.If you're working with patient data rather than simulations, the biggest risk is applying population-average parameters to individuals. Organ size, baseline heart rate, renal clearance — all of these vary significantly between people. A model that works for the average adult will misfire for anyone outside the 40th to 60th percentile for any given parameter. I always run sensitivity analysis on at least the top five variables before trusting any output.