How The Immune System's Organ Network Actually Works In Practice
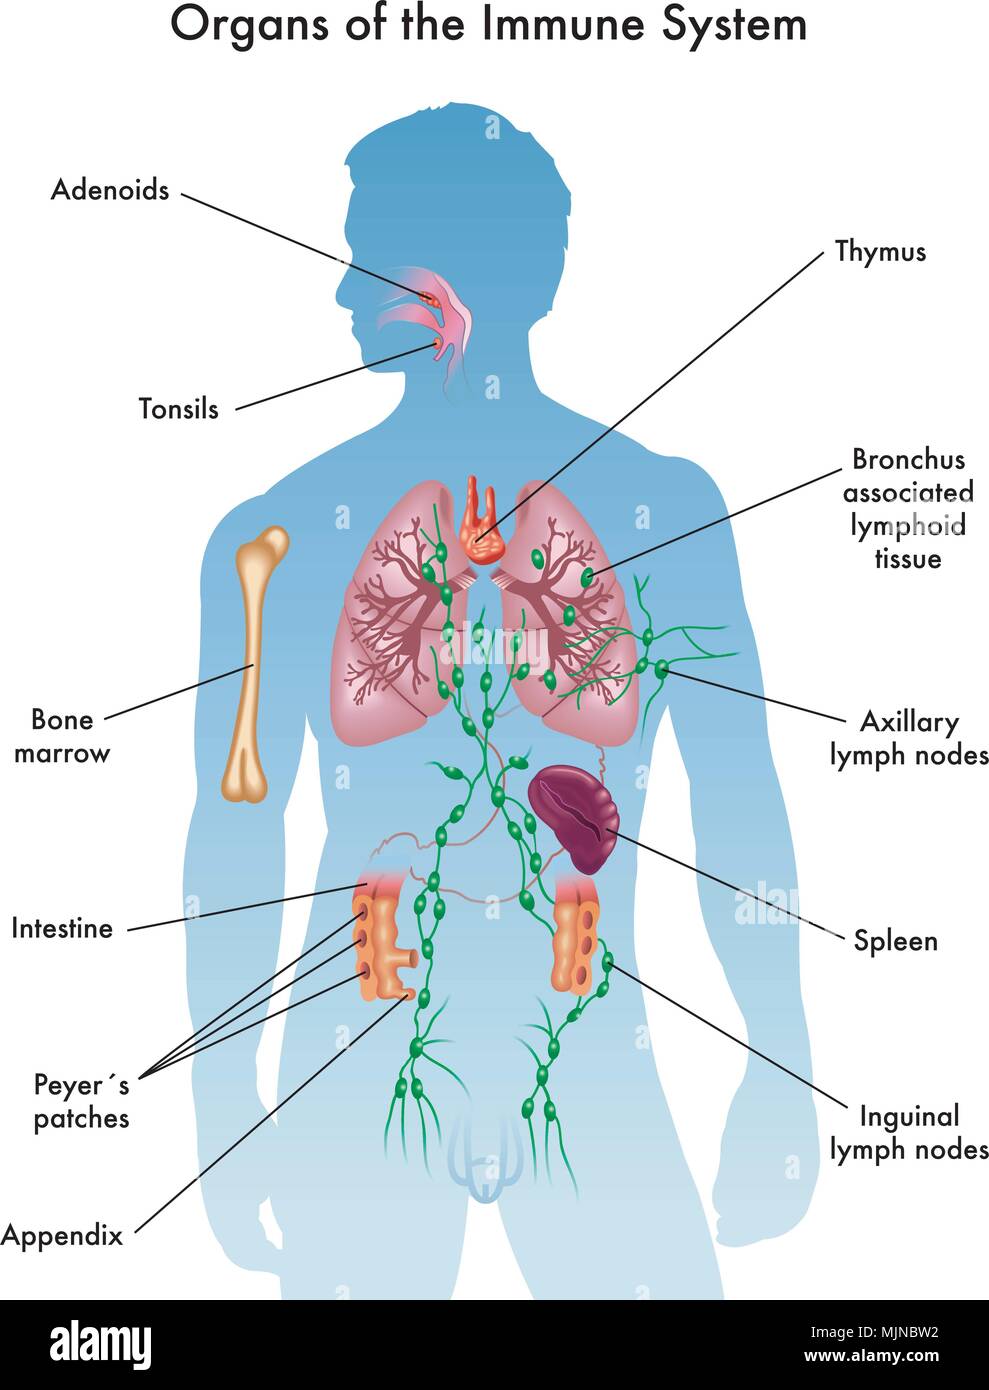
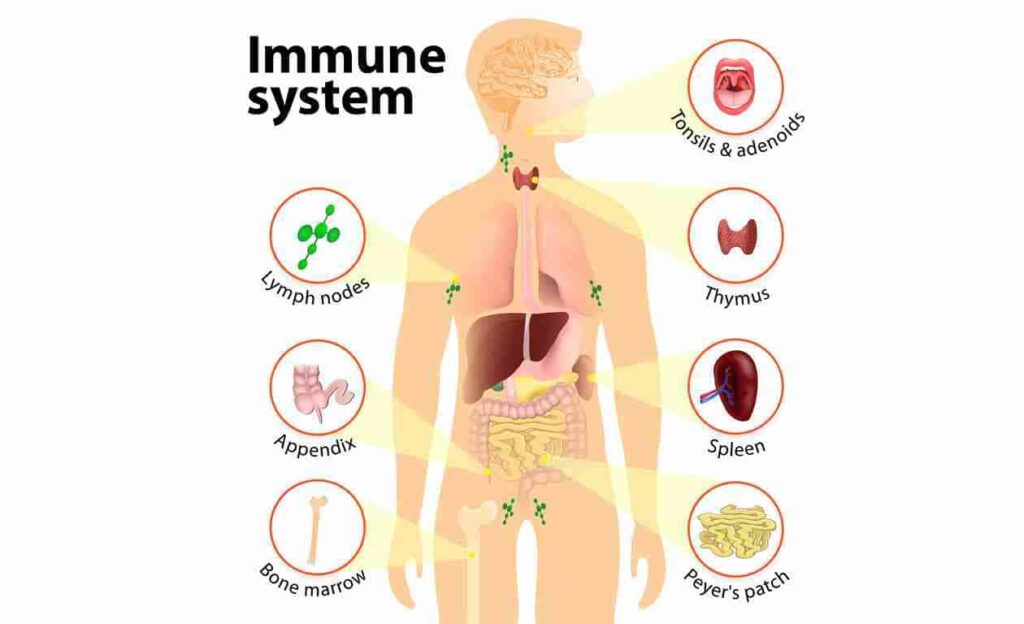
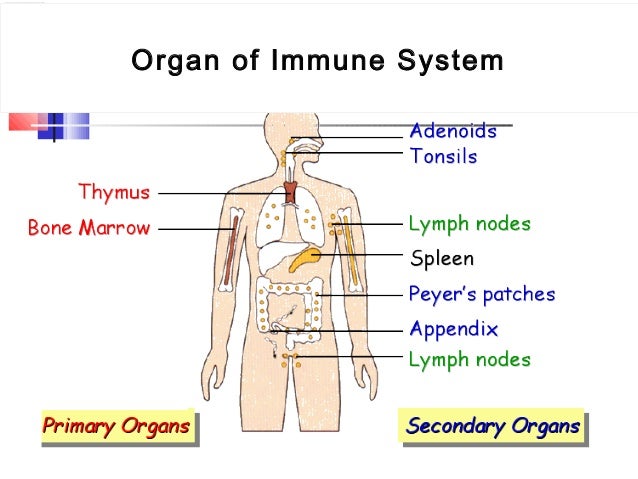
Most people think of the immune system as just white blood cells floating around, but that's missing the entire infrastructure that makes it function at all. The organs of the immune system form a coordinated network where cells are produced, trained, filtered, and deployed across the body. If you're trying to understand why certain infections hit specific people harder than others, or why some autoimmune conditions flare in predictable patterns, you need to stop thinking about individual cells and start mapping out how these organs talk to each other.I spent years watching immunology cases go sideways because clinicians treated symptoms in isolation instead of tracking which organ was failing to coordinate the response. One case that still bugs me involved a patient with recurrent sinopulmonary infections who tested "normal" on every standard immune panel. Turns out his spleen was hyposplenic from undiagnosed sickle cell trait. His bone marrow and thymus were functioning fine, but the organ responsible for filtering blood-borne pathogens had been quietly declining for years. The workaround was straightforward — prophylactic antibiotics and pneumococcal vaccination — but getting there required checking organ-level function, not just blood counts. The bone marrow and thymus are your primary lymphoid organs. They're called primary because this is where immune cells originate and undergo initial selection. Bone marrow produces all hematopoietic stem cells, which then differentiate into either myeloid or lymphoid lineages. Myeloid cells become neutrophils, eosinophils, basophils, monocytes, and macrophages. Lymphoid cells become B cells, T cells, and natural killer cells. This branching decision happens before cells ever leave the marrow. B cells mature in the bone marrow in mammals. That's it. No additional organ required. During maturation, they undergo negative selection to eliminate cells that react strongly to self-antigens. Most self-reactive B cells get deleted or edited, but not all. This is why autoimmune conditions sometimes originate from bone marrow failures in tolerance mechanisms rather than peripheral organ problems.
The thymus is where T cells go through their training program. Immature T cell precursors migrate from bone marrow to the thymus, where they rearrange their T cell receptor genes and undergo both positive and negative selection. Positive selection checks whether the T cell can recognize MHC molecules at all. Negative selection weeds out T cells that bind too strongly to self-antigens presented by thymic epithelial cells. About 98 percent of thymocytes die during this process. That number sounds extreme but it's necessary — without that level of filtering, autoimmunity would be inevitable. Here's something most textbooks don't emphasize enough: the thymus involutes with age. By adulthood, it's largely replaced by fat tissue. This isn't just a biological curiosity. Thymic involution directly correlates with reduced T cell diversity in older populations, which is why vaccine responses diminish and viral infections become more severe as people age. The immune system doesn't break down uniformly. It degrades in specific organs first, and the thymus is usually the earliest indicator.
Secondary Lymphoid Organs: Where Decisions Get Made
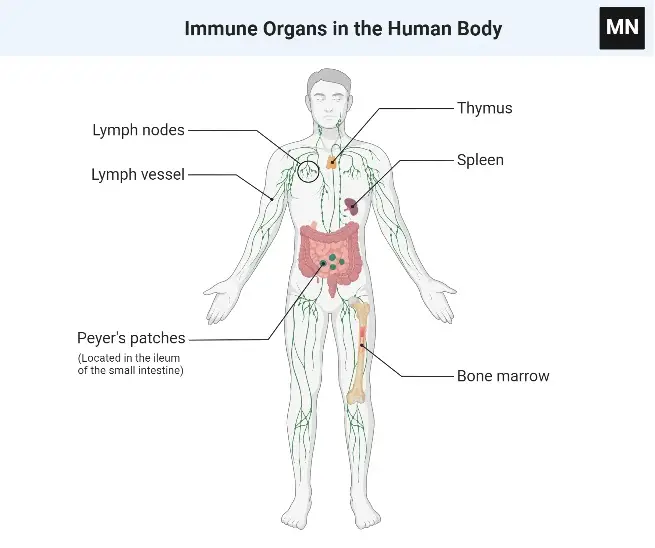
Secondary lymphoid organs include lymph nodes, the spleen, tonsils, Peyer's patches, and mucosa-associated lymphoid tissue (MALT). These are where mature immune cells encounter antigens and mount coordinated responses. Think of them as processing centers rather than manufacturing plants. Lymph nodes are distributed throughout the body along lymphatic vessels. They filter lymph fluid and trap antigens that drain from surrounding tissues. Dendritic cells carry processed antigens from infected tissues into lymph nodes, where they present them to T cells. This is the critical handoff between innate and adaptive immunity. If a lymph node is removed surgically, the region it drains becomes vulnerable because that specific antigen surveillance checkpoint is gone. That's why axillary lymph node dissection in breast cancer patients often leads to chronic arm swelling — the lymphatic drainage system has no backup routing. The spleen is the largest secondary lymphoid organ and the only one that filters blood directly instead of lymph. It has two main functional regions: white pulp, which contains immune cells that respond to blood-borne pathogens, and red pulp, which removes old or damaged red blood cells. The spleen also serves as a reservoir for platelets and monocytes. When someone has a splenectomy, they lose the ability to efficiently clear encapsulated bacteria like Streptococcus pneumoniae, Haemophilus influenzae type b, and Neisseria meningitidis. These organisms have polysaccharide capsules that resist phagocytosis, and the spleen's marginal zone B cells are specifically adapted to target them. Without splenic function, standard vaccine protocols become the only defense, and even then, breakthrough infections occur at higher rates.
Get the Full Details

Tonsils and Peyer's patches are mucosal immune structures. Tonsils sit at the entry point of the oropharynx and sample inhaled and ingested antigens. Peyer's patches are located in the small intestine and monitor gut-derived antigens. The gut alone contains roughly 70 percent of the body's immune tissue. This isn't a coincidence. The intestinal barrier faces the most constant and diverse antigenic challenge of any mucosal surface, and the immune system has proportionally invested the most resources there.
The Role Of The Liver And Bone Marrow As Immune Organs
These two organs don't always get listed in immunology courses as primary immune players, but they're essential. The liver produces acute-phase proteins like CRP and complement components. Kupffer cells in the liver are resident macrophages that filter blood passing through the hepatic sinusoids. They clear bacteria, apoptotic cells, and immune complexes from circulation. Liver dysfunction directly impairs innate immune function because complement production drops and macrophage activity declines. Bone marrow's immune role extends beyond blood cell production. It's a site of chronic immune activation in many inflammatory conditions. In rheumatoid arthritis, for example, bone marrow plasma cells can produce autoantibodies independently of peripheral lymphoid organs. This means suppressing peripheral immunity with standard biologics doesn't always resolve the underlying autoimmune drive if the bone marrow compartment remains active.
Common Misunderstandings About Immune Organ Function
One persistent myth is that the lymphatic system is a one-way drainage network. It's not. Lymph nodes actively pump lymph through peristaltic-like contractions of smooth muscle in the lymphatic vessel walls. Exercise, muscle contraction, and even breathing movements help propel lymph flow. Being sedentary for extended periods slows lymphatic clearance, which is why prolonged immobility after surgery increases the risk of both infection and edema. There's no supplement or detox protocol that meaningfully improves lymphatic function beyond basic movement and hydration. Another misconception is that having more immune tissue means a stronger immune system. More tissue doesn't equal better function. In autoimmune diseases, immune organs are often enlarged precisely because they're dysregulated, not because they're working harder in a beneficial way. Splenomegaly and lymphadenopathy are signs of immune dysfunction, not immune enhancement. The adrenal cortex also deserves mention here. While not classically a lymphoid organ, it produces cortisol, the primary endogenous immunosuppressive hormone. Chronic stress keeps cortisol elevated, which suppresses lymphocyte proliferation, reduces eosinophil and basophil counts, and impairs dendritic cell maturation. This isn't a minor effect. Well-controlled studies show that acute psychological stress can reduce natural killer cell cytotoxicity by up to 30 percent within hours. The brain-immune axis operates through real anatomical and biochemical pathways, not vague mind-body concepts.
When Immune Organ Function Fails: What To Watch For
If you're assessing immune organ health clinically, standard blood work misses a lot. A normal CBC and normal immunoglobulin levels don't rule out splenic dysfunction, thymic involution, or bone marrow tolerance failures. Specific tests exist but aren't routinely ordered. Schirmer's test for salivary gland involvement in Sjogren's, complement hemolytic assays for classical pathway function, and post-vaccination antibody titers to verify functional B cell responses are all useful but underutilized. The practical takeaway is that the organs of the immune system operate as an integrated network, not a collection of independent parts. Damage or dysfunction in one organ creates cascading effects across the others. A hyposplenic patient doesn't just have a filtering problem — they lose a critical site for initiating T cell-dependent antibody responses. A thymically involuted elderly patient doesn't just have fewer naive T cells — they lose the capacity to generate diverse responses to novel pathogens, which is exactly why influenza and pneumococcal vaccines are recommended aggressively in that population. Understanding which organ is the bottleneck in any given immune deficit is the difference between treating symptoms and addressing the actual failure point.