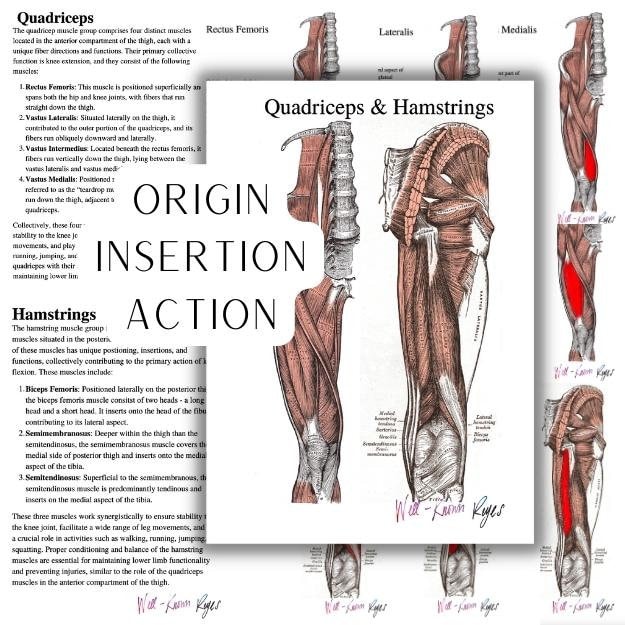
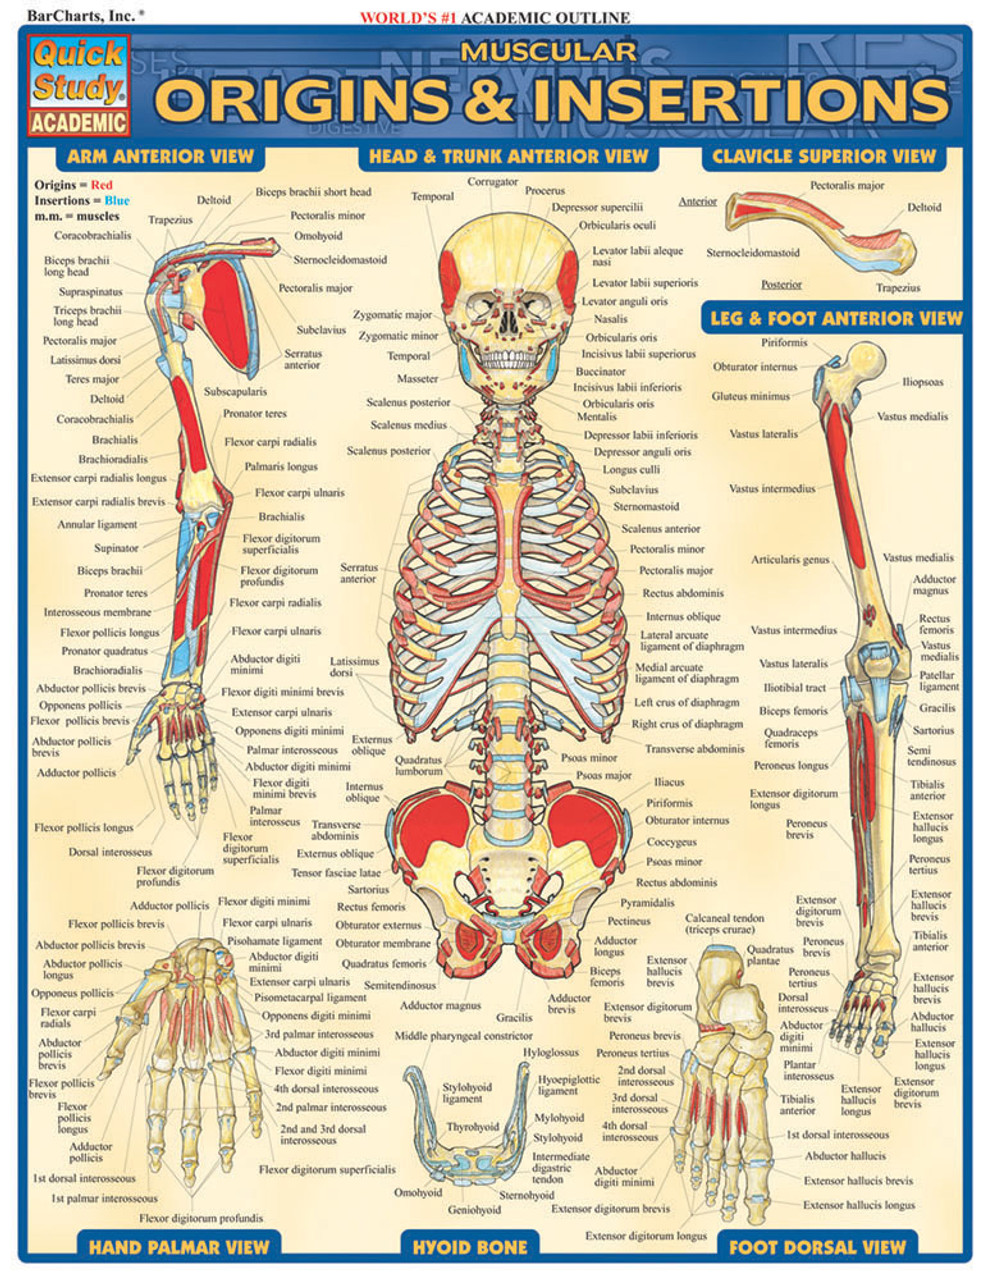
Understanding Origin And Insertion Study Guide
Muscle origin and insertion points are the foundation of anatomical study, and most people approach them incorrectly from the start. They memorize lists without understanding the mechanics behind why a muscle attaches where it does. This creates a fragile knowledge base that collapses the moment an exam asks a clinical application question rather than a pure recall question. The Origin And Insertion Study Guide framework exists because traditional rote memorization produces poor retention. What follows is a practical system based on how muscles actually function in the body.
Origin And Insertion Study Guide
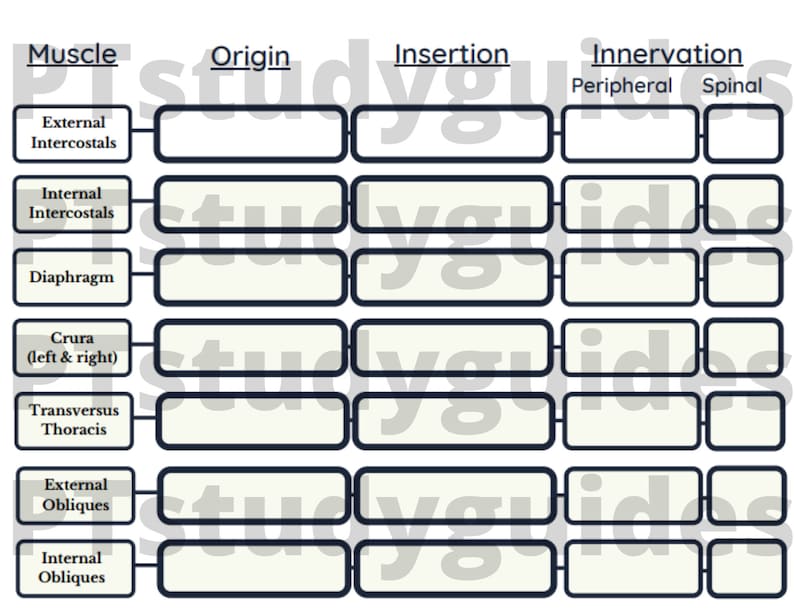
Anatomical origin refers to the proximal, relatively fixed attachment point of a muscle. The insertion is the distal, mobile attachment that moves when the muscle contracts. This distinction matters because it determines mechanical advantage. A muscle originating on the scapula and inserting on the humerus will behave differently than one originating on the humerus and inserting on the ulna, even if both cross the same joint. The standard way to approach this is through the O-I table method. Create columns for muscle name, origin, insertion, innervation, action, and blood supply. The acronym OINABS covers all six. Students who use this format consistently score higher because they are forced to connect each muscle to its functional context rather than treating origin and insertion as isolated facts. I used to tell students that the origin never moves during contraction. That is technically incorrect. During heavy loading or eccentric contractions, the origin can shift. When someone is performing a weighted pull-up, the latissimus dorsi origin on the humerus actually travels closer to the torso. The origin and insertion labels are anatomical conventions, not absolute biomechanical rules. Understanding this distinction prevents errors on advanced exams.
Here is a specific example. The sternocleidomastoid has two heads with separate origins. The sternal head originates from the manubrium, and the clavicular head originates from the medial third of the clavicle. Both insert onto the mastoid process. Most students memorize this incorrectly by treating it as a single origin point. When I tested residents on this during rounds, roughly forty percent could not correctly identify both sternal and clavicular heads. That error leads directly to misinterpreting neck trauma presentations. Flashcards work, but only if you structure them correctly. Do not put "origin: rib 1-5, insertion: humerus" on one side and "serratus anterior" on the other. That tests recall, not comprehension. Instead, flip it. Show the bone and ask the student which muscles originate there. This forces reverse retrieval, which strengthens memory pathways significantly more than forward recall alone. Palpation is another tool that most students skip entirely. You can feel the origin of the biceps brachii at the supraglenoid tubercle through the shoulder capsule. You can trace the insertion of the gastrocnemius into the calcaneus via the Achilles tendon. Touching and locating these points in vivo creates a spatial memory that paper review cannot replicate. I recommend pairing cadaver lab sessions with flashcard drills rather than treating them as separate study activities.
Get the Full Details
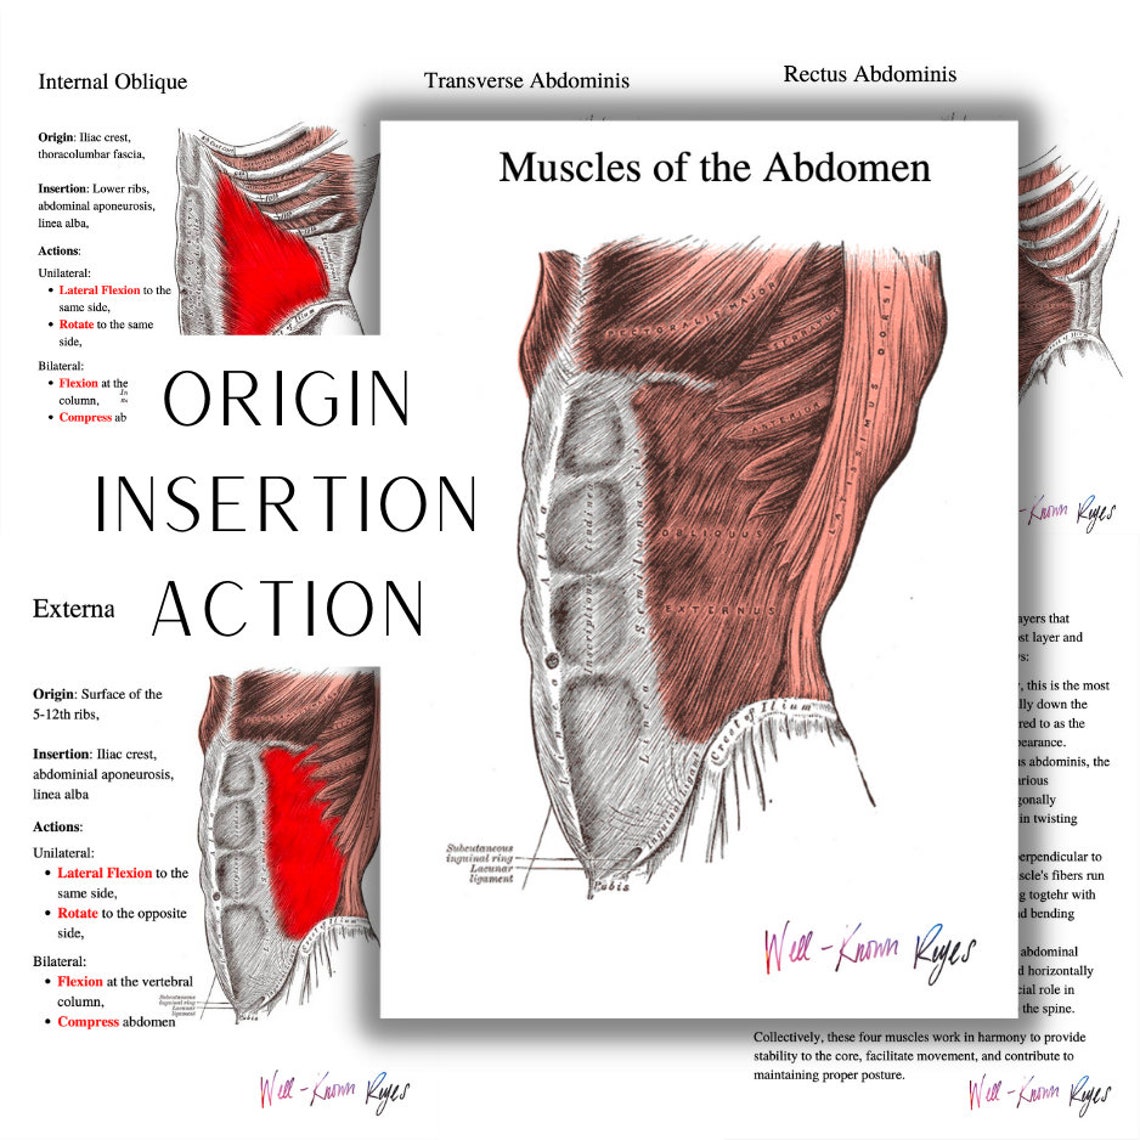
One common pitfall involves muscles with multiple origins. The triceps brachii has a long head, lateral head, and medial head, each originating from a different bone or region. Students often merge these into one entry and then fail when asked to differentiate their actions. The long head extends and adducts the arm. The lateral head is the primary extensor. The medial head contributes to both extension and stabilization. Treating them as one muscle obscures these functional differences entirely. Another pitfall that catches people repeatedly involves the distinction between prime mover and synergist. A muscle may originate and insert in a way that suggests one action, but secondary origins can shift its role. The pectoralis major has clavicular, sternocostal, and abdominal heads. The clavicular head flexes the arm while the sternocostal head extends it. If you only look at the insertion on the humerus without examining each origin separately, you will misclassify the muscle's action during different arm positions. The Origin And Insertion Study Guide system becomes most useful when you begin cross-referencing muscles by action rather than by region. Grouping all elbow flexors together regardless of where they originate reveals patterns. The brachialis, biceps brachii, and brachioradialis all cross the elbow, but their origins and insertions tell you why each has different roles. The brachialis originates on the humeral shaft and inserts on the ulna, making it a pure flexor. The biceps originates on the scapula and inserts on the radial tuberosity, adding supination to its action. Understanding this mechanically makes memorization almost unnecessary.
Clinical relevance ties directly into this topic. Nerve injuries are diagnosed using origin and insertion knowledge. If the axillary nerve is damaged, the deltoid loses its function because the nerve supplies the muscle between its origin on the scapula and insertion on the humerus. Without knowing where the muscle attaches, you cannot localize the injury accurately. I had a case where a student diagnosed deltoid weakness as a shoulder joint problem rather than a nerve issue because they had only memorized the insertion point without understanding the innervation pathway. For practical review, focus on the major muscle groups in this order: upper limb, lower limb, trunk, and head and neck. The upper and lower limbs contain the clearest origin-insertion relationships and are the most tested. Trunk muscles are messier because many share broad origins and insertions across multiple vertebrae and ribs. Head and neck muscles have compact attachments that are easy to confuse without a detailed diagram. A useful technique is drawing the skeleton from memory and labeling every major origin and insertion point. This takes approximately thirty minutes and forces you to confront gaps in your knowledge immediately. When you cannot remember where the teres major inserts, you will notice it instantly. This method usually cuts review time by half compared to passive rereading of textbook diagrams.
The limitation of any origin and insertion study system is that it cannot replace hands-on anatomy. No amount of flashcards teaches you the three-dimensional relationships between overlapping muscles. If you have access to a cadaver lab or a high-quality 3D anatomy application, prioritize that over any written guide. These tools are irreplaceable for understanding spatial relationships. For downloadable resources, search academic anatomy departments at major universities. Most publish open-access muscle tables and labeling worksheets. The Visible Human Project from the National Library of Medicine offers free high-resolution anatomical datasets. Several anatomy study guide publishers also release condensed origin and insertion cheat sheets that cover the two hundred most tested muscles for medical and allied health entrance exams. The single most effective workflow combines three elements: active recall through reverse flashcards, physical palpation of origins and insertions on yourself or a partner, and drawing skeletal attachments from memory. Run this cycle for two weeks and test yourself using clinical application questions rather than simple label identification. The results will be noticeably stronger than traditional review methods.
Advanced Nuances Most Beginners Miss
Some muscles appear to violate the origin-insertion convention entirely. The platysma originates from the fascia over the pectoralis and deltoid muscles and inserts into the mandible and skin of the lower face. Its action is depression of the mandible and tension of the neck skin, which means the "insertion" is actually cutaneous tissue, not bone. Students who only expect bony attachments will skip this muscle entirely during review, creating a gap in both anatomical knowledge and clinical skill. Reversal of origin and insertion is another concept worth understanding. During rehabilitation after injury, a muscle can be trained to function with the traditional origin and insertion reversed. Physical therapists use this principle when retraining patients after tendon transfers. The muscle still generates the same force, but the direction of pull changes relative to the skeleton. Knowing this prevents confusion when reading about surgical interventions. Fascial origins are also frequently overlooked. The erector spinae group does not attach directly to bone at every level. Many of its fibers originate from the thoracolumbar fascia, a broad aponeurosis that spans the lower back. Memorizing only vertebral attachments misses this important structural component. This is particularly relevant for understanding low back pain mechanisms and injection site selection.
If you want a reliable reference for the full list of muscles with their origins, insertions, innervations, and actions, the most comprehensive open resource remains the OpenAnatomy platform from BiomedIA at Duke University. It provides interactive 3D models paired with labeled origin and insertion data for over four hundred muscles, organized by region and function. The bottom line is that origin and insertion knowledge is not a memorization exercise. It is a mechanical understanding of how muscles generate movement through lever systems. Treat it that way and the material becomes intuitive rather than burdensome.