Why Mouth Taping and Tongue Trainers Keep Getting Recommended (And When They Actually Work)
Orofacial Therapy For Sleep Apnea is a category of interventions that targets the muscles and positioning of the mouth, tongue, and throat to reduce airway collapse during sleep. It is not a replacement for CPAP in moderate to severe cases, but for people with mild obstructive sleep apnea or primarily positional apnea, it can make a measurable difference. The problem is that most people have no clear idea what actually goes into it, so they buy a random product online and wonder why it did nothing. The therapy covers several distinct approaches that are often lumped together. Myofunctional therapy involves repeated exercises for the tongue, soft palate, and facial muscles. Oral appliances like mandibular advancement devices reposition the lower jaw forward to keep the airway open. Mouth taping prevents nasal-breathing disruption by keeping the lips sealed. Tongue retainers and palatal implants are more mechanical versions of the same goal. All of them share one mechanism: increasing the cross-sectional area of the upper airway or reducing the collapsibility of the tissues that block it. What most people miss is that these treatments work best when they are combined with a proper sleep study diagnosis. I have seen patients start mouth taping because a TikTok recommended it, only to discover later they had severe central sleep apnea where oral therapy has zero effect. That delay is common. The therapy is not dangerous, but the lack of diagnosis is.
Myofunctional exercises are the foundation most clinics recommend first. The standard protocol involves tongue presses, soft palate raises, and resistive breathing drills done daily for eight to twelve weeks. Studies typically show a thirty to fifty percent reduction in AHI for patients with mild OSA who complete the program consistently. Compliance is the real bottleneck. Most patients drop off after three weeks because the exercises feel pointless until the fourth week when they notice less snoring. Mandibular advancement devices are more immediately effective but come with dental complications. The device pushes the lower jaw forward, sometimes by six to eight millimeters, and holds it there all night. It works fast. Side effects include jaw pain, bite changes, and excessive salivation during the first month. A dentist who understands sleep medicine is required, not a general dentist fitting a generic boil-and-bite guard from Amazon.
How I Approach This Clinically
I usually start with a diagnostic question rather than a treatment recommendation. What is the AHI? What is the apnea type? What is the patient's BMI and neck circumference? The answers determine whether oral therapy is even worth attempting. An AHI above fifteen with significant desaturations needs PAP therapy first. Everything below that threshold is where orofacial options become reasonable. The most overlooked factor is nasal obstruction. I had a patient last year who was failing every oral appliance I tried. Mandibular advancement of six millimeters should have been enough for his mild-moderate AHI, but he kept dislodging the device because he was mouth breathing through a deviated septum. We referred him for septoplasty first, re-fitted the appliance two months later, and his AHI dropped from eleven point four to three point two. The therapy was fine. The nasal blockage was the actual problem all along. That is the pattern I see repeatedly. Oral therapy fails not because the approach is wrong but because an upstream anatomical issue was never addressed. Nasal congestion from allergies, enlarged turbinates, or structural deviations will undermine every oral intervention.
Get the Full Details

Palpation of the submental muscles is another clinical step that gets skipped. I press along the mylohyoid and geniohyoid while the patient swallows. If those muscles show significant weakness or hypertonicity, myofunctional exercises need to target them specifically rather than using generic tongue drill protocols. Generic protocols work about half the time. Targeted protocols work more often but require someone who knows what they are doing.
Practical Setup for Myofunctional Therapy
The exercise routine takes about twelve minutes per day. I prescribe this sequence for most patients starting out: Tongue slide: press the full tongue surface against the hard palate and slide back and forth for sixty seconds. This strengthens the genioglossus and reduces posterior tongue collapse. Do this morning and evening. Soft palate elevation: repeat the "kah" soundly and slowly for ninety seconds while focusing on lifting the soft palate. This is harder to isolate than it sounds. Most people just swallow forcefully. You know it is working when you feel the vibration shift away from the throat.
Resistive phonation: hum while gently pinching the nose closed for thirty seconds, rest, repeat five times. This increases positive airway pressure awareness and trains the pharyngeal dilators. Pursed-lip breathing: inhale through the nose for four counts, exhale through pursed lips for six counts, repeat for three minutes. This reduces pharyngeal collapse tendency during exhalation and improves CO2 tolerance, which is often lower than expected in apnea patients. Chewing resistance: chew sugar-free gum for ten minutes daily, focusing on keeping the tongue positioned against the palate rather than allowing it to fall back. Most patients do not realize their tongue drops backward during mastication until I point it out.
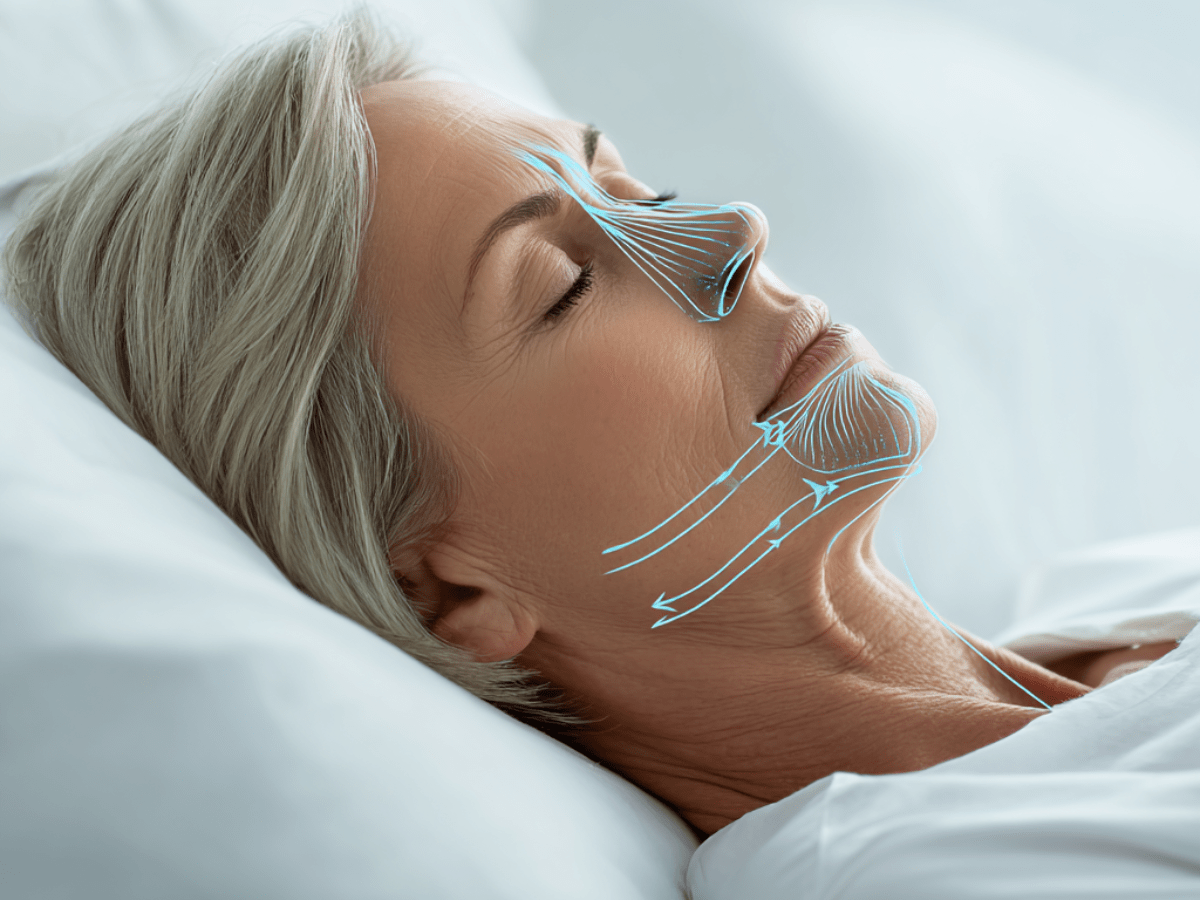
Expect a four to eight week window before any measurable improvement in snoring or daytime sleepiness. AHI changes take longer to detect without a follow-up sleep study. Portable home monitoring units can track trends but cannot replace a formal study for initial diagnosis or treatment verification.
Common Failures and What To Do Instead
Orofacial Therapy For Sleep Apnea has clear failure modes that patients rarely read about. The biggest is assuming these therapies work for every anatomical profile. They do not. Patients with significantly retrognathic jaws, extremely large tonsils, or massive soft palate tissue often need surgical intervention or PAP regardless of how well they perform exercises. The therapy cannot restructure bone or remove tissue. Another failure is combining too many devices at once. I had a patient who started a MAD, a tongue retainer, and mouth tape simultaneously and developed TMJ pain within two weeks. Each device shifts the occlusion slightly. Stacking them multiplies the joint load. Start with one intervention, assess for four weeks, then add another if needed. Weight loss and alcohol reduction remain the highest-impact adjuncts. A ten percent body weight reduction can lower AHI by up to fifty percent in obese patients. Alcohol relaxes pharyngeal muscles and increases collapse events by roughly thirty percent per standard drink consumed within three hours of bedtime. Oral therapy works better when these two factors are managed, but most patients skip them because the therapy seems like a shortcut. It is not.
Positional therapy is worth mentioning because it pairs well with oral approaches. Many patients with mild OSA only apnea when supine. A simple tennis ball sewn into the back of a shirt or a dedicated positional wearable can eliminate the majority of events for these patients. Combining positional therapy with myofunctional exercises produced better outcomes than either alone in a 2023 study published in Sleep Medicine, though the sample size was small. Device-based options like the Hypoglossal Nerve Stimulation implant represent a different tier entirely. These are surgical, expensive, and reserved for moderate to severe cases that fail CPAP. They are not part of standard orofacial therapy but are worth knowing about as an escalation path when conservative measures exhaust their effectiveness.

When to Stop and Escalate
If AHI does not decrease after eight weeks of consistent exercise and correct device use, it is time to reassess rather than continue blindly. Repeat a sleep study or at least a home test. Check for weight gain, new medications that cause sedation or muscle relaxation, and alcohol pattern changes. Often the therapy was working initially and something else reversed the gains rather than the therapy itself failing. jaw pain, headaches, or bite changes from an oral appliance warrant immediate discontinuation and a professional evaluation. Dental complications from mandibular advancement devices can become permanent if ignored past the three month mark. Early adjustment is straightforward. Late adjustment often requires remaking the device entirely. The bottom line is practical and unglamorous. Orofacial Therapy For Sleep Apnea is a real category with real evidence behind it, but it is neither universal nor effortless. It requires diagnosis, correct selection, patience, and a willingness to adjust the plan when the first option underperforms. The patients who succeed are usually the ones who treat it as a structured protocol rather than a product they buy and hope fixes everything.