
Writing Orthodontic Exam Questions And Answers That Actually Test Clinical Competence
The problem with most orthodontic exam study materials I see is that they prioritize recall over reasoning. You will find dozens of flashcard sets and PDF dumps online that list questions like "What is the Angle classification of Class II division 1?" with a one-line answer. That is not enough to pass the orthodontic board exams or the final professional certification. The questions you actually need to be prepared for require you to weigh trade-offs, read cephalometric values, and make decisions under uncertainty. I spent years building these materials for my students, and I learned the hard way what separates a useful set from noise. I once had a student who memorized every standard question about Nance appliance contraindications and still failed the viva. The examiner asked a modified version of a textbook question: "A 13-year-old patient presents with a deep bite, increased lower facial height, and a skeletal Class II tendency with hyperdivergent growth pattern. Would you recommend a Nance holding arch for molar distalization? Why or why not?" My student had the textbook answer perfectly memorized, but could not adapt it to the clinical scenario. The answer involves recognizing that in a hyperdivergent patient, intrusion of the molars can worsen the lower facial height and rotate the mandible clockwise. A Nance is not absolutely contraindicated, but it requires careful consideration of the growth pattern and the mechanics involved. This is exactly the kind of question that tripped him up.
Common Orthodontic Exam Questions And Answers
Below is a selection of the types of questions I see tested repeatedly across programs and licensing boards. I am not going to give you a simple Q-and-A dump. Instead I will frame each question with the reasoning you need to follow when you encounter it. Question: A patient presents with a skeletal Class III pattern, dental compensation present, mild crowding, and a negative overjet of 4mm. The patient is 16 years old. What is the most appropriate treatment approach? Answer framework: At 16, maxillary growth is nearly complete. Maxillomandibular disharmony of this magnitude with negative overjet suggests either surgical correction or camouflage. If the patient is not a surgical candidate, dental camouflage with a Class III elastics and possibly upper premolar extractions with lower incisor proclination may be attempted. However, the key decision point is assessing whether the skeletal discrepancy is mild, moderate, or severe. A negative overjet of 4mm at this age typically falls into the moderate-to-severe range where surgery should be discussed. The exam is testing whether you know the age-related growth limits and the indications for camouflage versus orthognathic surgery.
Question: Explain the biological mechanism by which light continuous force produces more efficient tooth movement than heavy force.
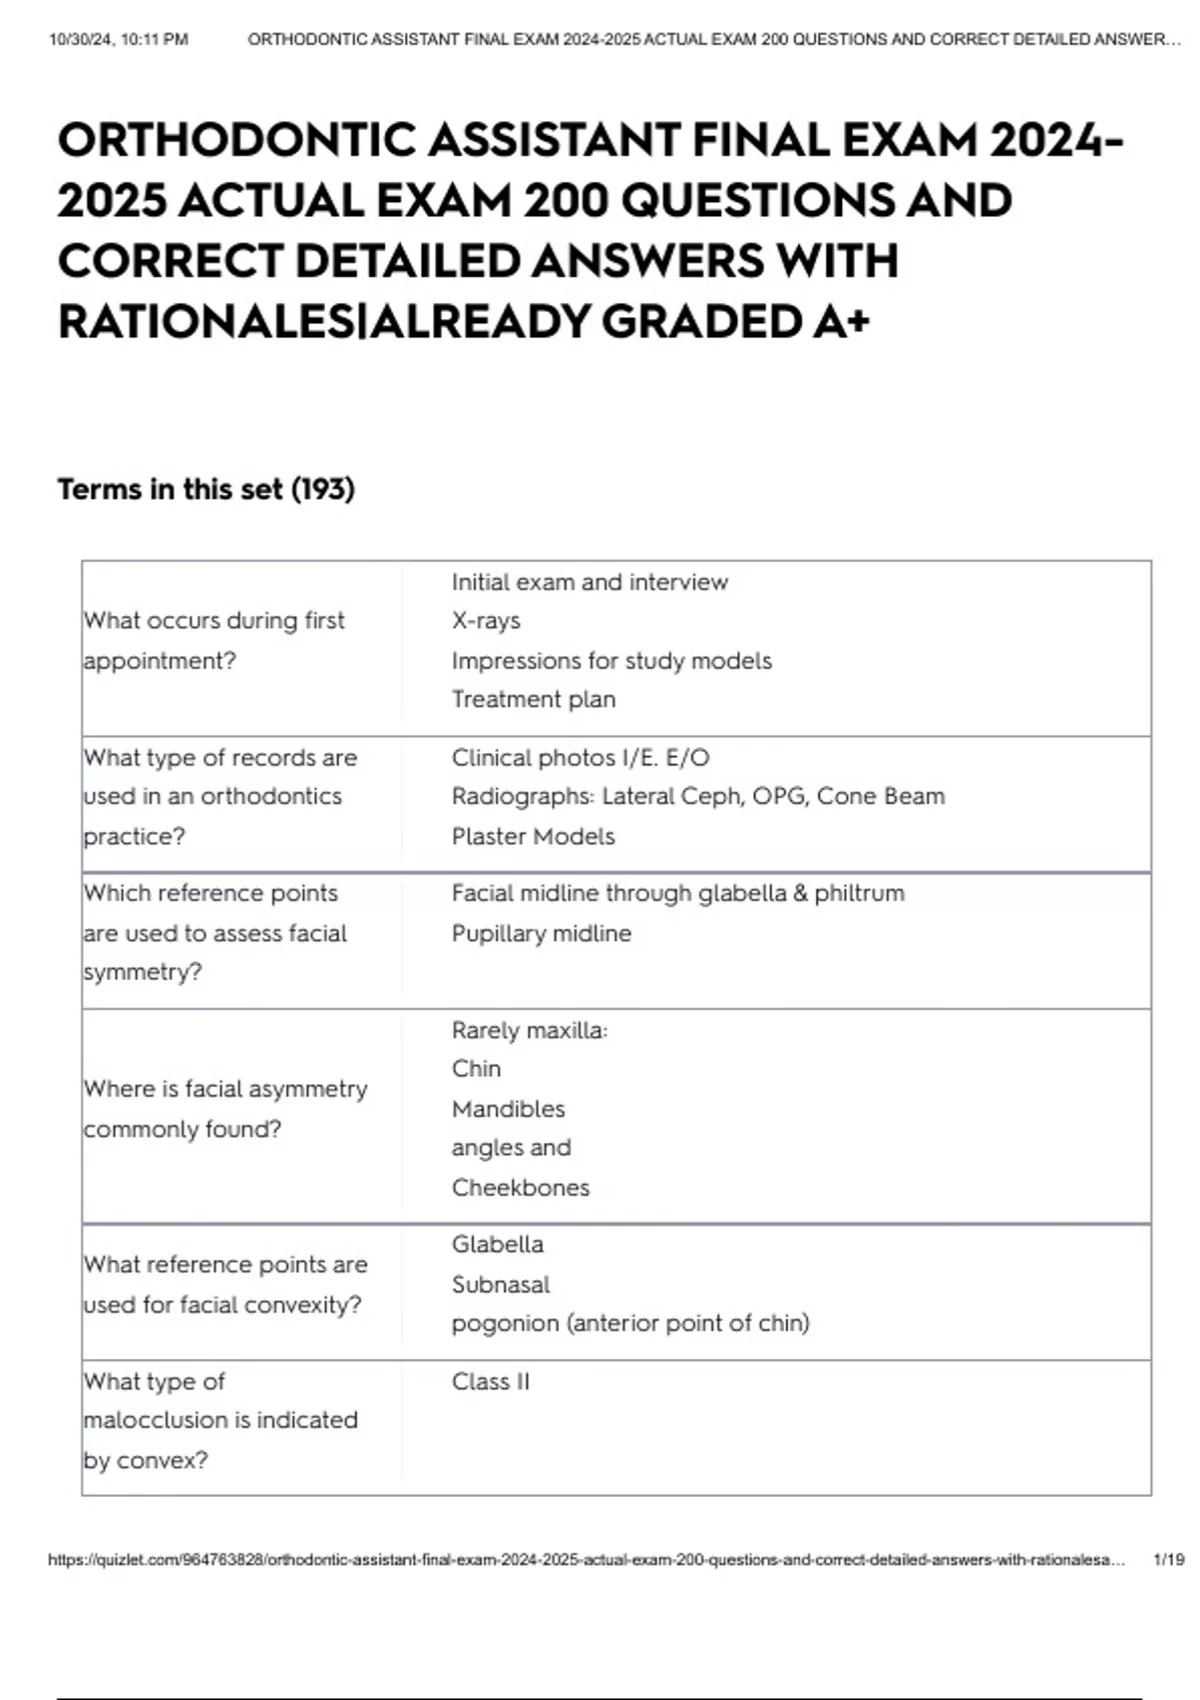
Get the Full Details
Answer framework: Light force creates controlled hyalinization at the pressure side of the periodontal ligament. This leads to direct bone resorption by osteoclasts arising from the marrow spaces adjacent to the hyalinized zone. Heavy force causes extensive hyalinization that eliminates the cell-rich perivascular space entirely. Under heavy force, the cells that would become osteoclasts are cut off from their blood supply and must migrate from distant marrow spaces. This creates a delay in tooth movement known as lag phase. The exam often wants you to mention Reimer Schwarz's work on optimal force levels and the distinction between immediate vs. delayed response. A good answer also references the ideal force range for molar distalization (approximately 150-200g per side) versus incisor retraction. Question: A patient undergoing orthodontic treatment develops root resorption on the maxillary lateral incisors. What factors contribute to this and how do you manage it? Answer framework: Root resorption in orthodontics is multifactorial. The lateral incisors are particularly susceptible due to their anatomical position and root morphology. Contributing factors include excessive force, prolonged treatment duration, individual genetic predisposition, and the direction of movement. Extrusive movements tend to cause more resorption than intrusive movements. Managing this requires discontinuing the active movement causing the stress, taking a periapical radiograph to assess severity, and allowing a repair phase before resuming treatment. Mild to moderate external apical root resorption affects approximately 85% of patients to some degree after comprehensive treatment, but clinically significant resorption requiring intervention occurs in about 1-5% of cases. The exam wants you to demonstrate you understand both the etiology and the monitoring protocol.
Question: Compare the advantages and disadvantages of mini-implants versus temporary anchorage devices in orthodontic treatment. Answer framework: The terminology itself is confusing because mini-implants are a type of temporary anchorage device. All mini-implants are TADs, but not all TADs are mini-implants. TADs include miniscrews, miniplates, and transmucosal attachments. Mini-implants (microscrews) are inserted directly into the bone and provide absolute anchorage. Their advantages include minimal patient discomfort, easy insertion and removal, and surgical flap reflection. The disadvantage is that they have a higher failure rate in the maxillary posterior region due to lower bone density. Miniplates require a surgical flap and are placed in areas of denser bone, providing superior retention but at the cost of a more invasive procedure. In my practice, I found that placing mini-implants in the paramedian palate between the roots of the maxillary premolars and molars gives the best stability with the lowest failure rate. The failure rate in this location is approximately 5-10%, compared to 15-20% in the interradicular maxillary alveolus.
How to Structure Your Study Approach
Most students approach orthodontic exam preparation the same way: they read the textbook, make flashcards, and repeat until the information sticks. This works for the basic recall questions. It does not work for the clinical application sections that carry the most weight in board examinations. Here is what actually works based on what I have observed over many cycles of teaching and reviewing exam performance. Start with the cases. Before you open any review book, work through real clinical cases from your own experience or from published case reports. When you encounter a case, write down every decision you would make and the rationale for each one. This builds the decision-making muscle that the exam tests. The exam questions are not asking what you know. They are asking what you would do in a specific clinical situation. For the biomechanics section, do not memorize formulas. Understand the physics. If you understand the center of rotation, the center of resistance, and the moment-to-force ratio, you can derive the answer to almost any force system question without having seen it before. A couple of specific values you must know cold: the MFR for translation is 10:1, for control of tipping it is 7:1, and for root movement it is approximately 5:1. These numbers are frequently tested directly.

For the growth and development portion, focus on the cephalometric norms and their variations by age and sex. The Steiner analysis, Tweed analysis, and Ricketts analysis each have different normal values. Know which norm applies to which analysis. A common pitfall is mixing up the SNA angle norms across different systems. Steiner considers 82 degrees normal for SNA, while Ricketts uses a different reference plane. This distinction matters when you are interpreting a cephalometric tracing in an exam.
Pitfalls That Cost Students the Exam
I have watched capable students fail orthodontic exams for reasons that had nothing to do with their technical knowledge. The most common mistake is answer choice selection under time pressure. The written portion often has a time limit that forces quick decisions. Students who rush through the questions without carefully reading each stem lose points on questions that are straightforward. Read the question twice before selecting an answer. Pay attention to qualifiers like "most likely," "first step," "contraindicated," and "best." These words change the correct answer entirely. Another frequent error is overthinking clinical management questions. Students sometimes choose an overly complex treatment plan when a simpler approach would be equally appropriate. The exam is testing whether you can apply the principle of least interference. Start with the least invasive option and escalate only if indicated. This is a core tenet of evidence-based orthodontics and it shows up repeatedly on the boards. There is also a persistent misconception about the necessity of pre-extraction imaging. Some students believe that panoramic radiographs alone are sufficient for all orthodontic cases. This is incorrect. A panoramic radiograph provides limited information about the apical structures and the temporomandibular joints. A posteroanterior cephalogram, a lateral cephalogram, and a panoramic radiograph form the minimum imaging standard for comprehensive orthodontic diagnosis. CBCT is not routinely indicated unless there is a specific clinical question about impaction, root resorption, or asymmetry that cannot be answered with conventional imaging. This is a nuanced point that many students miss.
Resources I Recommend
The textbooks that consistently produce the best results among my students are Proffit's Contemporary Orthodontics for the foundational concepts, Graber's Orthodontics for the comprehensive reference, and the Board Review sections from the AAOP candidate handbooks for the exam-specific preparation. For clinical case practice, the Journal of Clinical Orthodontics and the American Journal of Orthodontics and Dentofacial Orthopedics publish case studies that mirror the style of board examination scenarios. I do not recommend relying exclusively on question banks or commercial review courses. These materials are useful for identifying knowledge gaps, but they often present questions in isolation without the clinical context that the real exam requires. Use them as supplements, not as your primary study tool. The best preparation comes from working through actual patient cases and writing out your diagnostic and treatment reasoning in detail. If you want a downloadable compilation of high-yield questions organized by topic, the Orthodontic Resident Matching Program provides a question bank that aligns closely with the content outline used by the certification boards. The American Board of Orthodontics also publishes a candidate handbook with sample questions. These are the most authoritative sources available. Beyond those, the peer-reviewed literature is where you will find the clinical reasoning that distinguishes a competent practitioner from someone who can only recite facts.

Orthodontic Exam Questions And Answers for Last-Minute Review
Here are some of the highest-yield single-topic questions that appear with regular frequency across different exam administrations. These are not exhaustive, but they cover the topics where students most commonly lose points. What is the most common side effect of fixed appliance therapy? Decalcification and white spot lesions. This occurs in approximately 60-70% of patients who undergo fixed appliance treatment when oral hygiene is suboptimal. Prevention requires rigorous home care instructions and fluoride application at each adjustment visit.
What is the ideal overjet and overbite for a Class I occlusion? Overjet of 2-3mm and overbite of 20-30% of the clinical crown height of the mandibular incisors. These values are considered within the normal range and are frequently cited in both diagnosis and treatment outcome assessments. When is the best time to extract first premolars for orthodontic purposes?
There is no single ideal timing. The decision depends on the patient's growth status, the severity of crowding, and the treatment plan. In general, extraction of first premolars is most commonly performed between ages 10 and 14, during the mixed or early permanent dentition stage. This allows for optimal space closure and anchorage control during the active treatment phase. What is the primary advantage of clear aligner therapy over fixed appliances? The ability to remove the appliance for eating and oral hygiene, combined with better aesthetic acceptance and fewer emergency visits. However, clear aligners have limitations in achieving certain types of movements, particularly molar rotation and significant vertical control. The exam may test your understanding of when aligner therapy is appropriate versus when fixed appliances are necessary.

The reality of orthodontic exam preparation is that no amount of memorization will substitute for clinical reasoning. The questions are designed to separate students who understand the material from students who have simply studied for the test. Focus on building your diagnostic skills, practice writing out your reasoning for each clinical decision, and use question banks as a supplement rather than a crutch. That is the approach that consistently produces passing scores and, more importantly, competent practitioners.

