The Practical Reality of Getting Orthopedic Physical Exam Documentation Right
Most clinicians treat documentation as an afterthought. They finish the exam, then rush through paperwork while still thinking about their next patient. This approach works fine until an auditor, a billing review, or a legal query shows up and your notes don't hold up to scrutiny. I have spent years watching people get tripped up by exactly this, and the fix is not complicated. It is just something most people skip because it feels tedious in the moment.Orthopedic Physical Exam Documentation: What Actually Matters
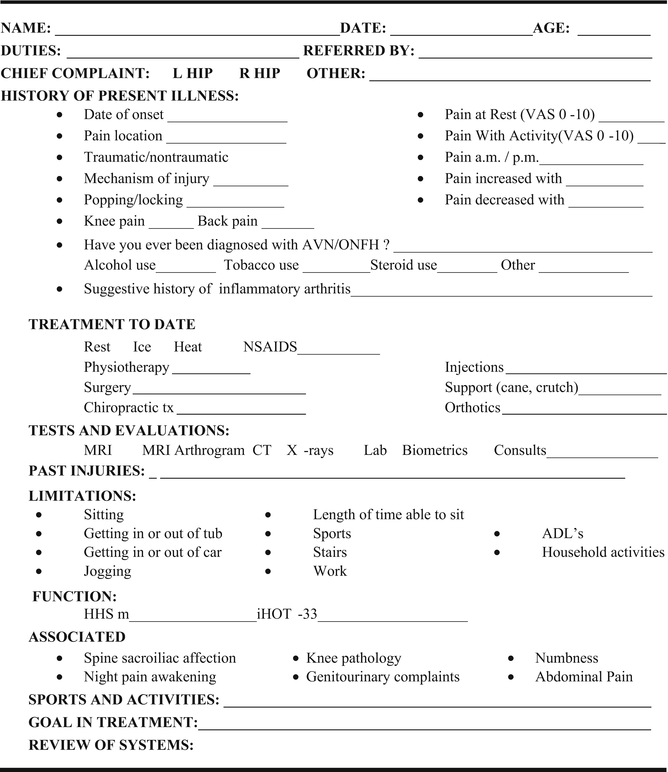
Orthopedic Physical Exam Documentation is not a creative writing exercise. It is a structured record that must survive repeated examination by people who are looking for reasons to reject it. The core elements are straightforward. You document the patient's chief complaint and mechanism of injury with enough specificity that another provider could understand what happened without calling you. You record the inspection findings, range of motion measurements with goniometric angles, ligamentous stress testing results with grade and endpoint characterization, special tests with sensitivity and specificity noted where relevant, and neurovascular status. That is the skeleton. Everything else is detail. The part that gets people in trouble is the special test section. Beginners tend to write things like "positive Lachman" and move on. A positive Lachman without documenting the degree of translation, the quality of the endpoint, and whether it was asymmetric compared to the contralateral side is essentially worthless in a review. I have seen charts pulled for exactly that reason. The workaround is to build a template that forces you to fill in translation amount (in millimeters), endpoint quality (firm, soft, absent), and side-to-side comparison before you can close the note. It adds about twenty seconds per exam and saves you from three hours of retrospective damage control. Range of motion is another area where people cut corners. Writing "ROM WFL" is not documentation. It is an abbreviation that means nothing to anyone who was not in the room. You need active and passive ranges for each relevant joint, recorded in degrees, with any pain or compensation noted at the end range. If a patient has 120 degrees of shoulder flexion with scapular hiking beginning at 90, that matters. If you write "ROM WFL," that scapular dyskinesis disappears from the record entirely and becomes a gap an auditor will notice.
Countering the Easy Assumptions
Here is something that is not obvious to most people entering this field. More detailed documentation does not automatically mean better documentation. I once spent two weeks tracking down a discrepancy in a peer's charts. The notes were voluminous but internally inconsistent. The text described a grade II ACL sprain with a soft endpoint, but the special test section said firm endpoint with no anterior translation. A reasonable reviewer would assume the provider was confused about the diagnosis itself. Precision without consistency is worse than brevity with accuracy. I now check my own notes for internal consistency before signing them, specifically cross-referencing the special test results against the diagnosis section. If they do not align, I rewrite the note rather than leaving the contradiction in place. Another common blind spot is the failure to document normal findings in context. When an exam is entirely unremarkable, some clinicians write "normal musculoskeletal exam" and move on. This is insufficient because it provides no basis for the conclusion. A defensible normal exam note specifies which structures were tested and what the results were. "No joint effusion, edema, or erythema observed. Ligamentous testing stable bilaterally. ROM full and pain-free. Neurovascular intact distally." That is the difference between a note that stands up and one that raises questions about whether the exam was actually performed.
A Real Problem I Ran Into and How I Handled It
Last year I was reviewing a case involving a patient who had sustained a lateral ankle injury. The initial documentation from an outside provider listed "positive anterior drawer test" and diagnosed an ankle instability, but the note did not specify which talar tilt values were obtained, whether the stress was applied in plantarflexion or dorsiflexion, or what the endpoint felt like. When the case moved to a second opinion, the lack of these details made it impossible to confirm whether the original diagnosis was accurate. The patient's symptoms persisted and treatment decisions were delayed by several weeks. The workaround was to create a standardized ankle examination template that requires specific fields for anterior drawer and talar tilt testing, including position, grade, and endpoint characterization. I also added a mandatory fields checklist that flags when any special test is recorded as positive without the required corroborating detail. This has not eliminated every problem, but it has significantly reduced the number of incomplete charts that come back for revision.
Get the Full Details

Limitations You Need to Accept
No documentation system is perfect, and acknowledging the weaknesses prevents them from catching you off guard. Structured templates reduce variability but they also create a false sense of completeness. A form can be filled out correctly while the underlying exam was inadequate. Templates do not verify that you actually tested what you claim to have tested. The only reliable check is having a second clinician review a sample of your notes monthly, looking specifically for gaps between the documented findings and what the clinical picture actually supports. Another limitation is the time investment. Building thorough Orthopedic Physical Exam Documentation takes longer than the shorthand most people default to. In a high-volume clinic, this can be a genuine bottleneck. The trade-off is between speed now and defensibility later. If your practice volume makes comprehensive documentation unsustainable, the alternative is to delegate the documentation process to trained scribes who are supervised by the examining clinician. This shifts the time cost but does not eliminate it. There is no free lunch here. Electronic health record systems also introduce their own problems. Default templates from vendors are often generic and may not include the specific fields that matter for orthopedic specialty practice. Customizing them requires initial setup time and ongoing maintenance as the system updates. I have seen practices abandon customization efforts after six months because the IT department refused to support changes to the template structure. If you go this route, lock in your template configuration early and document the rationale so that the next person inheriting the system understands why each field exists.
What to Focus On First
If you are starting from scratch or rebuilding your documentation practice, do not try to fix everything at once. Pick the three areas where your notes are currently weakest and address those first. For most clinicians I work with, this is special test documentation, range of motion recording, and the narrative summary that ties findings to diagnosis. Once those are consistent, add the remaining elements. Trying to overhaul an entire documentation system in a single week usually fails because the new process competes with your existing workflow and neither gets done properly. The metrics that matter are simple. After implementing better documentation practices, track how often your charts are returned for additional information, how frequently billing audits result in requests for clarification, and whether peer reviewers can reconstruct your clinical reasoning from the notes alone without asking you questions. These are the indicators that tell you whether your approach is working. If the numbers are improving, continue. If they are not, adjust the specific sections that are not contributing rather than abandoning the entire system.




