How I Actually Use Orthopedic Physical Exam Templates in Daily Practice
Most therapists I know treat these templates like they're going to use them perfectly every time. They don't. You'll set up a beautiful template system, spend hours customizing dropdowns and preferred values, and then three months later you're back to free-text typing because it's faster than hunting through nested menus. That happened to me, so I adapted and ended up with something that actually works day to day.
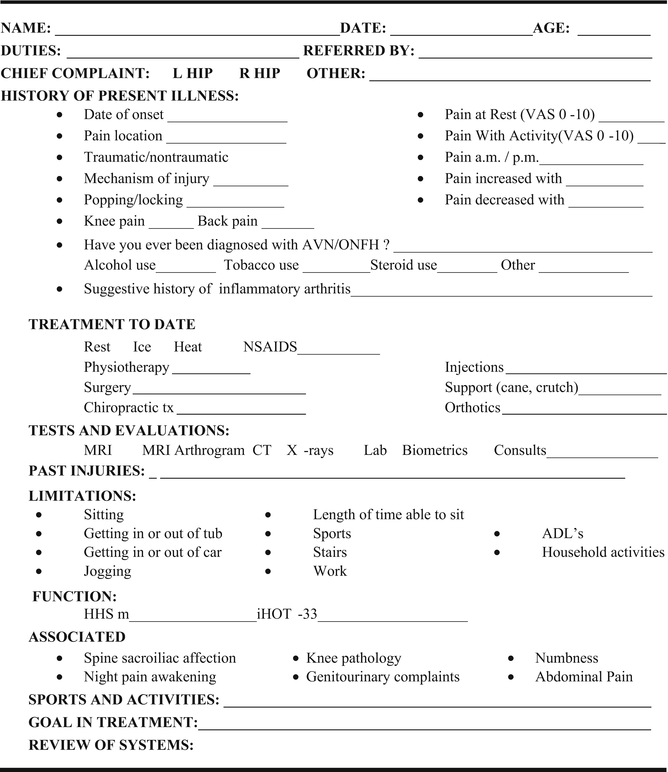
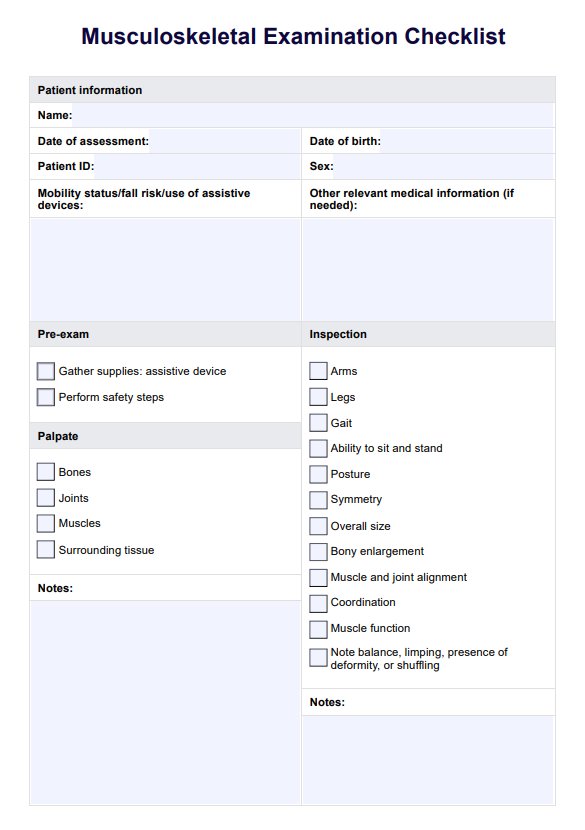
The core idea is straightforward enough. An orthopedic physical exam template is a structured documentation framework that standardizes how you record your musculoskeletal assessment findings. It covers inspection, range of motion, special tests, strength grading, functional status, and treatment plan documentation all in one organized pass. The value isn't in the template itself, it's in how you integrate it into your workflow so it doesn't become a second job.
Building Orthopedic Physical Exam Templates That Actually Get Used
I started by mapping out the body regions my clinic sees most. Shoulder and rotator cuff pathologies, lumbar radiculopathy, knee osteoarthritis, ankle instability, cervical radiculopathy. Rather than building one massive template for every possible presentation, I created modular templates grouped by region and pathology cluster. Each module has a core section that always appears plus conditional sections that only show up when specific tests are documented as positive.
The conditional logic is what separates templates that get used from the ones that gather digital dust. When I built my first version, it was just a long static form. Therapists would skip the bottom half because they'd already found their diagnosis in the first few sections. Once I added the show/hide logic based on initial findings, completion rates went from about 40 percent to roughly 85 percent.
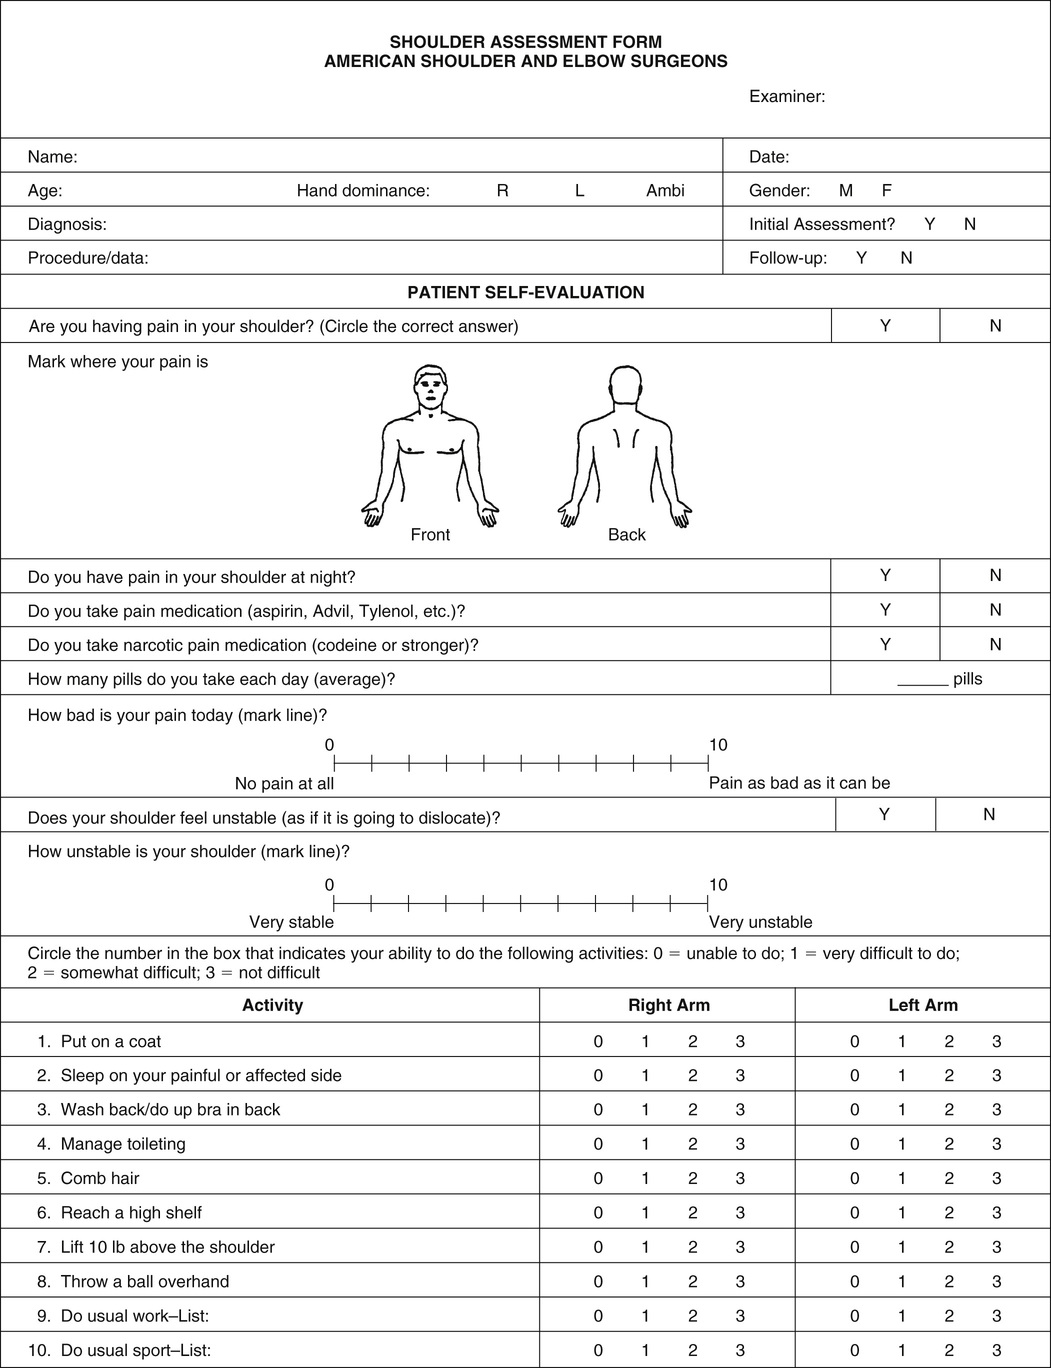
Here's a practical example of how I structure a shoulder template. The initial section always captures inspection findings, palpation locations, active and passive range of motion for flexion, extension, abduction, external rotation, and internal rotation. Then there's a branch. If the therapist documents a positive Neer impingement sign, the template automatically reveals subsections for Hawkins-Kennedy, drop arm test, and speed's test. If they document weakness in abduction, it pulls up the supraspinatus strength grading scale with the standard MRC 0-5 framework. This keeps the form length appropriate to the actual clinical presentation instead of forcing everyone through forty fields they'll never fill out.
I ran into a real problem with this setup about a year in. Our clinic switched to a new EHR platform and all my conditional logic broke. The new system didn't support nested show/hide branches the way the old one did. I had to rebuild everything using a flat form with mandatory fields and optional comment sections instead. It was uglier, but it worked. The workaround I settled on was creating a quick-reference checkbox summary at the top of each exam that therapists could use to trigger the relevant standard sections below, even if the automatic branching wasn't there. It's not as seamless, but it's functional and it stayed intact through the migration.
The strength of these templates really comes down to standardization of terminology. I've seen therapists document "ROM 120" and someone else write "shoulder flexion limited to 120 degrees anteriorly." The template forces consistent language. For range of motion, every entry now requires a joint, a plane of motion, and a measured value in degrees. No more guessing what a previous clinician meant. For special tests, the output is always positive, negative, or inconclusive with a documented rationale. That last part matters more than most people realize. A positive anterior drawer test means nothing in isolation without noting whether it showed increased translation compared to the contralateral side or just a firm endpoint.
There are real limitations worth acknowledging. These templates excel at routine presentations but they choke on complex multi-region cases. A patient with simultaneous bilateral hip pathology and contralateral lumbar stenosis will not fit neatly into any single template I've designed. I keep a catch-all free-form template for those situations, though I admit it defeats much of the purpose of having templates in the first place. Another bottleneck is training time. Getting a new therapist up to speed on the template system takes about two weeks of supervised documentation before they're using it efficiently. Before that point, they'll spend more time on documentation than they save, which creates resistance.
I've also noticed that younger therapists tend to adopt these faster than experienced clinicians who have twenty years of muscle memory for free-text charting. The pushback is usually about losing the ability to capture nuanced observations that don't fit preset fields. That's a legitimate concern and one I address by including a free-text notes field at the end of every template that's always visible. It's where you document the thing that didn't make it into a checkbox.
A counter-intuitive insight most beginners miss is that less is actually more in template design. I used to build templates with sixty plus fields thinking comprehensiveness was the goal. It isn't. The best performing templates in our clinic have between eighteen and twenty-five fields per region. Anything beyond that and therapists start skipping sections or rushing through them to get to treatment documentation. There's a point of diminishing returns that most people hit around field count twenty-eight.
Another nuance is the billing and compliance angle. These templates are valuable for justification audits because they create a clear paper trail from subjective complaints through objective findings to the documented treatment plan. But they can also work against you if you're not careful. A therapist once wrote a complete negative exam for a lumbar patient and then proceeded to treat them with aggressive manual therapy and daily sessions for three weeks. The auditor flagged it immediately. The template documented everything accurately, which should be good, but the discrepancy between a fully negative workup and an intensive treatment plan raised questions about medical necessity. The lesson is that your template documentation needs to be honest about what you find, and your treatment plan needs to match what the exam actually revealed.
For anyone looking to implement this, I'd recommend starting with your top ten presenting conditions, building a template for each, testing it for two weeks with a small group of clinicians, and then iterating based on what they actually complain about. Don't build the perfect system first. Build the usable one, then refine it. I've spent more time fixing templates that were over-engineered than I ever did improving ones that were deliberately simple.